


Prescribing information (package insert) - Tukysa
WARNING: HEPATOTOXICITY
- TUKYSA can cause severe and fatal hepatotoxicity, particularly after rechallenge [see Warnings and Precautions (5.1)].
- Obtain liver function tests before initiation and during treatment with TUKYSA. Withhold, reduce dose, or permanently discontinue TUKYSA as recommended based on severity of hepatotoxicity [see Dosage and Administration (2.3) and Warnings and Precautions (5.1)].
1 INDICATIONS AND USAGE
1.1 Unresectable or Metastatic Breast Cancer
Maintenance Treatment of HER2-Positive Breast Cancer
TUKYSA is indicated in combination with trastuzumab and pertuzumab for the maintenance treatment of adult patients with unresectable locally advanced or metastatic HER2-positive breast cancer following induction treatment.
HER2-Positive Breast Cancer
TUKYSA is indicated in combination with trastuzumab and capecitabine for treatment of adult patients with advanced unresectable or metastatic HER2-positive breast cancer, including patients with brain metastases, who have received one or more prior anti-HER2-based regimens in the metastatic setting.
1.2 Unresectable or Metastatic Colorectal Cancer
TUKYSA is indicated in combination with trastuzumab for the treatment of adult patients with RAS wild-type, HER2-positive unresectable or metastatic colorectal cancer that has progressed following treatment with fluoropyrimidine-, oxaliplatin-, and irinotecan-based chemotherapy.
This indication is approved under accelerated approval based on tumor response rate and durability of response [see Clinical Studies (14.2)]. Continued approval for this indication may be contingent upon verification and description of clinical benefit in confirmatory trials.
2 DOSAGE AND ADMINISTRATION
2.1 Patient Selection
Select patients for treatment of unresectable or metastatic colorectal cancer with TUKYSA based on the presence of:
- HER2 overexpression or gene amplification [see Clinical Studies (14.2)]. FDA-authorized tests for the detection of HER2 overexpression and gene amplification in patients with unresectable or metastatic colorectal cancer are not currently available, and
- RAS wild-type [see Clinical Studies (14.2)]. Information on FDA-authorized tests for the detection of RAS mutations in patients with unresectable or metastatic colorectal cancer is available at http://www.fda.gov/CompanionDiagnostics.
2.2 Recommended Dosage
The recommended dosages for TUKYSA are listed in Table 1.
Table 1: Recommended Dosage
| Indication | Recommended TUKYSA Dosage | Duration of Therapy |
Unresectable or Metastatic Breast Cancer Maintenance Treatment of HER2‑Positive Breast Cancer | 300 mg orally twice daily in combination with trastuzumab and pertuzumab. Refer to the Prescribing Information of combination agents for dosing and administration information. | Until disease progression or unacceptable toxicity. |
Unresectable or Metastatic Breast Cancer HER2-Positive Breast Cancer | 300 mg orally twice daily in combination with trastuzumab and capecitabine. When given in combination with TUKYSA, the recommended dosage of capecitabine is 1000 mg/m2 orally twice daily taken within 30 minutes after a meal. TUKYSA and capecitabine can be taken at the same time. | Until disease progression or unacceptable toxicity. |
| Unresectable or Metastatic Colorectal Cancer | 300 mg orally twice daily in combination with trastuzumab. | Until disease progression or unacceptable toxicity. |
Administration Instructions
Advise patients to swallow TUKYSA tablets whole and not to chew, crush, or split prior to swallowing. Advise patients not to ingest a tablet if it is broken, cracked, or not otherwise intact.
Advise patients to take TUKYSA approximately 12 hours apart and at the same time each day with or without a meal [see Clinical Pharmacology (12.3)].
If the patient vomits or misses a dose of TUKYSA, instruct the patient to take the next dose at its usual scheduled time.
2.3 Dosage Modifications for Adverse Reactions
The recommended TUKYSA dose reductions and dosage modifications for adverse reactions are provided in Tables 2 and 3. Refer to the Prescribing Information of combination agents for information about dosage modifications for these drugs.
Table 2: Recommended TUKYSA Dose Reductions for Adverse Reactions
| Dose Reduction | Recommended TUKYSA Dosage |
| First | 250 mg orally twice daily |
| Second | 200 mg orally twice daily |
| Third | 150 mg orally twice daily |
Permanently discontinue TUKYSA in patients unable to tolerate 150 mg orally twice daily.
Table 3: Recommended TUKYSA Dosage Modifications for Adverse Reactions
| Abbreviations: ALT = alanine aminotransferase; AST = aspartate aminotransferase; ULN = upper limit of normal. | ||
| Adverse Reaction Grades based on National Cancer Institute Common Terminology Criteria for Adverse Events Version 4.03. | Severity | TUKYSA Dosage Modification |
| Hepatotoxicity [see Warnings and Precautions (5.1)] | ALT or AST >3 × ULN AND Bilirubin >2 × ULN | Permanently discontinue TUKYSA. |
ALT or AST >3 × ULN AND Bilirubin > ULN to ≤2 × ULN | Repeat testing within 48-72 hours to determine if worsening. | |
| Grade 2 bilirubin (>1.5 to 3 × ULN) | Hold TUKYSA until recovery to ≤ Grade 1, then resume TUKYSA at the same dose. | |
| Grade 3 ALT or AST (>5 to 20 × ULN) | Hold TUKYSA and repeat testing within 48-72 hours to determine if worsening. Consider permanent discontinuation or hold until recovery to ≤ Grade 1, then resume TUKYSA at the next lower dose. Permanently discontinue TUKYSA for recurrent Grade 3 ALT or AST. | |
| Grade 3 bilirubin (>3 to 10 × ULN) | Hold until recovery to ≤ Grade 1, then resume TUKYSA at the next lower dose. | |
Grade 4 ALT or AST (>20 × ULN) OR Grade 4 bilirubin (>10 × ULN) | Permanently discontinue TUKYSA. | |
| Diarrhea [see Warnings and Precautions (5.2)] | Grade 3 without antidiarrheal treatment | Initiate or intensify appropriate medical therapy. Hold TUKYSA until recovery to ≤ Grade 1, then resume TUKYSA at the same dose. |
| Grade 3 with antidiarrheal treatment | Initiate or intensify appropriate medical therapy. Hold TUKYSA until recovery to ≤ Grade 1, then resume TUKYSA at the next lower dose. | |
| Grade 4 | Permanently discontinue TUKYSA. | |
| Other adverse reactions [see Adverse Reactions (6.1)] | Grade 3 | Hold TUKYSA until recovery to ≤ Grade 1, then resume TUKYSA at the next lower dose. |
| Grade 4 | Permanently discontinue TUKYSA. | |
2.4 Dosage Modifications for Severe Hepatic Impairment
For patients with severe hepatic impairment (Child-Pugh C), reduce the recommended dosage to 200 mg orally twice daily [see Use in Specific Populations (8.7), Clinical Pharmacology (12.3)].
2.5 Dosage Modifications for Concomitant Use with Strong CYP2C8 Inhibitors
Avoid concomitant use of strong CYP2C8 inhibitors with TUKYSA. If concomitant use with a strong CYP2C8 inhibitor cannot be avoided, reduce the recommended dosage to 100 mg orally twice daily. After discontinuation of the strong CYP2C8 inhibitor for 3 elimination half-lives, resume the TUKYSA dose that was taken prior to initiating the inhibitor [see Drug Interactions (7.1), Clinical Pharmacology (12.3)].
3 DOSAGE FORMS AND STRENGTHS
Tablets:
- 50 mg: round, yellow, film-coated, debossed with “TUC” on one side and “50” on the other side.
- 150 mg: oval-shaped, yellow, film-coated, debossed with “TUC” on one side and “150” on the other side.
4 CONTRAINDICATIONS
None.
5 WARNINGS AND PRECAUTIONS
5.1 Hepatotoxicity
TUKYSA can cause severe and fatal hepatotoxicity, particularly after rechallenge [see Adverse Reactions (6.1)].
Monitor ALT, AST, and bilirubin prior to starting TUKYSA, every 2 weeks for the first 2 months, then every 3 weeks during treatment, and as clinically indicated. For patients who experience AST/ALT >3 × ULN and bilirubin > ULN to ≤2 × ULN, repeat testing within 48-72 hours. For patients who experience AST/ALT >5 × ULN, withhold TUKYSA and repeat testing within 48-72 hours to determine if worsening. Based on the severity of hepatotoxicity, reduce dose or permanently discontinue TUKYSA [see Dosage and Administration (2.3)]. Institute weekly liver function monitoring if TUKYSA is resumed after resolution to Grade ≤1.
TUKYSA with trastuzumab and pertuzumab
In HER2CLIMB-05, 18% of patients who received TUKYSA had an ALT increase >5 × ULN, 10% had an AST increase >5 × ULN, and 1.2% had a bilirubin increase >3 × ULN (Grade ≥3). There were five confirmed Hy’s Law cases, including a fatal case. All occurred following rechallenge with TUKYSA. Hepatotoxicity led to dose reduction of TUKYSA in 16% of patients and discontinuation of TUKYSA in 8% of patients.
TUKYSA with trastuzumab and capecitabine
In HER2CLIMB, 8% of patients who received TUKYSA had an ALT increase >5 × ULN, 6% had an AST increase >5 × ULN, and 1.5% had a bilirubin increase >3 × ULN (Grade ≥3). Hepatotoxicity led to dose reduction of TUKYSA in 8% of patients and discontinuation of TUKYSA in 1.5% of patients.
TUKYSA with trastuzumab
In MOUNTAINEER, 6% of patients had a bilirubin increase >3 × ULN (Grade ≥3), 6% had an AST increase >5 × ULN, and 4.7% had an ALT increase >5 × ULN. Hepatotoxicity led to dose reduction of TUKYSA in 3.5% of patients and discontinuation of TUKYSA in 2.3% of patients.
5.2 Diarrhea
TUKYSA can cause severe diarrhea, including dehydration, hypotension, acute kidney injury, and death [see Adverse Reactions (6.1)].
If diarrhea occurs, administer antidiarrheal treatment as clinically indicated. Perform diagnostic tests as clinically indicated to exclude other causes of diarrhea. Based on the diarrhea severity, interrupt dose, reduce dose, or permanently discontinue TUKYSA [see Dosage and Administration (2.3)].
TUKYSA with trastuzumab and pertuzumab
In HER2CLIMB-05, 73% of patients who received TUKYSA experienced diarrhea, including 6% with Grade 3 events. The median time to onset of the first episode of diarrhea was 11 days and the median time to resolution was 2 days. Diarrhea led to dose reductions of TUKYSA in 6% of patients and discontinuation of TUKYSA in 1.5% of patients. Prophylactic use of antidiarrheal treatment was not required in HER2CLIMB-05.
TUKYSA with trastuzumab and capecitabine
In HER2CLIMB, 81% of patients who received TUKYSA experienced diarrhea, including 0.5% with Grade 4 diarrhea and 12% with Grade 3 diarrhea. Both patients who developed Grade 4 diarrhea subsequently died, with diarrhea as a contributor to death. The median time to onset of the first episode of diarrhea was 12 days and the median time to resolution was 8 days. Diarrhea led to dose reductions of TUKYSA in 6% of patients and discontinuation of TUKYSA in 1% of patients. Prophylactic use of antidiarrheal treatment was not required in HER2CLIMB.
TUKYSA with trastuzumab
In MOUNTAINEER, diarrhea occurred in 64% of patients, including Grade 3 (3.5%), Grade 2 (10%), and Grade 1 (50%).
5.3 Embryo-Fetal Toxicity
Based on findings from animal studies and its mechanism of action, TUKYSA can cause fetal harm when administered to a pregnant woman. In animal reproduction studies, administration of tucatinib to pregnant rats and rabbits during organogenesis caused embryo-fetal mortality, reduced fetal weight and fetal abnormalities at maternal exposures ≥1.3 times the human exposure (AUC) at the recommended dose.
Advise pregnant women and females of reproductive potential of the potential risk to a fetus. Advise females of reproductive potential to use effective contraception during treatment with TUKYSA and for 1 week after the last dose. Advise male patients with female partners of reproductive potential to use effective contraception during treatment with TUKYSA and for 1 week after the last dose [see Use in Specific Populations (8.1, 8.3)].
TUKYSA is used in combination with other agents. Refer to the Prescribing Information of combination agents for pregnancy and contraception information.
5.4 Increased Serum Creatinine Without Affecting Renal Function
TUKYSA can increase serum creatinine. Across three clinical trials in 816 patients (HER2CLIMB-05, HER2CLIMB, and MOUNTAINEER), the mean increase in serum creatinine was 29%-32% within the first 21 days of treatment with TUKYSA. The serum creatinine increases persisted throughout treatment and were reversible upon treatment completion. These increases were not associated with changes in glomerular function [see Adverse Reactions (6.1)]. These increases in serum creatinine may be due to inhibition of renal tubular transport of creatinine. During TUKYSA treatment, use alternative measures that are not based on serum creatinine to assess renal function [see Clinical Pharmacology (12.3)].
6 ADVERSE REACTIONS
The following clinically significant adverse reactions are described elsewhere in the labeling:
- Hepatotoxicity [see Warnings and Precautions (5.1)]
- Diarrhea [see Warnings and Precautions (5.2)]
6.1 Clinical Trials Experience
Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice.
Unresectable or Metastatic Breast Cancer
Maintenance Treatment of HER2-Positive Metastatic Breast Cancer (HER2CLIMB-05)
The safety of TUKYSA in combination with trastuzumab and pertuzumab was evaluated in HER2CLIMB-05 [see Clinical Studies (14.1)]. Patients received TUKYSA 300 mg twice daily plus trastuzumab and pertuzumab (n = 326) or placebo plus trastuzumab and pertuzumab (n = 324). The median duration of treatment was 17 months (range: 0.4 to 37) for the TUKYSA arm.
Serious adverse reactions occurred in 17% of patients who received TUKYSA. Serious adverse reactions in ≥1% of patients included hepatotoxicity (3.9%). One patient experienced a fatal adverse reaction of drug-induced liver injury.
Permanent discontinuation of TUKYSA due to an adverse reaction occurred in 14% of patients. Adverse reactions leading to permanent discontinuation in ≥1% of patients were hepatotoxicity (8%) and diarrhea (1.5%).
Dosage interruptions of TUKYSA due to an adverse reaction occurred in 49% of patients. Adverse reactions which required dosage interruption in >5% of patients included hepatotoxicity (19%) and diarrhea (9%).
Dose reduction of TUKYSA due to an adverse reaction occurred in 29% of patients. Adverse reactions leading to dose reduction in ≥2% of patients were hepatotoxicity (16%) and diarrhea (6%).
The most common (≥20%) adverse reactions were diarrhea, musculoskeletal pain, hepatotoxicity, nausea, fatigue, rash, and vomiting.
Table 4 summarizes the adverse reactions in HER2CLIMB-05.
Table 4: Adverse Reactions (≥10%) in Patients Who Received TUKYSA in HER2CLIMB-05 (All Grades)
| Adverse Reaction | TUKYSA + Trastuzumab + Pertuzumab N = 326 | Placebo + Trastuzumab + Pertuzumab N = 324 | ||||
All Grades % | Grade 3 % | Grade 4 % | All Grades % | Grade 3 % | Grade 4 % | |
| Gastrointestinal disorders | ||||||
| Diarrhea | 73 | 6 | 0 | 51 | 4 | 0 |
| Nausea | 33 | 0.9 | 0 | 24 | 0.9 | 0 |
| Vomiting | 20 | 0.3 | 0 | 14 | 0.3 | 0 |
| StomatitisStomatitis includes angular cheilitis, aphthous ulcer, cheilitis, mouth ulceration, oral dysesthesia, oral pain, oropharyngeal discomfort, oropharyngeal pain, and stomatitis. | 18 | 0 | 0 | 18 | 0 | 0 |
| Constipation | 11 | 0 | 0 | 11 | 0 | 0 |
| Musculoskeletal and connective tissue disorders | ||||||
| Musculoskeletal painMusculoskeletal pain includes arthralgia, arthritis, back pain, bone pain, musculoskeletal chest pain, musculoskeletal discomfort, musculoskeletal pain, musculoskeletal stiffness, myalgia, neck pain, non-cardiac chest pain, pain in extremity, and spinal pain. | 45 | 1.2 | 0 | 42 | 0.9 | 0 |
| Muscle spasms | 14 | 0 | 0 | 12 | 0.6 | 0 |
| Hepatobiliary disorders | ||||||
| HepatotoxicityHepatotoxicity includes ALT increased, AST increased, bilirubin conjugated increased, blood bilirubin increased, drug-induced liver injury, gamma-glutamyltransferase increased, hepatic cytolysis, hepatic failure, hepatotoxicity, hyperbilirubinemia, hypertransaminasemia, liver injury, and transaminases increased. | 44 | 15 | 2.5 | 16 | 1.2 | 0 |
| General disorders | ||||||
| FatigueFatigue includes fatigue and asthenia. | 33 | 0.9 | 0 | 25 | 1.9 | 0 |
| Pyrexia | 16 | 0 | 0 | 9 | 0 | 0 |
| Skin and subcutaneous tissue disorders | ||||||
| RashRash includes dermatitis, dermatitis acneiform, dermatitis allergic, dermatitis bullous, erythema, hand dermatitis, rash, rash macular, rash maculo-papular, rash papular, rash pruritic, rash pustular, skin reaction, skin toxicity, and urticaria. | 32 | 0.3 | 0 | 27 | 0.9 | 0 |
| Pruritus | 19 | 0 | 0 | 18 | 0 | 0 |
| Nervous system disorders | ||||||
| Headache | 19 | 0 | 0 | 18 | 0 | 0 |
| Respiratory, thoracic and mediastinal disorders | ||||||
| Cough | 18 | 0 | 0 | 14 | 0 | 0 |
| Blood and lymphatic system disorders | ||||||
| Anemia | 17 | 1.5 | 0 | 9 | 0.6 | 0 |
| Infections and infestations | ||||||
| Upper respiratory tract infection | 16 | 0 | 0 | 8 | 0.3 | 0 |
| COVID-19 | 14 | 0.3 | 0 | 13 | 0 | 0 |
| Metabolism and nutrition disorders | ||||||
| Decreased appetite | 14 | 0.3 | 0 | 7 | 0.3 | 0 |
| Investigations | ||||||
| Weight decreased | 11 | 0.6 | 0 | 9 | 0.3 | 0 |
Other clinically relevant adverse reactions in <10% of patients who received TUKYSA in combination with trastuzumab and pertuzumab included epistaxis (3.7%).
Table 5: Laboratory Abnormalities (≥20%) Worsening from Baseline in Patients Who Received TUKYSA and with a Difference of ≥5% Compared to Placebo in HER2CLIMB-05
| Laboratory Abnormality | TUKYSA + Trastuzumab + Pertuzumab N = 326 | Placebo + Trastuzumab + Pertuzumab N = 324 | ||
All Grades % | Grades ≥3 % | All Grades % | Grades ≥3 % | |
| Chemistry | ||||
| Increased ALT | 67 | 18 | 32 | 0.9 |
| Increased AST | 60 | 10 | 32 | 0 |
| Increased creatinine | 46 | 0.6 | 16 | 0 |
| Increased alkaline phosphatase | 29 | 0 | 23 | 0 |
| Decreased potassium | 23 | 3.7 | 14 | 0.9 |
| Hematology | ||||
| Decreased leukocytes | 27 | 0.9 | 21 | 0.6 |
| Decreased neutrophils | 25 | 2.9 | 17 | 1.4 |
Treatment of HER2-Positive Breast Cancer (HER2CLIMB)
The safety of TUKYSA in combination with trastuzumab and capecitabine was evaluated in HER2CLIMB [see Clinical Studies (14.1)]. Patients received either TUKYSA 300 mg twice daily plus trastuzumab or a non-US approved trastuzumab product, and capecitabine (n = 404) or placebo plus trastuzumab or a non-US approved trastuzumab product and capecitabine (n = 197). The median duration of treatment was 5.8 months (range: 3 days, 2.9 years) for the TUKYSA arm.
Serious adverse reactions occurred in 26% of patients who received TUKYSA. Serious adverse reactions in ≥2% of patients who received TUKYSA were diarrhea (4%), vomiting (2.5%), nausea (2%), abdominal pain (2%), and seizure (2%). Fatal adverse reactions occurred in 2% of patients who received TUKYSA including sudden death, sepsis, dehydration, and cardiogenic shock.
Adverse reactions leading to treatment discontinuation occurred in 6% of patients who received TUKYSA. Adverse reactions leading to treatment discontinuation of TUKYSA in ≥1% of patients were hepatotoxicity (1.5%) and diarrhea (1%).
Adverse reactions leading to dose reduction occurred in 21% of patients who received TUKYSA. Adverse reactions leading to dose reduction of TUKYSA in ≥2% of patients were hepatotoxicity (8%) and diarrhea (6%).
The most common adverse reactions in patients who received TUKYSA (≥20%) were diarrhea, palmar-plantar erythrodysesthesia, nausea, hepatotoxicity, vomiting, stomatitis, decreased appetite, anemia, and rash.
Table 6 summarizes the adverse reactions in HER2CLIMB.
Table 6: Adverse Reactions (≥10%) in Patients Who Received TUKYSA and with a Difference Between Arms of ≥5% Compared to Placebo in HER2CLIMB (All Grades)
| Adverse Reaction | TUKYSA + Trastuzumab + Capecitabine N = 404 | Placebo + Trastuzumab + Capecitabine N = 197 | ||||
All Grades % | Grade 3 % | Grade 4 % | All Grades % | Grade 3 % | Grade 4 % | |
| Gastrointestinal disorders | ||||||
| Diarrhea | 81 | 12 | 0.5 | 53 | 9 | 0 |
| Nausea | 58 | 3.7 | 0 | 44 | 3 | 0 |
| Vomiting | 36 | 3 | 0 | 25 | 3.6 | 0 |
| StomatitisStomatitis includes stomatitis, oropharyngeal pain, oropharyngeal discomfort, mouth ulceration, oral pain, lip ulceration, glossodynia, tongue blistering, lip blister, oral dysesthesia, tongue ulceration, and aphthous ulcer. | 32 | 2.5 | 0 | 21 | 0.5 | 0 |
| Skin and subcutaneous tissue disorders | ||||||
| Palmar-plantar erythrodysesthesia syndrome | 63 | 13 | 0 | 53 | 9 | 0 |
| RashRash includes rash maculo-papular, rash, dermatitis acneiform, erythema, rash macular, rash papular, rash pustular, rash pruritic, rash erythematous, skin exfoliation, urticaria, dermatitis allergic, palmar erythema, plantar erythema, skin toxicity, and dermatitis. | 20 | 0.7 | 0 | 15 | 0.5 | 0 |
| Hepatobiliary disorders | ||||||
| HepatotoxicityHepatotoxicity includes hyperbilirubinemia, blood bilirubin increased, bilirubin conjugated increased, alanine aminotransferase increased, transaminases increased, hepatotoxicity, aspartate aminotransferase increased, liver function test increased, liver injury, and hepatocellular injury. | 42 | 9 | 0.2 | 24 | 3.6 | 0 |
| Metabolism and nutrition disorders | ||||||
| Decreased appetite | 25 | 0.5 | 0 | 20 | 0 | 0 |
| Blood and lymphatic system disorders | ||||||
| AnemiaAnemia includes anemia, hemoglobin decreased, and normocytic anemia. | 21 | 3.7 | 0 | 13 | 2.5 | 0 |
| Musculoskeletal and connective tissue disorders | ||||||
| Arthralgia | 15 | 0.5 | 0 | 4.6 | 0.5 | 0 |
| Investigations | ||||||
| Creatinine increasedDue to inhibition of renal tubular transport of creatinine without affecting glomerular function. | 14 | 0 | 0 | 1.5 | 0 | 0 |
| Weight decreased | 13 | 1 | 0 | 6 | 0.5 | 0 |
| Nervous System Disorders | ||||||
| Peripheral neuropathyPeripheral neuropathy includes peripheral sensory neuropathy, neuropathy peripheral, peripheral motor neuropathy, and peripheral sensorimotor neuropathy. | 13 | 0.5 | 0 | 7 | 1 | 0 |
| Respiratory, thoracic and mediastinal disorders | ||||||
| Epistaxis | 12 | 0 | 0 | 5 | 0 | 0 |
Table 7: Laboratory Abnormalities (≥20%) Worsening from Baseline in Patients Who Received TUKYSA and with a Difference of ≥5% Compared to Placebo in HER2CLIMB
| Laboratory Abnormality | TUKYSA + Trastuzumab + Capecitabine The denominator used to calculate the rate varied from 351 to 400 in the TUKYSA arm and 173 to 197 in the control arm based on the number of patients with a baseline value and at least one post-treatment value. Grading was based on NCI CTCAE v.4.03 for laboratory abnormalities, except for increased creatinine which only includes patients with a creatinine increase based on the upper limit of normal definition for Grade 1 events (NCI CTCAE v5.0). | Placebo + Trastuzumab + Capecitabine | ||
All Grades % | Grades ≥3 % | All Grades % | Grades ≥3 % | |
| Hematology | ||||
| Decreased hemoglobin | 59 | 3.3 | 51 | 1.5 |
| Chemistry | ||||
| Decreased phosphate | 57 | 8 | 45 | 7 |
| Increased bilirubin | 47 | 1.5 | 30 | 3.1 |
| Increased ALT | 46 | 8 | 27 | 0.5 |
| Increased AST | 43 | 6 | 25 | 1 |
| Decreased magnesium | 40 | 0.8 | 25 | 0.5 |
| Decreased potassiumLaboratory criteria for Grade 1 are identical to laboratory criteria for Grade 2. | 36 | 6 | 31 | 5 |
| Increased creatinine | 33 | 0 | 6 | 0 |
| Decreased sodiumThere is no definition for Grade 2 in CTCAE v.4.03. | 28 | 2.5 | 23 | 2 |
| Increased alkaline phosphatase | 26 | 0.5 | 17 | 0 |
RAS Wild-Type, HER2-Positive Unresectable or Metastatic Colorectal Cancer
The safety of TUKYSA in combination with trastuzumab or a non-US approved trastuzumab product was evaluated in 86 patients enrolled in MOUNTAINEER with unresectable or metastatic colorectal cancer [see Clinical Studies (14.2)]. The median duration of exposure to TUKYSA was 6.9 months (range 0.7, 49.3).
Serious adverse reactions occurred in 22% of patients. Serious adverse reactions that occurred in ≥2% of patients were intestinal obstruction (7%), urinary tract infection (3.5%), pneumonia (2.3%), abdominal pain (2.3%) and rectal perforation (2.3%).
Permanent discontinuation of TUKYSA due to an adverse reaction occurred in 6% of patients. The adverse reaction which resulted in permanent discontinuation of TUKYSA in ≥2% of patients was increased ALT (2.3%). Dosage interruptions of TUKYSA due to an adverse reaction occurred in 23% of patients. Adverse reactions which required dosage interruption in ≥3% of patients were increased ALT (3.5%) and diarrhea (3.5%). Dose reductions of TUKYSA due to an adverse reaction occurred in 9% of patients. Adverse reactions which required dose reductions in ≥2% of patients were increased ALT (2.3%) and diarrhea (2.3%).
The most common adverse reactions reported in ≥20% of patients treated with TUKYSA and trastuzumab were diarrhea, fatigue, rash, nausea, abdominal pain, infusion related reactions, and pyrexia. The most common laboratory abnormalities reported in ≥20% of patients were increased creatinine, increased glucose, increased ALT, decreased hemoglobin, increased AST, increased bilirubin, increased alkaline phosphatase, decreased lymphocytes, decreased albumin, decreased leukocytes, and decreased sodium.
Table 8 summarizes the adverse reactions in MOUNTAINEER.
Table 8: Adverse Reactions (≥10%) in Patients with Unresectable or Metastatic Colorectal Cancer (MOUNTAINEER)
| Adverse Reaction | TUKYSA + Trastuzumab N = 86 Includes 1 patient who only received trastuzumab. | |
All Grades % | Grade 3 % | |
| Gastrointestinal disorders | ||
| Diarrhea | 64 | 3.5 |
| Nausea | 35 | 0 |
| Vomiting | 16 | 0 |
| Abdominal painAbdominal pain includes abdominal discomfort, abdominal pain, and abdominal pain upper. | 21 | 2.3 |
| Constipation | 14 | 1.2 |
| General disorders | ||
| Fatigue | 44 | 2.3 |
| Pyrexia | 20 | 0 |
| Chills | 19 | 1.2 |
| Skin and subcutaneous disorders | ||
| RashRash includes acne, dermatitis acneiform, dermatitis contact, erythema, erythema multiforme, rash, rash macular, rash maculo-papular, rash papular, rash pustular, skin exfoliation, and urticaria. | 37 | 0 |
| Injury, poisoning, and procedural complications | ||
| Infusion related reaction | 21 | 0 |
| Metabolism and nutrition disorders | ||
| Decreased appetite | 19 | 0 |
| Blood and lymphatic system disorders | ||
| Anemia | 10 | 0 |
| Vascular disorders | ||
| Hypertension | 17 | 7 |
| Musculoskeletal and connective tissue disorders | ||
| Back pain | 17 | 2.3 |
| Arthralgia | 16 | 1.2 |
| Myalgia | 13 | 0 |
| Respiratory, thoracic and mediastinal disorders | ||
| Cough | 16 | 0 |
| Dyspnea | 14 | 0 |
| Psychiatric disorders | ||
| Anxiety | 10 | 0 |
Other clinically relevant adverse reactions in <10% of patients who received TUKYSA in combination with trastuzumab include epistaxis (7%), weight decreased (7%), oropharyngeal pain (5%), oral dysesthesia (1%), and stomatitis (1%).
Table 9: Laboratory Abnormalities (≥15%) Worsening from Baseline in Patients with Unresectable or Metastatic Colorectal Cancer (MOUNTAINEER)
| Laboratory Abnormality | TUKYSA + Trastuzumab N = 85 Number of patients with both baseline and post-baseline results for each test. | ||
All Grades % | Grade 3 % | Grade 4 % | |
| Hematology | |||
| Decreased hemoglobin | 46 | 3.5 | 0 |
| Decreased lymphocytes | 39 | 12 | 0 |
| Decreased leukocytes | 22 | 0 | 0 |
| Decreased platelets | 15 | 0 | 0 |
| Chemistry | |||
| Increased creatinineNCI CTCAE v5.0 was used for creatinine increased. NCI CTCAE v4.03 was used for all other laboratory parameters. | 58 | 0 | 0 |
| Increased glucose | 56 | 2.4 | 0 |
| Increased ALT | 46 | 2.4 | 2.4 |
| Increased AST | 33 | 2.4 | 3.5 |
| Increased bilirubin | 28 | 3.5 | 2.4 |
| Increased alkaline phosphatase | 25 | 1.2 | 0 |
| Decreased albumin | 24 | 1.2 | 0 |
| Decreased sodium | 20 | 6 | 0 |
| Decreased potassium | 16 | 1.2 | 0 |
7 DRUG INTERACTIONS
7.1 Effects of Other Drugs on TUKYSA
Table 10 summarizes the effect of other drugs on TUKYSA.
Table 10: Drug Interactions that Affect TUKYSA
| Strong CYP3A Inducers or Moderate CYP2C8 Inducers | |
| Clinical Impact | Concomitant use of TUKYSA with a strong CYP3A or moderate CYP2C8 inducer decreased tucatinib plasma concentrations [see Clinical Pharmacology (12.3)], which may reduce TUKYSA activity. |
| Management | Avoid concomitant use of TUKYSA with a strong CYP3A inducer or a moderate CYP2C8 inducer. |
| Strong or Moderate CYP2C8 Inhibitors | |
| Clinical Impact | Concomitant use of TUKYSA with a strong CYP2C8 inhibitor increased tucatinib plasma concentrations [see Clinical Pharmacology (12.3)], which may increase the risk of TUKYSA toxicity. |
| Management | Avoid concomitant use of TUKYSA with a strong CYP2C8 inhibitor [see Dosage and Administration (2.5)]. Increase monitoring for TUKYSA toxicity with moderate CYP2C8 inhibitors. |
7.2 Effects of TUKYSA on Other Drugs
Table 11 summarizes the effect of TUKYSA on other drugs.
Table 11: TUKYSA Drug Interactions that Affect Other Drugs
| CYP3A Substrates | |
| Clinical Impact | Concomitant use of TUKYSA with a CYP3A substrate increased the plasma concentrations of CYP3A substrate [see Clinical Pharmacology (12.3)], which may increase the toxicity associated with a CYP3A substrate. |
| Management | Avoid concomitant use of TUKYSA with CYP3A substrates, where minimal concentration changes may lead to serious or life-threatening toxicities. If concomitant use is unavoidable, decrease the CYP3A substrate dosage in accordance with approved product labeling. |
| P-glycoprotein (P-gp) Substrates | |
| Clinical Impact | Concomitant use of TUKYSA with a P-gp substrate increased the plasma concentrations of P-gp substrate [see Clinical Pharmacology (12.3)], which may increase the toxicity associated with a P-gp substrate. |
| Management | Consider reducing the dosage of P-gp substrates, where minimal concentration changes may lead to serious or life-threatening toxicities. |
8 USE IN SPECIFIC POPULATIONS
8.1 Pregnancy
Risk Summary
TUKYSA is used in combination with other agents. Refer to the Prescribing Information of combination agents for pregnancy information.
Based on findings in animals and its mechanism of action, TUKYSA can cause fetal harm when administered to a pregnant woman [see Clinical Pharmacology (12.1)]. There are no available human data on TUKYSA use in pregnant women to inform a drug-associated risk. In animal reproduction studies, administration of tucatinib to pregnant rats and rabbits during organogenesis resulted in embryo-fetal mortality, reduced fetal weight and fetal abnormalities at maternal exposures ≥1.3 times the human exposure (AUC) at the recommended dose (see Data). Advise pregnant women and females of reproductive potential of the potential risk to the fetus.
The background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2%-4% and 15%-20%, respectively.
Data
Animal Data
In pilot embryo-fetal development studies, pregnant rats and rabbits received oral doses of tucatinib up to 150 mg/kg/day during the period of organogenesis.
In rats, oral administration of tucatinib resulted in maternal toxicity (body weight loss, reduced body weight gain, low food consumption) at doses ≥90 mg/kg/day. Fetal effects included reduced number of live fetuses, decreased fetal weight, and fetal abnormalities (increase in skeletal variations, incomplete ossification) at ≥90 mg/kg/day (approximately 3.5 times the human exposure at the recommended dose based on AUC).
In rabbits, oral administration of tucatinib resulted in increased resorptions, decreased percentages of live fetuses, and skeletal, visceral, and external malformations in fetuses at doses ≥90 mg/kg/day (1.3 times the human exposure at the recommended dose based on AUC). Fetal abnormalities included domed head, brain dilation, incomplete ossification of frontal and parietal bones, and a hole in the parietal bone.
8.2 Lactation
Risk Summary
TUKYSA is used in combination with other agents. Refer to the Prescribing Information of combination agents for lactation information. When TUKYSA is used in combination, advise patients not to breastfeed during treatment and for the longest post-treatment duration recommended in the Prescribing Information of any of the individual products.
There are no data on the presence of tucatinib or its metabolites in human or animal milk or its effects on the breastfed child or on milk production. Because of the potential for serious adverse reactions in a breastfed child, advise women not to breastfeed during treatment with TUKYSA and for 1 week after the last dose.
8.3 Females and Males of Reproductive Potential
TUKYSA can cause fetal harm when administered to a pregnant woman [see Use in Specific Populations (8.1)]. TUKYSA is used in combination with other agents. Refer to the Prescribing Information of combination agents for contraception and infertility information. When TUKYSA is used in combination, advise patients to use effective contraception during treatment and for the longest post-treatment duration recommended in the Prescribing Information of any of the individual products.
Pregnancy Testing
Verify the pregnancy status of females of reproductive potential prior to initiating treatment with TUKYSA.
Contraception
Females
Advise females of reproductive potential to use effective contraception during treatment with TUKYSA and for 1 week after the last dose.
Males
Advise male patients with female partners of reproductive potential to use effective contraception during treatment with TUKYSA and for 1 week after the last dose.
Infertility
Based on findings from animal studies, TUKYSA may impair male and female fertility [see Nonclinical Toxicology (13.1)].
8.4 Pediatric Use
The safety and effectiveness of TUKYSA in pediatric patients have not been established.
8.5 Geriatric Use
In HER2CLIMB-05, 51 patients who received TUKYSA were ≥65 years of age of whom 12 patients were ≥75 years of age. The incidence of ≥ Grade 3 adverse reactions was 57% in patients ≥65 years of age compared to 40% in patients <65 years of age. There were no overall differences in the effectiveness of TUKYSA in patients ≥65 years of age compared to younger patients. There were too few patients ≥75 years of age to assess differences in effectiveness or safety.
In HER2CLIMB, 82 patients who received TUKYSA were ≥65 years of age, of whom 8 patients were ≥75 years of age. The incidence of serious adverse reactions in those receiving TUKYSA was 34% in patients ≥65 years of age compared to 24% in patients <65 years of age. The most frequent serious adverse reactions in patients ≥65 years of age who received TUKYSA were diarrhea (9%), vomiting (6%), and nausea (5%). There were no observed overall differences in the effectiveness of TUKYSA in patients ≥65 years of age compared to younger patients. There were too few patients ≥75 years of age to assess differences in effectiveness or safety.
In MOUNTAINEER, 12 patients were ≥65 years of age. There were too few patients ≥65 years of age to assess differences in effectiveness or safety.
8.6 Renal Impairment
The use of TUKYSA in combination with capecitabine and trastuzumab is not recommended in patients with severe renal impairment (creatinine clearance [CLcr]: <30 mL/min estimated by Cockcroft-Gault Equation), because capecitabine is contraindicated in patients with severe renal impairment. Refer to the Prescribing Information of capecitabine for additional information in severe renal impairment.
No dose adjustment is recommended for patients with mild or moderate renal impairment (CLcr: 30 to 89 mL/min).
8.7 Hepatic Impairment
Tucatinib exposure is increased in patients with severe hepatic impairment (Child-Pugh C). Reduce the dose of TUKYSA for patients with severe (Child‑Pugh C) hepatic impairment [see Dosage and Administration (2.4), Clinical Pharmacology (12.3)].
No dose adjustment for TUKYSA is required for patients with mild (Child-Pugh A) or moderate (Child-Pugh B) hepatic impairment.
11 DESCRIPTION
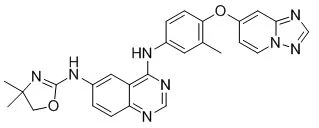
Tucatinib is a kinase inhibitor. The chemical name is (N4-(4-([1,2,4]triazolo[1,5-a]pyridin-7-yloxy)-3-methylphenyl)-N6-(4,4-dimethyl-4,5-dihydrooxazol-2-yl)quinazoline-4,6-diamine. The molecular formula is C26H24N8O2 and the molecular weight is 480.52 g/mol. The chemical structure is as follows:
TUKYSA (tucatinib) is supplied as 50 mg and 150 mg film-coated tablets for oral use and contain the following inactive ingredients:
Tablet core: copovidone, crospovidone, sodium chloride, potassium chloride, sodium bicarbonate, colloidal silicon dioxide, magnesium stearate, and microcrystalline cellulose.
Coating: yellow film coat: polyvinyl alcohol, titanium dioxide, macrogol/polyethylene glycol, talc, and yellow iron oxide non-irradiated.
Each TUKYSA 50 mg tablet contains 10.10 mg (0.258 mEq) potassium and 9.21 mg (0.401 mEq) sodium.
Each TUKYSA 150 mg tablet contains 30.29 mg (0.775 mEq) potassium and 27.64 mg (1.202 mEq) sodium.
12 CLINICAL PHARMACOLOGY
12.1 Mechanism of Action
Tucatinib is a tyrosine kinase inhibitor of HER2. In vitro, tucatinib inhibits phosphorylation of HER2 and HER3, resulting in inhibition of downstream MAPK and AKT signaling and cell proliferation, and showed anti-tumor activity in HER2 expressing tumor cells. In vivo, tucatinib inhibited the growth of HER2 expressing tumors. The combination of tucatinib and trastuzumab showed increased anti-tumor activity in vitro and in vivo compared to either drug alone.
12.2 Pharmacodynamics
Exposure-Response Relationship
Tucatinib exposure-response relationships and the time course of pharmacodynamics response have not been fully characterized.
Cardiac Electrophysiology
No large mean increase in QTc (i.e., >20 ms) was detected following treatment with TUKYSA at the recommended dose of 300 mg taken orally twice daily.
12.3 Pharmacokinetics
Tucatinib AUC0-INF and Cmax increased proportionally over a dosage range from 50 mg to 300 mg (0.17 to 1 times the approved recommended dosage). Time to steady state was approximately 4 days. Steady-state pharmacokinetic parameters following administration of TUKYSA 300 mg twice daily for 7 days in patients with mBC and mCRC are described in Table 12. The geometric mean (CV%) tucatinib AUC accumulation ratios ranged from 2.0 (26) fold to 2.5 (28) fold.
Table 12: Tucatinib Cmax and AUC
| Tumor Type | AUCss (ng*h/mL) | Cmax,ss (ng/mL) | Ctrough,ss (ng/mL) |
| mBC | 5620 (43) | 747 (45) | 288 (59) |
| mCRC | 3370 (49) | 405 (45) | 197 (63) |
Absorption
The median time to peak plasma concentration of tucatinib was approximately 2 hours (range 1 to 4 hours).
Effects of Food
Following administration of a single oral dose of TUKYSA in 11 subjects after a high-fat meal (approximately 58% fat, 26% carbohydrate, and 16% protein), the mean AUC0-INF increased by 1.5-fold, the Tmax shifted from 1.5 hours to 4 hours, and Cmax was unaltered. The effect of food on the pharmacokinetics of tucatinib was not clinically meaningful.
Distribution
The geometric mean (CV%) apparent volume of distribution of tucatinib at steady-state were 903 (42) L and 829 (21) L in patients with mBC and mCRC, respectively. The plasma protein binding was 97.1% at clinically relevant concentrations.
At steady-state, concentrations of tucatinib and its metabolite ONT-993 in the cerebrospinal fluid were comparable to unbound plasma concentrations.
Elimination
At steady-state, tucatinib effective half-life was approximately 11.9 hours and geometric mean (CV%) apparent clearance was 53 (43) L/h in patients with mBC. Tucatinib effective half-life was approximately 16.4 hours and geometric mean (CV%) apparent clearance was 89 (49) L/h in patients with mCRC.
Metabolism
Tucatinib is metabolized primarily by CYP2C8 and to a lesser extent via CYP3A.
Excretion
Following a single oral dose of 300 mg radiolabeled tucatinib, approximately 86% of the total radiolabeled dose was recovered in feces (16% of the administered dose as unchanged tucatinib) and 4.1% in urine with an overall total recovery of 90% within 13 days post-dose. In plasma, approximately 76% of the plasma radioactivity was unchanged, 19% was attributed to identified metabolites, and approximately 5% was unassigned.
Specific Populations
Age (18-77 years), albumin (19 to 52 g/L), creatinine clearance (CLcr: 60 to 89 mL/min (n = 63); CLcr 30 to 59 mL/min (n = 6)), body weight (41 to 146 kg), sex (male (n = 170), female (n = 113)) and race (White (n = 205), Black (n = 37), or Asian (n = 25)) did not have a clinically meaningful effect on tucatinib exposure.
Renal Impairment
No clinically significant differences in the pharmacokinetics of tucatinib were observed in patients with mild to moderate renal impairment (CLcr: 30 to 89 mL/min by Cockcroft-Gault). The effect of severe renal impairment (CLcr: <30 mL/min) on the pharmacokinetics of tucatinib is unknown.
Hepatic Impairment
Mild (Child-Pugh A) and moderate (Child-Pugh B) hepatic impairment had no clinically relevant effect on tucatinib exposure. Tucatinib AUC0-INF was increased by 1.6 fold in subjects with severe (Child-Pugh C) hepatic impairment compared to subjects with normal hepatic function.
Drug Interaction Studies
Clinical Studies
Table 13: Effect of Other Drugs on TUKYSA
Concomitant Drug (Dose) | TUKYSA Dose | Ratio (90% CI) of Tucatinib Exposure With and Without Concomitant Drug | |
| Cmax | AUC | ||
Strong CYP3A Inhibitor Itraconazole (200 mg BID) | 300 mg single dose | 1.3 (1.2, 1.4) | 1.3 (1.3, 1.4) |
Strong CYP3A/Moderate 2C8 Inducer Rifampin (600 mg once daily) | 0.6 (0.5, 0.8) | 0.5 (0.4, 0.6) | |
Strong CYP2C8 Inhibitor Gemfibrozil (600 mg BID) | 1.6 (1.5, 1.8) | 3.0 (2.7, 3.5) | |
Table 14: Effect of TUKYSA on Other Drugs
Concomitant Drug (Dose) | TUKYSA Dose | Ratio (90% CI) of Exposure Measures of Concomitant Drug with/without Tucatinib | |
| Cmax | AUC | ||
CYP2C8 Substrate Repaglinide (0.5 mg single dose) | 300 mg twice daily | 1.7 (1.4, 2.1) | 1.7 (1.5, 1.9) |
CYP3A Substrate Midazolam (2 mg single dose) | 3.0 (2.6, 3.4) | 5.7 (5.0, 6.5) | |
P-gp Substrate Digoxin (0.5 mg single dose) | 2.4 (1.9, 2.9) | 1.5 (1.3, 1.7) | |
MATE1/2-K substrate Tucatinib reduced the renal clearance of metformin without any effect on glomerular filtration rate (GFR) as measured by iohexol clearance and serum cystatin C. Metformin (850 mg single dose) | 1.1 (1.0, 1.2) | 1.4 (1.2, 1.5) | |
No clinically significant difference in the pharmacokinetics of tucatinib were observed when used concomitantly with omeprazole (proton pump inhibitor) or tolbutamide (sensitive CYP2C9 substrate).
In Vitro Studies
Cytochrome P450 (CYP) Enzymes: Tucatinib is a reversible inhibitor of CYP2C8 and CYP3A and a time-dependent inhibitor of CYP3A, but is not an inhibitor of CYP1A2, CYP2B6, CYP2C9, CYP2C19, or CYP2D6.
Uridine diphosphate (UDP)-glucuronosyl transferase (UGT) Enzymes: Tucatinib is not an inhibitor of UGT1A1.
Transporter Systems: Tucatinib is a substrate of P-gp and BCRP, but is not a substrate of OAT1, OAT3, OCT1, OCT2, OATP1B1, OATP1B3, MATE1, MATE2-K, or BSEP.
Tucatinib inhibits MATE1/MATE2-K-mediated transport of metformin and OCT2/MATE1-mediated transport of creatinine. The observed serum creatinine increase in clinical studies with tucatinib is due to inhibition of tubular secretion of creatinine via OCT2 and MATE1.
13 NONCLINICAL TOXICOLOGY
13.1 Carcinogenesis, Mutagenesis, Impairment of Fertility
Carcinogenicity studies have not been conducted with tucatinib.
Tucatinib was not mutagenic in an in vitro bacterial reverse mutation (Ames) assay. Tucatinib was not clastogenic in either an in vitro chromosome aberration assay or an in vivo mouse bone marrow micronucleus assay.
Fertility studies in animals have not been conducted. In repeat-dose toxicity studies up to 13 weeks duration, decreased corpora lutea/corpus luteum cyst, increased interstitial cells of the ovary, atrophy of the uterus, and mucification of the vagina were observed in female rats at doses ≥6 mg/kg/day (approximately 0.1 times the human exposure at the recommended dose based on AUC). Atrophy and edema of the testes and oligospermia/germ cell debris in the epididymides were observed in male rats at ≥120 mg/kg/day (approximately 13 times the human exposure at the recommended dose based on AUC).
14 CLINICAL STUDIES
14.1 Unresectable or Metastatic Breast Cancer
Maintenance Treatment of HER2-Positive Breast Cancer
HER2CLIMB-05
The efficacy of TUKYSA in combination with trastuzumab and pertuzumab was evaluated in 654 adult patients in HER2CLIMB-05 (NCT05132582), a randomized (1:1), double-blind, placebo-controlled trial. Eligible patients were required to have HER2-positive, unresectable locally advanced or metastatic breast cancer, with or without brain metastases, and no evidence of disease progression by investigator assessment (i.e., experiencing a complete response, partial response, or stable disease) after induction treatment with 4-8 cycles of trastuzumab, pertuzumab, and a taxane. Tumor HER2 positivity was determined at a central laboratory by immunohistochemistry (IHC) and in situ hybridization (ISH) prior to randomization (defined as a 3+ score on IHC and/or 2+ IHC and concurrent positive by ISH).
Patients with a presence or history of brain metastases were eligible provided they were asymptomatic and stable and did not require immediate local treatment. Randomization was stratified by the presence or history of brain metastases (yes vs. no), hormone receptor status (positive vs. negative), and diagnosis (de novo vs. recurrent).
Patients received TUKYSA 300 mg or placebo orally twice daily with trastuzumab 6 mg/kg intravenously or subcutaneously at a fixed dose of 600 mg and pertuzumab 420 mg intravenously once every 21 days, or with a fixed-dose combination of 600 mg trastuzumab, 600 mg pertuzumab, and 20,000 units hyaluronidase given subcutaneously every 21 days. Patients with hormone receptor positive disease were permitted to continue endocrine therapy (with ovarian suppression, if applicable). Patients were treated until disease progression or unacceptable toxicity.
The primary efficacy outcome measure was progression-free survival (PFS) by investigator assessment using Response Evaluation Criteria in Solid Tumors (RECIST) v1.1. Additional efficacy outcome measures included overall survival (OS).
The median age was 54 years (range: 24 - 83); 108 (17%) patients were 65 years of age and older. Forty-five percent were White, 35% were Asian, and 3% were Black; 19% were Hispanic or Latino and 66% were not Hispanic or Latino, and 14% were missing/unknown; all were female; and patients had an Eastern Cooperative Oncology Group (ECOG) performance status of 0 (64%), 1 (36%), or 2 (0.3%). Fifty-three percent had estrogen and/or progesterone receptor-positive disease. Twelve percent had a presence or history of brain metastases and 56% of patients had visceral metastases.
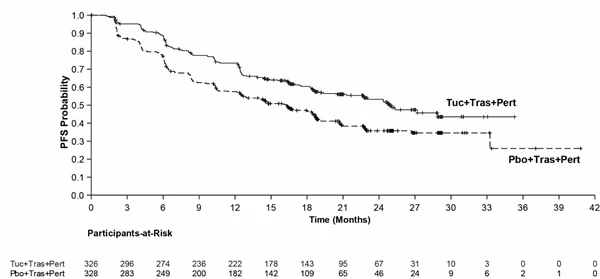
Efficacy results are summarized in Table 15 and Figure 1. Overall survival data were not mature at the time of PFS analysis, with 51 deaths (8%) across both arms in the overall population.
Table 15: Efficacy Results in HER2CLIMB-05
| Abbreviations: CI = confidence interval; NR = not reached; PFS = progression-free survival. | ||
TUKYSA + Trastuzumab + Pertuzumab (N = 326) | Placebo + Trastuzumab + Pertuzumab (N = 328) | |
| PFS per Investigator | ||
| Number of events (%) | 141 (43) | 191 (58) |
| Median, months (95% CI) | 24.9 (21.3, NR) | 16.3 (12.6, 18.7) |
| Hazard ratio (95% CI)Computed using stratification factors: presence or history of brain metastases (yes vs. no), hormone receptor status (positive vs. negative), and diagnosis (de novo vs. recurrent). Hazard ratio is calculated based on a stratified Cox proportional hazards model. | 0.64 (0.51, 0.80) | |
| P-valueTwo-sided P-value is calculated using the stratified log-rank test. | <0.0001 | |
Figure 1: Kaplan-Meier Plot of PFS per Investigator in HER2CLIMB-05
Treatment of HER2-Positive Breast Cancer
HER2CLIMB
The efficacy of TUKYSA in combination with trastuzumab and capecitabine was evaluated in 612 patients in HER2CLIMB (NCT02614794), a randomized (2:1), double-blind, placebo-controlled trial. Patients were required to have HER2-positive, unresectable locally advanced or metastatic breast cancer, with or without brain metastases, and prior treatment with trastuzumab, pertuzumab, and ado-trastuzumab emtansine (T-DM1) separately or in combination, in the neoadjuvant, adjuvant or metastatic setting. HER2 positivity was based on archival or fresh tissue tested with an FDA-approved test at a central laboratory prior to enrollment with HER2 positivity defined as HER2 IHC 3+ or ISH positive.
Patients with brain metastases, including those with progressing or untreated lesions, were eligible provided they were neurologically stable and did not require immediate radiation or surgery. The trial excluded patients with leptomeningeal disease. Randomization was stratified by the presence or history of brain metastases (yes vs. no), ECOG performance status (0 vs. 1), and region (U.S., Canada, or rest of world).
Patients received TUKYSA 300 mg or placebo orally twice daily with a trastuzumab or a non-U.S. approved trastuzumab product loading dose of 8 mg/kg on Day 1 of Cycle 1 if needed and then a maintenance dose of 6 mg/kg on Day 1 of every 21-day cycle thereafter and capecitabine 1000 mg/m2 orally twice daily on Days 1 through 14 of every 21-day cycle. An alternate trastuzumab dosing regimen was 600 mg administered subcutaneously on Day 1 of every 21-day cycle. Patients were treated until disease progression or unacceptable toxicity. Tumor assessments, including brain-MRI in patients with presence or history of brain metastases at baseline, occurred every 6 weeks for the first 24 weeks and every 9 weeks thereafter.
The major efficacy outcome measure was PFS in the first 480 randomized patients assessed by Blinded Independent Central Review (BICR) using RECIST v1.1. Additional efficacy outcome measures were evaluated in all randomized patients and included OS, PFS among patients with a history or presence of brain metastases (PFSBrainMets) and confirmed objective response rate (ORR).
The median age was 54 years (range: 22 - 82); 116 (19%) patients were age 65 or older. The majority were White (73%) and female (99%) and 51% had an ECOG performance status of 1. Sixty percent had estrogen and/or progesterone receptor-positive disease. Forty-eight percent had a presence or history of brain metastases; of these patients, 23% had untreated brain metastases, 40% had treated but stable brain metastases, and 37% had treated but radiographically progressing brain metastases. Seventy-four percent of patients had visceral metastases. Patients had received a median of 4 (range, 2 to 17) prior lines of systemic therapy and a median of 3 (range, 1 to 14) prior lines of systemic therapy in the metastatic setting. All patients received prior trastuzumab and T-DM1 and all but 2 patients had prior pertuzumab.
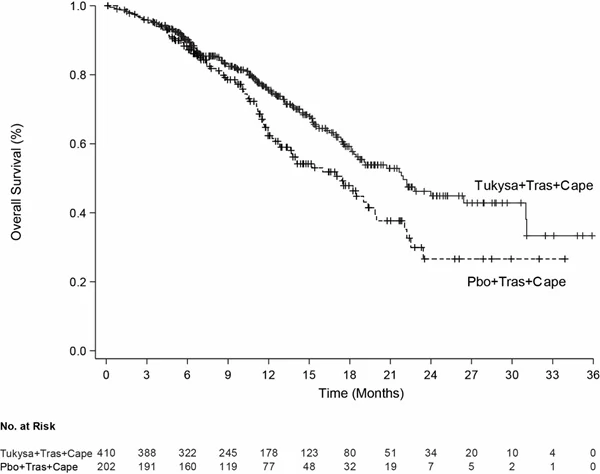
Efficacy results are summarized in Table 16 and Figures 2 and 3. Efficacy results were consistent across patient subgroups defined by stratification factors (presence or history of brain metastases, ECOG status, region of world) and hormone receptor status.
Table 16: Efficacy Results in HER2CLIMB
| Abbreviations: BICR = blinded independent central review; CI = confidence interval; CR = complete response; DOR = duration of response; OS = overall survival; ORR = objective response rate; PFS = progression-free survival; PR = partial response. | ||
| TUKYSA + Trastuzumab + Capecitabine | Placebo + Trastuzumab + Capecitabine | |
| PFS Primary PFS analysis conducted in first 480 randomized patients. | N = 320 | N = 160 |
| Number of events (%) | 178 (56) | 97 (61) |
| Median, months (95% CI) | 7.8 (7.5, 9.6) | 5.6 (4.2, 7.1) |
| Hazard ratio (95% CI)Hazard ratio and 95% confidence intervals are based on stratified Cox proportional hazards regression model controlling for stratification factors (presence or history of brain metastases, ECOG status, and region of world). | 0.54 (0.42, 0.71) | |
| P-valueTwo-sided p-value based on re-randomization procedure (Rosenberger and Lachin 2002) controlling for stratification factors, compared with the allocated alpha of 0.05. | <0.00001 | |
| OS | N = 410 | N = 202 |
| Number of deaths (%) | 130 (32) | 85 (42) |
| Median, months (95% CI) | 21.9 (18.3, 31.0) | 17.4 (13.6, 19.9) |
| Hazard ratio (95% CI) | 0.66 (0.50, 0.87) | |
| P-valueTwo-sided p-value based on re-randomization procedure (Rosenberger and Lachin 2002) controlling for stratification factors, compared with the allocated alpha of 0.0074 for this interim analysis (with 60% of the planned number of events for final analysis). | 0.00480 | |
| PFSBrainMets Analysis includes patients with history or presence of parenchymal brain metastases at baseline, including target and non-target lesions. Does not include patients with dural lesions only. | N = 198 | N = 93 |
| Number of events (%) | 106 (53.5) | 51 (54.8) |
| Median, months (95% CI) | 7.6 (6.2, 9.5) | 5.4 (4.1, 5.7) |
| Hazard ratio (95% CI) | 0.48 (0.34, 0.69) | |
| P-valueTwo-sided p-value based on re-randomization procedure (Rosenberger and Lachin 2002) controlling for stratification factors, compared with the allocated alpha of 0.0080 for this interim analysis (with 71% of the planned number of events for final analysis). | <0.00001 | |
| Confirmed ORR for Patients with Measurable Disease | N = 340 | N = 171 |
| ORR (95% CI)Two-sided 95% exact confidence interval, computed using the Clopper-Pearson method (1934). | 40.6 (35.3, 46.0) | 22.8 (16.7, 29.8) |
| CR (%) | 3 (0.9) | 2 (1.2) |
| PR (%) | 135 (39.7) | 37 (21.6) |
| P-value | 0.00008 | |
| DOR | ||
| Median, months (95% CI)Calculated using the complementary log-log transformation method (Collett, 1994). | 8.3 (6.2, 9.7) | 6.3 (5.8, 8.9) |
Figure 2: Kaplan-Meier Plot of PFS per BICR in HER2CLIMB
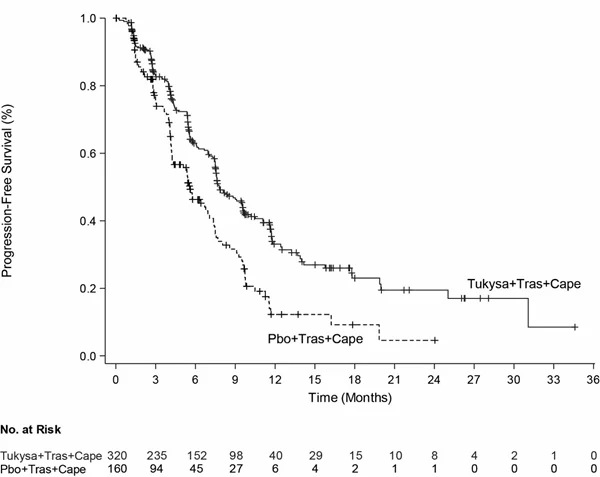
Figure 3: Kaplan-Meier Plot of Overall Survival in HER2CLIMB
14.2 HER2-Positive Metastatic Colorectal Cancer
The efficacy of TUKYSA in combination with trastuzumab was evaluated in 84 patients in MOUNTAINEER (NCT03043313), an open-label, multicenter trial. Patients were required to have HER2-positive, RAS wild-type, unresectable or metastatic colorectal cancer and prior treatment with fluoropyrimidines, oxaliplatin, irinotecan, and anti-vascular endothelial growth factor (VEGF) monoclonal antibody (mAb). Patients whose disease had deficient mismatch repair (dMMR) proteins or microsatellite instability-high (MSI-H) must have also received an anti-programmed cell death protein-1 (PD-1) mAb. Patients who received prior anti-HER2 targeting therapy were excluded. HER2 positivity as defined by HER2 overexpression or gene amplification was prospectively determined in local laboratories using immunohistochemistry (IHC), in situ hybridization (ISH), and/or next generation sequencing (NGS) on tumor tissue. RAS status was performed as standard of care prior to study entry based on expanded RAS testing including KRAS exons 2, 3, and 4 and NRAS exons 2, 3, and 4.
The median age was 55 years (range: 24 to 77); 12 (14%) patients were age 65 or older. Seventy-seven percent of patients were White, 4% were Black, 4% were Asian, and 4% were Hispanic or Latino. Sixty-one percent of patients were male. Seventy percent of patients had lung metastases, 64% had liver metastases, 60% had an ECOG performance status of 0, 37% had an ECOG performance status of 1, and 4% had an ECOG performance status of 2. Ninety-nine percent of patients received prior treatment with fluoropyrimidine, oxaliplatin, and irinotecan and 83% and 52% received anti-VEGF antibodies and anti-EGFR antibodies respectively; 23%, 38%, and 39% received 1, 2, or ≥3 prior lines of therapy, respectively.
Patients received TUKYSA 300 mg orally twice per day with a loading dose of trastuzumab or a non-U.S. approved trastuzumab product 8 mg/kg intravenously on Day 1 of Cycle 1, followed by a maintenance dose of trastuzumab 6 mg/kg on Day 1 of each subsequent 21-day cycle. Patients were treated until disease progression or unacceptable toxicity.
The major efficacy outcome measures were overall response rate (ORR) and duration of response (DOR) as assessed by BICR according to RECIST version 1.1.
Efficacy results are summarized in Table 17.
Table 17: Efficacy Results in MOUNTAINEER
TUKYSA + trastuzumab N = 84 | |
| Overall Response Rate (%) (95% CI) | 38 (28, 49) |
| CR (%) | 3 (3.6) |
| PR (%) | 29 (35) |
| Duration of Response | N = 32 |
| MedianBased on Kaplan-Meier method., months (95% CI) | 12.4 (8.5, 20.5) |
| Patients with DOR≥6 monthsBased on observed duration of response. | 81% |
| Patients with DOR≥12 months | 34% |
16 HOW SUPPLIED/STORAGE AND HANDLING
16.1 How Supplied
TUKYSA 50 mg tablets are supplied as yellow, film-coated, round tablets containing 50 mg of tucatinib. Each tablet is debossed with “TUC” on one side and “50” on the other side, and is packaged as follows:
50 mg tablets: bottle of 60 tablets (NDC 51144-001-60)
TUKYSA 150 mg tablets are supplied as yellow, film-coated, oval-shaped tablets containing 150 mg of tucatinib. Each tablet is debossed with “TUC” on one side and “150” on the other side, and is packaged as follows:
150 mg tablets: bottle of 60 tablets (NDC 51144-002-60)
150 mg tablets: bottle of 120 tablets (NDC 51144-002-12)
Store at controlled room temperature at 20ºC to 25ºC (68ºF to 77ºF); excursions permitted from 15ºC to 30ºC (59ºF to 86ºF) [see USP Controlled Room Temperature].
Dispense to patient in original container only. Store in original container to protect from moisture. Replace cap securely each time after opening. Do not discard desiccant.
Once opened, use within 3 months. Discard any unused tablets 3 months after opening the bottle.
17 PATIENT COUNSELING INFORMATION
Advise the patient to read the FDA-approved patient labeling (Medication Guide).
Hepatotoxicity
- Inform patients that TUKYSA can cause severe and fatal hepatotoxicity, particularly after rechallenge, and that they should report signs and symptoms of liver dysfunction to their healthcare provider immediately [see Warnings and Precautions (5.1)].
Diarrhea
- Inform patients that TUKYSA can cause severe diarrhea including dehydration, hypotension, acute kidney injury and death. Instruct patients on how to manage diarrhea and to inform their healthcare provider immediately if there is any change in bowel patterns [see Warnings and Precautions (5.2)].
Embryo-Fetal Toxicity
- Inform pregnant women and females of reproductive potential of the risk to a fetus. Advise females to inform their healthcare provider of a known or suspected pregnancy [see Warnings and Precautions (5.3) and Use in Specific Populations (8.1)].
- Advise females of reproductive potential to use effective contraception during treatment with TUKYSA and for 1 week after the last dose [see Use in Specific Populations (8.3)].
- Advise male patients with female partners of reproductive potential to use effective contraception during treatment with TUKYSA and for 1 week after the last dose [see Use in Specific Populations (8.3)].
- Refer to the Prescribing Information of combination agents for pregnancy and contraception information. When TUKYSA is used in combination, advise patients to use effective contraception during treatment and for the longest post-treatment duration recommended in the Prescribing Information of any of the individual products.
Lactation
- Advise women not to breastfeed during treatment with TUKYSA and for 1 week after the last dose [see Use in Specific Populations (8.2)]. Refer to the Prescribing Information of combination agents for lactation information. When TUKYSA is used in combination, advise patients not to breastfeed during treatment and for the longest post-treatment duration recommended in the Prescribing Information of any of the individual products.
Infertility
- Advise males and females of reproductive potential that TUKYSA may impair fertility [see Use in Specific Populations (8.3)]. Refer to the Prescribing Information of combination agents for infertility information.

Manufactured for:
Seagen Inc.
Bothell, WA 98021
1-855-4SEAGEN
TUKYSA, Seagen, and  are US registered trademarks of Seagen Inc.
© 2026 Seagen Inc., Bothell, WA 98021. All rights reserved.
This product’s labeling may have been updated. For the most recent prescribing information, please visit www.pfizer.com.
LAB-1593-1.0