


Prescribing information (package insert) - Ojemda
1 INDICATIONS AND USAGE
OJEMDA is indicated for the treatment of patients 6 months of age and older with relapsed or refractory pediatric low-grade glioma (LGG) harboring a BRAF fusion or rearrangement, or BRAF V600 mutation.
This indication is approved under accelerated approval based on response rate and duration of response [see Clinical Studies (14)]. Continued approval for this indication may be contingent upon verification and description of clinical benefit in a confirmatory trial(s).
2 DOSAGE AND ADMINISTRATION
2.1 Patient Selection
Select patients for treatment with OJEMDA based on the presence of BRAF fusion or rearrangement, or BRAF V600 mutation in tumor specimens [see Clinical Studies (14)].
Information on FDA-approved tests for the detection of BRAF fusions, BRAF rearrangements, and BRAF V600 mutations is available at http://www.fda.gov/companiondiagnostics.
2.2 Recommended Testing Before Initiating OJEMDA
Before initiating OJEMDA, evaluate liver function tests, including ALT, AST and bilirubin [see Warnings and Precautions (5.3)].
2.3 Recommended Dosage
The recommended dosage of OJEMDA based on body surface area (BSA) is 380 mg/m2 orally once weekly (the maximum recommended dosage is 600 mg orally once weekly) with or without food [see Administration (2.4) and Clinical Pharmacology (12.3)] until disease progression or intolerable toxicity. OJEMDA may be administered as an immediate release tablet (see Table 1) or as an oral suspension (see Table 2). A recommended dosage for patients with BSA less than 0.3 m2 has not been established.
Table 1 Recommended OJEMDA Tablets Dosage Based on Body Surface Area
| Body Surface Area (m2) | Recommended Dosage |
|---|---|
| 0.30-0.89 | Administer OJEMDA oral suspension once weekly (see Table 2) |
| 0.90-1.12 | 400 mg once weekly |
| 1.13-1.39 | 500 mg once weekly |
| ≥ 1.40 | 600 mg once weekly |
Table 2 Recommended Dosage for OJEMDA for Oral Suspension Based on Body Surface Area
| Body Surface Area (m2) | Dose Volume (mL)OJEMDA for oral suspension has a concentration of 25 mg/mL. Each bottle of OJEMDA for oral suspension delivers 300 mg/12 mL. | Dosage |
|---|---|---|
| 0.30-0.35 | 5 | 125 mg once weekly |
| 0.36-0.42 | 6 | 150 mg once weekly |
| 0.43-0.48 | 7 | 175 mg once weekly |
| 0.49-0.54 | 8 | 200 mg once weekly |
| 0.55-0.63 | 9 | 225 mg once weekly |
| 0.64-0.77 | 11 | 275 mg once weekly |
| 0.78-0.83 | 12 | 300 mg once weekly |
| 0.84-0.89 | 14 | 350 mg once weekly |
| 0.90-1.05 | 15 | 375 mg once weekly |
| 1.06-1.25 | 18 | 450 mg once weekly |
| 1.26-1.39 | 21 | 525 mg once weekly |
| ≥1.40 | 24 | 600 mg once weekly |
Continue once weekly dosing until disease progression or intolerable toxicity.
2.4 Administration
- Take OJEMDA at a regularly scheduled time once weekly.
- OJEMDA may be taken with or without food [see Clinical Pharmacology (12.3)].
If a dose is missed by:
- 3 days or less, take the missed dose as soon as possible, and take the next dose on its regularly scheduled day.
- more than 3 days, skip the missed dose and take the next dose on its regularly scheduled day.
If vomiting occurs immediately after taking a dose, repeat that dose.
OJEMDA tablets
- Swallow tablets whole with water.
- Do not chew, cut, or crush.
OJEMDA for oral suspension
- Prior to first time use of OJEMDA for oral suspension, ensure that caregivers (and if appropriate, patients) read and understand the "Instructions for Use" before preparing, measuring, and administering OJEMDA.
Preparation and Administration
- Reconstitute the powder in each supplied bottle with exactly 14 mL of room temperature water to form the OJEMDA for oral suspension. After reconstitution each mL contains 25 mg of tovorafenib. Product foaming after reconstitution reduces the deliverable volume.
- Each bottle delivers 300 mg of tovorafenib in 12 mL. For doses greater than 300 mg, reconstitute two bottles to achieve the dose. Split the dose as equally as possible between the two bottles (e.g., 6 mL and 7 mL for a 325 mg dose). Prepare the first bottle and administer dose prior to preparing the second bottle.
- Administer OJEMDA for oral suspension using the supplied oral dosing syringe or feeding tube (minimum 12 French) immediately after preparation.
- If the OJEMDA for oral suspension is not administered within 15 minutes after preparation, instruct the patient to discard it.
2.5 Dosage Modifications for Adverse Reactions
The recommended dosage reductions for adverse reactions for OJEMDA tablets are provided in Table 3 and OJEMDA for oral suspension in Table 4.
Table 3 OJEMDA Tablets: Recommended Dosage Reductions for Adverse Reactions
| BSA (m2) | First Dosage Reduction | Second Dosage Reduction |
|---|---|---|
| 0.30-1.12 | Administer the oral suspension once weekly (see Table 4) | |
| 1.13-1.39 | 400 mg once weekly | Administer OJEMDA oral suspension once weekly (see Table 4) |
| ≥1.40 | 500 mg once weekly | 400 mg once weekly |
Table 4 OJEMDA for Oral Suspension: Recommended Dosage Reductions for Adverse Reactions
| BSA (m2) | First Dosage Reduction | Second Dosage Reduction | ||
|---|---|---|---|---|
| Volume (mL) | Dose (mg) | Volume (mL) | Dose (mg) | |
| 0.30-0.35 | 4 | 100 mg once weekly | 3 | 75 mg once weekly |
| 0.36-0.42 | 5 | 125 mg once weekly | 4 | 100 mg once weekly |
| 0.43-0.48 | 6 | 150 mg once weekly | 5 | 125 mg once weekly |
| 0.49-0.54 | 7 | 175 mg once weekly | 6 | 150 mg once weekly |
| 0.55-0.63 | 8 | 200 mg once weekly | 6 | 150 mg once weekly |
| 0.64-0.77 | 9 | 225 mg once weekly | 8 | 200 mg once weekly |
| 0.78-0.83 | 10 | 250 mg once weekly | 8 | 200 mg once weekly |
| 0.84-0.89 | 12 | 300 mg once weekly | 10 | 250 mg once weekly |
| 0.90-1.05 | 13 | 325 mg once weekly | 11 | 275 mg once weekly |
| 1.06-1.25 | 15 | 375 mg once weekly | 13 | 325 mg once weekly |
| 1.26-1.39 | 18 | 450 mg once weekly | 15 | 375 mg once weekly |
| ≥1.40 | 20 | 500 mg once weekly | 16 | 400 mg once weekly |
The recommended dosage modifications of OJEMDA for adverse reactions are in Table 5.
Table 5 Recommended Dosage Modifications for Adverse Reactions
| Severity of ADRNational Cancer Institute Common Terminology Criteria for Adverse Events (NCI CTCAE) version 5.0. | Dosage ModificationSee Table 3 and Table 4 for recommended dosage reductions. |
|---|---|
| Hemorrhage [see Warnings and Precautions (5.1)] | |
| Withhold OJEMDA.
|
| Withhold OJEMDA.
OR
|
| Permanently discontinue OJEMDA. |
| Skin Toxicity including Photosensitivity [see Warnings and Precautions (5.2)] | |
| Withhold OJEMDA.
|
| Hepatotoxicity [see Warnings and Precautions (5.3)] | |
| Withhold OJEMDA. If improved to Grade ≤ 2 or baseline, resume as follows:
|
| Withhold OJEMDA.
OR
|
| Permanently discontinue OJEMDA. |
| Other Adverse Reactions [see Adverse Reactions (6.1)] | |
| Withhold OJEMDA.
|
| Withhold OJEMDA.
OR
|
| Permanently discontinue OJEMDA. |
3 DOSAGE FORMS AND STRENGTHS
Tablets:
- 100 mg: orange, film-coated, oval tablets debossed with "100"; on one side and "D101" on the opposite side. Each tablet contains 100 mg of tovorafenib.
For Oral Suspension:
- 25 mg/mL: white to off white powder. After reconstitution, each mL of strawberry flavored tovorafenib suspension contains 25 mg of tovorafenib. Each bottle delivers 300 mg of tovorafenib in 12 mL.
4 CONTRAINDICATIONS
None.
5 WARNINGS AND PRECAUTIONS
5.1 Hemorrhage
Hemorrhage, including major hemorrhage defined as symptomatic bleeding in a critical area or organ, can occur with OJEMDA. In the pooled safety population [see Adverse Reactions (6.1)], hemorrhagic events occurred in 37% of patients, including epistaxis in 26% and intratumoral hemorrhage in 9%. Serious events of bleeding occurred in 5% of patients including Grade 5 tumor hemorrhage in 1 patient (0.6%). OJEMDA was permanently discontinued for hemorrhage in 2% of patients.
Advise patients and caregivers of the risk of hemorrhage during treatment with OJEMDA. Monitor for signs and symptoms of hemorrhage and evaluate as clinically indicated. Withhold and resume at reduced dose upon improvement, or permanently discontinue based on severity [see Dosage and Administration (2.5)].
5.2 Skin Toxicity Including Photosensitivity
OJEMDA can cause rash, including maculopapular rash and photosensitivity. In the pooled safety population [see Adverse Reactions (6.1)], rash occurred in 67% of patients treated with OJEMDA, including Grade 3 rash in 12%. Rash resulted in dose interruption in 15% of patients and dose reduction in 7% of patients. OJEMDA was permanently discontinued due to rash in 1% of patients (n=2). In the pooled safety population, dermatitis acneiform occurred in 26% of patients treated with OJEMDA, including Grade 3 dermatitis acneiform in 0.6% of patients (n=1). Dose reduction was required in 2% of patients (n=3) due to dermatitis acneiform.
Monitor for new or worsening skin reactions. Consider dermatologic consultation and initiate supportive care as clinically indicated. Withhold, reduce the dose, or permanently discontinue OJEMDA based on severity of adverse reaction [see Dosage and Administration (2.5)].
Photosensitivity
In the pooled safety population [see Adverse Reactions (6.1)], photosensitivity occurred in 12% of patients treated with OJEMDA, including Grade 3 events in 0.6% of patients (n=1). Advise patients to use precautionary measures against ultraviolet exposure such as use of sunscreen, sunglasses, and/or protective clothing during treatment with OJEMDA. Withhold, reduce the dose, or permanently discontinue OJEMDA based on severity of adverse reaction [see Dosage and Administration (2.5)].
5.3 Hepatotoxicity
OJEMDA can cause hepatotoxicity. In the pooled safety population [see Adverse Reactions (6.1)], increased alanine aminotransferase (ALT) occurred in 42% and increased aspartate aminotransferase (AST) occurred in 74%, including Grade 3 ALT in 4% and increased AST in 2% of patients treated with OJEMDA. The median time to onset of increased ALT or AST was 14 days (range: 3 to 280 days). Increased ALT or AST leading to dose interruption occurred in 5% of patients and dose reductions were required in 1.2% of patients. Increased bilirubin occurred in 23% of patients, including Grade 3 increased bilirubin in 0.6% of patients (n=1) treated with OJEMDA. Hyperbilirubinemia leading to dose discontinuation occurred in a single adult patient with an advanced non-CNS solid tumor.
Monitor liver function tests, including ALT, AST and bilirubin, before initiation of OJEMDA, one month after initiation and then every three months thereafter and as clinically indicated. Withhold and resume at the same or reduced dose upon improvement, or permanently discontinue OJEMDA based on the severity [see Dosage and Administration (2.5)].
5.4 Effect on Growth
OJEMDA can cause reductions in growth velocity. In FIREFLY-1 [see Adverse Reactions (6.1)], treatment-emergent adverse effects on growth were reported in 46% of 133 patients 18 years of age or younger; 35% were Grade 3 or higher. Reduction in growth velocity resulted in dose interruption in 5% of patients, dose reduction in 2.3% of patients, and permanent discontinuation in 3% of patients. The median change from baseline in height percentile was -14 (z-score change -0.6) for evaluable patients on study for 12 months (N=107) and -20 (z-score change -0.9) for evaluable patients on study for 18 months (N=95).
Growth velocity improved after interruption of treatment with OJEMDA. Among 81 evaluable patients, the median annualized growth velocity ranged from 0.86 to 1.8 cm/year during the 2-year treatment period. Of those, 17 patients had height measurements recorded at least 90 days off-treatment and had a 4.2 cm/year median annualized growth velocity. Routinely monitor patient growth during treatment with OJEMDA [see Adverse Reactions (6), Use in Specific Populations (8.4)].
5.5 Embryo-Fetal Toxicity
Based on findings from animal studies and its mechanism of action, OJEMDA may cause fetal harm when administered to a pregnant woman. Tovorafenib was embryo lethal in rats at doses approximately 0.8-fold the human exposure at the recommended dose based on area under the curve (AUC). Advise pregnant women and females of reproductive potential of the potential risk to a fetus. Advise females of reproductive potential to use effective nonhormonal contraception during treatment with OJEMDA and for 28 days after the last dose, since OJEMDA can render some hormonal contraceptives ineffective [see Drug Interactions (7.2)]. Advise male patients with female partners of reproductive potential to use effective contraception during treatment with OJEMDA and for 2 weeks after the last dose [see Use in Specific Populations (8.1, 8.3)].
5.6 NF1 Associated Tumors
Based on nonclinical data in NF1 models without BRAF alterations, tovorafenib may promote tumor growth in patients with NF1 tumors [see Nonclinical Toxicology (13.2)]. Confirm evidence of a BRAF alteration prior to initiation of treatment with OJEMDA.
6 ADVERSE REACTIONS
The following clinically significant adverse reactions are described elsewhere in the labeling:
- Hemorrhage [see Warnings and Precautions (5.1)]
- Skin Toxicity Including Photosensitivity [see Warnings and Precautions (5.2)]
- Hepatotoxicity [see Warnings and Precautions (5.3)]
- Effect on Growth [see Warnings and Precautions (5.4)]
6.1 Clinical Trials Experience
Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice.
The safety population described in WARNINGS AND PRECAUTIONS reflects exposure to OJEMDA taken orally once weekly at a dose based on body surface area [see Clinical Studies (14)] in 140 patients with relapsed or refractory pediatric LGG or advanced solid tumors harboring a RAF alteration and a flat dose of 600 mg in 32 adult patients with advanced solid tumors until disease progression or intolerable toxicity. Among 172 patients treated with OJEMDA, 86% were exposed for 6 months or longer and 49% were exposed for 1 year or longer.
Pediatric Low-grade Glioma
The safety of OJEMDA was evaluated in 137 patients with relapsed or refractory pediatric LGG harboring a BRAF alteration in FIREFLY-1 (Arms 1 and 2) [see Clinical Studies (14)]. Patients received OJEMDA at a dose based on body surface area [see Dosage and Administration (2.3] orally once weekly until disease progression or intolerable toxicity.
The median age of patients was 9 years (range 1 to 24 years); 53% male; 58% White, 7% Asian, 2% Black or African American, 6% other races, 25% race was not reported; 2.9% were Hispanic or Latino; and 90% Karnofsky/Lansky performance status of 80 to 100.
Serious adverse reactions occurred in 45% of patients who received OJEMDA. Serious adverse reactions in >2% of patients included viral infection (9%), pneumonia (4%), and sepsis (4%). A fatal adverse reaction of tumor hemorrhage occurred in 1 patient (1%).
Permanent discontinuation of OJEMDA due to an adverse reaction occurred in 7% of patients. Adverse reactions which resulted in permanent discontinuation of OJEMDA in more than one patient were tumor hemorrhage and reduction in growth velocity.
Dosage interruptions of OJEMDA due to an adverse reaction occurred in 57% of patients. Adverse reactions which required dose interruption in ≥5% of patients included rash, pyrexia, vomiting, and hemorrhage.
Dosage reductions of OJEMDA due to an adverse reaction occurred in 24% of patients. Adverse reactions which required dose reduction in ≥2% of patients included rash, and fatigue.
The most common adverse reactions (≥30%) were rash, hair color changes, fatigue, viral infection, vomiting, headache, hemorrhage, pyrexia, dry skin, constipation, nausea, dermatitis acneiform, and upper respiratory tract infection.
The most common Grade 3 or 4 laboratory abnormalities (≥2%) were decreased phosphate, decreased hemoglobin, increased creatine phosphokinase, increased alanine aminotransferase, decreased albumin, decreased lymphocytes, decreased leukocytes, increased aspartate transferase, decreased potassium, and decreased sodium.
Table 6 and Table 7 present adverse reactions and laboratory abnormalities, respectively, identified in FIREFLY-1 (Arms 1 and 2).
Table 6 Adverse Reactions (≥20%) in Patients with Pediatric LGG Who Received OJEMDA in FIREFLY-1 (Arms 1 and 2)
| Adverse Reaction | OJEMDA (N=137) | |
|---|---|---|
| All Grades (%) | Grade 3 or 4 (%) | |
| Skin and Subcutaneous Tissue Disorders | ||
| RashIncludes terms erythema multiforme, eczema, rash erythematous, rash macular, rash follicular, rash pruritic, rash maculopapular, rash, rash papular, rash pustular, skin exfoliation, drug eruption, dermatitis, dermatitis bullous. | 77 | 12 |
| Hair color changes | 76 | 0 |
| Dry skin | 36 | 0 |
| Dermatitis acneiform | 31 | 1 |
| Pruritus | 26 | 1 |
| General Disorders | ||
| Fatigue | 55 | 4 |
| Pyrexia | 39 | 4 |
| EdemaIncludes terms lip edema, periorbital edema, edema peripheral, localized edema, face edema, vulval edema. | 26 | 0 |
| Infections and Infestations | ||
| Viral infectionIncludes terms viral infection, rhinovirus infection, enterovirus infection, viral upper respiratory tract infection, enterocolitis viral, oral herpes, gastroenteritis viral, influenza, influenza like illness, respiratory syncytial virus infection, enterovirus infection, coronavirus infection, COVID-19, SARS-COV-2 test positive, herpes simplex, parainfluenza virus infection, adenoviral upper respiratory infection, viraemia, adenovirus infection, conjunctivitis viral, eye infection viral, metapneumovirus infection, parvovirus infection, respiratory syncytial virus bronchiolitis, respiratory tract infection viral, viral pharyngitis, viral rhinitis, viral tonsillitis. | 55 | 7 |
| Upper respiratory tract infection | 31 | 1.5 |
| Paronychia | 26 | 1.5 |
| Gastrointestinal Disorders | ||
| VomitingIncludes terms retching, hematemesis. | 50 | 4 |
| Constipation | 33 | 0 |
| Nausea | 33 | 0 |
| Abdominal pain | 28 | 0 |
| DiarrheaIncludes terms colitis, enterocolitis. | 22 | 1.5 |
| StomatitisIncludes terms mouth ulceration, mucosal inflammation, aphthous ulcer, cheilitis. | 20 | 0 |
| Nervous system disorders | ||
| Headache | 45 | 1 |
| Vascular Disorders | ||
| HemorrhageIncludes terms tumor hemorrhage, gastrointestinal hemorrhage, subdural hemorrhage, epistaxis, intracranial tumor hemorrhage, upper gastrointestinal hemorrhage, lower gastrointestinal hemorrhage, vaginal hemorrhage, gingival bleeding, post procedural hemorrhage, hemoptysis, anal hemorrhage. | 42 | 5Includes one Grade 5 event. |
Other clinically important adverse reactions observed in <20% of patients treated with OJEMDA were reductions in growth velocity [see Warnings and Precautions (5.4)] skin discoloration, myalgia, photosensitivity reaction [see Warnings and Precautions (5.2)], and arthralgia.
Table 7 Select Laboratory Abnormalities (≥20%) that Worsened from Baseline in Patients with Pediatric LGG Who Received OJEMDA in FIREFLY-1 (Arms 1 and 2)
| Laboratory AbnormalitySeverity as defined by National Cancer Institute CTCAE v5.0 | OJEMDAThe denominator for each laboratory parameter is based on the number of patients with a baseline and post-treatment laboratory value available which ranged from 67 to 137 patients. | |
|---|---|---|
| All Grades (%) | Grade 3 or 4 (%) | |
| Hematology | ||
| Decreased hemoglobin | 90 | 15 |
| Decreased lymphocytes | 50 | 2 |
| Decreased leukocytes | 31 | 2 |
| Increased lymphocytes | 23 | 0 |
| Chemistry | ||
| Decreased phosphate | 87 | 25 |
| Increased AST | 83 | 2 |
| Increased creatine phosphokinase | 83 | 11 |
| Increased LDH | 73 | 0 |
| Decreased potassium | 51 | 2 |
| Increased ALT | 50 | 5 |
| Increased bilirubin | 22 | 1 |
| Decreased albumin | 24 | 5 |
| Decreased sodium | 20 | 2 |
Increased creatine phosphokinase was a clinically important laboratory abnormality that worsened from baseline in patients treated with OJEMDA.
7 DRUG INTERACTIONS
7.1 Effects of Other Drugs on OJEMDA
Table 8 describes drug interactions where coadministration with another drug affects OJEMDA.
Table 8 Coadministration with Other Drugs that Affect the Use of OJEMDA
| Strong or Moderate CYP2C8 Inhibitors | |
| Prevention or Management |
|
| Mechanism and Clinical Effect(s) |
|
| Strong or Moderate CYP2C8 Inducers | |
| Prevention or Management |
|
| Mechanism and Clinical Effect(s) |
|
7.2 Effects of OJEMDA on Other Drugs
Table 9 describes drug interactions where coadministration with OJEMDA affects another drug.
Table 9 Coadministration with OJEMDA that Affects the Use of Other Drugs
| CYP3A Substrates | |
| Prevention or Management |
|
| Mechanism and Clinical Effect(s) |
|
8 USE IN SPECIFIC POPULATIONS
8.1 Pregnancy
Risk Summary
Based on findings from animal studies and its mechanism of action [see Clinical Pharmacology (12.1)], OJEMDA can cause fetal harm when administered to a pregnant woman. There are no available data on the use of OJEMDA in pregnant women. Oral administration of tovorafenib to pregnant rats during the period of organogenesis resulted in embryo lethality at exposures 0.8 times the human exposure at the recommended dose based on AUC (see Data ). Advise pregnant women of the potential risk to a fetus. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Data
Animal Data
In an embryo-fetal development study, once daily oral administration of tovorafenib to pregnant rats during the period of organogenesis from gestation days 7 through 17 at doses of 37.5, 75, and 150 mg/kg resulted in early resorptions and total litter loss at all doses. The dose of 37.5 mg/kg/day is approximately 0.8-fold the human exposure at the recommended dose based on AUC.
8.2 Lactation
Risk Summary
There are no data on the presence of tovorafenib or its metabolites in human milk, their effects on the breastfed child, or on milk production. Due to the potential for serious adverse reactions in breastfed children from OJEMDA, advise lactating women not to breastfeed during treatment with OJEMDA and for 2 weeks following the last dose.
8.3 Females and Males of Reproductive Potential
OJEMDA can cause fetal harm when administered to pregnant women [see Use in Specific Populations (8.1)].
Pregnancy Testing
Verify pregnancy status in females of reproductive potential prior to initiating OJEMDA [see Use in Specific Populations (8.1)].
Contraception
Females
Advise females of reproductive potential to use effective nonhormonal contraception during treatment with OJEMDA and for 28 days after the last dose. OJEMDA can render hormonal contraceptives ineffective [see Drug Interactions (7.2)].
Males
Advise male patients with female partners of reproductive potential to use effective contraception during treatment with OJEMDA and for 2 weeks after the last dose.
Infertility
Based on findings in animals, OJEMDA may impact fertility in males and females of reproductive potential. The effects on male animal fertility were reversible. The effects on female animal fertility were not reversible [see Nonclinical Toxicology (13.1)].
8.4 Pediatric Use
The safety and effectiveness of OJEMDA in pediatric patients 6 months of age and older with relapsed or refractory pediatric LGG harboring a BRAF fusion or rearrangement, or BRAF V600 mutation have been established based on data from a multicenter, open-label, single-arm clinical trial [see Clinical Studies (14)].
The efficacy of OJEMDA was evaluated in 76 patients with relapsed or refractory pediatric LGG. The safety of OJEMDA was evaluated in 137 patients with relapsed or refractory pediatric LGG in FIREFLY-1 (Arms 1 and 2). Of these 137 patients, 2% (n=3) were 6 month to < 2 years of age, 67% (n=92) were 2 years to < 12 years of age, and 31% (n=42) were >12 years of age [see Adverse Reactions (6.1)]. Cmax and AUC in pediatric patients aged 11 months to 17 years were within the range of values observed in adults given the same dose per body surface area.
The safety and effectiveness of OJEMDA in patients younger than 6 months of age have not been established.
Effect on Growth
Patients with pediatric LGG treated with OJEMDA for up to 24 months showed reductions from baseline in Z-scores for height compared to age and sex-matched normative data. Among 35 patients who experienced reductions in growth velocity who had hand radiographs taken to assess bone age, there was no evidence of premature closure of the epiphyseal growth plates or advancement of bone age. Patients followed after interruption of treatment with OJEMDA showed recovery of growth and increase in Z-scores. Monitor growth routinely during treatment [see Warnings and Precautions (5.4)].
8.6 Hepatic Impairment
No dose adjustment is recommended for patients with mild (bilirubin ≤ upper limit of normal (ULN) and aspartate aminotransferase (AST) > ULN or bilirubin > 1× to 1.5× ULN and any AST) hepatic impairment. OJEMDA has not been studied in patients with moderate (bilirubin > 1.5× to 3× ULN and any AST) to severe (bilirubin > 3× ULN and any AST) hepatic impairment [see Clinical Pharmacology (12.3)].
8.7 Renal Impairment
No dose adjustment is recommended for patients with mild-to-moderate renal impairment (eGFR ≥ 30 mL/min/1.73 m2 calculated by Schwartz equation or MDRD equation). OJEMDA has not been studied in patients with severe renal impairment (eGFR <30 mL/min/1.73 m2) [see Clinical Pharmacology (12.3)].
11 DESCRIPTION
OJEMDA contains tovorafenib, a kinase inhibitor. Tovorafenib has the molecular formula C17H12Cl2F3N7O2S and a molecular weight of 506.29. The chemical name for tovorafenib is 6-amino-5-chloro-N-[(1R)-1-[5-[[[5-chloro-4-(trifluoromethyl)-2-pyridinyl]amino]carbonyl]-2-thiazolyl]ethyl]-4-pyrimidinecarboxamide. Tovorafenib has the following chemical structure:
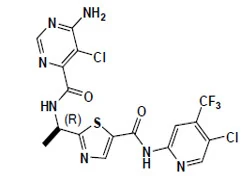
It is a white to off-white powder. The solubility of tovorafenib at 37ºC is ≤ 3 micrograms/mL from pH 1.2 to 8 in aqueous media.
OJEMDA (tovorafenib) tablets are supplied as 100 mg strength tablets for oral administration. Each tablet contains 100 mg tovorafenib and the following inactive ingredients: copovidone, colloidal silicon dioxide, croscarmellose sodium, magnesium stearate, microcrystalline cellulose, and orange film coating (hypromellose, polyethylene glycol 8000, titanium dioxide, ferric oxide yellow, ferric oxide red).
OJEMDA (tovorafenib) for oral suspension is a white to off white powder which produces a white suspension when reconstituted with water. Each mL of reconstituted tovorafenib suspension contains 25 mg of tovorafenib and the following inactive ingredients: artificial strawberry flavor, colloidal silicon dioxide, copovidone, maltodextrin, mannitol, microcrystalline cellulose, simethicone, sodium lauryl sulfate, and sucralose.
12 CLINICAL PHARMACOLOGY
12.1 Mechanism of Action
Tovorafenib is a Type II RAF kinase inhibitor of mutant BRAF V600E, wild-type BRAF, and wild-type CRAF kinases.
Tovorafenib exhibited antitumor activity in cultured cells and xenograft tumor models harboring BRAF V600E and V600D mutations, and in a xenograft model harboring a BRAF fusion.
12.2 Pharmacodynamics
Exposure Response Relationships
Tovorafenib exposure is associated with reduction in height-for-age z-scores in pediatric patients. Reduced height-for-age risk persists during treatment with tovorafenib.
Higher tovorafenib exposure is associated with increased risk of skin rash, elevated liver enzymes (AST and ALT), and elevated creatine phosphokinase.
The exposure-response relationship for overall response rate based on RAPNO-LGG (Response Assessment in Pediatric Neuro-Oncology), and RANO-LGG (Response Assessment in Neuro-Oncology) were not clinically significant over the dosage range of 290 to 476 mg/m2 (0.76-1.25 times the approved recommended dosage) [see Dosage and Administration (2.3) and Clinical Studies (14)].
Cardiac Electrophysiology
At the recommended OJEMDA dosage of 380 mg/m2 orally once weekly (not to exceed 600 mg), a mean increase in the QT interval >20 milliseconds was not observed.
12.3 Pharmacokinetics
Tovorafenib pharmacokinetic parameters are presented as mean (CV%) unless otherwise indicated. Tovorafenib steady state maximum concentration (Cmax) is 6.9 µg/mL (23%) and the area under the concentration-time curve (AUC) is 508 µg*h/mL (31%). Time to reach steady state of tovorafenib is 12 days (33%). Tovorafenib exposure increases in a dose-proportional manner. No clinically significant tovorafenib accumulation occurs.
Absorption
Tovorafenib median (minimum, maximum) time to achieve peak plasma concentration (Tmax) is 3 hours (1.5, 4 hours), following a single dose with tablets or oral suspension.
Effect of Food
No clinically significant differences in tovorafenib Cmax and AUC were observed following administration of tablets with a high-fat meal (approximately 859 total calories, 54% fat) compared to fasted conditions, but the Tmax was delayed to 6.5 hours.
Distribution
Tovorafenib apparent volume of distribution is 60 L/m2 (23%). Tovorafenib is 97.5% bound to human plasma proteins in vitro.
Elimination
Tovorafenib terminal half-life is approximately 56 hours (33%) and the apparent clearance is 0.7 L/h/m2 (31%).
Metabolism
Tovorafenib is primarily metabolized by aldehyde oxidase and CYP2C8 in vitro. CYP3A, CYP2C9, and CYP2C19 metabolize tovorafenib to a minor extent.
Excretion
Following a single oral dose of radiolabeled tovorafenib, 65% of the total radiolabeled dose was recovered in the feces (8.6% unchanged) and 27% of the dose was recovered in the urine (0.2% unchanged).
Specific Populations
No clinically significant differences of tovorafenib were observed based on age (range: 1 to 94 years), sex, race (White, Black, Asian), mild hepatic impairment [bilirubin ≤ upper limit of normal (ULN) and AST > ULN or bilirubin > 1 to 1.5× ULN and any AST], and mild-to-moderate renal impairment (eGFR) ≥ 30 mL/min/1.73 m2 calculated by Schwartz equation or MDRD equation.
Drug Interaction Studies
Clinical Studies and Model-Informed Approaches
CYP3A Substrates: Midazolam (CYP3A4 substrate) steady-state Cmax and AUC are predicted to decrease by at least 20% following coadministration with tovorafenib.
In Vitro Studies
CYP450 Enzymes: Tovorafenib inhibits CYP2C8, CYP2C9, CYP2C19 and CYP3A, but does not inhibit CYP1A2, CYP2B6, and CYP2D6 at clinically relevant concentrations.
Tovorafenib induces CYP3A, CYP2C8, CYP1A2, CYP2B6, CYP2C9 and CYP2C19 at clinically relevant concentrations.
Transporter Systems: Tovorafenib is not a substrate of BCRP, P-glycoprotein (P-gp), OATP1B1 and OATP1B3. Tovorafenib has not been evaluated as a substrate of OAT1, OAT3, MATE1, MATE2-K and OCT2. Tovorafenib inhibits BCRP at clinically relevant concentrations.
13 NONCLINICAL TOXICOLOGY
13.1 Carcinogenesis, Mutagenesis, Impairment of Fertility
Tovorafenib was not carcinogenic in the 6-month study in transgenic rasH2 mice that received oral doses up to 100 mg/kg/day.
Tovorafenib was not mutagenic in the in vitro bacterial reverse mutation (Ames) assay. Tovorafenib was not genotoxic in cultured human lymphocytes without metabolic activation. Tovorafenib induced chromosomal aberrations in cultured human lymphocytes with metabolic activation at a single concentration in vitro. Tovorafenib was not genotoxic in an in vivo rat bone marrow micronucleus assay.
In a fertility and early embryonic development study in rats, animals were administered tovorafenib doses of 37.5, 75, or 150 mg/kg/day orally. Female animals, paired with untreated males, were dosed for 14 days prior to pairing, during the mating period, and up to Gestation Day 6. Tovorafenib decreased the number of pregnancies, corpora lutea, and live embryos, as well as increased post-implantation losses at all doses. The dose of 37.5 mg/kg/day is approximately 0.8-fold the human exposure at the recommended dose based on AUC.
In repeat- dose toxicology studies in rats of up to 3 months duration, tovorafenib-related findings in female rats included reversible increased thickness of the vaginal mucosa, increased size and/or numbers of corpora hemorrhagicum and hemorrhage, and non-reversible cystic follicles, decreased corpora lutea, and interstitial cell hyperplasia were observed in ovaries at doses ≥ 50 mg/kg once every other day (approximately 0.4-fold the human exposure at the recommended dose based on AUC). In male rats, tovorafenib reduced weights of epididymis and testes, which correlated with reversible tubular degeneration/atrophy of the testes and reduced epididymal sperm at doses ≥ 50 mg/kg once every other day (approximately 0.3-fold the human exposure at the recommended dose based on AUC).
13.2 Animal Toxicology and/or Pharmacology
In vitro, tovorafenib increased phosphorylation of ERK at clinically relevant concentrations in cells with neurofibromatosis Type 1-loss of function (NF1-LOF) suggesting activation, rather than inhibition, of the MAP kinase pathway. In an NF1 genetically engineered mouse model of plexiform neurofibroma without BRAF alteration, tovorafenib did not have antitumor activity, and while not statistically significant, an increase in tumor volume was noted in 2/12 mice (approximately 17%).
14 CLINICAL STUDIES
The efficacy of OJEMDA was evaluated in a multicenter, open-label, single-arm clinical trial (FIREFLY-1; NCT04775485). Eligible patients (N=76) were required to have a relapsed or refractory pediatric low-grade glioma (LGG) harboring an activating BRAF alteration based on local laboratory testing. Patients were also required to have at least one measurable lesion as defined by RANO 2010 criteria. All patients had received at least one line of prior systemic therapy and had documented evidence of radiographic progression. Patients with tumors harboring additional activating molecular alteration(s) (e.g., IDH1/2 mutations, FGFR mutations, etc.) or patients with known or suspected diagnosis of neurofibromatosis type 1 (NF1) were excluded.
Patients received OJEMDA approximately 420 mg/m2 orally once weekly (range: 290 to 476 mg/m2, 0.76-1.25 times the approved recommended dosage) according to body surface area with a maximum dose of 600 mg until disease progression or unacceptable toxicity. Although the OJEMDA dosages administered in FIREFLY-1 were between 290 mg/m2 to 476 mg/m2, the recommended OJEMDA dosage is 380 mg/m2 orally once weekly because this dosage was determined to be safe and effective for the treatment of patients 6 months of age and older with relapsed or refractory pediatric LGG harboring a BRAF fusion or rearrangement, or BRAF V600 mutation [see Dosage and Administration (2.3)].
Tumor assessments were performed every 12 weeks.
The major efficacy outcome measure was overall response rate (ORR), defined as the proportion of patients with complete response (CR), partial response (PR), or minor response (MR) by blinded independent central review based on RAPNO-LGG (Response Assessment in Pediatric Neuro-Oncology) criteria. Additional efficacy outcome measures were duration of response, time to response, and ORR by independent review based on RANO-LGG (2011) criteria.
The efficacy population included 76 patients who had measurable disease at baseline and who received OJEMDA. The median age was 8.5 years (range 2 to 21 years); 53% were male; 61% White, 7% Asian, 2.6% Black or African American, 3.9% multiple races, 8% other race, 18% where race was not reported; 3.9% were Hispanic or Latino, and 93% had Karnofsky/Lansky performance status of 80 to 100. Patients received a median of 3 prior systemic regimens (range: 1 to 9). Forty-five patients (59%) received prior treatment with a MAP kinase pathway inhibitor. The most common tumor locations were the optic pathway (51%), deep midline structures (12%), brain stem (8%), cerebellum (7%), and cerebral hemisphere (5%). Fifty-six patients (74%) had a KIAA1549:BRAF fusion, twelve patients (16%) had a V600E mutation, and eight patients (11%) had a BRAF alteration classified as "other" including BRAF duplication or BRAF rearrangement. Efficacy results are shown in Table 10.
Table 10 Efficacy Results in FIREFLY-1
| Efficacy Parameter | OJEMDAEfficacy Results Based on RAPNO-LGG criteria in FIREFLY-1 N=76At least one measurable lesion at baseline based on RAPNO-LGG criteria. |
|---|---|
| Abbreviations: LGG = low-grade glioma; RAPNO = Response Assessment in Pediatric Neuro-Oncology; CI = confidence interval. | |
| Overall Response Rate | |
| ORR (95% CI)Based on Clopper-Pearson exact confidence interval. | 53% (41, 64) |
| Partial Response (PR), n (%) | 29 (38) |
| Minor Response (MR), n (%) | 11 (14) |
| Duration of Response (DoR) | N=40 |
| Median (95% CI)Based on Kaplan-Meier estimate., Months | 18 (12.0, 22.8) |
| % with observed DoR ≥ 12 months | 65% |
| % with observed DoR ≥ 18 months | 50% |
Among responders, the median time to response was 5.4 months (range 1.6, 17.5). In exploratory analyses of BRAF alteration status, the ORR was 53% among patients with BRAF fusion or rearrangement (n=64), and 50% among patients with BRAF V600E mutation (n=12), respectively. In exploratory analyses of prior therapies, the ORR was 51% among patients who had received prior MAPK-targeted therapy (n=45), and 55% among patients who had not received prior MAPK-targeted therapy (n=31).
Based on RANO-LGG (2011) criteria (n=76), the ORR was 54% [95% CI: (42, 65)], including 23 patients with PR and 18 patients with MR.
16 HOW SUPPLIED/STORAGE AND HANDLING
OJEMDA tablets:
100 mg: orange, film-coated, oval tablets debossed with "100" on one side and "D101" on the opposite side and supplied as follows:
| Weekly dose | Each carton contains | Each blister card contains | NDC |
|---|---|---|---|
| 400 mg | 4 blister cards | four 100 mg tablets | NDC 82950-001-16 |
| 500 mg | 4 blister cards | five 100 mg tablets | NDC 82950-001-20 |
| 600 mg | 4 blister cards | six 100 mg tablets | NDC 82950-001-24 |
Store at 20°C to 25°C (68°F to 77°F); excursions permitted between 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature].
Dispense product in the original package. Tablets should not be removed from blister cards until immediately before use.
OJEMDA for oral suspension:
25 mg/mL: white to off white powder in a clear glass bottle, co-packaged with a press-in bottle adaptor and a 20 mL oral dosing syringe (NDC# 82950-012-01).
Each mL of reconstituted, strawberry flavored tovorafenib suspension contains 25 mg of tovorafenib. Each bottle delivers 300 mg of tovorafenib in 12 mL.
Store at 20°C to 25°C (68°F to 77°F); excursions permitted between 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature].
Do not use if safety seal under cap is broken or missing.
Suspension must be used immediately after reconstitution.
Discard the bottle (including any unused portion) and syringe after dosing.
17 PATIENT COUNSELING INFORMATION
Advise the patient to read the FDA-approved patient labeling (Patient Information and Instructions for Use).
Hemorrhage
Advise patients that OJEMDA can cause bleeding and to contact their healthcare provider for signs or symptoms of bleeding [see Warnings and Precautions (5.1)].
Skin Toxicities
Advise patients that OJEMDA can cause skin toxicities and to contact their healthcare provider for worsening or intolerable rash [see Warnings and Precautions (5.2)].
Photosensitivity
Advise patients that OJEMDA can cause photosensitivity. Advise patients to limit direct ultraviolet exposure during treatment with OJEMDA. Recommend that patients use precautionary measures such as use of sunscreen, sunglasses, and/or protective clothing during treatment with OJEMDA [see Warnings and Precautions (5.2)].
Hepatotoxicity
Advise patients that OJEMDA can cause liver toxicity and to contact their healthcare provider for signs or symptoms of liver dysfunction. Advise patients that serial testing of serum liver tests (ALT, AST, bilirubin) is recommended during treatment with OJEMDA [see Warnings and Precautions (5.3)].
Effect on Growth
Advise patients and caregivers that treatment with OJEMDA may cause a reduction in growth velocity, and that growth will be monitored during treatment with OJEMDA [see Warnings and Precautions (5.4)].
Embryo-Fetal Toxicity
- Advise pregnant women and females of reproductive potential of the potential risk to a fetus [see Warnings and Precautions (5.5), Use in Specific Populations (8.1, 8.3)].
- Advise females to inform their healthcare provider of a known or suspected pregnancy during treatment with OJEMDA.
- Advise females of reproductive potential to use effective nonhormonal contraception during treatment and for 28 days after discontinuation of treatment with OJEMDA.
- Advise male patients with female partners of reproductive potential to use effective nonhormonal contraception during treatment with OJEMDA and for 2 weeks after the last dose.
Lactation
Advise women not to breastfeed during treatment with OJEMDA and for 2 weeks after the last dose of OJEMDA [see Use in Specific Populations (8.2)].
Infertility
Advise males and females of reproductive potential of the potential risk for impaired fertility with OJEMDA [see Nonclinical Toxicology (13.1)].
Dosing and Administration
Inform patients and caregivers on how to take OJEMDA and what to do for missed or vomited doses [see Dosage and Administration (2.4)].
Prior to use of the oral suspension, ensure patients or caregivers receive training on proper dosing, preparation, and administration [see Dosage and Administration (2.4) and Instructions for Use].
Storage
Advise patients not to take the OJEMDA tablets out of the blister card until ready to use.
Discard the bottle (including any unused portion) and syringe after dosing.
OJEMDA is a trademark of Day One Biopharmaceuticals Inc.
© 2025 Day One Biopharmaceuticals, Inc. All rights reserved.
Manufactured for:
Day One Biopharmaceuticals, Inc.
Brisbane CA 94005
Manufactured by (tablets):
Quotient Sciences – Philadelphia LLC
3 Chelsea Parkway, Suite 305
Boothwyn PA 19061
Manufactured by (oral suspension):
Quotient Sciences – Philadelphia LLC
3080 McCann Farm Dr.
Garnet Valley, PA 19060
DAY101-USPI-082025v04