


Prescribing information (package insert) - Hyrnuo
1 INDICATIONS AND USAGE
HYRNUO is indicated for the treatment of adult patients with locally advanced or metastatic non-squamous non-small cell lung cancer (NSCLC) whose tumors have HER2 (ERBB2) tyrosine kinase domain (TKD) activating mutations, as detected by an FDA-authorized test [see Dosage and Administration (2.1)].
This indication is approved under accelerated approval based on objective response rate (ORR) and duration of response (DOR) [see Clinical Studies (14)]. Continued approval for this indication may be contingent upon verification and description of clinical benefit in a confirmatory trial.
2 DOSAGE AND ADMINISTRATION
2.1 Patient Selection
Select patients for treatment of locally advanced or metastatic non-squamous NSCLC based on the presence of HER2 (ERBB2) TKD activating mutations in tumor specimens [see Clinical Studies (14)].
Information on FDA-authorized tests is available at http://www.fda.gov/CompanionDiagnostics.
2.2 Recommended Dosage
The recommended dosage of HYRNUO is 20 mg orally twice daily with food, until disease progression or unacceptable toxicity [see Clinical Pharmacology (12.3)]. Swallow tablets whole. Do not cut, crush, or chew tablets.
Missed Dose
If a dose is missed, take the missed dose as soon as you remember prior to the next scheduled dose. Do not take 2 doses at the same time to make up for the missed dose.
Vomited Dose
If a dose is vomited, do not take an additional dose. Resume dosing at the next scheduled time.
2.3 Dosage Modifications for Adverse Reactions
The recommended dosage reductions for adverse reactions are provided in Table 1.
Table 1: Recommended HYRNUO Dosage Reductions for Adverse Reactions
| Dose Reduction | Dosage Modification |
|---|---|
| First | 10 mg twice daily |
| Second | 10 mg once daily |
| Permanently discontinue HYRNUO in patients who are unable to tolerate 10 mg once daily. | |
The recommended dosage modifications for adverse reactions are provided in Table 2.
Table 2: Recommended HYRNUO Dosage Modifications for Adverse Reactions
| Adverse Reaction | SeverityGrades based on National Cancer Institute Common Terminology Criteria for Adverse Events (NCI CTCAE) Version 5.0. | Dosage Modification |
|---|---|---|
| Diarrhea [see Warnings and Precautions (5.1)] | Intolerable Grade 2 or Grade 3 |
|
| Grade 4 |
| |
| Hepatotoxicity [see Warnings and Precautions (5.2)] | Grade 2, 3 or 4 ALT and/or AST without increased total bilirubin or Grade 3 total bilirubin |
|
| ALT or AST ≥ 3× ULN with total bilirubin ≥ 2× ULN or Grade 4 total bilirubin |
| |
| Interstitial Lung Disease (ILD)/Pneumonitis [see Warnings and Precautions (5.3)] | Any Grade |
|
| Left Ventricular Dysfunction [see Warnings and Precautions (5.4)] | LVEF 40 to 50% and decrease from baseline of 10 to 19% |
|
| LVEF 20 to 39% or ≥ 20% decrease from baseline |
| |
| Symptomatic Congestive Heart Failure |
| |
| Ocular toxicity [see Warnings and Precautions (5.5)] | Grade 2 |
|
| Grade 3 or Grade 4 |
| |
| Pancreatic Enzyme Elevation [see Warnings and Precautions (5.6)] | Grade 3 |
|
| Grade 4 |
| |
| Other adverse reactions [see Adverse Reactions (6.1)] | Intolerable or recurrent Grade 2 or Grade 3 |
|
| Grade 4 |
|
2.4 Dosage Modifications for Strong CYP3A Inhibitors
Avoid concomitant use of strong CYP3A inhibitors. If concomitant use cannot be avoided, reduce HYRNUO dosage as shown in Table 3. After the CYP3A inhibitor has been discontinued for 3 to 5 elimination half-lives, resume the HYRNUO dosage that was used prior to initiating the inhibitor [see Drug Interactions (7.1)].
Table 3: Recommended HYRNUO Dosage Modifications for Concomitant Use with Strong CYP3A Inhibitors
| Current Dosage | Recommended Dosage |
|---|---|
| 20 mg twice daily | 10 mg twice daily |
| 10 mg twice daily | 10 mg once daily |
| 10 mg once daily | Withhold HYRNUO until strong CYP3A inhibitor is discontinued |
3 DOSAGE FORMS AND STRENGTHS
Tablets: red brown film-coated, round, biconvex tablets debossed with "SE" on one side and "10" on the other side containing 10 mg of sevabertinib.
4 CONTRAINDICATIONS
None.
5 WARNINGS AND PRECAUTIONS
5.1 Diarrhea
HYRNUO can cause severe diarrhea that can lead to dehydration and electrolyte imbalances. In the pooled safety population [see Adverse Reactions (6.1)], diarrhea was reported in 89% of patients who received HYRNUO including 16% Grade 3. The median time to first onset of any grade diarrhea was four days. Dosage interruptions occurred in 15% of patients, and dose reductions occurred in 14% of patients.
At the first sign of diarrhea or increased bowel movement frequency, instruct patients to start an antidiarrheal treatment (e.g., loperamide [refer to full Prescribing Information]), and to increase their fluid and electrolyte intake. Interrupt, reduce the dose, or permanently discontinue HYRNUO based on severity [see Dosage and Administration (2.3)].
5.2 Hepatotoxicity
HYRNUO can cause severe hepatotoxicity characterized by elevations of liver function tests. In the pooled safety population [see Adverse Reactions (6.1)], based on adverse reaction data, hepatotoxicity occurred in 29% of patients treated with HYRNUO, including 3.1% Grade 3 and 0.3% Grade 4. Based on laboratory data, 41% of patients treated with HYRNUO experienced increased alanine aminotransferase (ALT), including 2.5% Grade 3 and 0.4% Grade 4. Increased aspartate aminotransferase (AST) occurred in 44% of patients treated with HYRNUO, including 2.5% Grade 3. Increased bilirubin occurred in 15% of patients treated with HYRNUO. The median time to first onset of AST or ALT elevation was 1.4 (range 0.2 to 24.1) months. HYRNUO was interrupted for an adverse reaction of hepatotoxicity in 4.2% of patients, the dose was reduced in 4.9% and permanently discontinued in 0.3%.
Monitor liver function tests including ALT, AST, and total bilirubin at baseline prior to the first administration of HYRNUO, every 2 weeks for the first month, and then monthly thereafter as clinically indicated, with more frequent testing in patients who develop transaminase elevations. Interrupt, reduce the dose, or permanently discontinue HYRNUO based on severity [see Dosage and Administration (2.3)].
5.3 Interstitial Lung Disease/Pneumonitis
HYRNUO can cause severe interstitial lung disease (ILD)/pneumonitis. In the pooled safety population [see Adverse Reactions (6.1)], ILD/pneumonitis occurred in four patients (1.4%) treated with HYRNUO, including 0.3% Grade 3. One patient required interruption of HYRNUO.
Monitor patients for new or worsening symptoms indicative of ILD/pneumonitis (e.g., dyspnea, cough, fever). Discontinue HYRNUO upon confirmation of ILD/pneumonitis [see Dosage and Administration (2.3)].
5.4 Left Ventricular Dysfunction
HYRNUO can cause severe left ventricular dysfunction. Left ventricular ejection fraction (LVEF) decrease has occurred with anti-HER2 therapies, including HYRNUO. Treatment with HYRNUO has not been studied in patients with a history of clinically significant cardiac disease or LVEF less than 50% prior to initiation of treatment. In the pooled safety population [see Adverse Reactions (6.1)], LVEF decrease occurred in one patient (0.3%) treated with HYRNUO. This Grade 3 LVEF decrease required permanent discontinuation of HYRNUO, and the event recovered.
Evaluate LVEF prior to initiation of HYRNUO and monitor at regular intervals during treatment and as clinically indicated. Interrupt, reduce the dose, or permanently discontinue HYRNUO based on severity [see Dosage and Administration (2.3)].
5.5 Ocular Toxicity
HYRNUO can cause ocular toxicity. In the pooled safety population [see Adverse Reactions (6.1)], ocular toxicity occurred in 17% of patients treated with HYRNUO, including 11% Grade 1, 4.9% Grade 2 and 0.3% Grade 3 (one case of corneal epithelial microcysts with temporary unilateral blindness).
Promptly refer patients presenting with new or worsening eye symptoms to an ophthalmologist. Interrupt, reduce the dose, or permanently discontinue HYRNUO based on severity [see Dosage and Administration (2.3)].
5.6 Pancreatic Enzyme Elevation
HYRNUO can cause elevations of amylase and lipase levels. In the pooled safety population [see Adverse Reactions (6.1)], based on laboratory data, increased amylase occurred in 39% of patients treated with HYRNUO, including 3.9% Grade 3 and 0.7% Grade 4. Increased lipase occurred in 48% of patients treated with HYRNUO, including 13% Grade 3 and 1.1% Grade 4. Four patients (1.4%) required interruption of HYRNUO due to increased lipase and 3 (1%) required interruption of HYRNUO due to increased amylase. One patient (0.3%) required dose reduction of HYRNUO due to increased amylase. The median time to onset of increased amylase/lipase was 0.7 months (range 0.2 to 20.4 months).
Monitor amylase and lipase regularly during treatment with HYRNUO. Interrupt, reduce the dose, or permanently discontinue HYRNUO based on severity [see Dosage and Administration (2.3)].
5.7 Embryo-Fetal Toxicity
Based on findings from animal studies and its mechanism of action, HYRNUO can cause fetal harm when administered to a pregnant woman. In embryo-fetal development studies, oral administration of sevabertinib to pregnant rats during the period of organogenesis resulted in alterations to growth at maternal exposures ≥0.18 times the human exposure based on area under the curve (AUC) at the clinical dose of 20 mg twice daily. Animal studies with disrupted or depleted HER2/EGFR and in vitro assays have demonstrated that inhibition of HER2 and/or EGFR results in structural abnormalities, alteration to growth, and embryo-fetal and infant mortality.
Advise pregnant women and females of reproductive potential of the potential risk to a fetus. Advise females of reproductive potential to use effective contraception during treatment with HYRNUO and for 1 week after the last dose. Advise male patients with female partners of reproductive potential to use effective contraception during treatment with HYRNUO and for 1 week after the last dose [see Use in Specific Populations (8.1, 8.3)].
6 ADVERSE REACTIONS
The following clinically significant adverse reactions are discussed in greater detail in other sections of the labeling:
- Diarrhea [see Warnings and Precautions (5.1)]
- Hepatotoxicity [see Warnings and Precautions (5.2)]
- Interstitial Lung Disease (ILD)/Pneumonitis [see Warnings and Precautions (5.3)]
- Left Ventricular Dysfunction [see Warnings and Precautions (5.4)]
- Ocular Toxicity [see Warnings and Precautions (5.5)]
- Pancreatic Enzyme Elevation [see Warnings and Precautions (5.6)]
6.1 Clinical Trial Experience
Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice.
The pooled safety population in the WARNINGS AND PRECAUTIONS reflects exposure to HYRNUO at 20 mg orally twice daily in 287 patients with locally advanced or metastatic NSCLC harboring HER2 activating and/or other mutations from the SOHO-01 study [see Clinical Studies (14)]. Among 287 patients who received HYRNUO, 61% were exposed for greater than 6 months and 37% were exposed for greater than 1 year.
In this pooled safety population, the most common (>20%) adverse reactions were diarrhea, rash, paronychia, nausea, vomiting, and stomatitis. The most common (≥2%) Grade 3 or 4 laboratory abnormalities were decreased potassium, increased lipase, decreased phosphate, decreased lymphocyte count, decreased sodium, increased amylase, decreased hemoglobin, increased ALT, increased AST, and decreased calcium.
Locally Advanced or Metastatic Non-squamous NSCLC whose tumors have HER2 (ERBB2) TKD Activating Mutations
The safety of HYRNUO at 20 mg orally twice daily was evaluated in 191 patients with locally advanced or metastatic non-squamous NSCLC harboring HER2 (ERBB2) TKD activating mutations in the SOHO-01 study [see Clinical Studies (14)]. The safety population included treatment naïve patients (Group F, N=69), previously treated patients naïve to HER2-targeted therapy (Group D, N=70), and previously treated patients with documented progression on HER2-targeted antibody drug conjugates (ADCs) (Group E, N=52).
Among 191 patients who received HYRNUO, 66% were exposed for greater than 6 months and 43% were exposed for greater than 1 year. The median age of patients who received HYRNUO was 62 years (range: 29 to 91); 65% female; 68% Asian, 26% White, 2.1% Black or African American; and 1.6% were of Hispanic or Latino ethnicity.
Serious adverse reactions occurred in 33% of patients who received HYRNUO. Serious adverse reactions in ≥2% of patients were diarrhea (3.7%), dyspnea (3.1%), vomiting (3.7%), pneumonia (2.6%), and pleural effusion (2.1%). A fatal adverse reaction of cerebral infarction occurred in one patient (0.5%) who received HYRNUO.
Permanent discontinuation of HYRNUO due to an adverse reaction occurred in 4.2% of patients. Adverse reactions which resulted in permanent discontinuation were corneal epithelial microcysts, hepatic function abnormal, increased blood alkaline phosphatase, electrocardiogram QT prolonged, pain in extremity, renal failure and dyspnea (0.5%, 1 patient each).
Dosage interruptions of HYRNUO due to an adverse reaction occurred in 49% of patients. Adverse reactions which resulted in dosage interruptions in >2% of patients were diarrhea, potassium decreased, hepatotoxicity, nausea, vomiting, rash, pneumonia, paronychia, decreased appetite, pruritus, acute kidney injury, and stomatitis.
Dose reductions of HYRNUO due to adverse reactions occurred in 32% of patients. Adverse reactions which resulted in dose reductions in >2% of patients were diarrhea, hepatotoxicity, rash, potassium decrease, stomatitis, vomiting, and decreased appetite.
Table 4 summarizes the adverse reactions in SOHO-01 (Groups D, E and F).
Table 4: Adverse Reactions (≥15%) in Patients with NSCLC with HER2 Activating Mutations who Received HYRNUO in SOHO-01 (Groups D, E and F)
| Adverse ReactionGraded per NCI CTCAE version 5. | HYRNUO N = 191 | |
|---|---|---|
All Grades (%) | Grade 3 or 4No Grade 4 were reported. (%) | |
| Gastrointestinal disorders | ||
| DiarrheaGrouped term. | 90 | 14 |
| Stomatitis | 37 | 1 |
| Nausea | 22 | 2.1 |
| Vomiting | 19 | 4.2 |
| Skin and subcutaneous tissue disorders | ||
| Rash | 76 | 1.6 |
| Paronychia | 36 | 1 |
| Dry skin | 18 | 0 |
| Pruritus | 16 | 1 |
| Investigations | ||
| Weight decreased | 22 | 0.5 |
| Metabolism and nutrition disorders | ||
| Decreased appetite | 19 | 2.6 |
| Musculoskeletal and connective tissue disorders | ||
| Musculoskeletal pain | 18 | 0 |
| General disorders and administration site conditions | ||
| Fatigue | 17 | 2.6 |
| Eye disorders | ||
| Ocular toxicity | 16 | 0.5 |
Clinically relevant adverse reactions in <15% of patients who received HYRNUO included abdominal pain (14%), cardiac arrhythmia (10%; including arrhythmia, atrial fibrillation, atrial tachycardia, atrioventricular block complete, atrioventricular block first degree, electrocardiogram QT prolonged, sinus arrhythmia, sinus bradycardia, sinus tachycardia, supraventricular extrasystoles, supraventricular tachycardia, tachycardia, and ventricular extrasystoles) and alopecia (7%).
Table 5 summarizes the laboratory abnormalities in SOHO-01 (Groups D, E and F).
Table 5: Select Laboratory Abnormalities (≥20%) that Worsened from Baseline in Patients with NSCLC with HER2 Activating Mutations in SOHO-01 (Groups D, E and F)
| Laboratory Abnormality | HYRNUO N=191The denominator used to calculate the rate varied from 153 to 189 based on the number of patients with a baseline value and at least one post-treatment value. | |
|---|---|---|
All Grades (%)Graded per NCI CTCAE version 5 using only numeric values. | Grade 3 or 4 (%) | |
| Chemistry | ||
| Lipase increased | 53 | 18 |
| Potassium decreased | 51 | 18 |
| Aspartate aminotransferase increased | 46 | 2.6No Grade 4 were reported. |
| Glucose increasedGraded per NCI CTCAE version 4.03 using only numeric values. | 45 | 0.5 |
| Alanine aminotransferase increased | 43 | 3.2 |
| Magnesium decreased | 41 | 0 |
| Amylase increased | 39 | 5 |
| Calcium decreased | 36 | 1.6 |
| Phosphate decreased | 35 | 13 |
| Sodium decreased | 33 | 5 |
| Creatinine increased | 33 | 1.1 |
| Albumin decreased | 33 | 1.1 |
| Triglycerides increased | 33 | 0 |
| Alkaline phosphatase increased | 25 | 0.5 |
| Hematology | ||
| Hemoglobin decreased | 52 | 3.7 |
| Lymphocyte count decreased | 29 | 4.6 |
| White blood cell decreased | 20 | 1.1 |
Laboratory abnormalities in <20% of patients who received HYRNUO include bilirubin increased (19%; all were Grades 1 and 2), platelet count decreased and neutrophil count decreased (16% each).
7 DRUG INTERACTIONS
7.1 Effect of Other Drugs on HYRNUO
Table 6 describes drug interactions where concomitant use of another drug affects HYRNUO.
Table 6: Drug Interactions that Affect HYRNUO
| Strong and Moderate CYP3A Inhibitors | |
| Prevention or management | Strong CYP3A Inhibitors:
|
Moderate CYP3A Inhibitors:
| |
| Mechanism and Clinical Effect |
|
| Strong and Moderate CYP3A Inducers | |
| Prevention or management |
|
| Mechanism and Clinical Effect |
|
7.2 Effects of HYRNUO on Other Drugs
Table 7 describes drug interactions where concomitant use of HYRNUO affects another drug.
Table 7: HYRNUO Drug Interactions that Affect Other Drugs
| Certain CYP3A Substrates | |
| Prevention or management |
|
| Mechanism and Clinical Effect |
|
| Certain P-gp Substrates | |
| Prevention or management |
|
| Mechanism and Clinical Effect |
|
| CYP1A1 Substrates | |
| Prevention or management |
|
| Mechanism and Clinical Impact |
|
8 USE IN SPECIFIC POPULATIONS
8.1 Pregnancy
Risk Summary
Based on findings from animal studies and its mechanism of action [see Clinical Pharmacology (12.1)], HYRNUO can cause fetal harm when administered to a pregnant woman. There are no available data on the use of HYRNUO in pregnant women to inform a drug-associated risk. In embryo-fetal development studies, oral administration of sevabertinib to pregnant rats during the period of organogenesis resulted in alterations to growth at maternal exposures ≥0.18 times the human exposure based on area under the curve (AUC) at the clinical dose of 20 mg twice daily. Animal studies with disrupted or depleted HER2/EGFR and in vitro assays have demonstrated that inhibition of HER2 and/or EGFR results in structural abnormalities, alteration to growth, and embryo-fetal and infant mortality (see Data). Advise pregnant women of the potential risk to a fetus.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Data
Animal Data
In embryo-fetal development studies, sevabertinib was administered orally to pregnant rats during the period of organogenesis from gestation day 6 to 17 at doses ranging from 1.5 to 11 mg/kg/day. Sevabertinib treatment resulted in maternal toxicity (reduced body weight and body weight gain) and a reduction in fetal weights at ≥6 mg/kg/day (≥0.18 times the human exposure based on AUC at the clinical dose).
Additional Nonclinical Data
A literature-based assessment of the effects on reproduction in mouse models with disrupted or depleted HER2/EGFR demonstrated that HER2/EGFR is critically important in reproductive and developmental processes including blastocyst implantation, placental development, and embryo-fetal/postnatal survival and development.
In a human-induced pluripotent stem cell-based assay, sevabertinib reduced cardiomyocyte and hepatocyte differentiation markers.
8.2 Lactation
Risk Summary
There are no data on the presence of sevabertinib or its metabolites in human milk or their effects on a breastfed child or on milk production. In rats, sevabertinib or its metabolites are excreted in milk (see Data). Because of the potential for serious adverse reactions in breastfed children from HYRNUO, advise women not to breastfeed during treatment with HYRNUO and for 1 week after the last dose.
Data
Animal Data
Following administration of radiolabeled sevabertinib to lactating rats, sevabertinib or its metabolites were excreted in milk. Sevabertinib-derived radioactivity concentrations were 13- to 26-times higher in milk than in plasma. Approximately 1.3% of the administered dose of sevabertinib-derived radioactivity was excreted into the milk.
8.3 Females and Males of Reproductive Potential
HYRNUO can cause fetal harm when administered to a pregnant woman [see Use in Specific Populations (8.1)].
Pregnancy Testing
Verify pregnancy status in females of reproductive potential prior to initiating HYRNUO.
Contraception
Females
Advise females of reproductive potential to use effective contraception during treatment with HYRNUO and for 1 week after the last dose.
Males
Advise males with female partners of reproductive potential to use effective contraception during treatment with HYRNUO and for 1 week after the last dose.
8.4 Pediatric Use
The safety and effectiveness of HYRNUO have not been established in pediatric patients.
8.5 Geriatric Use
Of the 287 patients with locally advanced or metastatic NSCLC harboring HER2 activating mutations who received HYRNUO at 20 mg twice daily in the SOHO-01 study, 43% were 65 years and over and 14% were 75 years and over. No overall differences in effectiveness were observed between these older and younger patients. Grade 3 diarrhea was observed in 26% of patients age ≥75 years and 15% of patients <75 years old.
11 DESCRIPTION
HYRNUO tablets contain sevabertinib, a kinase inhibitor. The chemical name of the drug substance is 3-(3-chloro-2-methoxyanilino)-2-{3-[(2S)-1,4-dioxan-2-ylmethoxy]pyridin-4-yl}-1,5,6,7-tetrahydro-4H-pyrrolo[3,2-c]pyridin-4-one hydrate. The molecular formula is C24H25ClN4O5 (anhydrate) and the molecular weight is 484.93 g/mol (anhydrate).
The structural formula is shown below:
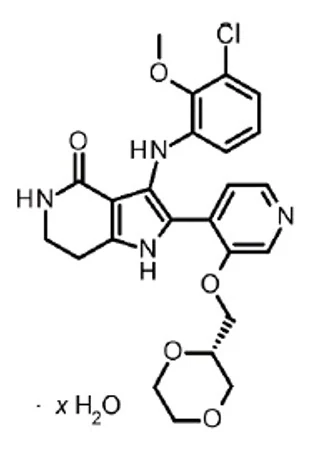
Sevabertinib is present as a non-stoichiometric hydrate as a white to off-white to yellow to pinkish powder. It is slightly soluble in aqueous solution at pH 2, and practically insoluble in aqueous solutions at pH 4.5 and above.
The strength of HYRNUO is based on the anhydrate form. Each HYRNUO tablet for oral use contains 10 mg of sevabertinib. The inactive ingredients are: cellulose microcrystalline, crospovidone, lactose monohydrate, and magnesium stearate. The tablet film coating contains ferric oxide red, hypromellose 5 cP, and macrogol 3350.
12 CLINICAL PHARMACOLOGY
12.1 Mechanism of Action
Sevabertinib is a reversible kinase inhibitor of human epidermal growth factor receptor 2 (HER2). It also exhibits activity against epidermal growth factor receptor (EGFR).
In vitro, sevabertinib inhibited the phosphorylation of HER2 and downstream signaling in cancer cells with HER2 alterations and proliferation of cancer cells overexpressing wild-type HER2 or harboring HER2 mutations.
In vivo, sevabertinib demonstrated antitumor activity in subcutaneous mouse xenograft models derived from human NSCLC tumors harboring an activating HER2 exon 20 mutation.
12.2 Pharmacodynamics
Exposure-Response Relationship
Higher sevabertinib exposure, across the dose range of 10 to 80 mg total daily dose (0.25 to 2 times the recommended dosage), was associated with an increased incidence of diarrhea (all grade and Grade ≥ 3) and rash.
Cardiac Electrophysiology
At 2 times the maximum recommended dose, a mean increase in the QTc interval >20 ms was not observed.
12.3 Pharmacokinetics
Sevabertinib pharmacokinetics were observed at steady state in patients with advanced NSCLC harboring activating HER2 or EGFR mutations at the approved recommended dosage and are presented as mean (CV%), unless otherwise specified.
Sevabertinib maximum concentration (Cmax) is 902 (45%) ng/mL and total systemic exposure (AUC) is 6,640 (50%) ng*h/mL. Sevabertinib Cmax and AUC increase in a dose-proportional manner across the dose range of 10 mg to 80 mg (0.25 to 2 times the approved recommended total daily dose). Sevabertinib accumulation is approximately 1.7-fold for AUC and 1.3-fold for Cmax at the approved recommended dosage. Steady state is achieved within 3 days.
Absorption
Sevabertinib median (min, max) time to maximum concentrations (Tmax) is approximately 2 hours (0.5, 8.2 hours) after a single dose.
Effect of Food
Sevabertinib Cmax decreases by 56% and AUC decreases by 28% with a high-fat meal (1,000 calories, 50% fat) in healthy subjects. No clinically significant differences in sevabertinib pharmacokinetics were observed following administration of a low-fat meal (400 calories, 25% fat).
Distribution
Sevabertinib apparent volume of distribution is 28 L (42%). Sevabertinib plasma protein binding is 95%. The blood-to-plasma concentration ratio is 0.6.
Elimination
Sevabertinib effective half-life is approximately 8 hours (33%) with an apparent clearance of 3.1 L/hour (38%).
Metabolism
Sevabertinib is primarily metabolized by CYP3A (major), CYP1A1 (minor), and glucuronidation (minor).
Excretion
After a single oral dose of radiolabeled sevabertinib 40 mg to healthy subjects, approximately 84% of the dose was recovered in feces (14% unchanged) and approximately 10% in urine (1.3% unchanged).
Specific Populations
No clinically significant effects in the pharmacokinetics of sevabertinib were observed based on age (18 to 91 years), race (27% White, 65% Asian, 2.7% Black/African American), sex, body weight (29 to 155 kg), smoking status, eGFR 30 to <90 mL/min, or mild hepatic impairment (AST > ULN and total bilirubin ≤ ULN; or total bilirubin >1 to 1.5× ULN and any AST). The effect of severe renal impairment (eGFR 15 to <30 mL/min), end-stage renal disease (eGFR <15 mL/min), moderate hepatic impairment (total bilirubin >1.5 to 3× ULN and any AST) or severe hepatic impairment (total bilirubin >3× ULN and any AST) on sevabertinib pharmacokinetics is unknown.
Drug Interaction Studies
Clinical Studies
Strong CYP3A Inhibitors: Sevabertinib AUC increased 2.3-fold and Cmax 1.6-fold following concomitant use of itraconazole (strong CYP3A inhibitor) 200 mg once daily.
Strong CYP3A Inducers: Sevabertinib AUC decreased by 79% and Cmax by 57% following concomitant use of carbamazepine (strong CYP3A inducer) 600 mg daily.
CYP3A Substrates: Midazolam (CYP3A substrate) AUC increased 2-fold and Cmax 1.8-fold following concomitant use of HYRNUO 20 mg twice daily.
P-gp Substrates: Dabigatran etexilate (P-gp substrate) AUC increased 1.4-fold following concomitant use of HYRNUO 20 mg twice daily.
BCRP Substrates: Rosuvastatin (BCRP substrate) AUC increased 1.2-fold and Cmax 1.4-fold following concomitant use of HYRNUO 20 mg twice daily.
Other Drugs: No clinically significant differences in sevabertinib pharmacokinetics were observed when used concomitantly with esomeprazole (proton pump inhibitor).
In Vitro Studies
CYP450 Enzymes: Sevabertinib inhibits CYP1A1 and CYP2C8 but does not inhibit CYP2A6, CYP2C9, CYP1A2, CYP2B6, CYP2D6, CYP2C19, or CYP2E1. Sevabertinib does not induce CYP1A2, CYP2B6, or CYP2C19.
Transporter Systems: Sevabertinib is a substrate of P-gp, and BCRP. Sevabertinib inhibits MATE1 and MATE2-K but does not inhibit OATP1B1, OATP1B3, MRP2, OAT1, OAT3, OCT1, or OCT2.
13 NONCLINICAL TOXICOLOGY
13.1 Carcinogenesis, Mutagenesis, Impairment of Fertility
Carcinogenesis
Carcinogenicity studies have not been conducted with sevabertinib.
Mutagenesis
Sevabertinib was not genotoxic in a bacterial reverse mutation (Ames) and an in vitro micronucleus assay, or an in vivo micronucleus assay in rats.
Impairment of Fertility
Fertility studies have not been conducted with sevabertinib.
14 CLINICAL STUDIES
14.1 Locally Advanced or Metastatic Non-squamous NSCLC with HER2 TKD Activating Mutations
The efficacy of HYRNUO was evaluated in SOHO-01 (NCT05099172), an open-label, single-arm, multicenter, multi-cohort clinical study. Eligible patients (Groups D, E and F) were required to have locally advanced or metastatic NSCLC with HER2 (ERBB2) activating mutations and have an Eastern Cooperative Oncology Group Performance Status (ECOG PS) of 0 or 1. HER2 (ERBB2) activating mutations were determined in tumor tissue or plasma by local laboratories prior to enrollment. Patients with treated, stable and asymptomatic brain metastases were eligible. Patients with symptomatic CNS metastases, clinically significant cardiac disease, and history of steroid dependent interstitial lung disease (ILD)/pneumonitis were excluded.
Patients received HYRNUO 20 mg orally twice daily until disease progression or unacceptable toxicity. The major efficacy outcomes were confirmed objective response rate (ORR) and duration of response (DOR), as assessed by Blinded Independent Central Review (BICR) using RECIST v1.1.
The efficacy population included treatment naïve patients (Group F, N=69), previously treated patients naïve to HER2- targeted therapy (Group D, N=70), and previously treated patients with documented progression on HER2-targeted antibody drug conjugates (ADCs) (Group E, N=52), with advanced non-squamous NSCLC with HER2 (ERBB2) TKD activating mutations based on prospective local testing.
Of the 69 patients in Group F, tumor tissue samples from 84.1% (58/69) of patients were retrospectively tested using Oncomine™ Dx Target Test (Life Technologies Corporation). While 86.2% (50/58) of samples were positive for HER2 (ERBB2) TKD activating mutations, 12.1% (7/58) were unevaluable, and 1.7% (1/58) were negative for HER2 (ERBB2) TKD activating mutations. Of the 122 patients in the combined cohorts (Groups D and E), tumor tissue samples from 67.2% (82/122) of patients were retrospectively tested using Oncomine™ Dx Target Test (Life Technologies Corporation). While 92.7% (76/82) of samples were positive for HER2 (ERBB2) TKD activating mutations, 7.3% (6/82) were unevaluable, and there were no samples with negative status for HER2 (ERBB2) TKD activating mutations.
NSCLC Treatment Naïve: Group F
Efficacy was evaluated in 69 patients with locally advanced or metastatic non-squamous NSCLC with HER2 (ERBB2) TKD activating mutations who have not received prior systemic therapy. Baseline demographic and disease characteristics of the efficacy population were: median age 66 years (range 31 to 82 years); 61% female; 70% Asian, 28% White and 2.9% race not reported. Patients had an ECOG performance status of either 0 (26%) or 1 (73%) or 2 (1.4%); 78% were never-smokers and 22% were former smokers. All patients had adenocarcinoma histology. Eighty-four percent (84%) of patients had stage IV disease and 12% had stable brain metastases. Seven percent (7%) of patients received prior platinum-based chemotherapy, 2.9% received prior immunotherapy, and 2.9% received both in combination. Among the patients, 80% of patients had a Y772_A775dup (YVMA) exon 20 insertion.
Efficacy results for SOHO-01 Group F are presented in Table 8.
Table 8: Efficacy Results for SOHO-01: Group F
| Efficacy Parameter | HYRNUO N=69 |
|---|---|
| CI: Confidence Interval, +: ongoing response. | |
| Objective Response Rate (ORR) ORR 95% CI calculated using Clopper-Pearson method., (95% CI) | 75% (64, 85) |
| Complete Response | 6% |
| Partial Response | 70% |
| Duration of Response (DOR) | N=52 |
| Range (months) | 1.5, 21.6+ |
| DOR ≥ 6 monthsObserved proportion of responding patients with duration of response beyond landmark time. | 73% |
| DOR ≥ 12 months | 38% |
NSCLC Previously Treated, Naïve to HER2-Targeted Therapy: Group D
Efficacy was evaluated in 70 patients with locally advanced or metastatic non-squamous NSCLC with HER2 (ERBB2) TKD activating mutations who had received prior systemic therapy but were naïve to therapy targeting HER2 mutations. Baseline demographic and disease characteristics of the efficacy population were: median age 59 years (range 29 to 77 years); 67% female; 70% Asian, 23% White, 1.4% Black or African American, 6% race not reported; 2.9% were of Hispanic or Latino ethnicity. Patients had an ECOG performance status of either 0 (39%) or 1 (61%); 69% were never-smokers, 29% were former smokers and 2.9% were current smokers. All patients had adenocarcinoma histology. Ninety-one percent (91%) of patients had stage IV disease and 20% had stable brain metastases. The median number of prior therapies was 1 (range 1 to 8); 94% of patients received prior platinum-based chemotherapy, 71% received prior immunotherapy, and 69% received both in combination. Among the patients, 70% of patients had a Y772_A775dup (YVMA) exon 20 insertion.
Efficacy results for SOHO-01 Group D are presented in Table 9.
Table 9: Efficacy Results for SOHO-01: Group D
| Efficacy Parameter | HYRNUO N=70 |
|---|---|
| CI: Confidence Interval. | |
| Objective Response Rate (ORR) ORR 95% CI calculated using Clopper-Pearson method., (95% CI) | 71% (59, 82) |
| Complete Response | 2.9% |
| Partial Response | 69% |
| Duration of Response (DOR) | N=50 |
| Median, months (95% CI)Kaplan-Meier estimate. | 9.2 (6.3, 15.0) |
| DOR ≥ 6 monthsObserved proportion of responding patients with duration of response beyond landmark time. | 54% |
| DOR ≥ 12 months | 18% |
NSCLC Previously Treated, Including Prior HER2 Targeted Antibody Drug Conjugates (ADCs): Group E
Efficacy was evaluated in 52 patients with locally advanced or metastatic non-squamous NSCLC with HER2 (ERBB2) TKD activating mutations who had received prior systemic therapy including HER2-targeted ADCs.
Baseline demographic and disease characteristics of this efficacy population were: median age 65 years (range 35 to 91 years); 67% female; 62% Asian, 27% White, 6% Black or African American, 6% race not reported; 1.9% were of Hispanic or Latino ethnicity. Patients had an ECOG performance status of either 0 (29%) or 1 (71%); 65% were never-smokers, and 35% were former smokers. All patients had adenocarcinoma histology. Eighty-five percent (85%) of patients had stage IV disease and 29% had stable brain metastases. The median number of prior therapies was 2 (range 1 to 8), 77% of patients received prior platinum-based chemotherapy, 56% received prior immunotherapy, and 56% received both in combination. Among the patients, 77% of patients had a Y772_A775dup (YVMA) exon 20 insertion.
The ORR was 38% (95% CI 25, 53), with 6% of patients having a complete response and 33% of patients having a partial response. The median DOR was 7 months (95% CI 5.6, NE); ranging from 1+ to 17.2+ months based on the observed DOR. The observed proportion of responding patients with DOR of ≥ 6 months and ≥ 12 months was 60% and 10%, respectively.
16 HOW SUPPLIED/STORAGE AND HANDLING
How Supplied
HYRNUO 10 mg tablets are supplied as red brown film-coated, round, biconvex tablets debossed with "SE" on one side and "10" on the other side.
HYRNUO tablets are packaged in a HDPE bottle of 120 tablets closed with a child-resistant screw cap.
NDC 50419-397-01
Storage and Handling
Store at 20°C to 25°C (68°F to 77°F); excursions permitted between 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature].
17 PATIENT COUNSELING INFORMATION
Advise the patient to read the FDA-approved patient labeling (Patient Information).
Diarrhea
Inform patients that HYRNUO can cause severe diarrhea. At the first sign of diarrhea or increased bowel movement frequency, instruct patients to start an antidiarrheal treatment (e.g., loperamide), to increase their fluid and electrolyte intake, and to immediately contact their healthcare provider [see Warnings and Precautions (5.1)].
Hepatotoxicity
Inform patients that HYRNUO can cause severe hepatotoxicity characterized by elevations of liver function tests. Inform patients that they will need to undergo lab tests to monitor hepatic function. Advise patients to immediately contact their healthcare provider for signs and symptoms of hepatotoxicity [see Warnings and Precautions (5.2)].
Interstitial Lung Disease (ILD)/Pneumonitis
Inform patients that HYRNUO can cause ILD/pneumonitis. Advise patients to immediately contact their healthcare provider for new or worsening respiratory symptoms [see Warnings and Precautions (5.3)].
Left Ventricular Dysfunction
Inform patients that HYRNUO can cause severe left ventricular dysfunction. Advise patients to immediately contact their healthcare provider for new or worsening cardiovascular symptoms [see Warnings and Precautions (5.4)].
Ocular Toxicity
Inform patients that HYRNUO can cause ocular toxicity. Advise patients to immediately contact their healthcare provider for new or worsening ocular symptoms [see Warnings and Precautions (5.5)].
Pancreatic Enzyme Elevation
Inform patients that HYRNUO can cause pancreatic enzyme elevation. Inform patients that they will need to undergo lab tests to monitor pancreatic function. Advise patients to immediately contact their healthcare provider for signs and symptoms associated with pancreatic enzyme elevation [see Warnings and Precautions (5.6)].
Embryo-Fetal Toxicity
Advise pregnant women and females of reproductive potential of the potential risk to a fetus. Advise females to inform their healthcare provider of a known or suspected pregnancy [see Warnings and Precautions (5.7) and Use in Specific Populations (8.1, 8.3)].
Advise females of reproductive potential to use effective contraception during treatment with HYRNUO and for 1 week after the last dose [see Use in Specific Populations (8.3)].
Advise male patients with female partners of reproductive potential to use effective contraception during treatment with HYRNUO and for 1 week after the last dose [see Use in Specific Populations (8.3)].
Lactation
Advise women not to breastfeed during treatment with HYRNUO and for 1 week after the last dose [see Use in Specific Populations (8.2)].
Dosage and Administration
- Instruct patients to take HYRNUO twice daily with food. Each tablet should be swallowed whole [see Dosage and Administration (2.2)].
- Instruct patients that if a dose of HYRNUO is missed to take the missed dose as soon as they remember prior to the next scheduled dose. Advise patients not to take two doses together to make up for a missed dose [see Dosage and Administration (2.2)].
- Instruct patients that if a dose of HYRNUO is vomited not to take an additional dose but to take the next dose at the next scheduled time [see Dosage and Administration (2.2)].
Drug Interactions
Advise patients and caregivers to inform their healthcare provider of all concomitant medications, including prescription medicines, over-the-counter drugs, vitamins, and herbal products. Inform patients to avoid grapefruit, or grapefruit juice while taking HYRNUO [see Drug Interactions (7.1, 7.2)].
Manufactured for:
Bayer HealthCare Pharmaceuticals Inc.
Whippany, NJ 07981 USA
© 2026 Bayer HealthCare Pharmaceuticals Inc.