


Prescribing information (package insert) - Epinephrine Injection 0.15 mg/0.15 mL
1 INDICATIONS AND USAGE
Epinephrine Injection is indicated for the emergency treatment of type I allergic reactions, including anaphylaxis in adult and pediatric patients who weigh 15 kg or greater.
2 DOSAGE AND ADMINISTRATION
2.1 Recommended Dosage
Recommended dosage for patients who weigh 15 kg or greater is based on weight and the dosage is provided in Table 1. Administer Epinephrine Injection intramuscularly or subcutaneously into the anterolateral aspect of the thigh.
Table 1 Recommended Dosage of Epinephrine Injection Based on Patient’s Weight
| Patient’s Weight | Dosage |
| 30 kg or greater | 0.3 mg |
| 15 kg to less than 30 kg | 0.15 mg |
- Since the doses of epinephrine delivered from Epinephrine Injection are fixed, use other forms of injectable epinephrine if doses lower than 0.15 mg are deemed necessary.
- In the absence of clinical improvement or if symptoms worsen after the initial treatment, a second dose of Epinephrine Injection may be administered with a second auto-injector starting 5 minutes after the first dose.
- Advise patients when to seek emergency medical assistance for close monitoring of the anaphylactic episode and in the event further treatment is required.
- It is recommended that patients are prescribed and have immediate access to two Epinephrine Injection devices at all times.
2.2 Administration Instructions
Injection:
- 0.3 mg (0.3 mg/0.3 mL) of clear and colorless solution in single-dose pre-filled auto-injector
- 0.15 mg (0.15 mg/0.15 mL) of clear and colorless solution in single-dose pre-filled auto-injector
3 DOSAGE FORMS AND STRENGTHS
- Injection: 0.3 mg (0.3 mg/0.3 mL) of clear and colorless solution in single-dose pre-filled auto-injector
- Injection: 0.15 mg (0.15 mg/0.15 mL) of clear and colorless solution in single-dose pre-filled auto-injector
4 CONTRAINDICATIONS
None.
5 WARNINGS AND PRECAUTIONS
5.1 Injection-Related Complications
Epinephrine Injection should only be injected into the anterolateral aspect of the thigh [see Dosage and Administration (2.2)].
Do not inject intravenously
Large doses or accidental intravenous injection of epinephrine may result in cerebral hemorrhage due to a sharp rise in blood pressure. Rapidly acting vasodilators can counteract the marked pressor effects of epinephrine for this inadvertent administration.
Do not inject into buttock
Injection into the buttock may not provide effective treatment of anaphylaxis. If Epinephrine Injection is injected into the buttock, advise the patient to administer a second dose of Epinephrine Injection into the anterolateral aspect of the thigh if symptoms worsen or persist, and then go immediately to the nearest emergency room for further treatment of anaphylaxis. Additionally, injection into the buttock has been associated with the development of Clostridial infections (gas gangrene). Cleansing with alcohol does not kill bacterial spores, and therefore, does not lower the risk.
Do not inject into digits, hands or feet
Since epinephrine is a strong vasoconstrictor, accidental injection into the digits, hands or feet may result in loss of blood flow to the affected area and may not provide effective treatment of anaphylaxis. Advise the patient to administer a second dose of Epinephrine Injection into the anterolateral aspect of the thigh if experiencing anaphylaxis, and then go immediately to the nearest emergency room and inform the healthcare provider in the emergency room of the location of the accidental injection. Treatment of such inadvertent administration should consist of vasodilation, in addition to further appropriate treatment of anaphylaxis [see Adverse Reactions (6)].
Hold leg firmly during injection
To minimize the risk of injection related injury when administering Epinephrine Injection to young children or infants, instruct caregivers to hold the child’s leg firmly in place and limit movement prior to and during injection.
5.2 Serious Infections at the Injection Site
Rare cases of serious skin and soft tissue infections, including necrotizing fasciitis and myonecrosis caused by Clostridia (gas gangrene), have been reported at the injection site following epinephrine injection for anaphylaxis. Clostridium spores can be present on the skin and introduced into the deep tissue with subcutaneous or intramuscular injection. While cleansing with alcohol may reduce presence of bacteria on the skin, alcohol cleansing does not kill Clostridium spores. To decrease the risk of Clostridium infection, do not inject Epinephrine Injection into the buttock [see Warnings and Precautions (5.1)]. Advise patients to seek medical care if they develop signs or symptoms of infection, such as persistent redness, warmth, swelling, or tenderness, at the epinephrine injection site.
5.3 Risks Associated with Use of Epinephrine in Certain Coexisting Conditions
Some patients may be at greater risk for developing adverse reactions after epinephrine administration. Despite these concerns, it should be recognized that the presence of these conditions is not a contraindication to epinephrine administration in an acute, life-threatening situation. Therefore, instruct patients with these conditions, and/or caregivers to the circumstances under which epinephrine should be used.
Administer epinephrine with caution to patients who have heart disease, including patients with cardiac arrhythmias, coronary artery or organic heart disease, or hypertension. In such patients, or in patients who are on drugs that may sensitize the heart to arrhythmias, epinephrine may precipitate or aggravate angina pectoris as well as produce ventricular arrhythmias [see Adverse Reactions (6) and Drug Interactions (7)].
Epinephrine can temporarily exacerbate the underlying condition or increase symptoms in
patients with the following: hyperthyroidism, Parkinson’s disease, diabetes, renal impairment.
Administer epinephrine with caution in patients with these conditions, including elderly patients and pregnant women.
5.4 Allergic Reactions Associated with Sulfite
Epinephrine is the preferred treatment for serious allergic reactions or other emergency situations even though Epinephrine Injection contains sodium bisulfite, a sulfite that may, in other products, cause allergic-type reactions including anaphylactic symptoms or life-threatening or less severe asthmatic episodes in certain susceptible persons. The alternatives to using epinephrine in a life-threatening situation may not be satisfactory. The presence of a sulfite in Epinephrine Injection should not deter administration of the drug for treatment of serious allergic or other emergency situations.
6 ADVERSE REACTIONS
The following clinically significant adverse reactions are described elsewhere in the labeling:
- Injection-Related Complications [see Warnings and Precautions (5.1)]
- Serious Infections at the Injections [see Warnings and Precautions (5.2)]
- Risks Associated with Use of Epinephrine in Certain Coexisting Conditions [see Warnings and Precautions (5.3)]
- Allergic Reactions Associated with Sulfite [see Warnings and Precautions (5.4)]
The following adverse reactions associated with the use of epinephrine were identified in observational trials, case reports, studies, or postmarketing reports. Because some of these reactions were reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
Cardiovascular: angina, arrhythmias (including fatal ventricular fibrillation), cerebral hemorrhage, hypertension, pallor, palpitations, tachyarrhythmia, tachycardia, vasoconstriction, ventricular ectopy, and stress cardiomyopathy
Gastrointestinal Disorders: nausea and vomiting
Infections: Clostridial infections (gas gangrene)
Metabolism and Nutrition Disorders: transient hyperglycemia, sweating
Neurological: disorientation, impaired memory, panic, psychomotor agitation, sleepiness,
tingling, weakness, tremor, hypoesthesia, dizziness, headache
Psychiatric: anxiety, apprehensiveness, restlessness
Respiratory: respiratory difficulties
Skin and Subcutaneous Tissue Disorders: bruising, bleeding, discoloration, erythema, necrotizing fasciitis, myonecrosis
7 DRUG INTERACTIONS
7.1 Drugs Increasing Risk of Cardiac Arrhythmias
Patients who receive epinephrine while concomitantly taking cardiac glycosides, diuretics, or anti-arrhythmics should be observed carefully for the development of cardiac arrhythmias [see Warnings and Precautions (5.3) and Adverse Reactions (6)].
7.2 Drugs Potentiating Effects of Epinephrine
The effects of epinephrine may be potentiated by tricyclic antidepressants, monoamine oxidase inhibitors, levothyroxine sodium, and certain antihistamines, notably chlorpheniramine, tripelennamine, and diphenhydramine, and catechol-O-methyl transferase (COMT) inhibitors such as entacapone.
7.3 Drugs Antagonizing Effects of Epinephrine
The cardiostimulating and bronchodilating effects of epinephrine are antagonized by beta- adrenergic blocking drugs, such as propranolol.
The vasoconstricting and hypertensive effects of epinephrine are antagonized by alpha-adrenergic blocking drugs, such as phentolamine.
Ergot alkaloids may also reverse the pressor effects of epinephrine.
8 USE IN SPECIFIC POPULATIONS
8.1 Pregnancy
Risk Summary
Prolonged experience with epinephrine use in pregnant women over several decades, based on published literature, have not identified a drug associated risk of major birth defects, miscarriage or adverse maternal or fetal outcomes. There are risks to the mother and fetus associated with anaphylaxis, and treatment with epinephrine should not be delayed (see Clinical Considerations). In animal reproduction studies, epinephrine administered by the subcutaneous route to pregnant rabbits, mice, and hamsters, during the period of organogenesis was teratogenic at doses 7 times and higher than the maximum recommended human intramuscular and subcutaneous dose on a mg/m2 basis (see Data).
The background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Clinical Considerations
Disease-Associated Maternal and Embryo/Fetal Risk:
During pregnancy, anaphylaxis can be catastrophic and can lead to hypoxic-ischemic encephalopathy and permanent central nervous system damage or death in the mother and, more commonly, in the fetus or neonate. Treatment of anaphylaxis during pregnancy should not be delayed.
Data
Animal Data
In an embryofetal development study with rabbits dosed during the period of organogenesis, epinephrine was shown to be teratogenic (including gastroschisis and embryonic lethality) at doses approximately 40 times the maximum recommended intramuscular or subcutaneous dose (on a mg/m2 basis at a maternal subcutaneous dose of 1.2 mg/kg/day for two to three days).
In an embryofetal development study with mice dosed during the period of organogenesis, epinephrine was shown to be teratogenic (including embryonic lethality) at doses approximately 8 times the maximum recommended intramuscular or subcutaneous dose (on a mg/m2 basis at maternal subcutaneous dose of 1 mg/kg/day for 10 days). These effects were not seen in mice at approximately 4 times the maximum recommended daily intramuscular or subcutaneous dose (on a mg/m2 basis at a subcutaneous maternal dose of 0.5 mg/kg/day for 10 days).
In an embryofetal development study with hamsters dosed during the period of organogenesis from gestation days 7 to 10, epinephrine was shown to be teratogenic at doses approximately 7 times the maximum recommended intramuscular or subcutaneous dose (on a mg/m2 basis at a maternal subcutaneous dose of 0.5 mg/kg/day).
8.2 Lactation
Risk Summary
There is no information on the presence of epinephrine in human milk, the effects on the breastfed infants, or the effects on milk production. However, due to its poor oral bioavailability and short half-life, transfer of epinephrine into breastmilk is expected to be low. Treatment of anaphylaxis in breastfeeding patients should not be delayed.
8.4 Pediatric Use
The safety and effectiveness of Epinephrine Injection for the emergency treatment of type I allergic reactions, including anaphylaxis have been established in pediatric patients who weigh 15 kg or greater. The use of Epinephrine Injection for this indication is supported by clinical experience. Clinical experience with the use of epinephrine suggests that the adverse reactions seen in pediatric patients are similar in nature and extent to those both expected and reported in adults. Since the doses of epinephrine delivered from Epinephrine Injection are fixed, use other forms of injectable epinephrine if doses lower than 0.15 mg are deemed necessary.
The safety and effectiveness of Epinephrine Injection have not been established in pediatric patients who weigh less than 15 kg.
8.5 Geriatric Use
Clinical studies of Epinephrine Injection for emergency treatment of type I allergic reactions, including anaphylaxis, were not conducted in geriatric patients aged 65 and over to determine whether they respond differently from younger adult patients. However, other reported clinical experience with use of epinephrine for the treatment of anaphylaxis has identified that geriatric patients may be particularly sensitive to the effects of epinephrine. Therefore, these patients may be at greater risk for developing adverse reactions after epinephrine administration.
10 OVERDOSAGE
Overdosage of epinephrine has been reported to produce extremely elevated arterial pressure, which may result in cerebrovascular hemorrhage, particularly in elderly patients. Overdosage may also result in pulmonary edema because of peripheral vascular constriction together with cardiac stimulation.
Epinephrine overdosage can also cause transient bradycardia followed by tachycardia which may be accompanied by fatal cardiac arrhythmias; premature ventricular contractions followed by multifocal ventricular tachycardia; atrial tachycardia and occasionally by atrioventricular block; extreme pallor and coldness of the skin; metabolic acidosis; kidney failure.
Epinephrine is rapidly inactivated in the body and treatment following overdosage with epinephrine is primarily supportive. Treatment of epinephrine associated pulmonary edema consists of a rapidly acting alpha-adrenergic blocking drug (such as phentolamine mesylate) and respiratory support. Treatment of epinephrine associated arrhythmias consists of administration of a beta-adrenergic blocking drug (such as propranolol). If necessary, pressor effects may be counteracted by rapidly acting vasodilators or α-adrenergic blocking drugs. If prolonged hypotension follows such measures, it may be necessary to administer another pressor drug.
Consider contacting the Poison Help line (1-800-222-1222) or a medical toxicologist for additional overdosage management recommendations.
11 DESCRIPTION
Epinephrine Injection, USP 0.3 mg and 0.15 mg, are single-dose auto-injectors and combination products containing drug and device components.
Each Epinephrine Injection, USP 0.3 mg, delivers a single dose of 0.3 mg epinephrine from Epinephrine Injection, USP (0.3 mL) in a sterile solution.
Each Epinephrine Injection, USP 0.15 mg, delivers a single dose of 0.15 mg epinephrine from Epinephrine Injection, USP (0.15 mL) in a sterile solution.
Epinephrine Injection, USP 0.3 mg and Epinephrine Injection, USP 0.15 mg each contain 1.1 mL of epinephrine solution. 0.3 mL and 0.15 mL epinephrine solution are dispensed for Epinephrine Injection, USP 0.3 mg and Epinephrine Injection, USP 0.15 mg, respectively, when activated. The solution remaining after activation is not available for future use and should be discarded.
Each 0.3 mL in Epinephrine Injection, USP 0.3 mg, contains 0.3 mg epinephrine, 2.6 mg sodium chloride, not more than 1.5 mg chlorobutanol, 0.45 mg sodium bisulfite, hydrochloric acid and sodium hydroxide to adjust pH, and water for injection. The pH range is 2.2-5.0.
Each 0.15 mL in Epinephrine Injection, USP 0.15 mg, contains 0.15 mg epinephrine, 1.3 mg sodium chloride, not more than 0.75 mg chlorobutanol, 0.225 mg sodium bisulfite, hydrochloric acid and sodium hydroxide to adjust pH, and water for injection. The pH range is 2.2-5.0.
Epinephrine is a sympathomimetic catecholamine. Chemically, epinephrine is (-)-3,4-Dihydroxy-α-[(methylamino)methyl]benzyl alcohol with the following structure:
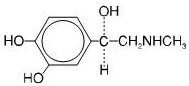
Epinephrine solution deteriorates rapidly on exposure to air or light, turning pink from oxidation to adrenochrome and brown from the formation of melanin. Replace Epinephrine Injection, USP if the epinephrine solution appears discolored (pinkish or brown color), cloudy, or contains particles.
12 CLINICAL PHARMACOLOGY
12.1 Mechanism of Action
Epinephrine acts on both alpha- and beta-adrenergic receptors.
Through its action on alpha-adrenergic receptors, epinephrine lessens the vasodilation and increased vascular permeability that occurs during anaphylaxis, which can lead to loss of intravascular fluid volume and hypotension.
Through its action on beta-adrenergic receptors, epinephrine causes bronchial smooth muscle relaxation and helps alleviate bronchospasm, wheezing, and dyspnea that may occur during anaphylaxis.
Epinephrine also alleviates pruritus, urticaria, and angioedema, and may relieve gastrointestinal and genitourinary symptoms associated with anaphylaxis because of its relaxer effects on the smooth muscle of the stomach, intestine, uterus and urinary bladder.
12.2 Pharmacodynamics
When given subcutaneously or intramuscularly, epinephrine has a rapid onset and short duration of action.
13 NONCLINICAL TOXICOLOGY
13.1 Carcinogenesis, Mutagenesis, Impairment of Fertility
Long-term studies to evaluate the carcinogenic potential of epinephrine have not been conducted.
Epinephrine and other catecholamines have been shown to have mutagenic potential in vitro. Epinephrine was positive in the Salmonella bacterial reverse mutation assay, positive in the mouse lymphoma assay, and negative in the in vivo micronucleus assay. Epinephrine is an oxidative mutagen based on the E. coli WP2 Mutoxitest bacterial reverse mutation assay. This should not prevent the use of epinephrine where indicated [see Indications and Usage (1)].
The potential for epinephrine to impair reproductive performance has not been evaluated, but epinephrine has been shown to decrease implantation in female rabbits dosed subcutaneously with 1.2 mg/kg/day (40-fold the highest human intramuscular or subcutaneous daily dose) during gestation days 3 to 9.
16 HOW SUPPLIED/STORAGE AND HANDLING
How Supplied
Epinephrine Injection is a clear and colorless solution for intramuscular or subcutaneous use. Epinephrine Injection is available as an auto-injector as described in Table 2.
Table 2 Epinephrine Injection Auto-injector Package Configurations and Strengths
| Strength | Package Configuration | NDC |
| 0.3 mg/0.3 mL | Each carton contains 2 single-dose prefilled auto-injectors in individual carrier tubes | NDC 0115-1694-49 |
| Auto-injector in carrier tube | NDC 0115-1694-30 | |
| 0.15 mg/0.15 mL | Each carton contains 2 single-dose prefilled auto-injectors in individual carrier tubes | NDC 0115-1695-49 |
| Auto-injector in carrier tube | NDC 0115-1695-30 |
Storage and Handling
- Protect from light. Epinephrine Injection is light sensitive and should be stored in the individual carrier tube provided.
- Store at 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [See USP Controlled Room Temperature].
- Do not refrigerate or freeze.
- Before using, check to make sure the solution in the auto-injector is clear and colorless.
- Replace the auto-injector if the solution is discolored (pinkish or brown color), cloudy, or contains particles.
- Properly dispose of all used, unwanted, or expired Epinephrine Injection, USP.
17 PATIENT COUNSELING INFORMATION
Advise the patient to read the FDA-approved patient labeling (Patient Information and Instructions for Use).
Administration
- Each Epinephrine Injection contains a single dose of epinephrine for single use.
- Instruct patients and/or caregivers to inspect the epinephrine solution visually through the viewing window periodically. Epinephrine Injection should be replaced if the epinephrine solution appears discolored, cloudy, or contains particles.
Instruct patients and/or caregivers on proper intramuscular or subcutaneous injection technique using the Epinephrine Injection Trainer. A Trainer device is not provided with epinephrine injection. Patients and/or caregivers may obtain a Trainer device at www.epinephrineautoinject.com. Instructions for use of the Trainer device are provided on the Trainer label. Instruct patients and/or caregivers to use the Trainer to familiarize themselves with the use of epinephrine injection in an allergic emergency. The Trainer device may be used multiple times.
For additional video instructions on the use of epinephrine injection,go to www.epinephrineautoinject.com.
- Instruct caregivers to hold the leg of young children or infants firmly in place and limit movement prior to and during injection. [see Warnings and Precautions (5.2)].
- Instruct patients and/or caregivers in the appropriate use of Epinephrine Injection.Epinephrine Injection should be injected into the middle of the outer thigh (through clothing if necessary).
- Instruct patients and/or caregivers when a second dose of Epinephrine Injection is needed. Administer a new Epinephrine Injection into the middle of the outer thigh starting 5 minutes after the first dose.
- Advise patients and/or caregivers when to seek emergency medical care for close monitoring of the type I allergic emergency and in the event that further treatment is required.
Injection-Related Complications
Advise patients to seek immediate medical care in the case of accidental injection into the digits, hands or feet because such an accidental injection to these areas may cause loss of blood flow to the affected area [see Warnings and Precautions (5.1)].
Serious Infections at the Injection Site
Advise patients that rare cases of serious skin and soft tissue infections, including necrotizing fasciitis and myonecrosis caused by Clostridia (gas gangrene), have been reported at the injection site following injection of epinephrine for anaphylaxis. Instruct patients to seek medical care if they develop signs or symptoms of infection, such as persistent redness, warmth, swelling, or tenderness, at the Epinephrine Injection site [see Warnings and Precautions (5.2)].
Risks Associated with Certain Coexisting Conditions
Advise patients with coexisting conditions (cardiac arrhythmia and ischemia, coronary artery disease, hypertension, pulmonary edema, hyperthyroidism, renal impairment, Parkinson's disease, diabetes), for increased risks that may be associated with use of epinephrine [see Warnings and Precautions (5.3)].
Storage and Handling
Epinephrine Injection is light sensitive and should be stored in the individual carrier tube provided to protect it from light. The individual carrier tube is not waterproof. Instruct patients that Epinephrine Injection must be properly disposed of once the blue end caps have been removed or after use [see How Supplied/Storage and Handling (16)].
Manufactured for and Distributed by:
Amneal Pharmaceuticals LLC
Bridgewater, NJ 08807
© 2025 Amneal Pharmaceuticals LLC. All rights reserved.
For inquiries call 1-877-835-5472
1871-05
Rev. 03-2026-05