


Prescribing information (package insert) - Xuriden
1 INDICATIONS AND USAGE
XURIDEN ®is indicated in adult and pediatric patients for the treatment of hereditary orotic aciduria.
2 DOSAGE AND ADMINISTRATION
2.1 Recommended Dosage
The recommended starting dosage of oral XURIDEN is 60 mg/kg once daily. Increase the dosage of XURIDEN to 120 mg/kg (not to exceed 8 grams) once daily for insufficient efficacy, such as occurrence of one of the following:
- Levels of orotic acid in urine remain above normal or increase above the usual or expected range for the patient
- Laboratory values (e.g., red blood cell or white blood cell indices) affected by hereditary orotic aciduria show evidence of worsening
- Worsening of other signs or symptoms of the disease
The XURIDEN dose to be administered at the 60 mg/kg and 120 mg/kg dose levels by body-weight is presented in Tables 1 and 2.
A 2 gram packet of XURIDEN contains approximately ¾ teaspoon of XURIDEN. Therefore, in the tables below for patients requiring doses in multiples of 2 grams (¾ teaspoon) an entire packet(s) may be administered without weighing or measuring.
XURIDEN Daily Dose Based on Body Weight (kg)
| Patient Weight | Table 1: XURIDEN 60 mg/kg total daily dose by weight category in the tables was rounded to achieve the approximate dose levelDose Level | |
|---|---|---|
| Kilograms | Dose to be Administered Using a Scale (grams) | Dose in Teaspoons |
| up to 5 | 0.4 | ⅛ |
| 6-10 | 0.4 to 0.6 | ¼ |
| 11-15 | 0.7 to 0.9 | ½ |
| 16-20 | 1 to 1.2 | |
| 21-25 | 1.3 to 1.5 | |
| 26-30 | 1.6 to 1.8 | ¾ |
| 31-35 | 1.9 to 2.1 may use 1 entire 2 gram packet without weighing or measuring | |
| 36-40 | 2.2 to 2.4 | 1 |
| 41-45 | 2.5 to 2.7 | |
| 46-50 | 2.8 to 3 | |
| 51-55 | 3.1 to 3.3 | 1 ¼ |
| 56-60 | 3.4 to 3.6 | |
| 61-65 | 3.7 to 3.9 may use 2 entire 2 gram packets without weighing or measuring | 1 ½ |
| 66-70 | 4 to 4.2 | |
| 71-75 | 4.3 to 4.5 | |
| Above 75 | 6 may use 3 entire 2 gram packets without weighing or measuring | 2 |
| Patient Weight | Table 2: XURIDEN 120 mg/kg total daily dose by weight category in the tables was rounded to achieve the approximate dose levelDose Level | |
|---|---|---|
| Kilograms | Dose to be Administered Using a Scale (grams) | Dose in Teaspoons |
| up to 5 | 0.8 | ¼ |
| 6-10 | 0.8 to 1.2 | ½ |
| 11-15 | 1.4 to 1.8 | ¾ |
| 16-20 | 2 to 2.4 | 1 |
| 21-25 | 2.6 to 3 | |
| 26-30 | 3.2 to 3.6 | 1 ¼ |
| 31-35 | 3.8 to 4.2 may use 2 entire 2 gram packets without weighing or measuring | 1 ½ |
| 36-40 | 4.4 to 4.8 | 1 ¾ |
| 41-45 | 5 to 5.4 | 2 may use 3 entire 2 gram packets without weighing or measuring |
| 46-50 | 5.6 to 6 | |
| 51-55 | 6.2 to 6.6 | 2 ¼ |
| 56-60 | 6.8 to 7.2 | 2 ½ |
| 61-65 | 7.4 to 7.8 | |
| 66-70 | 8 | 2 ¾ may use 4 entire 2 gram packets without weighing or measuring |
| 71-75 | 8 | |
| Above 75 | 8 | |
2.2 Preparation and Administration
Preparation
Measure the dose using either a scale accurate to at least 0.1 gram, or a graduated teaspoon, accurate to the fraction of the dose to be administered.
Once the measured dose has been removed from the XURIDEN packet, discard the unused portion of granules. Do not use any granules left in the open packet.
Administration with Food
- 1. Place 3 to 4 ounces of applesauce, pudding or yogurt in a small clean container.
- 2. Mix the measured amount of granules in the applesauce, pudding or yogurt
- 3. Swallow applesauce/pudding/yogurt immediately. Do not chew the granules. Do not save the applesauce/pudding/yogurt for later use.
- 4. Drink at least 4 ounces of water.
Administration in Milk or Infant Formula
XURIDEN can be mixed with milk or infant formula instead of the soft foods described above for patients receiving up to 3/4 teaspoon (2 grams) of XURIDEN. After weighing the dose of XURIDEN:
- 1. Pour 5 mL of milk or infant formula into a 30 mL medicine cup.
- 2. Insert the tip of the oral syringe into the medicine cup and draw up 5 mL of milk/infant formula into the syringe.
- 3. Hold the syringe with the tip pointing upward. Pull down on the plunger until the plunger reaches 10 mL. This will add air to the syringe.
- 4. Place the cap over the tip of the syringe. Then invert the syringe so the syringe tip is pointing down, and remove the plunger.
- 5. Pour the measured amount of XURIDEN granules into the syringe barrel and reinsert the syringe plunger. Do not push up on the plunger.
- 6. Gently swirl the syringe to mix the XURIDEN granules with the liquid.
- 7. Turn the syringe so the syringe tip is pointing up. Then remove the syringe cap and push up on the plunger until the plunger reaches the 5 mL mark. This will remove air from the syringe.
- 8. Place the tip of the syringe in the patient's mouth between the cheek and gum at the back of the mouth. Gently push the plunger all the way down.
- 9. Refill the syringe with another 5 mL of milk/infant formula.
- 10. Gently swirl the syringe to rinse any remaining XURIDEN granules from the syringe barrel.
- 11. Place the tip of the syringe in the patient's mouth between the cheek and gum at the back of the mouth. Gently push the plunger all the way down.
- 12. Follow with a bottle of milk or infant formula, if desired.
3 DOSAGE FORMS AND STRENGTHS
Oral granules: 2 grams of orange-flavored oral granules (95% w/w) in single-use packets
4 CONTRAINDICATIONS
None
5 WARNINGS AND PRECAUTIONS
None
6 ADVERSE REACTIONS
6.1 Clinical Trials Experience
Because clinical trials are conducted under widely varying conditions and using a wide range of doses, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice.
The safety of XURIDEN was assessed in 4 patients with hereditary orotic aciduria ranging in age from 3 to 19 years (3 male, 1 female) who received 60 mg/kg of XURIDEN once daily for six weeks. All patients continued to receive XURIDEN for at least 24 months at dosages of up to 120 mg/kg once daily. No adverse reactions were reported with XURIDEN.
8 USE IN SPECIFIC POPULATIONS
8.1 Pregnancy
Risk Summary
There are no available data on XURIDEN use in pregnant women to inform a drug-associated risk. When administered orally to pregnant rats during the period of organogenesis, uridine triacetate at doses similar to the maximum recommended human dose (MRHD) of 120 mg/kg per day was not teratogenic and did not produce adverse effects on embryo-fetal development [see Data] .
The background risk of major birth defects and miscarriage for the indicated population are unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Data
Animal Data
In an embryo-fetal development study, uridine triacetate was administered orally to pregnant rats during the period of organogenesis at doses up to 2000 mg/kg per day (about 2.7 times the maximum recommended human dose (MRHD) of 120 mg/kg per day on a body surface area basis). There was no evidence of teratogenicity or harm to the fetus and no effect on maternal body weight and overall health.
8.2 Lactation
Risk Summary
There are no data on the presence of uridine triacetate in human milk, the effect on the breastfed infant or the effect on milk production. The development and health benefits of breastfeeding should be considered along with the mother's clinical need for XURIDEN and any potential adverse effects on the breastfed infant from XURIDEN or from the underlying maternal condition.
8.4 Pediatric Use
The safety and effectiveness of XURIDEN have been established in pediatric patients. Use of XURIDEN is supported by a single open-label clinical trial of uridine triacetate in 4 patients and a retrospective review of the clinical course of 18 patients with hereditary orotic aciduria who were treated with uridine beginning at ages 2 months to 12 years. There are no apparent differences in clinical response between adults and pediatric patients with hereditary orotic aciduria treated with uridine, however, data are limited [see Clinical Studies (14)] .
8.5 Geriatric Use
Clinical trials of XURIDEN did not include patients 65 years of age and older.
11 DESCRIPTION
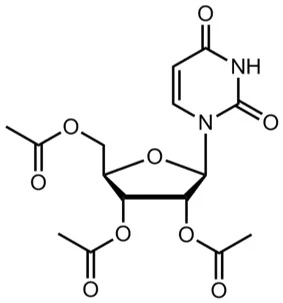
XURIDEN (uridine triacetate) oral granules is a pyrimidine analog indicated for uridine replacement therapy. Uridine triacetate has the chemical designation (2',3',5'-tri-O-acetyl-β-D-ribofuranosyl)-2,4(1H,3H)-pyrimidinedione. The molecular weight is 370.3 and it has an empirical formula of C 15H 18N 2O 9. The structural formula is:
Each single-use 2-gram packet of XURIDEN orange-flavored oral granules (95% w/w) contains 2 grams of uridine triacetate and the following inactive ingredients: ethylcellulose (0.062 grams), Opadry Clear [proprietary dispersion of hydroxypropylmethylcellulose and Macrogol] (0.015 grams), and natural orange juice flavor (0.026 grams).
12 CLINICAL PHARMACOLOGY
12.1 Mechanism of Action
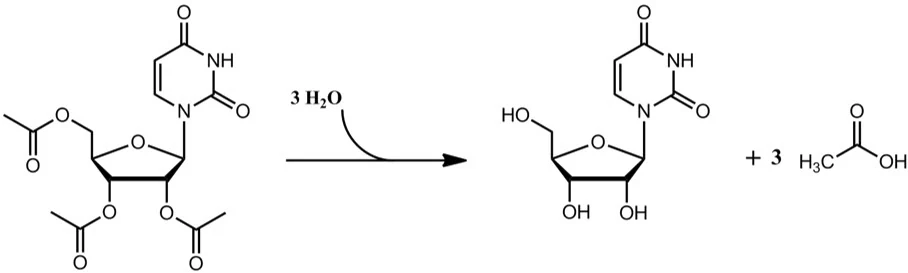
Uridine triacetate is an acetylated form of uridine. Following oral administration, uridine triacetate is deacetylated by nonspecific esterases present throughout the body, yielding uridine in the circulation (Figure 1).
Figure 1: Uridine Triacetate Conversion to Uridine
XURIDEN provides uridine in the systemic circulation of patients with hereditary orotic aciduria who cannot synthesize adequate quantities of uridine due to a genetic defect in uridine nucleotide synthesis.
12.2 Pharmacodynamics
Hereditary orotic aciduria (uridine monophosphate synthase deficiency) is a rare congenital autosomal recessive disorder of pyrimidine metabolism caused by a defect in uridine monophosphate synthase (UMPS). The UMPS gene encodes uridine 5′monophosphate synthase, a bifunctional enzyme that catalyzes the final two steps of the de novo pyrimidine biosynthetic pathway in mammalian cells.
The defect in UMP synthase in hereditary orotic aciduria has two primary biochemical consequences. First, the blockade of de novo UMP synthesis results in a systemic deficiency of pyrimidine nucleotides, accounting for most clinical consequences of the disease. Second, orotic acid from the de novo pyrimidine pathway that cannot be converted to UMP is excreted in the urine, accounting for the common name of the disorder, orotic aciduria. Orotic acid crystals in the urine can cause episodes of obstructive uropathy.
XURIDEN delivers uridine into the circulation, where it can be used by essentially all cells to make uridine nucleotides, compensating for the genetic deficiency in synthesis in patients with hereditary orotic aciduria. When intracellular uridine nucleotides are restored into the normal range, overproduction of orotic acid is reduced by feedback inhibition, so that urinary excretion of orotic acid is also reduced.
12.3 Pharmacokinetics
Absorption
XURIDEN delivers 4- to 6-fold more uridine into the systemic circulation compared to equimolar doses of uridine itself. Maximum concentrations of uridine in plasma following oral XURIDEN are generally achieved within 2 to 3 hours, and the half-life ranges from approximately 2 to 2.5 hours.
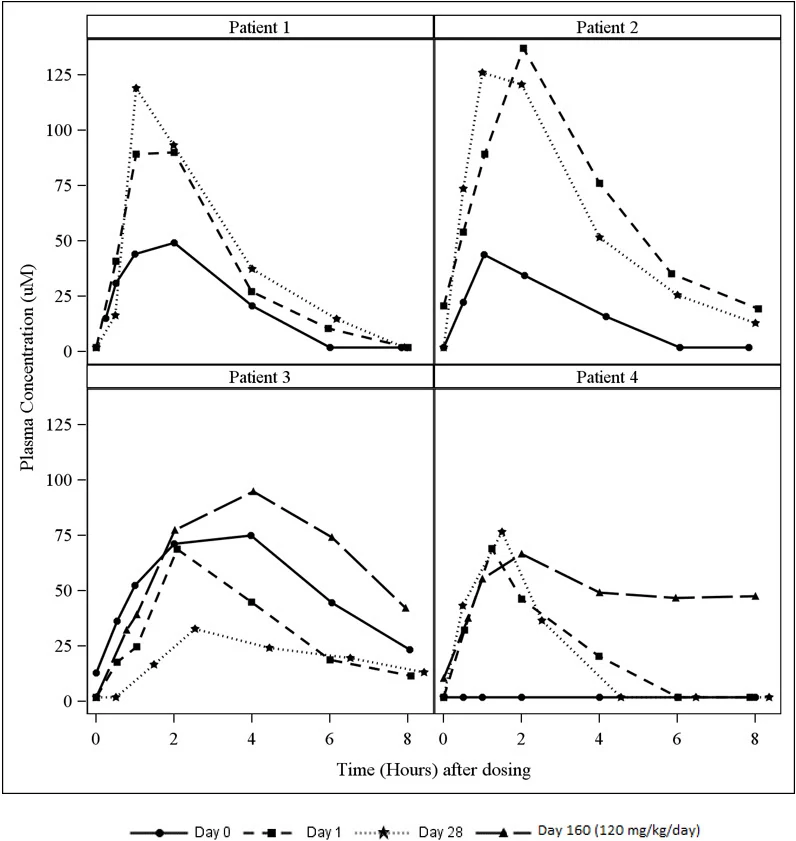
A study in patients with hereditary orotic aciduria included an assessment of plasma uridine pharmacokinetics in 4 patients. Three of the patients were previously treated with oral uridine. On Day 0 (baseline), these three patients received their usual daily dose of oral uridine as a single dose (150 to 200 mg/kg once daily) and on Day 1, initiated oral XURIDEN treatment (60 mg/kg once daily). A fourth patient was enrolled who was naïve to uridine replacement therapy. The dose of XURIDEN was increased on Day 116 to 120 mg/kg once daily in two patients (Patients 3 and 4) and plasma uridine concentrations were assessed on Day 160 (44 days after the dose increase).
Plasma uridine levels in all four patients are depicted in Figure 2. Pharmacokinetic parameters are summarized in Table 3. Mean exposure to plasma uridine as assessed by C maxand AUC was greater after oral XURIDEN than after oral uridine (approximately 4-fold on an equiweight basis, and 6-fold on an equimolar basis), although individual differences in relative bioavailability were noted. Plasma concentrations of the uridine catabolite uracil were generally below the limit of quantitation in all patients.
Table 3: Pharmacokinetic Parameters for Plasma Uridine
Pharmacokinetic Parameters (Plasma Uridine) | Day 0 (Baseline) (Oral Uridine, 150 to 200 mg/kg once daily) N = 3 Data shown are from patients previously treated with oral uridine | Day 1 (Oral XURIDEN, 60 mg/kg once daily) N = 4 | Day 28 (Oral XURIDEN, 60 mg/kg once daily) N = 4 | Day 160 (Oral XURIDEN, 120 mg/kg once daily) N = 2 The dose of XURIDEN was increased on Day 116 to 120 mg/kg per day. Serial plasma samples were taken on Day 160 (44 days after the dose increase) for plasma uridine levels. |
|---|---|---|---|---|
C max(µM) mean ± SD | 56.0 ± 16.6 | 91.3 ± 32.2 | 88.7 ± 43.2 | 80.9 ± 20.0 |
T max(hours) median (range T max range is expressed as the minimum and maximum values obtained ) | 2.0 (1.0, 4.0) | 2.0 (1.2, 2.1) | 1.3 (1.0, 2.5) | 3.0 (2.0, 4.0) |
t ½(hours) mean ± SD | 1.6 ± 0.7 | 1.6 ± 0.6 | 2.3 ± 1.6 | 8.2 ± 6.8 |
AUC (0-8)(µM∙hr) mean ± SD | 238.0 ± 163.2 | 311.2 ± 153.3 | 278.7 ± 148.5 | 465.6 ± 95.3 |
Figure 2 Plasma Uridine Following Oral Administration of Uridine (Day 0) or XURIDEN (Days 1, 28 and 160) in Patients with Hereditary Orotic Aciduria
Food Effect on Uridine PK:A study in healthy adult subjects receiving a slightly different formulation of uridine triacetate granules (6 gram dose) under fed and fasted conditions showed no difference in the overall rate and extent of uridine exposure.
Distribution
Circulating uridine is taken up into mammalian cells via specific nucleoside transporters, and also crosses the blood brain barrier.
Excretion
Uridine can be excreted via the kidneys, but is also metabolized by normal pyrimidine catabolic pathways present in most tissues.
Drug Interaction Studies
In vitroenzyme inhibition data did not reveal meaningful inhibitory effects of uridine triacetate or uridine on CYP3A4, CYP1A2, CYP2C8, CYP2C9, CYP2C19, CYP2D6, and CYP2E1. In vitroenzyme induction data did not reveal an inducing effect of uridine triacetate or uridine on CYP1A2, CYP2B6, or CYP3A4.
In vitrodata showed that uridine triacetate was a weak substrate for P-glycoprotein. Uridine triacetate inhibited the transport of a known P-glycoprotein substrate, digoxin, with an IC50 of 344 µM. Due to the potential for high local (gut) concentrations of the drug after dosing, the interaction of XURIDEN with orally administered P-gp substrate drugs cannot be ruled out.
In vivodata in humans are not available.
13 NONCLINICAL TOXICOLOGY
13.1 Carcinogenesis, Mutagenesis, Impairment of Fertility
Long-term studies in animals have not been performed to evaluate the carcinogenic potential of uridine triacetate.
Uridine triacetate was not genotoxic in the Ames test, the mouse lymphoma assay and the mouse micronucleus test.
Orally administered uridine triacetate did not affect fertility or general reproductive performance in male and female rats at doses up to 2000 mg/kg per day (about 2.7 times the maximum recommended human dose (MRHD) of 120 mg/kg per day on a body surface area basis).
14 CLINICAL STUDIES
The efficacy of XURIDEN was evaluated in a 6-week open-label study in 4 patients with hereditary orotic aciduria (3 male, 1 female; age range from 3 to 19 years). Three patients were previously treated with uridine and were switched at study entry to XURIDEN. All patients were administered XURIDEN orally at a daily dosage of 60 mg/kg once daily. Following the initial 6-weeks, all 4 patients continued to receive XURIDEN daily in the extension phase of the study at dosages of 60 to 120 mg/kg for a total duration of 24 months.
The study assessed changes in the patients' pre-specified hematologic parameters during the initial 6-week period and the extension phase. The pre-specified hematologic parameters were: neutrophil count and percent neutrophils (Patient 1), white blood cell count (Patient 2), and mean corpuscular volume (Patients 3 and 4). For patients switched from oral uridine to oral XURIDEN (Patients 1, 2, and 3), the primary endpoint was stability of the hematologic parameter; for the treatment-naïve patient (Patient 4), the primary endpoint was improvement of the hematologic parameter.
Secondary endpoints were urine orotic acid and orotidine levels, and growth (height and weight) for all patients.
Table 4 summarizes the changes in the patients' pre-specified hematologic parameters at Week 6 and 24 Months compared to baseline. After 6 weeks of treatment, Patients 1 and 3 met the pre-specified criteria for stability of the hematologic parameter. When Patient 2 was switched from uridine to XURIDEN treatment, the pre-specified parameter of white blood cell count remained stable; however, documentation of a low white blood cell count prior to uridine initiation was not available. Patient 4 did not meet the pre-specified endpoint of improvement of the hematologic parameter.
By 24 months of treatment with XURIDEN, the pre-specified hematologic parameter for Patient 1 worsened, but the assessment was confounded by Cohen syndrome with associated neutropenia, which was diagnosed after the patient completed the study. The pre-specified hematologic parameters for Patients 2, 3, and 4 remained essentially unchanged.
Table 4: Pre-Specified Hematologic Parameters at Baseline, 6 Weeks and 24 Months in XURIDEN-Treated Patients with Hereditary Orotic Aciduria
| Patient | Pre-specified Hematologic Parameter (Age-specific reference range) | Baseline (Day 0) | 6 Weeks (% Change from Baseline) | 24 Months (% Change from Baseline) |
|---|---|---|---|---|
| Patient 1 | Neutrophil Count (1.5 to 8.0 x10 3/mm 3) | 0.95 | 0.81 (-15%) | 0.61 (-36%) |
Neutrophil % (26 to 48%) | 21 | 23 (10%) | 13 (-38%) | |
| Patient 2 | White Blood Cell Count (3.8 to 10.6 x10 9/L) | 7.8 | 7.4 (-5%) | 8.6 (10%) |
| Patient 3 | Mean Corpuscular Volume (75 to 91 fL) | 109.9 | 108.5 (-1%) | 108.8 (-1%) |
| Patient 4 | Mean Corpuscular Volume (72 to 90 fL) | 114.6 | 113.4 (-1%) | 112.9 (-1.5%) |
At baseline, Patients 1, 2, and 3, previously treated with uridine, had normal urine orotic acid levels, and those remained stable after 6 weeks of treatment with XURIDEN. All four patients had normal urine orotidine levels at baseline which remained stable after 6 weeks of treatment with XURIDEN. After 24 months of treatment, urine orotic acid and orotidine levels remained stable in all four patients.
The treatment effect of XURIDEN on growth was assessed in the three pediatric patients (Patients 1, 3, and 4). At baseline, weight and height were at or below the lower limit of normal for age for all three patients. After 24 months of treatment, each patient's growth parameters remained essentially unchanged.
Case reports
Nineteen (19) case reports of patients with hereditary orotic aciduria have been documented in published literature. Eighteen (18) patients were diagnosed as infants or children between the ages of 2 months and 12 years and were treated with exogenous sources of uridine. One patient, diagnosed at age 28, was not treated with exogenous uridine.
All 19 patients presented with significantly elevated levels of urinary orotic acid. Fifteen of 19 had abnormal hematologic parameters at presentation, including 15 with megaloblastic anemia, 8 with leukopenia and at least 2 with neutropenia. Oral administration of exogenous sources of uridine was reported to significantly improve hematologic abnormalities (megaloblastic anemia, leukopenia and neutropenia) within 2 to 3 weeks in almost all documented cases when administered in sufficient amounts. Concentrations of urinary orotic acid were significantly reduced within 1 to 2 weeks of initiating uridine replacement therapy. Some fluctuation in levels of urinary orotic acid were observed, but always at much lower levels than those reported prior to treatment. Improvements in body weight were also documented over time with continued uridine replacement therapy.
The effects of exogenous uridine were maintained over months and years, as long as treatment continued at sufficient doses (with appropriate dose increases based on body weight increases). Most hematologic abnormalities and orotic aciduria reappeared within days up to 2 or 3 weeks when administration of uridine was stopped or the dose was reduced. If treatment was interrupted for longer periods, body weight growth receded. If absolute dosages were not adjusted adequately to compensate for body weight gains, signs and symptoms of hereditary orotic aciduria recurred.
16 HOW SUPPLIED/STORAGE AND HANDLING
XURIDEN orange-flavored oral granules (95% w/w) are available in single-use packets (NDC 50633-330-02) containing 2 grams of uridine triacetate in cartons of 30 packets each (NDC 50633-330-30).
Store at controlled room temperature, 25°C (77°F); excursions permitted to 15° to 30°C (59° to 86°F).
17 PATIENT COUNSELING INFORMATION
Advise the patient or caregiver to read the FDA-approved patient labeling (Instructions for Use)
Administration
Advise the patient or caregiver:
- To measure the prescribed dose using either a scale accurate to at least 0.1 gram, or a graduated teaspoon, accurate to the fraction of the dose to be administered.
- To discard the unused portion of granules in a packet after measuring out the dose.
- That XURIDEN can be taken mixed in food (applesauce, pudding or yogurt) or mixed in milk or infant formula.
- That the XURIDEN granules should not be chewed.
Manufactured for and distributed by: -
BTG International Inc.
West Conshohocken, PA, 19428
XURIDEN ®is a registered trademark of BTG International Inc. The SERB logo is a registered trademark of SERB S.à.r.l.