


Prescribing information (package insert) - Welireg
WARNING: EMBRYO-FETAL TOXICITY
- Exposure to WELIREG during pregnancy can cause embryo-fetal harm.
- Verify pregnancy status prior to the initiation of WELIREG.
- Advise patients of these risks and the need for effective non-hormonal contraception. WELIREG can render some hormonal contraceptives ineffective [see Warnings and Precautions (5.4), Drug Interactions (7.2), Use in Specific Populations (8.1, 8.3)].
1 INDICATIONS AND USAGE
1.1 von Hippel-Lindau disease
WELIREG is indicated for treatment of adult patients with von Hippel-Lindau (VHL) disease who require therapy for associated renal cell carcinoma (RCC), central nervous system (CNS) hemangioblastomas, or pancreatic neuroendocrine tumors (pNET), not requiring immediate surgery.
1.2 Renal Cell Carcinoma with a Clear Cell Component
- WELIREG, in combination with pembrolizumab or pembrolizumab and berahyaluronidase alfa-pmph, is indicated for the adjuvant treatment of adult patients with renal cell carcinoma with a clear cell component (ccRCC) at intermediate-high or high risk of recurrence following nephrectomy, or following nephrectomy and resection of metastatic lesions.
- WELIREG, in combination with lenvatinib, is indicated for the treatment of adult patients with advanced ccRCC following a programmed death receptor-1 (PD-1) or programmed death-ligand 1 (PD-L1) inhibitor.
- WELIREG, as monotherapy, is indicated for the treatment of adult patients with advanced ccRCC following a PD-1 or PD-L1 inhibitor and a vascular endothelial growth factor tyrosine kinase inhibitor (VEGF-TKI).
1.3 Pheochromocytoma or Paraganglioma
WELIREG is indicated for the treatment of adult and pediatric patients 12 years and older with locally advanced, unresectable, or metastatic pheochromocytoma or paraganglioma (PPGL).
2 DOSAGE AND ADMINISTRATION
2.1 Recommended Dosage
The recommended dosages for WELIREG are listed in Table 1.
Table 1: Recommended Dosage
| Indication | Recommended WELIREG Dosage | Duration of Therapy |
|---|---|---|
| von Hippel-Lindau Disease | 120 mg orally once daily. | Until disease progression or unacceptable toxicity. |
| Adjuvant Treatment of ccRCC | 120 mg orally once daily in combination with pembrolizumab or pembrolizumab and berahyaluronidase alfa-pmph.Refer to the Prescribing Information of the individual therapeutic agents used in combination with WELIREG for dosing and administration information. | Until disease recurrence or unacceptable toxicity, or up to 54 weeks. |
| Advanced ccRCC | 120 mg orally once daily as monotherapy or in combination with lenvatinib. | Until disease progression or unacceptable toxicity. |
| Pheochromocytoma or Paraganglioma | Adults:
Pediatric patients 12 years and older based on bodyweight:
| Until disease progression or unacceptable toxicity. |
Administration Instructions
WELIREG should be taken at the same time each day and may be taken with or without food [see Clinical Pharmacology (12.3)].
Advise patients to swallow tablets whole. Do not chew, crush, or split WELIREG prior to swallowing.
If a dose of WELIREG is missed, it can be taken as soon as possible on the same day. Resume the regular daily dose schedule for WELIREG the next day. Do not take extra tablets to make up for the missed dose.
If vomiting occurs any time after taking WELIREG, do not retake the dose. Take the next dose on the next day.
2.2 Dosage Modifications for Adverse Reactions
Dosage modifications for WELIREG for adverse reactions are summarized in Table 2 and Table 3.
The recommended dose reductions are:
- First dose reduction: WELIREG 80 mg orally once daily
- Second dose reduction: WELIREG 40 mg orally once daily
- Third dose reduction: Permanently discontinue
Table 2: Recommended Dosage Modifications for Adverse Reactions
| Adverse Reaction | Severity | Dosage Modification |
|---|---|---|
Anemia [see Warnings and Precautions (5.1)] | Adjuvant ccRCC Indication: | |
| Hemoglobin <9 g/dL or transfusion indicated |
| |
| Life-threatening or urgent intervention indicated |
| |
| All Other Indications: | ||
| Hemoglobin <8 g/dL or transfusion indicated |
| |
| Life-threatening or urgent intervention indicated |
| |
Hypoxia [see Warnings and Precautions (5.2)] | Decreased oxygen saturation with exercise (e.g., pulse oximeter <88%) |
|
| Decreased oxygen saturation at rest (e.g., pulse oximeter <88% or PaO2 ≤55 mm Hg) or urgent intervention indicated Life-threatening or recurrent symptomatic hypoxia |
| |
Other Adverse Reactions [see Adverse Reactions (6)] | Grade 3 |
|
| Grade 4 |
| |
Refer to the Prescribing Information of the individual therapeutic agents used in combination with WELIREG for dosage modifications for adverse reactions.
Additional recommended dosage modifications for adverse reactions when WELIREG is administered in combination with lenvatinib are provided in Table 3.
Table 3: Recommended Dosage Modifications for Adverse Reactions for WELIREG in Combination with Lenvatinib
| Adverse Reaction | Severity | Dosage Modification |
|---|---|---|
Cardiac Dysfunction [see Warnings and Precautions (5.3)] | Grade 3 |
|
| Grade 4 |
|
Refer to the Prescribing Information of lenvatinib for additional dosage modifications for adverse reactions.
3 DOSAGE FORMS AND STRENGTHS
Tablets: 40 mg, blue, oval shaped, film-coated, debossed with “177” on one side and plain on the other side.
4 CONTRAINDICATIONS
None.
5 WARNINGS AND PRECAUTIONS
5.1 Anemia
WELIREG can cause severe anemia that can require blood transfusion.
Monitor for anemia before initiation of, and periodically throughout, treatment with WELIREG. Transfuse patients as clinically indicated. Withhold, reduce dose, or permanently discontinue WELIREG based on severity [see Dosage and Administration (2.2)].
von Hippel-Lindau (VHL) disease
In LITESPARK-004, decreased hemoglobin occurred in 93% of patients and 7% had Grade 3 events [see Adverse Reactions (6.1)]. Median time to onset of anemia was 31 days (range: 1 day to 8.4 months).
The safety of erythropoiesis stimulating agents (ESAs) for treatment of anemia in patients with VHL disease treated with WELIREG has not been established. Randomized controlled trials in patients with cancer receiving myelosuppressive chemotherapy with ESAs have shown that ESAs increased the risks of death and serious cardiovascular reactions, and decreased progression-free survival and/or overall survival. See the prescribing information for ESAs for more information.
Renal Cell Carcinoma with a Clear Cell Component (ccRCC)
In LITESPARK-005, decreased hemoglobin occurred in 88% of patients and 29% had Grade 3 events [see Adverse Reactions (6.1)]. Median time to onset of anemia was 29 days (range: 1 day to 16.6 months). Of the patients with anemia, 22% received transfusions only, 20% of patients received ESAs only and 12% received both transfusion and ESAs.
In LITESPARK-022, decreased hemoglobin occurred in 95% of patients receiving WELIREG in combination with pembrolizumab and 11% had Grade 3 or higher events [see Adverse Reactions (6.1)]. Median time to onset of anemia was 42 days (range: 1 day to 11.1 months). Of the patients with anemia, 5% received transfusions only, 8% received ESAs only, and 1.3% received both transfusion and ESAs.
In LITESPARK-011, decreased hemoglobin occurred in 87% of patients receiving WELIREG in combination with lenvatinib and 20% had Grade 3 events or required transfusion [see Adverse Reactions (6.1)]. Median time to onset of anemia was 56 days (range: 1 day to 33 months). Of the patients with anemia, 15% of patients received transfusions only, 22% received ESAs only, and 8% received both transfusion and ESAs.
Pheochromocytoma or Paraganglioma (PPGL)
In LITESPARK-015, anemia occurred in 96% of patients and 22% had Grade 3 events [see Adverse Reactions (6.1)]. Median time to onset of anemia was 29 days (range: 1 day to 22.1 months). Of the patients with anemia, 20% received transfusions only, 26% received ESAs only, and 6% received both transfusion and ESAs.
5.2 Hypoxia
WELIREG can cause severe hypoxia that may require discontinuation, supplemental oxygen, or hospitalization [see Dosage and Administration (2.2)].
Monitor oxygen saturation before initiation of, and periodically throughout, treatment with WELIREG. For decreased oxygen saturation with exercise (e.g., pulse oximeter <88% or PaO2 ≤55 mm Hg), consider withholding WELIREG until pulse oximetry with exercise is greater than 88%, then resume at the same dose or at a reduced dose. For decreased oxygen saturation at rest (e.g., pulse oximeter <88% or PaO2 ≤55 mm Hg) or urgent intervention indicated, withhold WELIREG until resolved and resume at a reduced dose or discontinue. For life-threatening hypoxia or for recurrent symptomatic hypoxia, permanently discontinue WELIREG [see Dosage and Administration (2.2)].
Advise patients to report signs and symptoms of hypoxia immediately to a healthcare provider.
von Hippel-Lindau (VHL) disease
In LITESPARK-004, hypoxia occurred in 1.6% of patients [see Adverse Reactions (6.1)].
Renal Cell Carcinoma with a Clear Cell Component (ccRCC)
In LITESPARK-005, hypoxia occurred in 15% of patients and 10% had Grade 3 events [see Adverse Reactions (6.1)]. Of the patients with hypoxia, 69% were treated with oxygen therapy. Median time to onset of hypoxia was 30.5 days (range: 1 day to 21.1 months).
In LITESPARK-022, hypoxia occurred in 7% of patients receiving WELIREG in combination with pembrolizumab and 5% had Grade 3 or higher events [see Adverse Reactions (6.1)]. Of the patients with hypoxia, 47% were treated with oxygen therapy. Median time to onset of hypoxia was 93 days (range: 9 days to 11.7 months).
In LITESPARK-011, hypoxia occurred in 16% of patients receiving WELIREG in combination with lenvatinib 12% had Grade 3-4 events [see Adverse Reactions (6.1)]. Of the patients with hypoxia, 62% of patients were treated with oxygen therapy. Median time to onset was 63 days (range: 4 days to 25 months).
Pheochromocytoma or Paraganglioma (PPGL)
In LITESPARK-015, hypoxia occurred in 13% of patients and 10% had Grade 3 hypoxia [see Adverse Reactions (6.1)]. Median time to onset of hypoxia was 35 days (range: 6 days to 23.9 months). Of the patients with hypoxia, 67% were treated with oxygen therapy.
5.3 Cardiac Dysfunction with Concomitant Use of WELIREG and Lenvatinib
Serious cardiac dysfunction, including heart failure with reduced left ventricular ejection fraction (LVEF), and cardiomyopathy, can occur with WELIREG in combination with lenvatinib. The safety of WELIREG in combination with lenvatinib has not been established in patients with LVEF below 50%.
In patients treated with WELIREG in combination with lenvatinib in the LITESPARK-011 trial, Grade 3 or higher cardiac dysfunction adverse events occurred in 6% of patients. The median time to onset of Grade 3 or higher cardiac dysfunction was 26 weeks (range: 1 to 192 weeks). An absolute decrease in LVEF >20% with or without clinical symptoms occurred in 6% of patients. The median time to onset of LVEF decrease >20% was 29 weeks (range: 2 to 192 weeks).
Consider obtaining a baseline echocardiogram or Multigated Acquisition (MUGA) imaging. Monitor patients for symptoms or signs of heart failure and if present, reassess LVEF. Withhold and resume at a reduced dose upon recovery to baseline or Grade 1 or permanently discontinue WELIREG in combination with lenvatinib based on severity [see Dosage and Administration (2.2)].
5.4 Embryo-Fetal Toxicity
Based on findings in animals, WELIREG can cause fetal harm when administered to a pregnant woman. In an animal reproduction study, oral administration of belzutifan to pregnant rats during the period of organogenesis caused embryo-fetal lethality, reduced fetal body weight, and fetal skeletal malformations at maternal exposures ≥0.2 times the human exposures (AUC) at the recommended dose of 120 mg daily.
Advise pregnant women and females of reproductive potential of the potential risk to the fetus. Advise females of reproductive potential to use effective non-hormonal contraception during treatment with WELIREG and for 1 week after the last dose, since WELIREG can render some hormonal contraceptives ineffective [see Drug Interactions (7.2)]. Advise male patients with female partners of reproductive potential to use effective contraception during treatment with WELIREG and for 1 week after the last dose [see Use in Specific Populations (8.1, 8.3)].
6 ADVERSE REACTIONS
The following clinically significant adverse reactions are discussed elsewhere in the labeling:
- Anemia [see Warnings and Precautions (5.1)]
- Hypoxia [see Warnings and Precautions (5.2)]
- Cardiac Dysfunction with Concomitant Use of WELIREG and Lenvatinib [see Warnings and Precautions (5.3)]
6.1 Clinical Trials Experience
Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice.
von Hippel-Lindau (VHL) disease
LITESPARK-004
The safety of WELIREG was evaluated in an open-label clinical trial (LITESPARK-004) in 61 patients with VHL disease who had at least one measurable solid tumor localized to the kidney [see Clinical Studies (14.1)]. Patients received WELIREG 120 mg orally once daily until disease progression or unacceptable toxicity. The median duration of exposure to WELIREG was 68 weeks (range: 8.4 to 104.7 weeks).
Serious adverse reactions occurred in 15% of patients who received WELIREG, including anemia, hypoxia, anaphylaxis reaction, retinal detachment, and central retinal vein occlusion (1 patient each).
Permanent discontinuation of WELIREG due to adverse reactions occurred in 3.3% of patients. Adverse reactions which resulted in permanent discontinuation of WELIREG were dizziness and opioid overdose (1.6% each).
Dosage interruptions of WELIREG due to an adverse reaction occurred in 39% of patients. Adverse reactions which required dosage interruption in >2% of patients were fatigue, decreased hemoglobin, anemia, nausea, abdominal pain, headache, and influenza-like illness.
Dose reductions of WELIREG due to an adverse reaction occurred in 13% of patients. The most frequently reported adverse reaction which required dose reduction was fatigue (7%).
The most common (≥25%) adverse reactions, including laboratory abnormalities, that occurred in patients who received WELIREG were decreased hemoglobin, fatigue, increased creatinine, headache, dizziness, increased glucose, and nausea.
Table 4 summarizes the adverse reactions reported in patients treated with WELIREG in LITESPARK-004.
Table 4: Adverse Reactions Occurring in ≥10% of Patients Who Received WELIREG in LITESPARK-004
| Adverse Reaction | WELIREG (n=61) | |
|---|---|---|
All GradesGraded per NCI CTCAE v4.0 (%) | Grade 3-4 (%) | |
| General | ||
| FatigueIncludes other related terms | 64 | 5 |
| Nervous system | ||
| Headache | 39 | 0 |
| Dizziness | 38 | 0 |
| Gastrointestinal | ||
| Nausea | 31 | 0 |
| Constipation | 13 | 0 |
| Abdominal pain | 13 | 0 |
| Eye Disorders | ||
| Visual impairmentIncludes visual impairment, vision blurred, central retinal vein occlusion and retinal detachment | 21 | 3.3 |
| Infections | ||
| Upper respiratory tract infection | 21 | 0 |
| Respiratory, Thoracic and Mediastinal | ||
| Dyspnea | 20 | 1.6 |
| Musculoskeletal and Connective Tissue | ||
| Arthralgia | 18 | 0 |
| Myalgia | 16 | 0 |
| Vascular | ||
| Hypertension | 13 | 3.3 |
| Metabolism and Nutrition | ||
| Weight increased | 12 | 1.6 |
Table 5 summarizes the laboratory abnormalities in LITESPARK-004.
Table 5: Select Laboratory Abnormalities (≥10%) That Worsened from Baseline in Patients Who Received WELIREG in LITESPARK-004
| Laboratory AbnormalityThe denominator used to calculate the rate is based on all patients in the safety analysis population. | WELIREG (n=61) | |
|---|---|---|
Grades 1-4 % | Grades 3-4 % | |
| Hematology | ||
| Decreased hemoglobin | 93 | 7 |
| Decreased leukocytes | 11 | 0 |
| Chemistry | ||
| Increased creatinine | 64 | 0 |
| Increased glucose | 34 | 4.9 |
| Increased ALT | 20 | 0 |
| Increased AST | 16 | 0 |
| Decreased calcium (corrected) | 10 | 0 |
| Decreased phosphate | 10 | 1.6 |
Renal Cell Carcinoma with a Clear Cell Component (ccRCC)
LITESPARK-022
The safety of WELIREG in combination with intravenous pembrolizumab versus placebo in combination with intravenous pembrolizumab was investigated in LITESPARK-022, a randomized, double-blind trial in 1,828 patients who had undergone nephrectomy for ccRCC [see Clinical Studies (14.2)]. Patients received either WELIREG 120 mg orally once daily in combination with pembrolizumab 400 mg intravenously every 6 weeks (n=915), or oral placebo in combination with pembrolizumab 400 mg intravenously every 6 weeks (n=913) for up to 9 cycles (54 weeks) until disease recurrence or unacceptable toxicity. The median duration of exposure to WELIREG was 12.4 months (range: 1 day to 20.1 months).
Serious adverse reactions occurred in 30% of patients who received WELIREG in combination with pembrolizumab. Serious adverse reactions in ≥1% of patients included pneumonia (2%), hypoxia (1.9%), pneumonitis (1.6%), arrhythmia (1.5%), diarrhea (1.1%), and acute kidney injury (1.1%). Fatal adverse reactions occurred in 1.1% of patients who received WELIREG in combination with pembrolizumab, including sepsis (0.1%).
Permanent discontinuation of WELIREG due to adverse reactions occurred in 27% of patients. Adverse reactions which resulted in permanent discontinuation of WELIREG in ≥1% of patients included anemia (4%), fatigue (2.2%), rash (2%), increased ALT (1.7%), hypoxia (1.6%), diarrhea (1.4%), pneumonitis (1.3%), increased AST (1.1%), and hepatic function abnormal (1%).
Dosage interruptions of WELIREG due to an adverse reaction occurred in 52% of patients. Adverse reactions which required dosage interruption of WELIREG in ≥2% of patients included anemia (25%), fatigue (3.7%), increased ALT (3.5%), diarrhea (3.4%), increased AST (3.4%), COVID-19 (2.6%), hypoxia (2.5%), pyrexia (2.5%), musculoskeletal pain (2.1%), and rash (2.1%).
Dose reductions of WELIREG due to an adverse reaction occurred in 34% of patients. Adverse reactions which required dose reduction in ≥3% of patients included anemia (17%), hypoxia (3.5%), increased ALT (3.2%), and fatigue (3.1%).
The most common (≥25%) adverse reactions, including laboratory abnormalities, in patients who received WELIREG in combination with pembrolizumab were decreased hemoglobin, increased ALT, fatigue, increased AST, decreased lymphocytes, and increased alkaline phosphatase.
Tables 6 and 7 summarize the adverse reactions and laboratory abnormalities, respectively, in LITESPARK-022.
Table 6: Adverse Reactions (≥10%) in Patients with ccRCC Who Received WELIREG in Combination with Pembrolizumab [at a Higher Incidence (Between Arm Difference of ≥4%) Compared to Control] in LITESPARK-022
| Adverse Reaction | WELIREG plus Pembrolizumab (n=915) | Placebo plus Pembrolizumab (n=913) | ||
|---|---|---|---|---|
All GradesGraded per NCI CTCAE v5.0 (%) | Grade 3-4 (%) | All Grades (%) | Grade 3-4 (%) | |
| General | ||||
| FatigueIncludes other related terms | 49 | 3.1 | 33 | 0.7 |
| Gastrointestinal | ||||
| Diarrhea | 23 | 3 | 18 | 2.4 |
| Nausea | 16 | 0.3 | 12 | 0.2 |
| Nervous system | ||||
| Dizziness | 23 | 0.4 | 10 | 0.1 |
| Headache | 17 | 0.7 | 11 | 0.1 |
| Respiratory, thoracic, and mediastinal | ||||
| Dyspnea | 12 | 0.9 | 6 | 0.1 |
Clinically relevant adverse reactions in <10% of patients who received WELIREG in combination with pembrolizumab included hypertension (7%), hypoxia (7%), visual impairment (6.1%), arrhythmia (5%), hemorrhage (4.6%), chest discomfort (2.6%), and palpitations (1.9%).
Table 7: Select Laboratory Abnormalities (≥20%) That Worsened from Baseline In Patients with ccRCC Who Received WELIREG in Combination With Pembrolizumab [at a Higher Incidence (Between Arm Difference of ≥10%) Compared to Control] in LITESPARK-022
| Laboratory TestEach test incidence is based on the number of patients who had both baseline and at least one on-study laboratory measurement available: WELIREG + pembrolizumab (range: 907 to 911 patients), and placebo + pembrolizumab (range: 905 to 912 patients). | WELIREG plus Pembrolizumab | Placebo plus Pembrolizumab | ||
|---|---|---|---|---|
All GradesGraded per NCI CTCAE v5.0 % | Grades 3-4 % | All Grades % | Grades 3-4 % | |
| Hematology | ||||
| Decreased hemoglobin | 95 | 11 | 26 | 0.7 |
| Decreased lymphocytes | 38 | 9 | 25 | 7 |
| Chemistry | ||||
| Increased ALT | 57 | 13 | 33 | 3.2 |
| Increased AST | 46 | 8 | 29 | 3.1 |
| Increased alkaline phosphatase | 29 | 2.3 | 18 | 0.4 |
LITESPARK-011
The safety of WELIREG in combination with lenvatinib was evaluated in patients with advanced ccRCC that progressed on or after receiving a PD-1 or PD-L1 inhibitor in LITESPARK-011 [see Clinical Studies (14.2)]. Patients received WELIREG 120 mg in combination with lenvatinib 20 mg (n=370), or cabozantinib 60 mg (n=371) orally once daily until disease progression or unacceptable toxicity.
The median duration of exposure to WELIREG was 15.8 months (range: 1 day to 50.6 months).
Serious adverse reactions occurred in 54% of patients who received WELIREG in combination with lenvatinib. Serious adverse reactions in ≥2% of patients included hypoxia (6%), pneumonia (5%), hyponatremia (3.2%), acute kidney injury (3%), hemorrhage (2.7%), anemia (2.7%), cardiac failure (2.4%), and diarrhea (2.4%).
Fatal adverse reactions occurred in 5% of patients who received WELIREG in combination with lenvatinib, including sepsis (0.8%), pneumonia (0.5%), pneumonitis (0.5%), respiratory failure (0.5%), and one case (0.3%) each of acute cholecystitis, acute respiratory distress syndrome, pulmonary edema, embolic cerebral infarction, hemorrhage, postoperative wound complication, thrombotic microangiopathy and upper respiratory tract infection.
Permanent discontinuation of WELIREG due to an adverse reaction occurred in 17% of patients. Adverse reactions which resulted in permanent discontinuation of WELIREG in >0.5% of patients included hypoxia (2.2%), pneumonia (1.1%), fatigue (0.8%), hyponatremia (0.8%), pneumonitis (0.8%), and respiratory failure (0.8%).
Dosage interruptions of WELIREG due to an adverse reaction occurred in 69% of patients. Adverse reactions which required dosage interruption in >3% of patients included fatigue (14%), diarrhea (12%), anemia (9%), vomiting (9%), hypertension (9%), nausea (8%), decreased appetite (5%), abdominal pain (4.6%), COVID-19 (4.6%), musculoskeletal pain (4.1%), pneumonia (3.5%), hypoxia (3.5%), and hemorrhage (3.5%).
Dose reductions of WELIREG due to an adverse reaction occurred in 35% of patients. Adverse reactions which required dose reductions in >2% of patients included fatigue (7%), hypoxia (7%), anemia (6%), diarrhea (3%), and dyspnea (2.4%).
The most common (≥25%) adverse reactions, including laboratory abnormalities, that occurred in patients who received WELIREG in combination with lenvatinib were decreased hemoglobin, fatigue, increased AST, hypertension, increased ALT, musculoskeletal pain, diarrhea, decreased lymphocytes, decreased sodium, increased creatinine, nausea, hypothyroidism, decreased appetite, decreased platelets, increased potassium, increased lipase, proteinuria, decreased magnesium, decreased calcium, increased activated partial thromboplastin time, rash, vomiting, decreased weight, constipation, abdominal pain, and stomatitis.
Tables 8 and 9 summarize the adverse reactions and laboratory abnormalities, respectively, in LITESPARK-011.
Table 8: Adverse Reactions (≥15%) in Patients with Advanced ccRCC Who Received WELIREG in Combination with Lenvatinib in LITESPARK-011
| Adverse Reaction | WELIREG plus Lenvatinib (n=370) | Cabozantinib (n=371) | ||
|---|---|---|---|---|
All GradesGraded per NCI CTCAE v5.0 (%) | Grade 3-4 (%) | All Grades (%) | Grade 3-4 (%) | |
| General | ||||
| FatigueIncludes other related terms | 68 | 16 | 60 | 9 |
| Edema | 17 | 0.3 | 10 | 0.3 |
| Vascular | ||||
| Hypertension | 60 | 33 | 58 | 30 |
| Hemorrhage | 20 | 3 | 16 | 3 |
| Musculoskeletal and connective tissue | ||||
| Musculoskeletal pain | 55 | 5 | 43 | 4 |
| Gastrointestinal | ||||
| Diarrhea | 54 | 8 | 71 | 11 |
| Nausea | 42 | 3.8 | 39 | 1.1 |
| Vomiting | 32 | 0.8 | 17 | 1.1 |
| Constipation | 27 | 0.8 | 23 | 0 |
| Abdominal pain | 26 | 1.6 | 27 | 1.9 |
| Stomatitis | 25 | 1.9 | 46 | 5 |
| Endocrine | ||||
| Hypothyroidism | 42 | 0.3 | 37 | 0 |
| Metabolism and nutrition | ||||
| Decreased appetite | 41 | 2.7 | 40 | 3.5 |
| Renal and urinary | ||||
| Proteinuria | 38 | 10 | 20 | 3.5 |
| Skin and subcutaneous tissue | ||||
| Rash | 33 | 2.7 | 61 | 10 |
| Investigations | ||||
| Weight decreased | 29 | 5 | 30 | 6 |
| Nervous system | ||||
| Headache | 24 | 0.5 | 13 | 0 |
| Dizziness | 16 | 0.8 | 11 | 0.3 |
| Respiratory, Thoracic and Mediastinal | ||||
| Cough | 19 | 0 | 18 | 0.5 |
| Dyspnea | 17 | 1.9 | 11 | 1.1 |
| Hypoxia | 16 | 12 | 0 | 0 |
Clinically relevant adverse reactions occurring in <15% of patients who received WELIREG in combination with lenvatinib included COVID-19 (14%), dysphonia (14%), dysgeusia (14%), urinary tract infection (14%), pruritus (12%), pyrexia (11%), and arrhythmia (9%).
Table 9: Select Laboratory Abnormalities (≥20%) That Worsened from Baseline In Patients with Advanced ccRCC Who Received WELIREG in Combination with Lenvatinib in LITESPARK-011
| Laboratory TestEach test incidence is based on the number of patients who had both baseline and at least one on-study laboratory measurement available: WELIREG + lenvatinib (range: 319 to 368 patients), and cabozantinib (range: 320 to 371 patients). | WELIREG plus Lenvatinib | Cabozantinib | ||
|---|---|---|---|---|
All GradesGraded per NCI CTCAE v5.0 % | Grades 3-4 % | All Grades % | Grades 3-4 % | |
| Hematology | ||||
| Decreased hemoglobin | 87 | 17 | 50 | 7 |
| Decreased lymphocytes | 53 | 15 | 45 | 18 |
| Decreased platelets | 40 | 1.9 | 43 | 0.3 |
| Increased activated partial thromboplastin time | 34 | 2.5 | 27 | 2.5 |
| Decreased neutrophils | 21 | 4.9 | 29 | 3.8 |
| Chemistry | ||||
| Increased AST | 65 | 7 | 84 | 6 |
| Increased ALT | 56 | 7 | 77 | 7 |
| Decreased sodium | 47 | 7 | 49 | 4.6 |
| Increased creatinine | 42 | 3.8 | 36 | 2.4 |
| Increased potassium | 39 | 5 | 38 | 6 |
| Increased lipase | 38 | 15 | 50 | 17 |
| Decreased magnesium | 37 | 1.4 | 51 | 4.7 |
| Decreased calcium | 35 | 2.4 | 62 | 3.5 |
| Decreased potassium | 23 | 3.5 | 26 | 5 |
| Increased calcium | 20 | 0.3 | 11 | 0.5 |
LITESPARK-005
The safety of WELIREG was evaluated in a randomized, active-controlled study (LITESPARK- 005) in 732 patients with advanced ccRCC that has progressed after prior PD-1 or PD-L1 checkpoint inhibitor and VEGF receptor targeted therapies [see Clinical Studies (14.2)]. Patients received 120 mg WELIREG (n=372) or 10 mg everolimus (n=360) orally once daily until disease progression or unacceptable toxicity. The median duration of exposure to WELIREG was 7.6 months (range: 0.1 to 28.5 months).
Serious adverse reactions occurred in 38% of patients who received WELIREG. Serious adverse reactions in ≥2% of patients treated with WELIREG were hypoxia (7%), anemia (5%), pneumonia (3.5%), hemorrhage (3%), and pleural effusion (2.2%). Fatal adverse reactions occurred in 3.2% of patients who received WELIREG, including sepsis (0.5%) and hemorrhage (0.5%).
Permanent discontinuation of WELIREG due to adverse reactions occurred in 6% of patients. Adverse reactions which resulted in permanent discontinuation (≥0.5%) of WELIREG were hypoxia (1.1%), anemia (0.5%), and hemorrhage (0.5%).
Dosage interruptions of WELIREG due to an adverse reaction occurred in 39% of patients. Adverse reactions which required dosage interruption in ≥2% of patients were anemia (8%), hypoxia (5%), COVID-19 (4.3%), fatigue (3.2%), and hemorrhage (2.2%).
Dose reductions of WELIREG due to an adverse reaction occurred in 13% of patients. Adverse reactions which required dose reduction in ≥1% of patients were hypoxia (5%) and anemia (3.2%).
The most common (≥25%) adverse reactions, including laboratory abnormalities, that occurred in patients who received WELIREG were decreased hemoglobin, fatigue, musculoskeletal pain, increased creatinine, decreased lymphocytes, increased alanine aminotransferase, decreased sodium, increased potassium, and increased aspartate aminotransferase.
Table 10 summarizes the adverse reactions in LITESPARK-005.
Table 10: Adverse Reactions (≥10%) in Patients with Advanced RCC Receiving WELIREG in LITESPARK-005
| Adverse Reaction | WELIREG (n=372) | Everolimus (n=360) | ||
|---|---|---|---|---|
All GradesGraded per NCI CTCAE v5.0 (%) | Grade 3-4 (%) | All Grades (%) | Grade 3-4 (%) | |
| General | ||||
| FatigueIncludes other related terms | 43 | 3.2 | 41 | 6 |
| Edema | 20 | 0.5 | 23 | 0.6 |
| Musculoskeletal and Connective Tissue | ||||
| Musculoskeletal Pain | 34 | 1.1 | 27 | 2.2 |
| Gastrointestinal | ||||
| Nausea | 17 | 0.5 | 11 | 0.3 |
| Constipation | 15 | 0 | 8 | 0 |
| Vomiting | 11 | 0.8 | 8 | 0.8 |
| Diarrhea | 11 | 1.3 | 19 | 1.4 |
| Abdominal Pain | 10 | 0.8 | 8 | 0.3 |
| Respiratory, Thoracic, and Mediastinal | ||||
| Dyspnea | 16 | 1.6 | 16 | 2.5 |
| Hypoxia | 15 | 10 | 1.4 | 1.4 |
| Metabolism and Nutrition | ||||
| Decreased Appetite | 13 | 1.1 | 16 | 0 |
| Nervous System | ||||
| Headache | 12 | 0.5 | 8 | 0.3 |
| Dizziness | 11 | 0 | 1.9 | 0 |
Clinically relevant adverse reactions in <10% of patients who received WELIREG in LITESPARK-005 included hemorrhage (9%) [including intracranial/cerebral hemorrhage (0.8%)], rash (8%), hypertension (6%), visual impairment [including vision blurred (4%), visual acuity decreased (1.1%), visual impairment (0.5%), and retinal detachment (0.3%)] (6%) and increased weight (5%).
Table 11 summarizes the laboratory abnormalities in LITESPARK-005.
Table 11: Select Laboratory Abnormalities (≥20%) That Worsened from Baseline In Patients with Advanced RCC who Received WELIREG in LITESPARK-005
| Laboratory TestEach test incidence is based on the number of patients who had both baseline and at least one on-study laboratory measurement available WELIREG (range: 359 to 366 patients), and everolimus (range: 351 to 356 patients). | WELIREG | Everolimus | ||
|---|---|---|---|---|
All GradesGraded per NCI CTCAE v5.0 % | Grades 3-4 % | All Grades % | Grades 3-4 % | |
| Hematology | ||||
| Decreased hemoglobin | 88 | 29 | 76 | 17 |
| Decreased lymphocytes | 34 | 8 | 53 | 20 |
| Chemistry | ||||
| Increased creatinine | 34 | 4.7 | 43 | 5.1 |
| Increased alanine aminotransferase | 32 | 2.2 | 40 | 1.1 |
| Decreased sodium | 31 | 1.6 | 36 | 0.8 |
| Increased potassium | 29 | 2.5 | 20 | 2.8 |
| Increased aspartate aminotransferase | 27 | 2.2 | 38 | 2 |
| Decreased glucose | 22 | 1.1 | 19 | 1.1 |
| Decreased calcium | 21 | 1.1 | 45 | 3.1 |
Pheochromocytoma or Paraganglioma
LITESPARK-015
The safety of WELIREG was evaluated in an open-label clinical trial (LITESPARK-015) in 72 patients with locally advanced, unresectable, or metastatic pheochromocytoma or paraganglioma (PPGL) [see Clinical Studies (14.3)]. Patients received WELIREG 120 mg orally once daily until disease progression or unacceptable toxicity.
The median duration of exposure to WELIREG was 20 months (range: 0.3 to 32.5 months).
Serious adverse reactions occurred in 36% of patients who received WELIREG. Serious adverse reactions occurring in ≥2% of patients treated with WELIREG were anemia and hypertension (4.2% each) and pyelonephritis, pneumonia, hypoxia, dyspnea and hemorrhage (2.8% each).
Permanent discontinuation of WELIREG due to adverse reactions occurred in 2 patients (2.8%). Adverse reactions which resulted in permanent discontinuation of WELIREG were increased alanine aminotransferase and paraparesis (1.4% each).
Dosage interruptions of WELIREG due to an adverse reaction occurred in 40% of patients. Adverse reactions which required dosage interruption in >3% of patients were hypoxia, nausea and fatigue (4.2% each).
Dose reductions of WELIREG due to an adverse reaction occurred in 14% of patients. The most frequently reported adverse reaction which required dose reduction was hypoxia (4.2%).
The most common (≥25%) adverse reactions, including laboratory abnormalities, that occurred in patients who received WELIREG were anemia, fatigue, musculoskeletal pain, decreased lymphocytes, increased alanine aminotransferase, increased aspartate aminotransferase, increased calcium, dyspnea, increased potassium, decreased leukocytes, headache, increased alkaline phosphatase, dizziness, and nausea.
Table 12 summarizes the adverse reactions reported in patients treated with WELIREG in LITESPARK-015.
Table 12: Adverse Reactions Occurring in ≥10% of Patients with PPGL Who Received WELIREG in LITESPARK-015
| Adverse Reaction | WELIREG (n=72) | |
|---|---|---|
All GradesGraded per NCI CTCAE v5.0 (%) | Grade 3-4 (%) | |
| Blood and Lymphatic | ||
| Anemia | 96 | 22 |
| General | ||
| FatigueIncludes other related terms | 56 | 10 |
| Edema | 24 | 0 |
| Musculoskeletal and Connective Tissue | ||
| Musculoskeletal pain | 56 | 6 |
| Muscle spasms | 13 | 0 |
| Muscle weakness | 13 | 2.8 |
| Respiratory, Thoracic, and Mediastinal | ||
| Dyspnea | 33 | 1.4 |
| Cough | 15 | 0 |
| Hypoxia | 13 | 10 |
| Nasal congestion | 10 | 0 |
| Nervous System | ||
| Headache | 29 | 1.4 |
| Dizziness | 26 | 2.8 |
| Peripheral neuropathy | 13 | 0 |
| Gastrointestinal | ||
| Nausea | 25 | 1.4 |
| Constipation | 24 | 1.4 |
| Diarrhea | 15 | 0 |
| Abdominal Pain | 13 | 1.4 |
| Vomiting | 10 | 1.4 |
| Vascular Disorders | ||
| Hypertension | 21 | 13 |
| Hypotension | 10 | 2.8 |
| Hemorrhage | 10 | 2.8 |
| Infections | ||
| COVID-19 | 17 | 2.8 |
| Metabolism and Nutrition Disorders | ||
| Decreased appetite | 14 | 2.8 |
| Investigations | ||
| Weight increased | 13 | 7 |
| Cardiac Disorders | ||
| Arrhythmia | 11 | 2.8 |
| Palpitations | 10 | 0 |
Table 13 summarizes the laboratory abnormalities in LITESPARK-015.
Table 13: Select Laboratory Abnormalities (≥20%) That Worsened from Baseline in Patients with PPGL Who Received WELIREG in LITESPARK-015
| Laboratory Abnormality | WELIREG (n=72) | |
|---|---|---|
All Grades % | Grades 3 or 4 % | |
| Hematology | ||
| Decreased hemoglobin | 90 | 21 |
| Decreased lymphocytes | 54 | 14 |
| Decreased leukocytes | 30 | 0 |
| Decreased neutrophils | 24 | 1.4 |
| Decreased platelets | 21 | 1.4 |
| Chemistry | ||
| Increased ALT | 51 | 4.2 |
| Increased AST | 42 | 4.2 |
| Increased calcium | 34 | 0 |
| Increased potassium | 31 | 2.8 |
| Increased alkaline phosphatase | 25 | 0 |
| Increased creatinine | 24 | 1.4 |
| Decreased sodium | 21 | 0 |
7 DRUG INTERACTIONS
7.1 Effects of Other Drugs on WELIREG
UGT2B17 or CYP2C19 Inhibitors
Monitor for anemia and hypoxia and reduce the dosage of WELIREG as recommended [see Dosage and Administration (2.2), Warnings and Precautions (5.1, 5.2), Adverse Reactions (6)].
Coadministration of WELIREG with inhibitors of UGT2B17 or CYP2C19 increases belzutifan exposure [see Clinical Pharmacology (12.3, 12.5)], which may increase the risk of adverse reactions of WELIREG.
7.2 Effect of WELIREG on Other Drugs
CYP3A4 Substrates
Avoid coadministration of WELIREG with sensitive CYP3A4 substrates, for which minimal decrease in concentration may lead to therapeutic failures of the substrate. If coadministration cannot be avoided, increase the sensitive CYP3A4 substrate dosage in accordance with its Prescribing Information.
Coadministration of WELIREG with CYP3A4 substrates decreases concentrations of CYP3A substrates [see Clinical Pharmacology (12.3)], which may reduce the efficacy of these substrates. The magnitude of this decrease may be more pronounced in patients who are dual UGT2B17 and CYP2C19 poor metabolizers [see Clinical Pharmacology (12.3)].
Hormonal Contraceptives
Coadministration of WELIREG with hormonal contraceptives may lead to contraceptive failure or an increase in breakthrough bleeding [see Clinical Pharmacology (12.3), Use in Specific Populations (8.3)].
8 USE IN SPECIFIC POPULATIONS
8.1 Pregnancy
Risk Summary
Refer to the Prescribing Information of the individual therapeutic agents used in combination with WELIREG for pregnancy information.
Based on findings in animal studies, WELIREG can cause fetal harm when administered to a pregnant woman. There are no available data on the use of WELIREG in pregnant women to inform the drug-associated risk. In an animal reproduction study, oral administration of belzutifan to pregnant rats during the period of organogenesis caused embryo-fetal lethality, reduced fetal body weight, and fetal skeletal malformations at maternal exposures ≥0.2 times the human exposure (AUC) at the recommended dose of 120 mg daily (see Data ). Advise pregnant women and females of reproductive potential of the potential risk to a fetus.
The background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2–4% and 15–20%, respectively.
Data
Animal Data
In a pilot embryo-fetal development study, pregnant rats received oral doses of 6, 60, or 200 mg/kg/day of belzutifan during the period of organogenesis. Belzutifan caused embryo-fetal lethality at doses ≥60 mg/kg/day (approximately 1 time the human exposure at the recommended dose based on AUC). Reduced fetal body weights, fetal rib malformations, and reduced skeletal ossification occurred at doses of 6 and 60 mg/kg/day (approximately ≥0.2 times the human exposure at the recommended dose based on AUC).
8.2 Lactation
Risk Summary
Refer to the Prescribing Information of the individual therapeutic agents used in combination with WELIREG for lactation information. When used in combination, advise patients not to breastfeed during treatment and for the longest post-treatment duration recommended in the Prescribing Information of the individual products.
There are no data on the presence of belzutifan or its metabolites in human milk or their effects on the breastfed child or on milk production. Because of the potential for serious adverse reactions in a breastfed child, advise women not to breastfeed during treatment with WELIREG and for 1 week after the last dose.
8.3 Females and Males of Reproductive Potential
Refer to the Prescribing Information of the individual therapeutic agents used in combination with WELIREG for contraception and infertility information. When used in combination, advise patients to use effective contraception during treatment and for the longest post-treatment duration recommended in the Prescribing Information of the individual products.
WELIREG can cause fetal harm when administered to a pregnant woman [see Use in Specific Populations (8.1)].
Pregnancy Testing
Verify the pregnancy status of females of reproductive potential prior to initiating treatment with WELIREG.
Contraception
Females
Advise females of reproductive potential to use effective non-hormonal contraception during treatment with WELIREG and for 1 week after the last dose. WELIREG can render some hormonal contraceptives ineffective [see Drug Interactions (7.2)].
Males
Advise males with female partners of reproductive potential to use effective contraception during treatment with WELIREG and for 1 week after the last dose.
Infertility
Based on findings in animals, WELIREG may impair fertility in males and females of reproductive potential [see Nonclinical Toxicology (13.1) ]. The reversibility of the effect on fertility is unknown.
8.4 Pediatric Use
The safety and effectiveness of WELIREG have been established in pediatric patients aged 12 years and older for the treatment of locally advanced, unresectable, or metastatic pheochromocytoma or paraganglioma. Use of WELIREG in pediatric patients aged 12 years and older is supported by evidence from an adequate and well-controlled study of WELIREG in adults with additional pharmacokinetic data demonstrating that belzutifan exposure is predicted to be within range of that observed in adults, and that the course of locally advanced, unresectable, or metastatic pheochromocytoma or paraganglioma is sufficiently similar in adults and pediatric patients to allow extrapolation of data in adults to pediatric patients [see Clinical Pharmacology (12.3) and Clinical Studies (14.3)].
The safety and effectiveness of WELIREG have not been established in pediatric patients with VHL or ccRCC, or in pediatric patients younger than 12 years of age with PPGL.
8.5 Geriatric Use
Of the 61 patients who received WELIREG for VHL in LITESPARK-004, 3.3% were ≥65 years old [see Clinical Studies (14.1)]. Clinical trials of WELIREG in patients with VHL did not include sufficient numbers of patients aged 65 and older to determine whether they respond differently from younger patients.
Of the 915 patients who received WELIREG in combination with pembrolizumab for ccRCC in LITESPARK-022, 30% were ≥65 years old and 5% were ≥75 years old [see Clinical Studies (14.2)]. No overall differences in efficacy or safety were reported between patients who were ≥65 years of age and younger patients. Dose interruptions of WELIREG occurred in 57% of patients ≥65 years of age and in 49% of younger patients. Dose reductions of WELIREG occurred in 39% of patients ≥65 years of age and in 32% of younger patients.
Of the 370 patients who received WELIREG in combination with lenvatinib for advanced ccRCC in LITESPARK-011, 44% of patients were ≥65 years old and 10% were ≥75 years old [see Clinical Studies (14.2)]. Permanent discontinuation, dosage interruption, and dose reductions of WELIREG in patients ≥65 years of old were 23%, 73%, and 42%, respectively, compared with 12%, 65%, and 29%, respectively, in younger patients. No overall differences in effectiveness were reported between patients who were ≥65 years of age and younger patients.
Of the 372 patients who received WELIREG for advanced ccRCC in LITESPARK-005, 62% of patients were younger than 65 years, 28% of patients were 65 to 74 years, and 10% were 75 years and over [see Clinical Studies (14.2)]. No overall difference in efficacy was reported between patients who were ≥65 years of age and younger patients. Dose interruptions occurred in 48% of patients ≥65 years of age and in 34% of younger patients. Dose reductions occurred in 18% of patients ≥65 years of age and in 10% of younger patients.
Of the 72 patients who received WELIREG for PPGL in LITESPARK-015, 13% were ≥65 years old and 4.2% were ≥75 years old [see Clinical Studies (14.3)]. Clinical trials of WELIREG in patients with PPGL did not include sufficient numbers of patients aged 65 and older to determine whether they respond differently from younger patients. Other reported clinical experience has not identified differences in responses between the elderly and younger patients.
8.6 Renal Impairment
No dosage modification of WELIREG is recommended in patients with renal impairment including end-stage renal disease. For patients with severe renal impairment (eGFR 15-29 mL/min estimated by MDRD) monitor for increased adverse reactions and modify the dosage as recommended [see Dosage and Administration (2.2), Clinical Pharmacology (12.3)].
8.7 Hepatic Impairment
No dosage modification of WELIREG is recommended in patients with mild [total bilirubin ≤ upper limit of normal (ULN) and aspartate aminotransferase (AST) > ULN or total bilirubin >1 to 1.5 x ULN and any AST] or moderate (total bilirubin within range of >1.5 x ULN and ≤ 3 x ULN and any AST or Child-Pugh B) hepatic impairment. WELIREG has not been studied in patients with severe hepatic impairment (total bilirubin >3 x ULN and any AST). For patients with moderate and severe hepatic impairment, monitor for increased adverse reactions and modify the dosage as recommended [see Dosage and Administration (2.2), Clinical Pharmacology (12.3)].
8.8 Dual UGT2B17 and CYP2C19 Poor Metabolizers
Patients who are dual UGT2B17 and CYP2C19 poor metabolizers have higher belzutifan exposures, which may increase the risk of adverse reactions of WELIREG. Monitor for increased adverse reactions in patients who are dual UGT2B17 and CYP2C19 poor metabolizers [see Warnings and Precautions (5), Adverse Reactions (6), Clinical Pharmacology (12.5)].
10 OVERDOSAGE
There is no specific treatment for WELIREG overdose. In cases of suspected overdose, withhold WELIREG and institute supportive care. Grade 3 hypoxia occurred at dosages of 120 mg twice a day and Grade 4 thrombocytopenia occurred at dosages of 240 mg once daily (approximately 2 times the recommended dosage).
11 DESCRIPTION
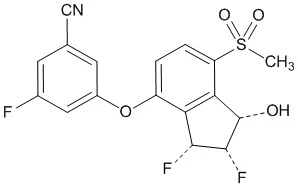
Belzutifan is an inhibitor of hypoxia-inducible factor-2α (HIF-2α). The chemical name of belzutifan is 3-[[(1S,2S,3R)-2,3-Difluoro-2,3-dihydro-1-hydroxy-7-(methylsulfonyl)-1H-inden-4-yl]oxy]-5-fluorobenzonitrile. The molecular formula is C17H12F3NO4S and the molecular weight is 383.34 Daltons. The chemical structure is:
 |
Belzutifan is a white to light brown powder that is soluble in acetonitrile, dimethoxyethane, and acetone, sparingly soluble in ethyl acetate, very slightly soluble in isopropanol and toluene, and insoluble in water.
WELIREG is supplied as blue, film-coated tablets for oral use containing 40 mg of belzutifan together with croscarmellose sodium, hypromellose acetate succinate, magnesium stearate, mannitol, microcrystalline cellulose, and silicon dioxide, as inactive ingredients. In addition, the film-coating contains FD&C Blue #2 aluminum lake, polyethylene glycol, polyvinyl alcohol, talc, titanium dioxide.
12 CLINICAL PHARMACOLOGY
12.1 Mechanism of Action
Belzutifan is an inhibitor of hypoxia-inducible factor 2 alpha (HIF-2α). HIF-2α is a transcription factor that plays a role in oxygen sensing by regulating genes that promote adaptation to hypoxia. Under normal oxygen levels, HIF-2α is targeted for ubiquitin-proteasomal degradation by VHL protein. Lack of functional VHL protein results in stabilization and accumulation of HIF-2α. Upon stabilization, HIF-2α translocates into the nucleus and interacts with hypoxia-inducible factor 1 beta (HIF-1β) to form a transcriptional complex that induces expression of downstream genes, including genes associated with cellular proliferation, angiogenesis, and tumor growth. Belzutifan binds to HIF-2α, and in conditions of hypoxia or impairment of VHL protein function, belzutifan blocks the HIF-2α-HIF-1β interaction, leading to reduced transcription and expression of HIF-2α target genes. In vivo, belzutifan demonstrated anti-tumor activity in mouse xenograft models of renal cell carcinoma.
12.2 Pharmacodynamics
Reductions in plasma levels of erythropoietin (EPO) were observed to be dose- and exposure-dependent at dosages up to 120 mg once daily. The maximum EPO suppression occurred following 2 weeks of consecutive dosing of WELIREG (mean percent decrease from baseline of approximately 60%). Mean EPO levels gradually returned to baseline values after 12 weeks of treatment.
The incidence of Grade 3 anemia increased with higher belzutifan exposure in patients with baseline hemoglobin levels <12 g/dL [see Warnings and Precautions (5.1)].
Cardiac Electrophysiology
At the recommended dosage, WELIREG does not cause large mean increases (i.e., >20 msec) in the QT interval.
12.3 Pharmacokinetics
The Cmax and AUC of belzutifan increase proportionally over a dose range of 20 mg to 120 mg (0.17 to 1 times the approved recommended dose). The estimated geometric mean steady-state (CV%) Cmax is 1.5 μg/mL (45%) and AUC0-24h is 20 μg•hr/mL (62%). Steady state is reached after approximately 3 days.
Absorption
The median Tmax occurs at 1 to 2 hours after WELIREG administration.
Effect of Food
A high-fat, high-calorie meal (total calories approximately 1000 kcal, 56 g fat, 55 g carbohydrate, and 31 g protein) delayed Tmax by approximately 2 hours with no clinically significant effect on Cmax and AUC of belzutifan.
Distribution
The estimated mean (CV%) volume of distribution is 119 L (28%). Plasma protein binding of belzutifan is 45%. The blood-to-plasma concentration ratio of belzutifan is 0.88.
Elimination
The estimated mean (CV%) clearance is 6 L/hr (58%) and the mean elimination half-life is 14 hrs.
Metabolism
Belzutifan is primarily metabolized by UGT2B17 and CYP2C19 and to a lesser extent by CYP3A4 [see Clinical Pharmacology (12.5)].
Excretion
Following a single oral dose of radiolabeled belzutifan, approximately 49.6% of the dose was excreted in urine and 51.7% in feces (primarily as inactive metabolites).
Specific Populations
Patients who are poor metabolizers of UGT2B17 and CYP2C19 had higher belzutifan AUC [see Clinical Pharmacology (12.5)].
No clinically significant differences in the pharmacokinetics of belzutifan were observed based on age (15 to 90 years), sex, ethnicity (non-Hispanic, Hispanic), race (White (76%), Black (5%), Asian (15%), Native American, Pacific Islander), or body weight (40 to 166 kg).
Pediatric patients
The exposure of belzutifan in pediatric patients 12 years and older is predicted to be within range of that observed in adults at the recommended dosage.
Patients with Renal Impairment
No clinically significant differences in the mean belzutifan exposure were observed between subjects with normal renal function and those with mild (eGFR 60-89 mL/min) or moderate renal impairment (eGFR 30-59 mL/min) and those with end-stage renal disease (eGFR <15 mL/min) requiring dialysis.
Patients with Hepatic Impairment
No clinically significant differences in the mean belzutifan exposure were observed between subjects with normal liver function (total bilirubin and AST ≤ ULN), and those with mild hepatic impairment (total bilirubin ≤ ULN and AST > ULN or total bilirubin >1 to 1.5 x ULN and any AST). Belzutifan exposure (AUC) increased by 1.5-fold in patients with moderate hepatic impairment (Child-Pugh B) compared to subjects with normal hepatic function. Patients with severe hepatic impairment have not been studied.
Drug Interaction Studies
Clinical Studies and Model-Informed Approaches
Effect of Belzutifan on CYP3A Substrates: Coadministration of WELIREG 120 mg once daily with midazolam (a sensitive CYP3A4 substrate) decreased the midazolam AUC by 40% and the Cmax by 34%. Midazolam AUC is predicted to decrease up to 70% in patients with higher belzutifan concentrations (e.g., dual poor metabolizers) [see Clinical Pharmacology (12.5)].
In Vitro Studies
Cytochrome P450 (CYP) Enzymes: Belzutifan does not inhibit CYP1A2, CYP2B6, CYP2C8, CYP2C9, CYP2C19, CYP2D6, or CYP3A4.
Belzutifan does not induce CYP1A2 or CYP2B6.
Transporter Systems: Belzutifan is a substrate of P-gp, OATP1B1, and OATP1B3, but is not a substrate of BCRP.
Belzutifan inhibits MATE2K. Belzutifan does not inhibit P-gp, BCRP, OATP1B1, OATP1B3, OAT1, OAT3, OCT2, or MATE1.
12.5 Pharmacogenomics
Patients who are UGT2B17, CYP2C19, or dual UGT2B17 and CYP2C19 poor metabolizers are estimated to have 2.5-, 1.3-, or 3.2-fold higher belzutifan steady state AUC0-24h, respectively compared to patients who are UGT2B17 normal (extensive) metabolizers and CYP2C19 non-poor (ultrarapid, rapid, normal, and intermediate) metabolizers [see Use in Specific Populations (8.8)].
UGT2B17 poor metabolizers who are homozygous for the UGT2B17*2 allele have no UGT2B17 enzyme activity. CYP2C19 poor metabolizers (such as *2/*2, *3/*3, *2/*3) have significantly reduced or absent CYP2C19 enzyme activity. Approximately 15% of White, 6% of Black or African American, and up to 77% of certain Asian populations are UGT2B17 poor metabolizers. Approximately 2% of White, 5% of Black or African American, and up to 19% of certain Asian populations are CYP2C19 poor metabolizers. Approximately 0.4% of White, 0.3% of Black or African American, and up to 15% of certain Asian populations are dual UGT2B17 and CYP2C19 poor metabolizers.
13 NONCLINICAL TOXICOLOGY
13.1 Carcinogenesis, Mutagenesis, Impairment of Fertility
Carcinogenesis
No carcinogenic risk was identified with belzutifan in a 6-month transgenic rasH2 mouse study with oral administration up to 600 mg/kg/day and a 2-year rat study with oral administration up to 300 mg/kg/day (up to 13 times the human exposure at the recommended dose based on AUC).
Mutagenesis
Belzutifan was not mutagenic in the in vitro bacterial reverse mutation (Ames) assay. Belzutifan was not clastogenic in either an in vitro micronucleus assay or an in vivo rat bone marrow micronucleus assay.
Impairment of Fertility
Fertility studies in animals have not been conducted with belzutifan. In repeat-dose toxicity studies up to 3-month duration, belzutifan-related findings included degeneration/atrophy of testes and hypospermia and cellular debris of the epididymis in rats administered ≥2 mg/kg/day (approximately 0.1 times the human exposure at the recommended dose of 120 mg daily). Findings in testes and epididymis were associated with decreased sperm count and motility and abnormal sperm morphology at ≥6 mg/kg/day (approximately 0.2 times the human exposure at the recommended dose of 120 mg daily) and did not reverse by the end of the recovery period. Belzutifan had no adverse effects on female reproductive organs in repeat-dose toxicity studies up to 3-month duration; however, belzutifan caused embryo-fetal lethality (post-implantation loss) in pregnant rats given oral doses ≥60 mg/kg/day (approximately 1 time the human exposure at the recommended dose based on AUC) during the period of organogenesis [see Use in Specific Populations (8.1)].
14 CLINICAL STUDIES
14.1 von Hippel-Lindau (VHL) disease
The efficacy of WELIREG was evaluated in LITESPARK-004 (NCT03401788), an open-label clinical trial in 61 patients with VHL-associated RCC diagnosed based on a VHL germline alteration and with at least one measurable solid tumor localized to the kidney as defined by response evaluation criteria in solid tumors (RECIST) v1.1. Enrolled patients had other VHL-associated tumors including CNS hemangioblastomas and pNET. CNS hemangioblastomas and pNET in these patients were diagnosed based on the presence of at least one measurable solid tumor in brain/spine or pancreas, respectively, as defined by RECIST v1.1 and identified by IRC. The study excluded patients with metastatic disease. Patients received WELIREG 120 mg orally once daily until disease progression or unacceptable toxicity.
The study population characteristics were: median age 41 years [range: 19-66 years], 3.3% age 65 or older; 53% male; 90% were White, 3.3% were Black or African-American, 1.6% were Asian, and 1.6% were Native Hawaiian or other Pacific Islander; 82% had an ECOG PS of 0, 16% had an ECOG PS of 1, and 1.6% had an ECOG PS of 2; and 84% had VHL Type I Disease. The median diameter of RCC target lesions per central independent review committee (IRC) was 2.2 cm (range: 1-6.1). Median time from initial radiographic diagnosis of VHL-associated RCC tumors that led to enrollment on LITESPARK-004 to the time of treatment with WELIREG was 17.9 months (range: 2.8-96.7). Seventy-seven percent of patients had prior surgical procedures for RCC.
The major efficacy endpoint for the treatment of VHL-associated RCC was objective response rate (ORR) measured by radiology assessment using Response Evaluation Criteria In Solid Tumors (RECIST) v1.1 as assessed by IRC. Additional efficacy endpoints included duration of response (DoR), and time to response (TTR).
Table 14 summarizes the efficacy results for VHL-associated RCC in LITESPARK-004.
Table 14: Efficacy Results (IRC assessment) for LITESPARK-004 for VHL-Associated RCC
| Efficacy Outcome Measure | WELIREG n=61 |
|---|---|
| + Denotes ongoing response. | |
Objective Response Rate, % (n) (95% CI) | 49% (30)All patients with a response were followed for a minimum of 18 months from the start of treatment. (36, 62) |
| Complete response | 0% |
| Partial response | 49% |
| Duration of Response | |
| Median in months (range) | Not reached (2.8+, 22+) |
| % (n) with DoR ≥ 12 months | 56% (17/30) |
For VHL-associated RCC, median TTR was 8 months (range: 2.7, 19).
Table 15 summarizes the efficacy results for VHL-associated pNET or CNS hemangioblastomas in LITESPARK-004.
Table 15: Efficacy Results (IRC assessment) for LITESPARK-004 for VHL-Associated Subgroups with CNS Hemangioblastomas or pNET
| Endpoint | Patients with CNS Hemangioblastomas n=24Number of patients with measurable solid lesions, based on IRC assessment. | Patients with pNET n=12 |
|---|---|---|
| + Denotes ongoing response. | ||
Objective Response Rate, % (n) (95% CI) | 63%, (15) (41, 81) | 83% (10) (52, 98) |
| Complete response | 4% (1) | 17% (2) |
| Partial response | 58% (14) | 67% (8) |
| Duration of Response | ||
| Median in months (range) | Not reached (3.7+, 22+) | Not reached (11+, 19+) |
| % (n) with DoR ≥12 months | 73% (11/15) | 50% (5/10) |
For VHL-associated CNS hemangioblastomas, TTR was 3.1 months (range: 2.5, 11). For VHL-associated pNET, median TTR was 8.1 months (range: 2.7, 11).
Decreases in size of CNS hemangioblastoma-associated peri-tumoral cysts and syringes were observed.
14.2 Renal Cell Carcinoma with a Clear Cell Component (ccRCC)
Adjuvant Treatment of ccRCC in Combination with Pembrolizumab
The efficacy of WELIREG in combination with intravenous pembrolizumab was investigated as adjuvant therapy versus placebo in combination with intravenous pembrolizumab for ccRCC in LITESPARK-022 (NCT05239728), a multicenter, double-blind, randomized trial in 1,841 patients with intermediate-high or high risk of recurrence of RCC, or M1 with no evidence of disease (NED). The intermediate-high risk category included: pT2, Grade 4 only; pT3, any Grade without nodal involvement (N0) or distant metastases (M0). The high risk category included: pT4, any Grade N0 and M0; any pT, any Grade with nodal involvement and M0. The M1 NED category included patients with metastatic disease who had undergone complete resection of primary and metastatic lesions. Patients were required to have undergone a partial or radical nephrectomy, and if indicated, metastasectomy within two years of nephrectomy, within ≥4 weeks prior to the time of screening. Patients were excluded from the trial if they had received prior systemic therapy for advanced RCC.
Patients were randomized (1:1) to receive WELIREG 120 mg orally once daily in combination with pembrolizumab 400 mg intravenously every 6 weeks (N=921), or oral placebo in combination with pembrolizumab 400 mg intravenously every 6 weeks (N=920) for up to 9 cycles (54 weeks) until disease recurrence or unacceptable toxicity. Randomization was stratified by risk of recurrence (intermediate-high, high risk, M1 NED) and tumor grade (1 or 2 versus 3 or 4).
The study population characteristics were: median age 60 years (range: 20 to 91 years), 32% age 65 or older; 71% male; 63% White; 29% Asian; 3.6% Unknown, 0.7% Black or African American; 1.7% American Indian or Alaska Native, 1.8% Multiracial; 78% Not Hispanic or Latino, 15% Hispanic or Latino, 7% Unknown; 85% ECOG PS 0 and 15% ECOG PS 1. Ninety-six percent of patients enrolled had N0 disease or unknown nodal status; 10% had sarcomatoid features; 85% had intermediate-high risk disease; 6% had high risk disease; and 9% had M1 NED. Ninety percent of patients had a radical nephrectomy, and 10% had a partial nephrectomy.
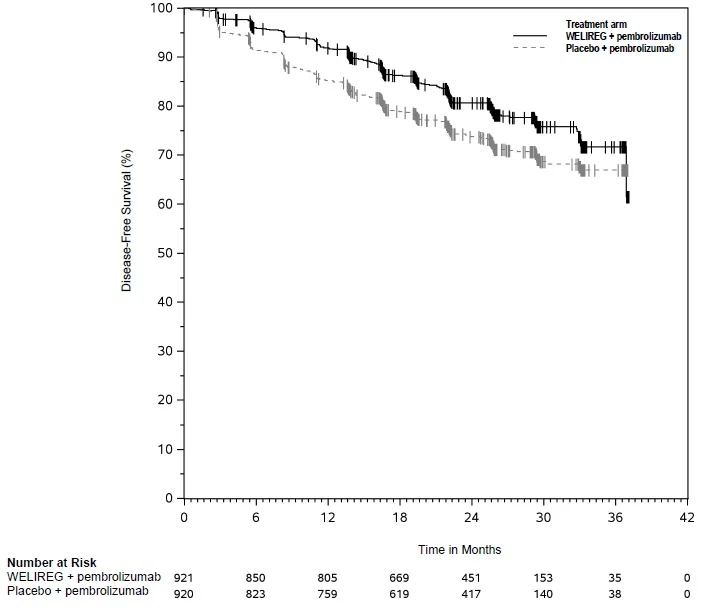
The major efficacy outcome measure was investigator-assessed disease-free survival (DFS), defined as time to recurrence, metastasis, or death. An additional outcome measure was overall survival (OS). A statistically significant improvement in DFS was demonstrated at pre-specified interim analysis in patients randomized to the WELIREG plus pembrolizumab arm compared with the placebo plus pembrolizumab arm. At the protocol pre-specified interim analysis, OS data were not mature with 29% of the required events for the final analysis.
Table 16 and Figure 1 summarize the efficacy results for LITESPARK-022.
Table 16: Efficacy Results for ccRCC for LITESPARK-022
| Efficacy Outcome Measure | WELIREG plus Pembrolizumab n=921 | Placebo plus Pembrolizumab n=920 |
|---|---|---|
| CI = confidence interval; NR = not reached | ||
| DFS | ||
| Number (%) of patients with event | 186 (20%) | 246 (27%) |
| Median in monthsBased on Kaplan-Meier estimates (95% CI) | NR (36.9, NR) | NR (NR, NR) |
| Hazard ratioBased on the stratified Cox proportional hazard model. (95% CI) | 0.72 (0.59, 0.87) | |
| p-ValueBased on stratified log-rank test. | 0.0003 | |
| 24-month DFS rate (95% CI) | 81% (78%, 83%) | 74% (71%, 77%) |
Figure 1: Kaplan-Meier Curve for Disease-Free Survival in LITESPARK-022
 |
In Combination with Lenvatinib for the Treatment of Advanced ccRCC
The efficacy of WELIREG in combination with lenvatinib was evaluated in LITESPARK-011 (NCT04586231), an open-label, randomized, active-controlled clinical trial in 747 patients with advanced ccRCC. Eligible patients had locally advanced or metastatic ccRCC and had progressed on or after a PD-1 or PD-L1 inhibitor, or within 6 months of completing adjuvant therapy with a PD-1 inhibitor. The study excluded patients with hypoxia, active CNS metastases and clinically significant cardiac disease within 6 months before first dose of study intervention.
Patients were randomized in a 1:1 ratio to receive WELIREG 120 mg in combination with lenvatinib 20 mg (n=371), or cabozantinib 60 mg (n=376) orally once daily until disease progression or unacceptable toxicity. Randomization was stratified by IMDC risk categories (favorable versus intermediate versus poor), number of prior lines of therapy (1 versus 2), and geographic region (North America versus Western Europe versus Rest of World). Imaging was performed every 8 weeks for the first 80 weeks, then every 12 weeks thereafter.
The major efficacy endpoints were progression-free survival (PFS) measured by BICR using RECIST v1.1 and overall survival (OS). Additional efficacy endpoints included objective response rate (ORR) by BICR using RECIST v1.1.
The study population characteristics were: median age 63 years (range: 30 to 86 years), 76% male; 87% White; 9% Asian; 1.6% American Indian or Alaska Native; 1.1% multiple races; 0.4% Black or African American; 0.8% not reported; 74% not Hispanic or Latino; 18% Hispanic or Latino; 8% ethnicity not reported. Fifty-eight percent of patients were ECOG performance status 0, 41% were ECOG performance status 1, and 1.2% were ECOG performance status 2. Seventy-two percent of patients had 1 prior line of therapy (4.4% with adjuvant therapy only), 28% had 2 or more prior lines of therapy. Patient distribution by IMDC risk categories was 24% favorable, 59% intermediate, and 17% poor. Bone metastasis was present in 40% of patients; liver metastasis was present in 25%.
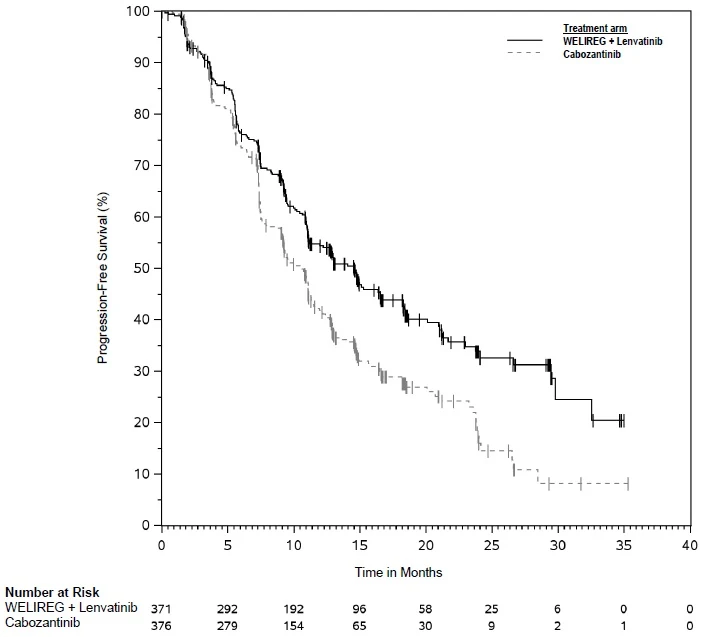
The trial demonstrated a statistically significant improvement in PFS and ORR for patients randomized to WELIREG in combination with lenvatinib compared to cabozantinib. The efficacy results for advanced ccRCC in LITESPARK-011 are summarized in Table 17 and Figure 2.
Table 17: Efficacy Results in Patients with Advanced ccRCC in LITESPARK-011
| Efficacy Outcome Measure | WELIREG plus Lenvatinib n=371 | Cabozantinib n=376 |
|---|---|---|
| NS – not statistically significant | ||
| Progression-Free Survival (PFS) | ||
| Number of events, n (%) | 196 (53%) | 240 (64%) |
| Progressive disease | 172 (46%) | 211 (56%) |
| Death | 24 (7%) | 29 (8%) |
| Median in months (95% CI) From product-limit (Kaplan-Meier) method for censored data | 14.6 (11.1, 16.6) | 10.6 (9.2, 11.1) |
| Hazard ratio Based on the stratified Cox proportional hazard model. (95% CI) | 0.74 (0.61, 0.89) | |
| p-ValueOne-sided p-Value based on stratified log-rank test compared with the significance boundary of 0.0017. | 0.001 | |
| Overall Survival (OS) | ||
| Number of events, n (%) | 195 (53%) | 224 (60%) |
| Median in months (95% CI) | 33.7 (29.0, 46.9) | 28.6 (24.1, 31.4) |
| Hazard ratio (95% CI) | 0.85 (0.70, 1.03) | |
| p-ValueBased on stratified log-rank test. | NS | |
| Confirmed Objective Response Rate | ||
| ORR % (n) (95% CI) | 53% (195) (47, 58) | 40% (149) (35, 45) |
| Complete response | 4% (15) | 1.1% (4) |
| Partial response | 49% (180) | 39% (145) |
| p-ValueOne-sided p-Value based on stratified Miettinen and Nurminen (M&N) method. | 0.0002 | |
Among the 195 patients treated with WELIREG in combination with lenvatinib who achieved a confirmed response based on BICR per RECIST 1.1, 122 (63%) patients had a duration of response ≥12 months at the pre-specified final analysis.
Figure 2: Kaplan-Meier Curve for Progression Free Survival in LITESPARK-011
 |
Monotherapy for the Treatment of Advanced ccRCC
The efficacy of WELIREG was evaluated in LITESPARK-005 (NCT04195750), an open-label, randomized, active-controlled clinical trial in 746 patients with unresectable, locally advanced or metastatic ccRCC that progressed following PD-1 or PD-L1 checkpoint inhibitor and VEGF receptor targeted therapies either in sequence or in combination.
Patients could have received up to 3 prior treatment regimens and were required to have measurable disease per RECIST v1.1. Patients were randomized in a 1:1 ratio to receive 120 mg WELIREG or 10 mg everolimus orally once daily until disease progression or unacceptable toxicity. Randomization was stratified by IMDC risk categories (favorable versus intermediate versus poor) and number of prior VEGF receptor targeted therapies (1 versus 2-3). Patients were evaluated radiologically at Week 9 from the date of randomization, then every 8 weeks through Week 49, and every 12 weeks thereafter.
The study population characteristics were: median age 63 years [range: 22 to 90 years], 42% age 65 or older; 78% male; 79% White; 12% Asian; 1% Black or African American; 11% Hispanic or Latino; 44% ECOG performance status 0 and 55% ECOG performance status 1. Prior therapies: 13% patients had 1 prior line of therapy, 43% had 2 prior lines of therapy and 43% had 3 prior lines of therapy; 49% received 2 to 3 prior VEGF receptor targeted therapies. Patient distribution by IMDC risk categories was 22% favorable, 66% intermediate, and 12% poor. Common sites of metastasis in patients were 65% lung, 59% lymph nodes, and 49% bone.
The major efficacy endpoints were Progression Free Survival (PFS) measured by BICR using RECIST v1.1 and Overall Survival (OS). Additional efficacy endpoint included objective response rate (ORR) by BICR using RECIST v1.1.
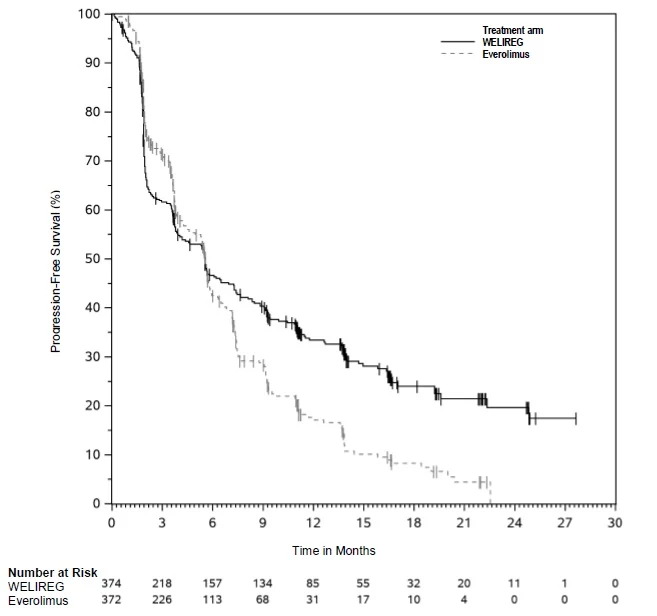
The trial demonstrated a statistically significant improvement in PFS for patients randomized to WELIREG compared with everolimus. Table 18 and Figure 3 summarize the efficacy results for LITESPARK-005.
Table 18: Efficacy Results for Advanced ccRCC (IRC assessment) for LITESPARK-005
| Efficacy Outcome Measure | WELIREG n=374 | Everolimus n=372 |
|---|---|---|
| NS – not statistically significant | ||
| Progression-Free Survival (PFS) | ||
| Number of events, n (%) | 257 (69%) | 262 (70%) |
| Progressive disease | 234 (63%) | 222 (60%) |
| Death | 23 (6%) | 40 (11%) |
| Median in months (95% CI)From product-limit (Kaplan-Meier) method for censored data | 5.6 (3.9, 7.0) | 5.6 (4.8, 5.8) |
| Hazard ratio Based on the stratified Cox proportional hazard model. (95% CI) | 0.75 (0.63, 0.90) | |
| p-Value One-sided p-Value based on stratified log-rank test compared with the significance boundary of 0.0021. | 0.0008 | |
| Overall Survival (OS) | ||
| Number of events, n (%) | 254 (68%) | 259 (70%) |
| Median in months (95% CI) | 21 (18, 24) | 18 (16, 22) |
| Hazard ratio (95% CI) | 0.92 (0.77, 1.10) | |
| p-ValueBased on stratified log-rank test. | NS | |
| Confirmed Objective Response Rate | ||
| Number of patients with measurable disease at baseline | 373 | 364 |
| ORR % (n) (95% CI) | 22% (82) (18, 27) | 4% (13) (2, 6) |
| Complete response | 3% (10) | 0% (0) |
| Partial response | 19% (72) | 4% (13) |
| p-ValueOne-sided p-value based on stratified Miettinen and Nurminen (M&N) method. | <0.0001 | |
Among the 82 patients treated with WELIREG who achieved a confirmed response based on BICR per RECIST 1.1, 25 (30%) patients had a duration of response ≥12 months.
Figure 3: Kaplan-Meier Curve for Progression-Free Survival in LITESPARK-005
 |
14.3 Pheochromocytoma or Paraganglioma
The efficacy of WELIREG was evaluated in LITESPARK-015 (NCT04924075), an open-label, multi-cohort clinical trial in 72 patients in Cohort A1 who had measurable disease verified by BICR per RECIST v1.1, documented histopathological diagnosis of pheochromocytoma or paraganglioma (PPGL), locally advanced or metastatic disease that was not amenable to surgery or curative treatment, and adequately controlled blood pressure (defined as BP <150/90 mm Hg, <135/85 mm Hg for adolescents) with no change in antihypertensive medications for patients with concomitant hypertension for at least 2 weeks prior to start of study treatment. Patients with carcinomatous meningitis were excluded. Patients received WELIREG 120 mg orally once daily until disease progression or unacceptable toxicity.
The study population characteristics were: median age 52 years [range: 22 to 77 years], 13% age 65 or older; 58% male; 93% White; 4.2% Black or African-American; 1.4% Asian; 6% Hispanic or Latino; 54% had an ECOG PS of 0 and 46% had an ECOG PS of 1. The median number of prior therapies was 1: (range: 0 to 5). A total of 50% of patients received prior chemotherapy, 44% received prior radiopharmaceuticals, and 25% received prior VEGF-TKIs. No patients had a history of VHL disease.
The major efficacy outcome measure for the treatment of locally advanced PPGL was objective response rate (ORR) measured by BICR using RECIST v1.1. Additional efficacy outcome measures were duration of response (DOR), time to response (TTR), and the proportion of patients who had a reduction in at least one antihypertensive medication by at least 50% maintained for at least six months.
Table 19 summarizes the efficacy results for PPGL in LITESPARK-015.
Table 19: Efficacy Results in Patients with PPGL in LITESPARK-015
| Efficacy Outcome Measure | WELIREG n=72 |
|---|---|
NR = not reached + = Denotes ongoing response. Data cut-off: October 23, 2024 | |
| Confirmed Objective Response Rate Based on BICR. , All responses were partial responses. | |
| ORR, % (95% CI) | 26% (17, 38) |
| Duration of Response | |
| Median in months (95% CI)Based on Kaplan-Meier estimates. | 20.4 (8.3, NR) |
| Range | 5.6+, 29.6+ |
| % with duration ≥ 12 months | 53% |
| Reduction in at least one antihypertensive medication by at least 50% maintained for at least 6 months | |
| Number of patients | 19 |
| Proportion of patients (95% CICalculated using the Clopper-Pearson method.)Based on the number of patients who were on antihypertensive medications at baseline (N=60). | 32% (20, 45) |
For PPGL, the median TTR was 11.0 months (range: 1.7 to 24.8).
16 HOW SUPPLIED/STORAGE AND HANDLING
How Supplied
WELIREG tablets are supplied as 40 mg blue, oval shaped, film-coated, debossed with “177” on one side and plain on the other side, available in:
- bottles of 90 tablets with child-resistant closure: NDC 0006-5331-01.
The bottle also contains two desiccant canisters. Do not eat.
Storage and Handling
Store at 20°C to 25°C (68°F to 77°F), excursions permitted between 15°C and 30°C (59°F and 86°F) [see USP Controlled Room Temperature].
17 PATIENT COUNSELING INFORMATION
Advise the patient to read the FDA-approved patient labeling (Medication Guide).
Anemia
Inform patients that WELIREG can cause severe anemia that may require blood transfusions and that red blood cell levels will be monitored routinely during treatment. Advise patients to contact their healthcare provider if the patient experiences any symptoms suggestive of anemia [see Warnings and Precautions (5.1)].
Hypoxia
Inform patients that WELIREG can cause severe hypoxia that may require discontinuation, supplemental oxygen, or hospitalization; and that oxygen levels will be monitored routinely during treatment. Advise patients to contact their healthcare provider if the patient experiences any symptoms suggestive of hypoxia [see Warnings and Precautions (5.2)].
Cardiac Dysfunction
Inform patients that WELIREG in combination with lenvatinib can cause cardiac dysfunction. Advise patients to immediately contact their healthcare provider for any symptoms or signs of cardiac dysfunction [see Warnings and Precautions (5.3)].
Embryo-Fetal Toxicity
- Advise pregnant women and females of reproductive potential of the risk to a fetus. Advise females to inform their healthcare provider of a known or suspected pregnancy [see Warnings and Precautions (5.4) and Use in Specific Populations (8.1)].
- Advise females of reproductive potential to use effective non-hormonal contraception during treatment with WELIREG and for 1 week after the last dose [see Use in Specific Populations (8.3)].
- Advise male patients with female partners of reproductive potential to use effective contraception during treatment with WELIREG and for 1 week after the last dose [see Use in Specific Populations (8.3)].
- Refer to the Prescribing Information of the individual therapeutic agents used in combination with WELIREG for pregnancy and contraception information. When used in combination, advise patients to use effective contraception during treatment and for the longest post-treatment duration recommended in the Prescribing Information of the individual products.
Lactation
- Advise females not to breastfeed during treatment with WELIREG and for 1 week after the last dose [see Use in Specific Populations (8.2)].
- Refer to the Prescribing Information of the individual therapeutic agents used in combination with WELIREG for lactation information. When used in combination, advise patients not to breastfeed during treatment and for the longest post-treatment duration recommended in the Prescribing Information of the individual products.
Infertility
Advise male and female patients that WELIREG may impair fertility [see Use in Specific Populations (8.3)].
Dosage and Administration
Instruct patients to take their dose of WELIREG at the same time each day (once daily). Advise patients that WELIREG can be taken with or without food. Each tablet should be swallowed whole [see Dosage and Administration (2.1)].
Manufactured for: Merck Sharp & Dohme LLC
Rahway, NJ 07065, USA
For patent information: www.msd.com/research/patent
Copyright © 2026 Merck & Co., Inc., Rahway, NJ, USA, and its affiliates.
All rights reserved.
uspi-mk6482-t-2609r006