


Prescribing information (package insert) - Voyxact
1 INDICATIONS AND USAGE
VOYXACT is indicated to reduce proteinuria in adults with primary immunoglobulin A nephropathy (IgAN) at risk for disease progression.
This indication is approved under accelerated approval based on reduction of proteinuria. It has not been established whether VOYXACT slows kidney function decline over the long-term in patients with IgAN. Continued approval for this indication may be contingent upon verification and description of clinical benefit in a confirmatory clinical trial.
2 DOSAGE AND ADMINISTRATION
2.1 Recommended Dosage
The recommended dosage of VOYXACT is 400 mg administered by subcutaneous injection once every 4 weeks.
2.2 Missed Dose
If a scheduled dose of VOYXACT is missed, administer the missed dose as soon as possible and then resume dosing every 4 weeks thereafter.
2.3 Preparation and Administration
VOYXACT is intended for patient self-administration or for administration by a caregiver. Provide proper training to patients and/or caregivers on the administration of VOYXACT prior to use according to the "Instructions for Use".
Visually inspect the prefilled syringe for particulate matter and discoloration. The solution should be clear to opalescent and colorless to yellow. Do not use the prefilled syringe if the solution contains visible particulate matter, is cloudy or discolored (other than clear to opalescent, colorless to yellow).
Allow VOYXACT prefilled syringe to come to room temperature up to 77°F (25°C) for 15 to 30 minutes before giving an injection. Keep VOYXACT prefilled syringe in the original carton to protect it from light. Once VOYXACT prefilled syringe has reached room temperature, do not return it to the refrigerator. Do not use VOYXACT if it has been at room temperature for 7 days or longer.
Administer VOYXACT by subcutaneous injection only. Inject into the front of the thigh or abdomen. The back of the upper arm can also be used as an injection site if administered subcutaneously by a caregiver. Do not inject into the same site used for the previous injection, or into moles, scars, bruises or areas where the skin is tender, damaged, red, scaly, or hard.
3 DOSAGE FORMS AND STRENGTHS
Injection: 400 mg/2 mL (200 mg/mL) clear to opalescent, colorless to yellow, solution in a single-dose prefilled syringe.
4 CONTRAINDICATIONS
VOYXACT is contraindicated in patients with serious hypersensitivity to sibeprenlimab-szsi or any of the excipients of VOYXACT.
5 WARNINGS AND PRECAUTIONS
5.1 Immunosuppression and Increased Risk of Infections
VOYXACT suppresses the immune system by reducing antibody production, which may increase the risk of infections. Patients with chronic or recurring infections may have an increased risk of serious infection. In clinical trials, infections occurred in 49% of patients treated with VOYXACT compared with 45% of patients treated with placebo.
Before initiating VOYXACT, assess patients for active infections. During treatment, monitor patients for signs and symptoms of infection. If a serious infection develops, consider interrupting VOYXACT until the infection is controlled.
There are limited clinical study data with concomitant use of VOYXACT and systemic immuno-suppressants. Consider the potential for increased immunosuppression when coadministering VOYXACT and immuno-suppressants or when initiating VOYXACT before or after immuno-suppressive therapy.
5.2 Immunosuppression and Immunization Risks
Because of its mechanism of action, VOYXACT may interfere with the immune responses to vaccines and increase the risk of infection from live vaccines. Live vaccines are not recommended within 30 days prior to initiation of VOYXACT or during treatment with VOYXACT as safety has not been established. No data are available on the secondary transmission of infection from persons receiving live vaccines to patients receiving VOYXACT or on the efficacy of immunizations administered while receiving VOYXACT.
6 ADVERSE REACTIONS
The following clinically significant adverse reactions are described elsewhere in the labeling:
- Immunosuppression and Increased Risk of Infections [see Warnings and Precautions (5.1)]
- Immunosuppression and Immunization Risks [see Warnings and Precautions (5.2)]
6.1 Clinical Trials Experience
Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice.
The safety of VOYXACT was evaluated in a randomized, double-blind, placebo-controlled, clinical study in patients with IgAN (VISIONARY). The median duration of exposure was 44 weeks in the 259 patients treated with VOYXACT and 48 weeks in the 251 patients administered placebo. The most common adverse reactions (reported in ≥10% of patients treated with VOYXACT and at a higher incidence than placebo) in patients treated with VOYXACT and placebo, respectively, were infections (49% versus 45%) and injection site reactions (24% versus 23%). The most common infection was upper respiratory infection (15% versus 14%), and the most common injection site reaction was injection site erythema (13% versus 12%). Most adverse reactions were reported as mild or moderate in severity and resolved without treatment interruption or discontinuation.
8 USE IN SPECIFIC POPULATIONS
8.1 Pregnancy
Risk Summary
There are no available data on VOYXACT use in pregnant women to evaluate for a drug-associated risk of major birth defects, miscarriage or other adverse maternal or fetal outcomes. Monoclonal antibodies, such as sibeprenlimab-szsi, can be actively transported across the placenta as pregnancy progresses; therefore, potential effects on a fetus are likely to be greater during the second and third trimester of pregnancy (see Clinical Considerations). In an enhanced prenatal and postnatal development (ePPND) toxicity study, administration of sibeprenlimab-szsi subcutaneously to pregnant monkeys did not result in any adverse effects on embryofetal or postnatal development at exposures approximately 10-times the clinical exposure at the maximum recommended human dose (MRHD) based on area under the curve (AUC) (see Data ).
The background risk of major birth defects and miscarriage for the indicated population are unknown. All pregnancies have a background risk of birth defect, loss or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Pregnant women exposed to VOYXACT, or their healthcare providers, should report VOYXACT exposure by calling 1-833-869-9228 or visiting www.VOYXACT.com.
Clinical Considerations
Disease-Associated Maternal and/or Embryo/Fetal Risk
IgA nephropathy is associated with adverse maternal outcomes, including increased rates of cesarean section, pregnancy-induced hypertension, pre-eclampsia and preterm delivery, and adverse fetal/neonatal outcomes, including stillbirth and low birth weight.
Fetal/Neonatal Adverse Reactions
Transport of endogenous IgG antibodies across the placenta increases as pregnancy progresses, and peaks during the third trimester. Therefore, VOYXACT may be present in infants exposed in utero. Consider the potential clinical impact of VOYXACT exposure in infants who were exposed to VOYXACT in utero.
Data
Animal Data
In an ePPND toxicity study, subcutaneous administration of sibeprenlimab-szsi once every two weeks to pregnant cynomolgus monkeys from gestation Day 20 through delivery (includes the period of organogenesis) did not result in any adverse effect on embryofetal or postnatal development at the single tested dose of 101 mg/kg, which provided an approximately 10-fold margin to the clinical exposure at the MRHD based on AUC.
8.2 Lactation
Risk Summary
There are no data on the presence of sibeprenlimab-szsi in human milk, the effects of sibeprenlimab-szsi on the breastfed infant, or the effects of sibeprenlimab-szsi on milk production. Endogenous maternal IgG and monoclonal antibodies are transferred into human milk. The effects of local gastrointestinal exposure on sibeprenlimab-szsi in the breastfed infant are unknown. The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for VOYXACT and any potential adverse effects on the breastfed child from VOYXACT or from the underlying maternal condition.
8.4 Pediatric Use
Safety and effectiveness of VOYXACT in pediatric patients have not been established.
8.5 Geriatric Use
Clinical studies of VOYXACT did not include sufficient numbers of patients aged 65 and over to determine whether they respond differently from younger adult patients.
No clinically meaningful differences in the pharmacokinetics of VOYXACT were observed in patients aged 65 and over compared to younger adult patients [see Clinical Pharmacology (12.3)].
11 DESCRIPTION
VOYXACT contains sibeprenlimab-szsi, an A Proliferation Inducing Ligand (APRIL) blocker and humanized immunoglobulin G2 (IgG2) monoclonal antibody produced by Chinese Hamster Ovary (CHO) cells.
The approximate molecular weight of sibeprenlimab-szsi is 146 kDa.
VOYXACT (sibeprenlimab-szsi) injection is a sterile, preservative-free, clear to opalescent, colorless to yellow solution in a single-dose prefilled syringe for subcutaneous use.
Each 2 mL prefilled syringe delivers 400 mg sibeprenlimab-szsi and the inactive ingredients: arginine (17.6 mg), glutamic acid (14.8 mg), histidine (4.34 mg), L-histidine hydrochloride monohydrate (4.62 mg), polysorbate 80 (0.40 mg), sorbitol (36.4 mg), and Water for Injection, USP. The pH is 6.2.
12 CLINICAL PHARMACOLOGY
12.1 Mechanism of Action
VOYXACT binds to APRIL with a dissociation constant (KD) of 0.95 pM, which blocks signaling at the B cell maturation antigen (BCMA) and transmembrane activator and calcium modulator and cyclophilin ligand interactor (TACI) receptors. Inhibition of APRIL results in reduced levels of serum galactose-deficient immunoglobulin A1 (Gd-IgA1), which is implicated in the pathogenesis of IgAN.
12.2 Pharmacodynamics
In healthy subjects administered a single 400 mg subcutaneous VOYXACT dose, serum levels of APRIL were reduced by >90% by Day 3 and the reduction was maintained until Day 42.
In IgAN patients treated with VOYXACT every four weeks in the VISIONARY Study, APRIL suppression > 90% was observed by Week 4 and was sustained throughout treatment. Serum Gd-IgA1, IgA, IgG, and IgM levels decreased within 4 weeks, reached a plateau by Week 24, and by Week 48 mean serum levels were reduced from baseline by 67% for Gd-IgA1, 69% for IgA, 35% for IgG, and 75% for IgM.
12.3 Pharmacokinetics
Following 400 mg doses of VOYXACT administered subcutaneously every 4 weeks to patients with IgAN, steady-state is reached by 20 weeks of dosing.
Absorption
Following a single subcutaneous dose of 400 mg VOYXACT in healthy subjects, the median time to reach peak concentration is 8 days.
The absolute bioavailability of sibeprenlimab-szsi is approximately 92% and there is no difference in relative bioavailability following administration to the abdomen, thigh, or arm.
Distribution
The volume of distribution is 4 L.
Elimination
Following a single 400 mg VOYXACT dose, the mean terminal half-life is 9.3 days. The mean apparent clearance of sibeprenlimab-szsi following 400 mg doses every 4 weeks is 206 mL/day.
Metabolism
As an IgG2 monoclonal antibody, sibeprenlimab-szsi is expected to be degraded by proteolytic enzymes via catabolic pathways in the same manner as endogenous IgG.
Specific Populations
No dedicated studies were conducted to evaluate the effects of renal impairment and hepatic impairment on the pharmacokinetics of sibeprenlimab-szsi.
Population pharmacokinetic analysis did not identify any clinically relevant differences in the pharmacokinetics of sibeprenlimab-szsi based on sex, age, weight, race, and mild to moderate renal impairment (eGFR: 30 to 89 mL/min).
12.6 Immunogenicity
The observed incidence of anti-drug antibodies (ADA) is highly dependent on the sensitivity and specificity of the assay. Differences in assay methods preclude meaningful comparisons of the incidence of ADA in the study described below with the incidence of ADA in other studies, including those of sibeprenlimab-szsi.
During the treatment period in the VISIONARY Study, 88 of 256 (34%) evaluable patients treated with VOYXACT developed ADA. Among the 88 patients who tested positive for ADA, 21 patients (23.9%) developed ADA that had neutralizing activity. Sibeprenlimab-szsi exposure in patients with IgAN who developed ADA was ~ 40% lower than in patients with undetectable ADA over the treatment period. The reduction in urine protein/creatinine ratio based on 24-hour urine collections (uPCR-24h) from baseline to Month 9 was numerically lower in patients who developed ADA (41.6%) compared to those who did not (52.7%). The clinical significance of the differences in uPCR reduction according to the presence or absence of ADA is not clear. The presence of ADA did not have a clinically significant effect on the incidence or severity of adverse reactions.
13 NONCLINICAL TOXICOLOGY
13.1 Carcinogenesis, Mutagenesis, Impairment of Fertility
No carcinogenicity or mutagenicity studies have been conducted with sibeprenlimab-szsi.
Impairment of Fertility
In cynomolgus monkeys intravenously administered sibeprenlimab-szsi at doses of 25, 50, or 100 mg/kg once every two weeks for 26 weeks, no sibeprenlimab-related adverse effects on female menstrual cycle frequency and lengths, male sperm analysis of motility, concentration and count, or male and female reproductive organs were observed at doses up to 100 mg/kg, which provides an approximately 13-fold exposure margin to the clinical exposure at the MRHD based on AUC.
14 CLINICAL STUDIES
The effect of VOYXACT on proteinuria was evaluated in a randomized, double-blind, placebo-controlled, multicenter, global study (VISIONARY, NCT05248646) in adults with biopsy-confirmed IgAN, an eGFR ≥30 mL/min/1.73 m2, proteinuria (defined as either urine protein/creatinine ratio based on 24-hour urine collections [uPCR-24h] ≥0.75 g/g or urine protein ≥1.0 g/day), and on a stable and maximally tolerated dose of an angiotensin-converting enzyme inhibitor (ACEi) and/or angiotensin receptor blocker (ARB) with or without a sodium-glucose co-transporter 2 inhibitor (SGLT2i). Patients with other glomerulopathies or those who had been treated with systemic immunosuppressants in the 16 weeks prior to screening were excluded. Patients were randomized 1:1 to receive either VOYXACT or placebo injected subcutaneously once every 4 weeks.
The study enrolled a total of 510 patients. An interim analysis for efficacy was conducted on the first 320 (63%) randomized patients who had the opportunity to reach the Month 9 visit, 152 of whom were randomized to receive VOYXACT while 168 were randomized to receive placebo. Baseline demographics and disease characteristics were generally balanced between treatment groups. At baseline, the median age was 42 years (range 18 to 83 years); 63% were male, 59% were Asian, 38% were White, and 3% were of Other race.
At baseline, mean uPCR-24h was 1.5 g/g, mean estimated glomerular filtration rate (eGFR) was 63 mL/min/1.73 m2, and 74% had hematuria (based on urine dipstick). Approximately 67% of patients had a history of hypertension and 7% had a history of type 2 diabetes mellitus. At baseline, 98% were treated with an ACEi and/or ARB and 40% of patients were also on an SGLT2i.
The primary endpoint was the relative change from baseline in uPCR-24h at Month 9. The mean estimated percent change from baseline in uPCR-24h is shown in Figure 1. The observed geometric mean percent change from baseline over time for uPCR from spot first morning void samples is shown in Figure 2.
Figure 1: Estimated Percent Change Compared to Baseline in uPCR-24h at Month 9 in Patients with IgAN in the VISIONARY Study
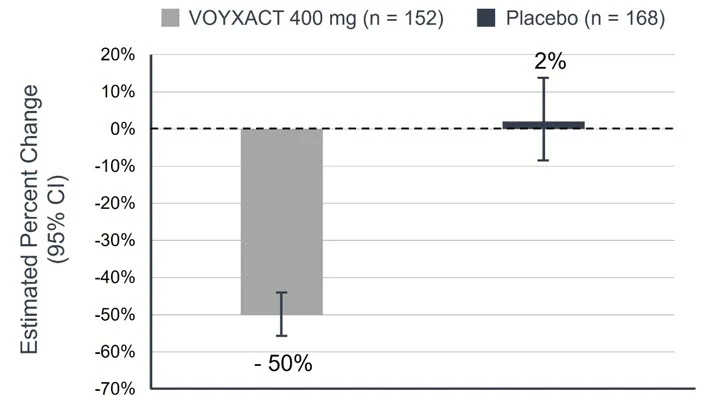
| CI = Confidence Interval | |
| 24-hour uPCR at Month 9 compared to baseline is defined as uPCR-24h9months/uPCR-24hBaseline. | |
| The bar indicates the geometric mean percentage change at 9 months compared with baseline, and the whiskers indicate the 95% CI. | |
| Data were included in the analysis regardless of early treatment discontinuation and initiation of confounding therapy (treatment policy strategy). Missing data were imputed using multiple imputation. | |
| VOYXACT | -50% |
| Placebo | 2% |
| VOYXACT vs. Placebo (96.5% CI)96.5% CI corresponds to the two-sided significance level of 0.035 for the interim analysis (IA). | 51% (43%, 58%) |
| p-value | <0.0001 |
Figure 2: Percent Change Compared to Baseline in Spot uPCR Over Time in Patients with IgAN in the VISIONARY Study
| CI = Confidence Interval |
| Spot uPCR at specific week is defined as spot uPCR/spot uPCRbaseline |
| The dots indicate the geometric mean percentage change at specific weeks compared with baseline and the whiskers indicate the corresponding 95% CIs based on observed and non-imputed spot uPCR. |
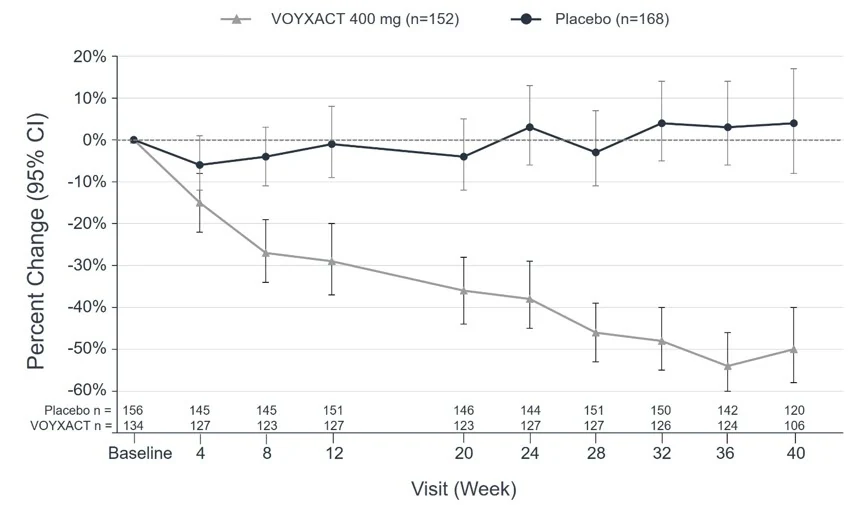 |
The treatment effect (percentage reduction in uPCR-24h between VOYXACT and placebo) was consistent across the following subgroups and pre-specified stratification factors: sex, age, race, ethnicity, and geographic region, baseline proteinuria (uPCR-24h), baseline eGFR, and SGLT2i use.
16 HOW SUPPLIED/STORAGE AND HANDLING
How Supplied
VOYXACT (sibeprenlimab-szsi) injection is supplied as a sterile, preservative-free, clear to opalescent, colorless to yellow solution in a single-dose prefilled syringe with a 27 gauge, ½ inch needle and a needle safety device.
VOYXACT prefilled syringe is not made with natural rubber latex.
VOYXACT 400 mg/2mL (200 mg/mL) prefilled syringe is packaged in an individual carton (NDC 59148-400-75).
Storage and Handling
Store VOYXACT in a refrigerator at 36°F to 46°F (2°C to 8°C). Keep the prefilled syringe in its original box to protect it from light.
Do not freeze. Do not shake. Do not expose to heat or direct sunlight.
Once VOYXACT prefilled syringe has reached room temperature, do not return it to the refrigerator.
Do not use VOYXACT if it has been at room temperature for 7 days or longer.
17 PATIENT COUNSELING INFORMATION
Advise the patient and/or caregiver to read the FDA-approved patient labeling (Patient Information and Instructions for Use).
Infections
Inform patients that they may be more likely to develop infections when taking VOYXACT. Instruct patients to tell their healthcare provider if they develop signs or symptoms of an infection [see Warnings and Precautions (5.1)].
Hypersensitivity
Inform patients about the signs and symptoms of hypersensitivity reactions. Advise patients to discontinue VOYXACT and seek immediate medical attention for signs or symptoms of hypersensitivity reactions [see Contraindications (4)].
Pregnancy
Advise patients who are exposed to VOYXACT during pregnancy to contact Otsuka Pharmaceutical Development and Commercialization, Inc. at 1-833-869-9228 or www.VOYXACT.com.
Manufactured by:
Otsuka Pharmaceutical Company, Ltd., Tokyo, 101-8535 Japan
U.S. License No 2387
Distributed by:
Otsuka America Pharmaceutical, Inc.
Rockville, MD 20850, USA
©2025, Otsuka Pharmaceutical Co., Ltd., Tokyo, 101-8535 Japan