


Prescribing information (package insert) - Veppanu
1 INDICATIONS AND USAGE
VEPPANU is indicated for the treatment of adults with estrogen receptor (ER)-positive, human epidermal growth factor receptor 2 (HER2)-negative, estrogen receptor-1 (ESR1)-mutated advanced or metastatic breast cancer, as detected by an FDA-authorized test, with disease progression following at least one line of endocrine therapy.
2 DOSAGE AND ADMINISTRATION
2.1 Patient Selection
Select patients for treatment of ER-positive, HER2-negative advanced or metastatic breast cancer with VEPPANU based on the presence of ESR1 mutation(s) in plasma specimen using an FDA-authorized test [see Indications and Usage (1) and Clinical Studies (14)].
Information on FDA-authorized tests for detection of ESR1 mutations in breast cancer is available at: http://www.fda.gov/CompanionDiagnostics.
2.2 Recommended Dosage and Administration
The recommended dosage of VEPPANU is 200 mg taken orally once daily with food [see Clinical Pharmacology (12.3)] until disease progression or unacceptable toxicity.
Swallow VEPPANU tablet(s) whole. Do not chew, crush, dissolve, or split prior to swallowing. Do not take VEPPANU tablets that are broken, cracked, or look damaged.
If a patient misses a dose or vomits after taking a dose, the patient should take the next dose at the regularly scheduled time.
2.3 Dosage Modifications for Adverse Reactions
The recommended dose reduction for adverse reactions is 100 mg orally once daily.
Permanently discontinue VEPPANU in patients who are unable to tolerate 100 mg orally once daily.
The recommended dosage modifications for VEPPANU for adverse reactions are provided in Table 1 and Table 2.
Table 1: Dosage Modifications for Adverse Reactions (Except QTc Prolongation)
| CTCAE Severity Grade | Dosage Modification |
|---|---|
| Abbreviations: CTCAE=National Cancer Institute (NCI) Common Terminology Criteria for Adverse Events | |
| Grade 1 | No dose modification is required. |
| Grade 2 | Consider interruption of VEPPANU until recovery to Grade ≤1 or baseline. Then resume VEPPANU at the same dose. |
| Grade 3 | First occurrence: Interrupt VEPPANU until recovery to Grade ≤1 or baseline. Then resume VEPPANU at the same dose or at the reduced dose at the discretion of the physician. If the Grade 3 toxicity recurs, interrupt VEPPANU until recovery to Grade ≤1 or baseline. Then resume VEPPANU at the reduced dose or discontinue VEPPANU at the discretion of the physician. |
| Grade 4 | First occurrence: Interrupt VEPPANU until recovery to Grade ≤1 or baseline. Then resume VEPPANU at the reduced dose. If a Grade 4 or intolerable adverse reaction recurs, permanently discontinue VEPPANU. |
Table 2: Dosage Modification and Management for QTc Prolongation
QTc Prolongation Heart-rate corrected QTc using Fridericia's method. [see Warnings and Precautions (5.1)] | Dosage Modification and Management |
|---|---|
QTc >480 ms or >60 ms increase from baseline (and QTc ≤500 ms) | Withhold until QTc resolves to ≤480 ms and ≤60 ms above baseline, then resume VEPPANU at the same dose. Identify and treat reversible causes (e.g., hypokalemia and hypomagnesemia). Initiate more frequent ECG monitoring. |
| QTc >500 ms | Withhold until QTc resolves to ≤480 ms and ≤60 ms above baseline, then:
Initiate more frequent ECG monitoring. Permanently discontinue if QTc >500 ms recurs. |
| Torsade de Pointes, polymorphic ventricular tachycardia, or signs/symptoms of serious arrhythmia | Permanently discontinue VEPPANU. |
2.4 Dosage Modifications for Drug Interactions
Strong CYP3A Inhibitors
Avoid concomitant use with strong CYP3A inhibitors in patients receiving VEPPANU 200 mg once daily. If concomitant use cannot be avoided, reduce VEPPANU from 200 mg once daily to 100 mg once daily [see Drug Interactions (7.1)]. After a CYP3A inhibitor has been discontinued for 3 to 5 elimination half-lives, resume VEPPANU 200 mg once daily.
Avoid concomitant use with strong CYP3A inhibitors in patients receiving VEPPANU 100 mg once daily.
Strong CYP3A Inducers
Avoid concomitant use with strong CYP3A inducers in patients receiving VEPPANU 200 mg once daily. If concomitant use cannot be avoided, increase VEPPANU from 200 mg once daily to 300 mg once daily [see Drug Interactions (7.1)]. After a CYP3A inducer has been discontinued for 7 to 14 days, resume VEPPANU 200 mg once daily.
Avoid concomitant use with strong CYP3A inducers in patients receiving VEPPANU 100 mg once daily.
3 DOSAGE FORMS AND STRENGTHS
Tablets:
- 100 mg blue film-coated, immediate release, round tablet debossed with "VEP" on one side and "100" on the other side.
- 200 mg blue film-coated, immediate release, oval tablet debossed with "VEP" on one side and "200" on the other side.
4 CONTRAINDICATIONS
None.
5 WARNINGS AND PRECAUTIONS
5.1 QTc Interval Prolongation
VEPPANU can cause QT (QTc) interval prolongation [see Clinical Pharmacology (12.2)].
In VERITAC-2, QTc interval prolongation was reported in 10% of patients; Grade 3 occurred in 1.6% of patients. The heart-rate corrected QTc interval using Fridericia's method was greater than 500 msec in 1.6% of patients, and the increase from baseline QTc was greater than 60 msec in 2.6% of patients. VEPPANU dose reduction was required for 0.3% of patients due to QTc interval prolongation [see Adverse Reactions (6.1)].
Correct electrolyte abnormalities, including hypokalemia and hypomagnesemia, prior to and during treatment with VEPPANU. Perform an ECG prior to initiation of treatment with VEPPANU, and do not initiate VEPPANU in patients with QTc > 470 msec. Repeat ECG approximately 4 weeks after initiating treatment and as clinically indicated. In patients with congenital long QTc syndrome, congestive heart failure, electrolyte abnormalities, or those who are taking medications known to prolong the QTc interval, additional ECG monitoring may be necessary. Avoid concomitant use of VEPPANU with strong CYP3A inhibitors or drugs known to prolong the QTc interval. Reduce VEPPANU dose when concomitant use with strong CYP3A inhibitors cannot be avoided [see Dosage and Administration (2.4), Drug Interactions (7.1, 7.3), and Clinical Pharmacology (12.2)]. If concomitant use with other QTc-prolonging agents cannot be avoided, increase the frequency of ECG monitoring.
Withhold, reduce dose, or permanently discontinue based on severity [see Dosage and Administration (2.3)].
5.2 Embryo-Fetal Toxicity
Based on findings from animal studies and its mechanism of action, VEPPANU can cause fetal harm when administered to a pregnant woman. In an animal reproduction study, oral administration of vepdegestrant to pregnant rats during the period of organogenesis resulted in adverse developmental outcomes, including embryo-fetal mortality and structural abnormalities, at maternal exposures below the recommended dose based on area under the curve (AUC).
Advise pregnant women and females of reproductive potential of the potential risk to a fetus. Advise females of reproductive potential to use effective contraception during treatment with VEPPANU and for 2 weeks after the last dose. Advise male patients with female partners of reproductive potential to use effective contraception during treatment with VEPPANU and for 2 weeks after the last dose [see Use in Specific Populations (8.1, 8.3) and Clinical Pharmacology (12.1)].
6 ADVERSE REACTIONS
The following clinically significant adverse reaction is described elsewhere in the labeling:
- QTc Interval Prolongation [see Warnings and Precautions (5.1)]
6.1 Clinical Trials Experience
Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice.
The safety of VEPPANU was evaluated in patients with ER-positive, HER2-negative, advanced or metastatic breast cancer following endocrine therapy in VERITAC-2 [see Clinical Studies (14)].
Patients received VEPPANU 200 mg orally once daily (N=312) or fulvestrant 500 mg intramuscularly on Days 1 and 15 of Cycle 1 and then on Day 1 of each subsequent 28-day cycle (N=307). Among patients who received VEPPANU, 33% were exposed for 6 months or longer and 6% were exposed for greater than one year.
Serious adverse reactions occurred in 9% of patients who received VEPPANU. The serious adverse reactions included any fracture (1.3%), fall, hypercalcemia, hepatic injury, pneumonia, musculoskeletal pain (0.6% each), and QTc prolonged (0.3%). Fatal adverse reactions occurred in 1.0% of patients who received VEPPANU, including dyspnea, cerebral ischemia, and unknown cause (one patient each).
Permanent discontinuation of VEPPANU due to an adverse reaction occurred in 2.9% of patients. Adverse reactions that resulted in permanent discontinuation of VEPPANU included increased alanine aminotransferase (ALT) and dyspnea (0.6% each).
Dosage interruptions of VEPPANU due to an adverse reaction occurred in 14% of patients. Adverse reactions which required dosage interruption in >1% of patients included neutropenia (1.9%), anemia, hepatic injury, nausea, fatigue, and musculoskeletal pain (1.3% each).
Dosage reductions of VEPPANU due to an adverse reaction occurred in 1.9% of patients. Adverse reactions which required dosage reductions of VEPPANU included electrocardiogram QT prolonged, fatigue and musculoskeletal pain (0.3% each).
The most common (≥10%) adverse reactions, including laboratory abnormalities, were decreased white blood cells, increased AST, musculoskeletal pain, fatigue, decreased hemoglobin, decreased neutrophils, increased ALT, increased alkaline phosphatase, nausea, decreased blood potassium, increased bilirubin, decreased appetite, electrocardiogram QT prolonged, decreased platelets, and constipation.
Table 3 and Table 4 summarize adverse reactions and laboratory abnormalities in VERITAC-2, respectively.
Table 3: Adverse Reactions (≥10%) in Patients with ER+, HER2-, Advanced or Metastatic Breast Cancer Who Received VEPPANU in VERITAC-2Adverse reactions were graded using NCI CTCAE version 5.0.
| Adverse Reaction | VEPPANU N=312 | Fulvestrant N=307 | ||
|---|---|---|---|---|
All Grades % | Grade 3No Grade 4 events were reported. % | All Grades % | Grade 3 % | |
| Musculoskeletal and Connective Tissue Disorders | ||||
| Musculoskeletal painIncludes multiple related terms. | 30 | 2.6 | 23 | 1 |
| General Disorders and Administration Site Conditions | ||||
| Fatigue | 29 | 1 | 16 | 1.3 |
| Gastrointestinal Disorders | ||||
| Nausea | 14 | 0 | 9 | 1 |
| Constipation | 10 | 0 | 3.3 | 0 |
| Metabolism and Nutrition Disorders | ||||
| Decreased appetite | 11 | 0.3 | 5 | 0 |
| Investigations | ||||
| Electrocardiogram QT prolonged | 10 | 1.6 | 1.3 | 0.3 |
Clinically relevant adverse reactions in <10% of patients who received VEPPANU included headache, hot flush, diarrhea, vomiting, bradycardia, and urinary tract infection.
Table 4: Select Laboratory Abnormalities (≥10%) that Worsened from Baseline in Patients with ER+, HER2-, Advanced or Metastatic Breast Cancer Who Received VEPPANU in VERITAC-2
| Laboratory Abnormality | VEPPANUThe denominator used to calculate the rate varied between 308 and 310 based on the number of patients with a baseline value and at least one post-treatment value. | FulvestrantThe denominator used to calculate the rate varied between 302 and 303 based on the number of patients with a baseline value and at least one post-treatment value. | ||
|---|---|---|---|---|
All Grades % | Grade 3 or 4 % | All Grades % | Grade 3 or 4 % | |
| Hematology | ||||
| White blood cells decreased | 33 | 0.3 | 15 | 0.7 |
| Hemoglobin decreased | 24 | 2.3 | 20 | 3.6 |
| Neutrophils decreased | 23 | 2.3 | 13 | 0.7 |
| Platelets decreased | 10 | 1.3 | 11 | 1.3 |
| Chemistry | ||||
| Aspartate aminotransferase increased | 31 | 1.6 | 23 | 1.7 |
| Alanine aminotransferase increased | 22 | 0.6 | 23 | 1.0 |
| Alkaline phosphatase increased | 21 | 0 | 23 | 0.3 |
| Blood potassium decreased | 14 | 2.6 | 6 | 0.3 |
| Bilirubin increased | 14 | 1.0 | 8 | 1.3 |
7 DRUG INTERACTIONS
7.1 Effect of Other Drugs on VEPPANU
Table 5 describes drug interactions where concomitant use of another drug affects VEPPANU.
Table 5: Drug Interactions that Affect VEPPANU
| Strong CYP3A Inhibitors | |
| Prevention or Management | Strong CYP3A Inhibitors:
|
| Mechanism and Clinical Effect(s) |
|
| Strong CYP3A Inducers | |
| Prevention or Management |
|
| Mechanism and Clinical Effect(s) |
|
7.2 Effect of VEPPANU on Other Drugs
Table 6 describes drug interactions where concomitant use of VEPPANU affects another drug.
Table 6: VEPPANU Drug Interactions that Affect Other Drugs
| Certain P-gp Substrates | |
| Prevention or Management |
|
| Mechanism and Clinical Effect(s) |
|
| Certain UGT1A9 Substrates | |
| Prevention or Management |
|
| Mechanism and Clinical Effect(s) |
|
7.3 Drugs that Prolong QTc Interval
Avoid concomitant use of VEPPANU with other drugs with a known potential to prolong the QTc interval.
If concomitant use cannot be avoided:
- Obtain ECGs when initiating and during concomitant use, and as clinically indicated [see Warnings and Precautions (5.1)].
- Withhold VEPPANU if the QTc interval is >480 ms or the change from baseline is >60 ms [see Dosage and Administration (2.3)].
Vepdegestrant causes QTc interval prolongation [see Clinical Pharmacology (12.2)]. Concomitant use of VEPPANU with other drugs that prolong the QTc interval may result in a greater increase in the QTc interval and adverse reactions associated with QTc interval prolongation, including Torsade de Pointes, other serious arrhythmias, and sudden death [see Warnings and Precautions (5.1)].
8 USE IN SPECIFIC POPULATIONS
8.1 Pregnancy
Risk Summary
Based on findings in animals and its mechanism of action, VEPPANU can cause fetal harm when administered to a pregnant woman [see Clinical Pharmacology (12.1)]. There are no available human data on the use of VEPPANU in pregnant women to inform the drug-associated risk. In an animal reproduction study, oral administration of vepdegestrant to pregnant rats during the period of organogenesis caused adverse developmental outcomes, including embryo-fetal mortality and structural abnormalities at maternal exposures below the recommended dose based on AUC (see Data ). Advise pregnant women and females of reproductive potential of the potential risk to a fetus.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Data
Animal Data
In an embryo-fetal development study in pregnant rats, administration of oral doses of vepdegestrant up to 300 mg/kg/day during the period of organogenesis resulted in embryo-fetal mortality (increased resorptions, post-implantation loss and reduced number of live fetuses) at ≥30 mg/kg/day (approximately 0.3 times the human AUC at the recommended dose). Additional adverse effects at ≥30 mg/kg/day included reduced fetal weight and skeletal abnormalities including delays in skeletal ossification (reduced number of ossification sites, incompletely ossified cervical arches or thoracic centra), skeletal malformations (fusion of sacral centra, hemivertebrae of the sacrum), and/or increased incidence of fetal variations (short cervical ribs, misaligned caudal vertebrae, misshapen cervical arches, and misaligned sacral vertebrae).
8.2 Lactation
Risk Summary
There are no data on the presence of vepdegestrant or its metabolites in human milk, or its effects on milk production or the breastfed child. Because of the potential for serious adverse reactions in the breastfed child, advise lactating women not to breastfeed during treatment with VEPPANU and for 2 weeks after the last dose.
8.3 Females and Males of Reproductive Potential
VEPPANU can cause fetal harm when administered to a pregnant woman [see Use in Specific Populations (8.1)].
Pregnancy Testing
Verify the pregnancy status in females of reproductive potential prior to initiating VEPPANU treatment.
Contraception
Females
Advise females of reproductive potential to use effective contraception during treatment with VEPPANU and for 2 weeks after the last dose.
Males
Advise male patients with female partners of reproductive potential to use effective contraception during treatment with VEPPANU and for 2 weeks after the last dose.
Infertility
Based on findings from animal studies, VEPPANU may impair fertility in females and males of reproductive potential. The effects of vepdegestrant on fertility were reversible in female animals [see Nonclinical Toxicology (13.1)] .
8.4 Pediatric Use
The safety and effectiveness of VEPPANU in pediatric patients have not been established.
8.5 Geriatric Use
Of 313 patients who received VEPPANU in the VERITAC-2 study, 39% were 65 years of age or older and 13% were 75 years of age or older. No overall differences in safety or effectiveness of VEPPANU were observed between patients 65 years of age or older compared to younger patients. There is an insufficient number of patients 75 years of age or older to assess whether there are differences in safety or effectiveness.
11 DESCRIPTION
Vepdegestrant is a heterobifunctional protein degrader. It is a small molecule comprised of an estrogen receptor binding domain joined by a linker to an E3 ligase binding domain. The chemical name of vepdegestrant is 2,6-piperidinedione, 3-[1,3-dihydro-1-oxo-5-[4-[[1-[4-[(1R,2S)-1,2,3,4-tetrahydro-6-hydroxy-2-phenyl-1-naphthalenyl]phenyl]-4-piperidinyl]methyl]-1-piperazinyl]-2H-isoindol-2-yl]-, (3S)-. The chemical structure of vepdegestrant is:
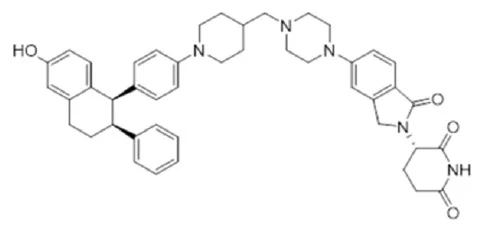
Vepdegestrant is white to off-white to pale yellow solid with the molecular formula of C45H49N5O4 and a molecular weight of 723.90 Daltons. Vepdegestrant solubility is pH dependent. The solubility ranges from freely soluble under gastric pH conditions to slightly soluble under intestinal pH conditions.
VEPPANU is supplied as blue film-coated, immediate release tablets containing either 100 mg or 200 mg vepdegestrant together with: colloidal silicon dioxide, croscarmellose sodium, hypromellose, lactose monohydrate, microcrystalline cellulose, sodium stearyl fumarate, vitamin E-polyethylene glycol succinate, and Opadry® QX Blue as inactive ingredients. Opadry® QX Blue film-coating contains: FD&C Blue No. 2 (indigo carmine) aluminum lake, ferric oxide yellow (yellow iron oxide), ferrosoferric oxide (black iron oxide), glyceryl mono and dicaprylocaprate (glycerol monocaprylocaprate), polyvinyl alcohol, polyvinyl alcohol polyethylene glycol graft copolymer [macrogol poly (vinyl alcohol) grafted copolymer], talc, and titanium dioxide.
12 CLINICAL PHARMACOLOGY
12.1 Mechanism of Action
Vepdegestrant is a heterobifunctional protein degrader that binds to estrogen receptor (ER) and the E3 ligase cereblon (CRBN). This interaction results in the degradation cascade through CRBN-mediated polyubiquitination and degradation of ER by the proteasome, leading to reduction of ER protein levels in breast cancer cells.
Vepdegestrant induced degradation of wild-type (WT) and mutant ER, inhibited ER-dependent breast cancer cell line proliferation in vitro and demonstrated antitumor activity in vivo in both WT and mutant ESR1 breast cancer models.
12.2 Pharmacodynamics
The exposure-response relationship and time-course of pharmacodynamic response of vepdegestrant have not been fully characterized.
Cardiac Electrophysiology
The largest mean increase in QTc interval was 12 ms (upper confidence interval = 15 ms) after administration of vepdegestrant at the recommended dosage of 200 mg once daily in patients with ESR1 mutation-positive breast cancer.
12.3 Pharmacokinetics
Vepdegestrant pharmacokinetics were observed at steady state in patients with ER+/HER2- breast cancer at the approved recommended dosage of 200 mg once daily and are presented as mean (coefficient of variation (CV%)) unless otherwise specified.
Vepdegestrant maximum concentration (Cmax) is 926 ng/mL (39%), and the total systemic exposure (AUC) is 17,155 ng•hr/mL (36%). Vepdegestrant AUC and Cmax increase in an approximately dose proportional manner over the dose range of 100 mg (0.5 times the approved recommended dose) to 500 mg (2.5 times the approved recommended dose). Vepdegestrant accumulation is approximately 1.4-fold for AUC and 1.3-fold for Cmax. Vepdegestrant steady state is reached in approximately 7 days.
Absorption
Vepdegestrant median (min, max) time to maximum plasma concentration (Tmax) is approximately 6 (4, 8) hours.
Effect of Food
Vepdegestrant AUC increased 2.9-fold and Cmax 3.2-fold following administration with a high-fat meal (approximately 800 to 1,000 calories; ≥50% fat).
Distribution
Vepdegestrant plasma protein binding is >99%. The apparent (oral) volume of distribution is 764 L (26%) following a single 200 mg dose.
Elimination
Vepdegestrant effective elimination half-life is 19 hours (50%) with an apparent (oral) clearance of 12 L/h (36%).
Metabolism
Vepdegestrant is primarily metabolized through direct sulfation via multiple SULT isoforms and oxidation via CYP3A4 and to a lesser extent by CYP2C8, CYP2C9 and CYP3A5. Unchanged total vepdegestrant represented 92% of total radioactivity in plasma.
Excretion
Following a single oral dose of radiolabeled vepdegestrant 200 mg to healthy subjects, approximately 68% of the dose was recovered in feces (18% unchanged) and 1.5% in urine (<0.02% unchanged).
Specific Populations
No clinically significant differences in the pharmacokinetics of vepdegestrant were observed based on age (26 to 89 years), sex, body weight (37 to 181 kg), race (60% White, 27% Asian, 2.2% Black or African American, and 10% other), CLcr 30 mL/min to 90 mL/min (estimated by Cockcroft Gault equation) or mild hepatic impairment (total bilirubin ≤ULN and AST>ULN or total bilirubin >1 to 1.5 × ULN and any AST).
The effect of moderate hepatic impairment (total bilirubin >1.5 to 3 × ULN and any AST), severe hepatic impairment (total bilirubin > 3 × ULN and any AST), CLcr 15 to < 30 mL/min, and end-stage renal disease (CLcr < 15 mL/min) on the pharmacokinetics of vepdegestrant is unknown.
Drug Interaction Studies
Clinical Studies and Model-Informed Approaches
Strong CYP3A Inhibitors : Vepdegestrant AUC increased 1.7-fold and Cmax 1.5-fold following concomitant use of itraconazole (strong CYP3A inhibitor) 200 mg once daily.
Strong CYP3A Inducers: Vepdegestrant AUC decreased to 64% and Cmax to 80% following concomitant use of carbamazepine (strong CYP3A inducer) 200 mg three times daily.
Acid Reducing Agents: Vepdegestrant AUC decreased to 84% and Cmax to 74% following concomitant use of esomeprazole (proton-pump inhibitor) 40 mg once daily.
CYP3A Substrates : Midazolam (CYP3A substrate) AUC increased 1.7-fold and Cmax 1.2-fold following concomitant use of VEPPANU 200 mg once daily.
P-gp Substrates : Dabigatran etexilate (P-gp substrate) AUC increased 2-fold and Cmax 1.9-fold following concomitant use of a single dose of VEPPANU 200 mg.
Breast Cancer Resistance Protein (BCRP) Substrates : Rosuvastatin (BCRP substrate) AUC increased 1.2-fold and Cmax 1.2-fold following concomitant use of a single dose of VEPPANU 200 mg.
UGT1A9 Substrates : Dapagliflozin (UGT1A9 index substrate) AUC is predicted to increase approximately 2-fold following multiple doses of VEPPANU.
In vitro studies:
CYP450 Enzymes: Vepdegestrant does not inhibit CYP1A2, CYP2C8, CYP2C9, CYP2C19 or CYP2D6 and does not induce CYP1A2, CYP2C8, CYP2C9, or CYP2C19.Vepdegestrant is an inhibitor of CYP2B6.
UDP-Glucuronosyltransferases (UGT): Vepdegestrant does not inhibit UGT1A1, UGT1A4, UGT1A6, UGT2B7, or UGT2B15.
Transporter Systems: Vepdegestrant is not a substrate of P-gp, BCRP, OATP1B1, or OATP1B3.
Vepdegestrant does not inhibit MATE1, MATE2-K, OAT1, OAT3, OATP1B1, OATP1B3, or OCT2.
13 NONCLINICAL TOXICOLOGY
13.1 Carcinogenesis, Mutagenesis, Impairment of Fertility
Carcinogenesis
Vepdegestrant was not carcinogenic in a 6-month carcinogenicity study in rasH2 transgenic mice with daily oral administration of vepdegestrant up to 800 mg/kg/day.
Mutagenesis
Vepdegestrant was not mutagenic in an in vitro bacterial reverse mutation assay (Ames) or clastogenic in an in vitro human lymphocyte micronucleus assay or an in vivo rat micronucleus assay.
Impairment of Fertility
Fertility studies with vepdegestrant in animals have not been conducted. In repeat-dose toxicity studies up to 26 weeks duration in rats and 39 weeks duration in dogs, oral administration of vepdegestrant resulted in adverse female reproductive effects including atrophy of the uterus, oviduct, cervix and vagina and follicular cysts in rats at doses ≥30 mg/kg/day (0.3 times the human AUC at the recommended dose) and in dogs at doses ≥10 mg/kg/day (0.4 times the human AUC at the recommended dose). Additional findings in the ovary in rats included decreased corpora lutea and follicle hemorrhage at ≥30 mg/kg/day. Oral administration of vepdegestrant resulted in adverse male reproductive effects including decreased epididymis and prostate weights with decreased secretion and decreased secretion in the seminal vesicle in rats at doses ≥30 mg/kg/day, and seminiferous tubular degeneration, hypoplasia of seminiferous tubules, and epididymal epithelial cell necrosis in dogs at 90 mg/kg/day (approximately 2 times the human AUC at the recommended dose). The effects of vepdegestrant on female reproductive organs were reversible following a 4-week recovery period. The effects on male reproductive organs were not reversible following a 4-week recovery period.
13.2 Animal Toxicology and/or Pharmacology
In a 6-month repeat-dose toxicity study, oral administration of vepdegestrant to rats resulted in granulosa cell hyperplasia in the ovary at 300 mg/kg/day (5 times the human AUC at the recommended dose). In a 9-month repeat-dose toxicity study, oral administration of vepdegestrant to dogs resulted in interstitial cell hypertrophy/hyperplasia in the testis at doses ≥10 mg/kg/day (0.4 times the human AUC at the recommended dose). Reversibility was not assessed.
14 CLINICAL STUDIES
The efficacy of VEPPANU was evaluated in VERITAC-2 (NCT05654623), a randomized, open-label, active-controlled, multicenter trial that enrolled 624 adult patients with ER-positive, HER2-negative, advanced or metastatic breast cancer, of whom 270 patients had tumors carrying ESR1 mutations. Patients were required to have disease progression on 1 to 2 prior lines of endocrine therapy, including 1 line with a CDK4/6 inhibitor. Progression during or within 12 months from the end of adjuvant therapy was counted as 1 line of endocrine therapy for advanced/metastatic setting. Pre-menopausal and peri-menopausal women and men received a gonadotropin-releasing hormone (GnRH) agonist. Patients were excluded if they had received chemotherapy for advanced or metastatic disease or fulvestrant in any line of therapy, or if progression on the most recent line of endocrine therapy occurred within the first 6 months.
Patients were randomized 1:1 to receive VEPPANU 200 mg orally once daily (N=313), or fulvestrant 500 mg intramuscularly on Days 1 and 15 of Cycle 1 and then once monthly thereafter (N=311). Randomization was stratified by ESR1 mutation status (detected vs. not detected) and visceral metastasis (yes vs. no). ESR1 mutational status was determined by blood circulating tumor deoxyribonucleic acid (ctDNA) using central or local testing. Patients were treated until disease progression or unacceptable toxicity.
Among the patients whose tumors had ESR1 mutations (N=270), the median age was 60 (range: 26 to 87) years; all but 1 were female; 47% were White; 41% Asian; 3.3% Black; 8% unknown/not reported; 7% were Hispanic/ Latino, 83% were Not Hispanic or Latino and 10% not reported. Of the 269 women, 20% were pre/perimenopausal. Baseline Eastern Cooperative Oncology Group (ECOG) performance status was 0 (57%) or 1 (43%). Most patients (68%) had visceral disease; 81% had received 1 line of endocrine therapy and 19% had received 2 lines of endocrine therapy in the advanced or metastatic setting. All patients had received prior treatment with a CDK4/6 inhibitor.
The major efficacy outcome was progression-free survival (PFS) as assessed by blinded independent central review (BICR) in the population of patients whose tumors had an ESR1 mutation and in the overall population evaluated according to Response Evaluation Criteria in Solid Tumors (RECIST), version 1.1. Additional efficacy outcomes were overall survival (OS) and objective response rate (ORR) as assessed by BICR.
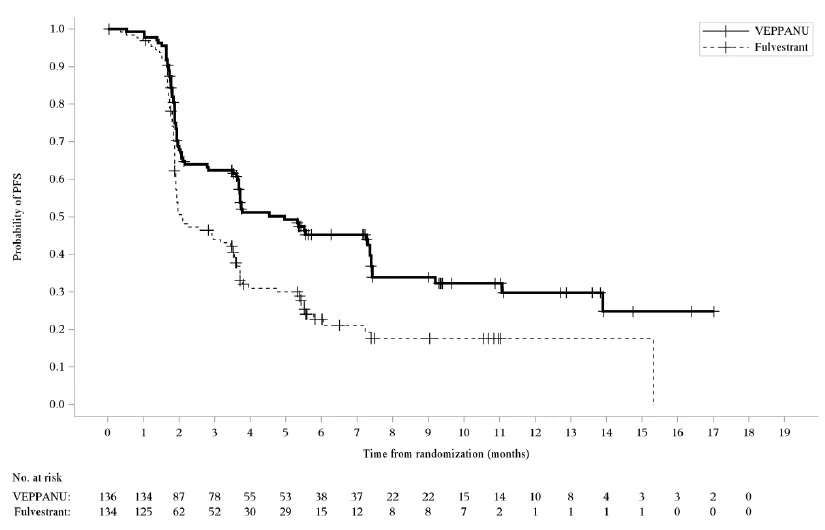
A statistically significant difference in PFS by BICR was observed for the patients whose tumors had ESR1 mutations for VEPPANU compared with fulvestrant.
Overall survival was immature with 16% of deaths in this population at the time of the PFS analysis. Efficacy results are provided in Table 7 and Figure 1.
Table 7: Efficacy Results for VERITAC-2 (Patients with ESR1-Mutated Tumors)
VEPPANU N=136 | Fulvestrant N=134 | |
|---|---|---|
| Abbreviations: CI=Confidence interval; n=number of events; N=number of participants | ||
| Progression-free SurvivalBy blinded independent central review (BICR). | ||
| Number of events (%) | 79 (58) | 95 (71) |
| Median in months (95% CI) | 5.0 (3.7, 7.4) | 2.1 (1.9, 3.5) |
| Hazard ratio (95% CI)Hazard ratio based on stratified Cox proportional hazards model. | 0.57 (0.42, 0.77) | |
| p-value (1-sided)p-value based on stratified log-rank test (compared to a significance level of 0.01875). | 0.0001 | |
| Confirmed Objective Response Rate | ||
| Patients with measurable disease | 97 | 100 |
| ORR (95% CI) | 19% (12, 27) | 4% (1.6, 10) |
| Complete response rate | 0% | 0% |
| Partial response rate | 19% | 4% |
Figure 1: Kaplan-Meier Plot of Progression-Free Survival Based on BICR Assessment in VERITAC-2 (Patients with ESR1-Mutated Tumors)
16 HOW SUPPLIED/STORAGE AND HANDLING
How Supplied
VEPPANU (vepdegestrant) film-coated tablets for oral use are supplied in bottles of 30 tablets with child-resistant closures as follows:
| Strength | Description | NDC Number |
|---|---|---|
| 100 mg | Blue round tablet "VEP" debossed on one side and "100" on the other side. | 71332-007-30 |
| 200 mg | Blue oval tablet "VEP" debossed on one side and "200" on the other side. | 71332-008-30 |
Storage
Store at 20°C to 25°C (68°F to 77°F). Excursions permitted between 15°C and 30°C (between 59°F and 86°F) [see USP controlled room temperature].
17 PATIENT COUNSELING INFORMATION
Advise the patient to read the FDA-approved patient labeling (Patient Information).
QTc Interval Prolongation
Inform patients that VEPPANU can cause QTc interval prolongation, which may increase the risk of Torsade de Pointes, other ventricular arrhythmias, and sudden death. Advise patients or caregivers of the signs or symptoms associated with the clinical consequences of QTc interval prolongation and to seek immediate medical attention if these are suspected or develop. Instruct patients to consult with their healthcare provider prior to taking other drugs that cause QTc interval prolongation with VEPPANU [see Warnings and Precautions (5.1) and Drug Interactions (7.3)] .
Embryo-Fetal Toxicity
Advise pregnant women and females of reproductive potential of the potential risk to a fetus. Advise females to inform their healthcare provider of a known or suspected pregnancy [see Warnings and Precautions (5.2) and Use in Specific Populations (8.1)].
Advise females of reproductive potential to use effective contraception during treatment with VEPPANU and for 2 weeks after the last dose. Advise male patients with female partners of reproductive potential to use effective contraception during treatment with VEPPANU and for 2 weeks after the last dose [see Use in Specific Populations (8.3)].
Lactation
Advise women not to breastfeed during treatment with VEPPANU and for 2 weeks after the last dose [see Use in Specific Populations (8.2)].
Infertility
Advise males and females of reproductive potential that VEPPANU may impair fertility [see Use in Specific Populations (8.3)].
Drug Interactions
Advise patients to inform their healthcare providers of all concomitant medications, including prescription medicines, over-the-counter drugs, vitamins, and herbal products. Inform patients to avoid St. John's wort, grapefruit, or grapefruit juice while taking VEPPANU [see Drug Interactions (7.1, 7.2)].
Administration
Advise patients to take VEPPANU with food, how to make up for a missed or vomited dose, and to swallow tablet(s) whole without chewing, crushing, dissolving or splitting the tablet [see Dosage and Administration (2.2)].
Manufactured by Pfizer Manufacturing Deutschland GmbH, Freiburg, Germany 79108
Manufactured for Rigel Pharmaceuticals, Inc., South San Francisco, CA 94080
VEPPANU is a trademark of Rigel Pharmaceuticals, Inc.
For more information go to www.VEPPANU.com or call 1-800-983-1329
06/2026