


Prescribing information (package insert) - Tolsura
WARNING: CONGESTIVE HEART FAILURE and DRUG INTERACTIONS
Congestive Heart Failure
TOLSURA can cause or exacerbate congestive heart failure (CHF). When itraconazole was administered intravenously to healthy human volunteers and dogs, negative inotropic effects were seen. If signs or symptoms of congestive heart failure occur or worsen during administration of TOLSURA, reassess the benefit and risk of continuing treatment [see Warnings and Precautions (5.1) and Adverse Reactions (6.1)].
Drug Interactions
- Co-administration of certain drugs that are metabolized by human CYP3A4 enzymes are contraindicated with TOLSURA because plasma concentrations of such drugs are increased, which may also increase or prolong both the pharmacologic effects and/or adverse reactions to these drugs [see Contraindications (4.1) and Drug Interactions (7.1)]
- Co-administration with colchicine, fesoterodine and solifenacin is contraindicated in subjects with varying degrees of renal or hepatic impairment, and
- Co-administration with eliglustat is contraindicated in subjects that are poor or intermediate metabolizers of CYP2D6 and in subjects taking strong or moderate CYP2D6 inhibitors.
- Increased plasma concentrations of some of these drugs caused by co-administration with TOLSURA can lead to QT prolongation and/or ventricular tachyarrhythmias, including occurrences of torsades de pointes, a potentially fatal arrhythmia [see Contraindications (4.1), Warnings and Precautions (5.5) and Drug Interactions (7.1)].
1 INDICATIONS AND USAGE
TOLSURA is indicated for the treatment of the following fungal infections in immunocompromised and non-immunocompromised adult patients:
- Blastomycosis, pulmonary and extrapulmonary
- Histoplasmosis, including chronic cavitary pulmonary disease and disseminated, non-meningeal histoplasmosis, and
- Aspergillosis, pulmonary and extrapulmonary, in patients who are intolerant of or who are refractory to amphotericin B therapy.
Specimens for fungal cultures and other relevant laboratory studies (wet mount, histopathology, serology) should be obtained before therapy to isolate and identify causative organisms. Therapy may be instituted before the results of the cultures and other laboratory studies are known; however, once these results become available, anti-fungal therapy should be adjusted accordingly
Limitations of Use:
TOLSURA is not indicated for the treatment of onychomycosis.
TOLSURA is NOT interchangeable or substitutable with other itraconazole products due to the differences in the dosing between TOLSURA and other itraconazole products. Therefore, follow the specific dosage recommendations for TOLSURA [see Dosage and Administration (2)].
2 DOSAGE AND ADMINISTRATION
TOLSURA must be administered with food.
TOLSURA capsules must be swallowed whole. Do not chew, crush or break TOLSURA capsules.
Table 1 below describes the recommended dosage for TOLSURA.
Table 1: Dosage and Administration of TOLSURA
| Indications | Daily Dosing |
|---|---|
| Treatment of Blastomycosis and Histoplasmosis | |
| Recommended dose | 130 mg (2 × 65 mg capsules) once daily If no obvious improvement, or there is evidence of progressive fungal disease, the dose should be increased in 65 mg increments to a maximum of 260 mg/day (130 mg (2 × 65 mg capsules) twice daily). Doses above 130 mg/day should be given in two divided doses. |
| Treatment of Aspergillosis | |
| Recommended dose | 130 mg (2 × 65 mg capsules) once daily |
| 260 mg/day (130 mg (2 × 65 mg capsules) twice daily) | |
| Treatment in Life-Threatening Situations | |
| Although clinical studies did not provide for a loading dose, it is recommended, based on pharmacokinetic data, that a loading dose should be used. | A loading dose of 130 mg (2 × 65 mg capsules) three times daily (390 mg/day) is recommended to be given for the first 3 days, followed by the appropriate recommended dosing based on indication. Treatment should be continued for a minimum of three months and until clinical parameters and laboratory tests indicate that the active fungal infection has subsided. An inadequate period of treatment may lead to recurrence of active infection. |
3 DOSAGE FORMS AND STRENGTHS
TOLSURA (itraconazole capsules) is available in a size 1, hard gelatin capsules with light blue cap and white body, imprinted with "i-65" in black on the cap and containing 65 mg of itraconazole.
4 CONTRAINDICATIONS
4.1 Drug Interactions
- Co-administration of certain drugs that are metabolized by human CYP3A4 substrates are contraindicated with TOLSURA because plasma concentrations of such drugs are increased, which may also increase or prolong both the pharmacologic effects and/or adverse reactions to these drugs [see Warnings and Precaution (5.5) and Drug Interactions (7.1)].
- Co-administration with colchicine, fesoterodine and solifenacin is contraindicated in subjects with varying degrees of renal or hepatic impairment.
- Co-administration with eliglustat is contraindicated in subjects that are poor or intermediate metabolizers of CYP2D6 and in subjects taking strong or moderate CYP2D6 inhibitors [see Drug Interactions (7.1)].
- Increased plasma concentrations of some of these drugs due to co-administration of TOLSURA can lead to QT prolongation and ventricular tachyarrhythmias including occurrences of torsade de pointes, a potentially fatal arrhythmia [see Drug Interactions (7.1)].
4.2 Hypersensitivity
TOLSURA is contraindicated in patients with known hypersensitivity to itraconazole. There is limited information regarding cross-hypersensitivity between itraconazole and other azole antifungal agents [see Warnings and Precautions (5.8)].
5 WARNINGS AND PRECAUTIONS
5.1 Congestive Heart Failure
TOLSURA can cause or exacerbate congestive heart failure (CHF) [see Boxed Warning and Adverse Reactions (6.1)]. For patients with evidence of ventricular dysfunction such as CHF, history or risk factors for CHF, physicians should carefully review the risks and benefits of TOLSURA therapy. These risk factors include cardiac disease such as ischemic and valvular disease; significant pulmonary disease such as chronic obstructive pulmonary disease; and renal failure and other edematous disorders. Inform such patients of the signs and symptoms of CHF and monitor carefully for signs and symptoms of CHF during treatment. If signs or symptoms of CHF appear or worsen during administration of TOLSURA, reassess the benefit-risk of continuing treatment.
When itraconazole was administered intravenously to anesthetized dogs, a dose-related negative inotropic effect was demonstrated. In a healthy volunteer study of itraconazole intravenous infusion, transient, asymptomatic decreases in left ventricular ejection fraction were observed using gated SPECT imaging; these resolved before the next infusion, 12 hours later.
Itraconazole has been associated with reports of CHF, peripheral edema, and pulmonary edema. In post-marketing experience, heart failure was more frequently reported in patients receiving higher total daily doses of itraconazole of 400 mg although there were also cases reported among those receiving lower total daily doses [see Adverse Reactions (6.2)].
Calcium channel blockers can have negative inotropic effects which may be additive to those of itraconazole. In addition, itraconazole can inhibit the metabolism of calcium channel blockers. Therefore, when co-administering itraconazole and calcium channel blockers, monitor carefully for signs and symptoms of CHF during treatment due to an increased risk of CHF. Concomitant administration of TOLSURA and felodipine or nisoldipine is contraindicated [see Contraindications (4.1), Drug Interactions (7.1) and Adverse Reactions (6.2)]
5.2 Hepatotoxicity
Itraconazole has been associated with cases of serious hepatotoxicity, including liver failure and death. Some of these cases had neither pre-existing liver disease nor a serious underlying medical condition, and some of these cases developed within the first week of treatment. If clinical signs or symptoms develop that are consistent with liver disease, discontinue treatment and perform testing for liver disease. Continued TOLSURA use or reinstitution of treatment with TOLSURA is strongly discouraged unless there is a serious or life-threatening situation where the expected benefit exceeds the risk [see Adverse Reactions (6.1)].
5.3 Cardiac Dysrhythmias
Life-threatening cardiac dysrhythmias and/or sudden death have occurred in patients using drugs such as, pimozide, methadone, or quinidine concomitantly with oral itraconazole and/or other CYP3A4 inhibitors. Concomitant administration of these drugs with TOLSURA is contraindicated [see Boxed Warning, Contraindications (4) and Drug Interactions (7)].
5.4 Pseudoaldosteronism
Pseudoaldosteronism, manifested by the onset of hypertension or worsening of hypertension, and abnormal laboratory findings (hypokalemia, low serum renin and aldosterone, and elevate 11-deoxycortisol), has been reported with itraconazole use in the postmarketing setting. Monitor blood pressure and potassium levels and manage as necessary. Management of pseudoaldosteronism may include discontinuation of TOLSURA, substitution with an appropriate antifungal drug that is not associated with pseudoaldosteronism, or use of aldosterone receptor antagonists.
5.5 Drug Interaction Potential
Itraconazole has a potential for clinically important drug interactions [see Drug Interactions (7.1, 7.2)]. Co-administration of specific drugs with TOLSURA may result in changes in the efficacy of itraconazole and/or the co-administered drug, life-threatening effects and/or sudden death. [see Boxed Warning, Contraindications (4.1) and Drug Interactions (7.1, 7.2)].
5.6 Peripheral Neuropathy
Cases of peripheral neuropathy have been reported in patients on long-term therapy with itraconazole. Monitor for and promptly evaluate neurologic symptoms. If neuropathy attributable to TOLSURA occurs, discontinue treatment.
5.7 Hearing Loss
Reversible or permanent hearing loss has been reported in patients receiving treatment with itraconazole. Several of these reports included concurrent administration of quinidine which is contraindicated [see Boxed Warning, Contraindications (4.2) and Drug Interactions (7)]. The hearing loss usually resolves when treatment is stopped but can persist in some patients.
5.8 Hypersensitivity Reactions
TOLSURA is contraindicated in patients with a known hypersensitivity to itraconazole [see Contraindications (4.2)]. Hypersensitivity reactions have been reported with the use of itraconazole [see Adverse Reactions (6.2)]. Due to the limited information regarding cross-hypersensitivity between itraconazole and other azole antifungal drugs, careful enquiry about previous hypersensitivity to other azole antifungal drugs should be made when prescribing TOLSURA. If hypersensitivity reactions to TOLSURA occurs, discontinue the drug and institute appropriate therapy.
6 ADVERSE REACTIONS
The following clinically significant adverse reactions are described elsewhere in the labeling:
- Congestive Heart Failure [see Warnings and Precautions (5.1)]
- Hepatotoxicity [see Warnings and Precautions (5.2)]
- Cardiac Dysrhythmias [see Warnings and Precautions (5.3)]
- Pseudoaldosteronism [see Warnings and Precautions (5.4)]
- Peripheral Neuropathy [see Warnings and Precautions (5.6)]
- Hearing Loss [see Warnings and Precautions (5.7)]
- Hypersensitivity Reactions [see Warnings and Precautions (5.8)]
6.1 Clinical Trials Experience
Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice.
Adverse Reactions in the Treatment of Systemic Fungal Infections
Safety data with itraconazole capsules were derived from 602 patients treated for systemic fungal disease in U.S. clinical trials who were immunocompromised or receiving multiple concomitant medications. Treatment was discontinued in 10.5% of patients due to adverse events. The median duration before discontinuation of therapy was 81 days (range: 2 to 776 days). Table 2 lists adverse reactions reported by at least 1% of patients.
Table 2: Clinical Trials of Systemic Fungal Infections: Adverse Reactions Occurring with an Incidence of ≥1%
| Body System/Adverse Reaction | Incidence (%) (N=602) |
|---|---|
| Gastrointestinal | |
| Nausea | 11 |
| Vomiting | 5 |
| Diarrhea | 3 |
| Abdominal Pain | 2 |
| Anorexia | 1 |
| Body as a Whole | |
| Edema | 4 |
| Fatigue | 3 |
| Fever | 3 |
| Malaise | 1 |
| Skin and Appendages | |
| RashRash tends to occur more frequently in immunocompromised patients receiving immunosuppressive medications. | 9 |
| Pruritus | 3 |
| Central/Peripheral Nervous System | |
| Headache | 4 |
| Dizziness | 2 |
| Psychiatric | |
| Libido Decreased | 1 |
| Somnolence | 1 |
| Cardiovascular | |
| Hypertension | 3 |
| Metabolic/Nutritional | |
| Hypokalemia | 2 |
| Urinary System | |
| Albuminuria | 1 |
| Liver and Biliary System | |
| Hepatic Function Abnormal | 3 |
| Reproductive System, Male | |
| Impotence | 1 |
Adverse reactions reported at a rate of <1% included: constipation, gastritis, depression, insomnia, tinnitus, menstrual disorder, adrenal insufficiency, gynecomastia, and male breast pain.
Adverse Reactions Reported from Other Clinical Trials
In addition, the following adverse reactions were reported in itraconazole-treated patients who participated in clinical trials:
Hepatobiliary Disorders: hyperbilirubinemia;
Cardiac Disorders: cardiac failure, left ventricular failure, tachycardia;
General Disorders and Administration Site Conditions: face edema, chest pain, chills;
Hepatobiliary Disorders: hepatic failure, jaundice;
Investigations: alanine aminotransferase increased, aspartate aminotransferase increased, blood alkaline phosphatase increased, blood lactate dehydrogenase increased, blood urea increased, gammaglutamyltransferase increased, urine analysis abnormal;
Metabolism and Nutrition Disorders: hyperglycemia, hyperkalemia, hypomagnesemia;
Psychiatric Disorders: confusional state;
Renal and Urinary Disorders: renal impairment;
Respiratory, Thoracic and Mediastinal Disorders: dysphonia, cough;
Skin and Subcutaneous Tissue Disorders: hyperhidrosis;
Vascular Disorders: hypotension
6.2 Postmarketing Experience
Adverse reactions that have been identified during post-marketing experience with itraconazole are listed in Table 3. Because these reactions are reported voluntarily from a population of uncertain size, reliably estimating their frequency or establishing a causal relationship to drug exposure is not always possible.
Table 3: Postmarketing Reports of Adverse Drug Reactions
| Blood and Lymphatic System Disorders: | Leukopenia, neutropenia, thrombocytopenia |
| Immune System Disorders: | Anaphylaxis; anaphylactic, anaphylactoid and allergic reactions; serum sickness; angioneurotic edema |
| Endocrine Disorders: | Pseudoaldosteronism |
| Nervous System Disorders: | Peripheral neuropathy, paresthesia, hypoesthesia, tremor |
| Eye Disorders: | Visual disturbances, including blurred vision and diplopia |
| Ear and Labyrinth Disorders: | Transientor permanent hearing loss |
| Respiratory, Thoracic and Mediastinal Disorders: | Pulmonary edema, dyspnea |
| Gastrointestinal Disorders: | Pancreatitis, dysgeusia |
| Hepatobiliary Disorders: | Serious hepatotoxicity (including some cases of fatal acute liver failure), hepatitis |
| Skin and Subcutaneous Tissue Disorders: | Toxic epidermal necrolysis, Stevens-Johnson syndrome, acute generalized exanthematous pustulosis, erythema multiforme, exfoliative dermatitis, leukocytoclastic vasculitis, alopecia, photosensitivity, urticaria |
| Musculoskeletal and Connective Tissue Disorders: | Arthralgia |
| Renal and Urinary Disorders: | Urinary incontinence, pollakiuria |
| Reproductive System and Breast Disorders: | Erectile dysfunction |
| General Disorders and Administration Site Conditions: | Peripheral edema |
| Investigations: | Blood creatine phosphokinase increased |
7 DRUG INTERACTIONS
7.1 Effect of TOLSURA on Other Drugs
Itraconazole and its major metabolite, hydroxy-itraconazole, are potent CYP3A4 inhibitors. Itraconazole is an inhibitor of the drug transporters P-glycoprotein and breast cancer resistance protein (BCRP). Consequently, itraconazole has the potential to interact with many concomitant drugs resulting in either increased or sometimes decreased concentrations of the concomitant drugs. Increased concentrations may increase the risk of adverse reactions associated with the concomitant drug which can be severe or life-threatening in some cases (e.g., QT prolongation, Torsade de Pointes, respiratory depression, hepatic adverse reactions, hypersensitivity reactions, myelosuppression, hypotension, seizures, angioedema, atrial fibrillation, bradycardia, priapism). Reduced concentrations of concomitant drugs may reduce their efficacy. Table 4 lists examples of drugs that may have their concentrations affected by itraconazole, but is not a comprehensive list. Refer to the approved product labeling to become familiar with the interaction pathways, risk potential, and specific actions to be taken with regards to each concomitant drug prior to initiating therapy with itraconazole.
Although many of the clinical drug interactions in Table 4 are based on information with a similar azole antifungal, ketoconazole, these interactions are expected to occur with itraconazole.
Table 4: Drug Interactions with TOLSURA that Affect Concomitant Drug Concentrations
| Concomitant Drug Within Class | Prevention or Management | |
|---|---|---|
| Drug Interactions with TOLSURA that Increase Concomitant Drug Concentrations and May Increase Risk of Adverse Reactions Associated with the Concomitant Drug | ||
| Alpha Blockers | ||
Alfuzosin Silodosin Tamsulosin | Not recommended during and 2 weeks after TOLSURA treatment. | |
| Analgesics | ||
| Methadone | Contraindicated during and 2 weeks after TOLSURA treatment. | |
| Fentanyl | Not recommended during and 2 weeks after TOLSURA treatment. | |
Alfentanil Buprenorphine (IV and sublingual) OxycodoneBased on clinical drug interaction information with itraconazole. Sufentanil | Monitor for adverse reactions. Concomitant drug dose reduction may be necessary. | |
| Antiarrhythmics | ||
Disopyramide Dofetilide Dronedarone Quinidine | Contraindicated during and 2 weeks after TOLSURA treatment. | |
| Digoxin | Monitor for adverse reactions. Concomitant drug dose reduction may be necessary. | |
| Antibacterials | ||
| BedaquilineBased on 400 mg Bedaquiline once daily for 2 weeks. | Concomitant TOLSURA not recommended for more than 2 weeks at any time during bedaquiline treatment. | |
| Rifabutin | Not recommended 2 weeks before, during, and 2 weeks after TOLSURA treatment. See also Table 5. | |
| Clarithromycin | Monitor for adverse reactions. Concomitant drug dose reduction may be necessary. See also Table 5. | |
| Trimetrexate | Monitor for adverse reactions. Concomitant drug dose reduction may be necessary. | |
| Anticoagulants and Antiplatelets | ||
| Ticagrelor | Contraindicated during and 2 weeks after TOLSURA treatment. | |
Apixaban Rivaroxaban Vorapaxar | Not recommended during and 2 weeks after TOLSURA treatment. | |
Cilostazol Dabigatran Warfarin | Monitor for adverse reactions. Concomitant drug dose reduction may be necessary. | |
| Anticonvulsants | ||
| Carbamazepine | Not recommended 2 weeks before, during, and 2 weeks after TOLSURA treatment. See also Table 5. | |
| Antidiabetic Drugs | ||
Repaglinide Saxagliptin | Monitor for adverse reactions. Concomitant drug dose reduction may be necessary. | |
| Antihelminthics, Antifungals and Antiprotozoals | ||
| Isavuconazonium | Contraindicated during and 2 weeks after TOLSURA treatment. | |
| Praziquantel | Monitor for adverse reactions. Concomitant drug dose reduction may be necessary. | |
Artemether-lumefantrine Quinine | Monitor for adverse reactions. | |
| Antimigraine Drugs | ||
| Ergot alkaloids (e.g., dihydroergotamine, ergotamine) | Contraindicated during and 2 weeks after TOLSURA treatment. | |
| Eletriptan | Monitor for adverse reactions. Concomitant drug dose reduction may be necessary | |
| Antineoplastics | ||
| Irinotecan | Contraindicated during and 2 weeks after TOLSURA treatment. | |
Axitinib Bosutinib Cabazitaxel Cabozantinib Ceritinib Cobimetinib Crizotinib Dabrafenib Dasatinib | Docetaxel Ibrutinib Lapatinib Nilotinib Olaparib Pazopanib Sunitinib Trabectedin Trastuzumab-emtansine Vinca alkaloids | Not recommended during and 2 weeks after TOLSURA treatment. |
Bortezomib Brentuximab-vedotin Busulfan Erlotinib Gefitinib Idelalisib Imatinib Ixabepilone | Nintedanib Panobinostat Ponatinib Ruxolitinib Sonidegib Vandetanib | Monitor for adverse reactions. Concomitant drug dose reduction may be necessary. For Idelalisib, see also Table 5. |
| Antipsychotics, Anxiolytics and Hypnotics | ||
Alprazolam Aripiprazole Buspirone Diazepam Haloperidol | Midazolam (IV) Quetiapine Ramelteon Risperidone Suvorexant | Monitor for adverse reactions. Concomitant drug dose reduction may be necessary. |
| Zopiclone | Monitor for adverse reactions. Concomitant drug dose reduction may be necessary. | |
Lurasidone Midazolam (oral) Pimozide Triazolam | Contraindicated during and 2 weeks after TOLSURA treatment. | |
| Antivirals | ||
| Simeprevir | Not recommended during and 2 weeks after TOLSURA treatment. | |
Daclatasvir Indinavir Maraviroc | Monitor for adverse reactions. Concomitant drug dose reduction may be necessary. For indinavir, see also Table 5. | |
Cobicistat Elvitegravir (ritonavir-boosted) Ritonavir Saquinavir (unboosted) | Monitor for adverse reactions. See also Table 5. | |
| Tenofovir disoproxil fumarate | Monitor for adverse reactions. | |
| Beta Blockers | ||
| Nadolol | Monitor for adverse reactions. Concomitant drug dose reduction may be necessary. | |
| Calcium Channel Blockers | ||
Felodipine Nisoldipine | Contraindicated during and 2 weeks after TOLSURA treatment. | |
Diltiazem Other dihydropyridines Verapamil | Monitor for adverse reactions. Concomitant drug dose reduction may be necessary. For diltiazem, see also Table 5. | |
| Cardiovascular Drugs, Miscellaneous | ||
Ivabradine Ranolazine | Contraindicated during and 2 weeks after TOLSURA treatment. | |
Aliskiren Riociguat Sildenafil (for pulmonary hypertension) Tadalafil (for pulmonary hypertension) | Not recommended during and 2 weeks after TOLSURA treatment. For sildenafil and tadalafil, see also Urologic Drugs below. | |
Bosentan Guanfacine | Monitor for adverse reactions. Concomitant drug dose reduction may be necessary. | |
| Contraceptives | ||
Dienogest Ulipristal | Monitor for adverse reactions. | |
| Diuretics | ||
| Eplerenone | Contraindicated during and 2 weeks after TOLSURA treatment. | |
| Gastrointestinal Drugs | ||
| Naloxegol | Contraindicated during and 2 weeks after TOLSURA treatment. | |
Aprepitant Loperamide | Monitor for adverse reactions. Concomitant drug dose reduction may be necessary. | |
| Netupitant | Monitor for adverse reactions. | |
| Immunosuppressants | ||
Everolimus Sirolimus Temsirolimus (IV) | Not recommended during and 2 weeks after TOLSURA treatment. | |
Budesonide (inhalation) Budesonide (noninhalation) Ciclesonide (inhalation) Cyclosporine (IV) Cyclosporine (non-IV) Dexamethasone | Fluticasone (inhalation) Fluticasone (nasal) Methylprednisolone Tacrolimus (IV) Tacrolimus (oral) | Monitor for adverse reactions. Concomitant drug dose reduction may be necessary. |
| Lipid-Lowering Drugs | ||
Lomitapide Lovastatin Simvastatin | Contraindicated during and 2 weeks after TOLSURA treatment. | |
| Atorvastatin | Monitor for drug adverse reactions. Concomitant drug dose reduction may be necessary. | |
| Respiratory Drugs | ||
| Salmeterol | Not recommended during and 2 weeks after TOLSURA treatment. | |
| SSRIs, Tricyclics and Related Antidepressants | ||
| Venlafaxine | Monitor for adverse reactions. Concomitant drug dose reduction may be necessary. | |
| Urologic Drugs | ||
| Avanafil | Contraindicated during and 2 weeks after TOLSURA treatment. | |
| Fesoterodine | Patients with moderate to severe renal or hepatic impairment: Contraindicated during and 2 weeks after TOLSURA treatment. Other patients: Monitor for adverse reactions. Concomitant drug dose reduction may be necessary | |
| Solifenacin | Patients with severe renal or moderate to severe hepatic impairment: Contraindicated during and 2 weeks after TOLSURA treatment. Other patients: Monitor for adverse reactions. Concomitant drug dose reduction may be necessary. | |
Darifenacin Vardenafil | Not recommended during and 2 weeks after TOLSURA treatment. | |
Dutasteride Oxybutynin Sildenafil (for erectile dysfunction) Tadalafil (for erectile dysfunction and benign prostatic hyperplasia) Tolterodine | Monitor for adverse reactions. Concomitant drug dose reduction may be necessary. For sildenafil and tadalafil, see also Cardiovascular Drugs above. | |
| Miscellaneous Drugs and Other Substances | ||
| Colchicine | Patients with renal or hepatic impairment: Contraindicated during and 2 weeks after TOLSURA treatment. Other patients: Not recommended during and 2 weeks after TOLSURA treatment. | |
| Eliglustat | CYP2D6 EMsEMs: extensive metabolizers; IMs: intermediate metabolizers, PMs: poor metabolizers.taking a strong or moderate CYP2D6 inhibitor, CYP2D6 IMs, or CYP2D6 PMs : Contraindicated during and 2 weeks after TOLSURA treatment. CYP2D6 EMsnot taking a strong or moderate CYP2D6 inhibitor: Monitor for adverse reactions. Eliglustat dose reduction may be necessary. | |
| Lumacaftor/Ivacaftor | Not recommended 2 weeks before, during, and 2 weeks after TOLSURA treatment. | |
Alitretinoin (oral) Cabergoline Cannabinoids Cinacalcet Ivacaftor | Monitor for adverse reactions. Concomitant drug dose reduction may be necessary. | |
| Vasopressin Receptor Antagonists | ||
Conivaptan Tolvaptan | Not recommended during and 2 weeks after TOLSURA treatment. | |
| Drug Interactions with TOLSURA that Decrease Concomitant Drug Concentrations and May Reduce Efficacy of the Concomitant Drug | ||
| Antineoplastics | ||
| Regorafenib | Not recommended during and 2 weeks after TOLSURA treatment. | |
| Gastrointestinal Drugs | ||
| Saccharomyces boulardii | Not recommended during and 2 weeks after TOLSURA treatment. | |
| Nonsteroidal Anti-Inflammatory Drugs | ||
| Meloxicam | Concomitant drug dose increase may be necessary. | |
7.2 Effect of Other Drugs on TOLSURA
Itraconazole is mainly metabolized through CYP3A4. Other substances that either share this metabolic pathway or modify CYP3A4 activity may influence the pharmacokinetics of itraconazole. Some concomitant drugs have the potential to interact with TOLSURA resulting in either increased or sometimes decreased concentrations of TOLSURA. Increased concentrations may increase the risk of adverse reactions associated with TOLSURA. Decreased concentrations may reduce TOLSURA efficacy.
Table 4 lists examples of drugs that may affect itraconazole concentrations, but is not a comprehensive list. Refer to the approved product labeling to become familiar with the interaction pathways, risk potential and specific actions to be taken with regards to each concomitant drug prior to initiating therapy with TOLSURA.
Although many of the clinical drug interactions in Table 5 are based on information with a similar azole antifungal, ketoconazole, these interactions are expected to occur with TOLSURA.
Table 5: Drug Interactions with Other Drugs that Affect TOLSURA Concentrations
| Concomitant Drug Within Class | Prevention or Management |
|---|---|
| Drug Interactions with Other Drugs that Increase TOLSURA Concentrations and May Increase Risk of Adverse Reactions Associated with TOLSURA | |
| Antibacterials | |
CiprofloxacinBased on clinical drug interaction information with itraconazole. Erythromycin Clarithromycin | Monitor for adverse reactions. TOLSURA dose reduction may be necessary. |
| Antineoplastics | |
| Idelalisib | Monitor for adverse reactions. TOLSURA dose reduction may be necessary. See also Table 4. |
| Antivirals | |
Cobicistat Darunavir (ritonavir-boosted) Elvitegravir (ritonavir-boosted) Fosamprenavir (ritonavir-boosted) Indinavir Ritonavir Saquinavir | Monitor for adverse reactions. TOLSURA dose reduction may be necessary. For, cobicistat, elvitegravir, indinavir, ritonavir, and saquinavir, see also Table 4. |
| Calcium Channel Blockers | |
| Diltiazem | Monitor for adverse reactions. TOLSURA dose reduction may be necessary. See also Table 4. |
| Gastrointestinal Drugs | |
| Drugs that reduce gastric acidity e.g. acid neutralizing medicines such as aluminum hydroxide, or acid secretion suppressors such as H2- receptor antagonists and proton pump inhibitors (e.g., omeprazole). | Co-administration of these drugs, including omeprazole, with TOLSURA increases the systemic exposure to itraconazole. Monitor for adverse reactions. TOLSURA dose reduction may be necessary [see Clinical Pharmacology (12.3)]. |
| Drug Interactions with Other Drugs that Decrease TOLSURA Concentrations and May Reduce Efficacy of TOLSURA | |
| Antibacterials | |
Isoniazid Rifampicin | Not recommended 2 weeks before and during TOLSURA treatment. |
| Rifabutin | Not recommended 2 weeks before, during, and 2 weeks after TOLSURA treatment. See also Table 4. |
| Anticonvulsants | |
Phenobarbital Phenytoin | Not recommended 2 weeks before and during TOLSURA treatment. |
| Carbamazepine | Not recommended 2 weeks before, during, and 2 weeks after TOLSURA treatment. See also Table 4. |
| Antivirals | |
Efavirenz Nevirapine | Not recommended 2 weeks before and during TOLSURA treatment. |
| Miscellaneous Drugs and Other Substances | |
| Lumacaftor/Ivacaftor | Not recommended 2 weeks before, during, and 2 weeks after TOLSURA treatment. |
8 USE IN SPECIFIC POPULATIONS
8.1 Pregnancy
Risk Summary
There are no data on exposure to itraconazole during pregnancy for the approved indications. Published epidemiologic studies of women exposed to short courses of treatment with itraconazole in the first trimester of pregnancy have reported no risk of major birth defects overall and inconclusive findings on the risk of miscarriage (see Data).
In animal reproduction studies, itraconazole was found to cause a dose-related increase in maternal toxicity, embryotoxicity, and teratogenicity in rats at dosage levels of approximately (6-25 times the maximum recommended human dose [MRHD] of 390 mg/day based on mg/kg comparisons), and in mice at dosage levels of approximately 80 mg/kg/day (12 times the MRHD).
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. The estimated background risk of major birth defects and miscarriage for the indicated populations is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Data
Human Data
Published prospective and retrospective cohort studies of women exposed to short courses of treatment with itraconazole in the first trimester of pregnancy (sample size 198-687) have reported no increase in the rate of major birth defects. The most important methodological limitation of these studies is the short duration of exposure in pregnancy (mean duration 6.9 to 8.5 days), or the lack of information on treatment duration. The risk of prolonged exposure in pregnancy is not known.
Published prospective and retrospective cohort studies of pregnant women exposed to itraconazole (sample size 131-198) have reported inconsistent findings on the risk of miscarriage. Available data are inconclusive and limited by possible bias due to earlier enrollment and possible residual confounding in the exposed group compared to the unexposed group.
Animal Data
Itraconazole has been shown to cross the placenta in a rat model. In animal reproduction studies, itraconazole administration to rats and mice during organogenesis resulted in maternal toxicity, embryotoxicity and teratogenicity at and above 40 and 80 mg/kg respectively (doses equivalent to 6- and 12-times the MRHD of 390 mg/day, based on mg/kg comparisons). In rats, the teratogenicity consisted of major skeletal defects; in mice, it consisted of encephaloceles and/or macroglossia.
8.2 Lactation
Risk Summary
Itraconazole is excreted in human milk; however, there are no data on the amount of itraconazole in human milk, the effects on the breastfed child, or the effects on milk production. The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for TOLSURA and any potential adverse effects on the breastfed child from TOLSURA or from the underlying maternal condition.
8.4 Pediatric Use
Safety and effectiveness in pediatric patients have not been established.
The long-term effects of itraconazole on bone growth in children are unknown. Bone lesions were observed in the young adult rats dosed with oral itraconazole for 3 to 12 months [see Nonclinical Toxicology (13.2)].
8.5 Geriatric Use
Clinical studies of itraconazole did not include sufficient numbers of subjects aged 65 years and over to determine whether they respond differently from younger subjects. It is advised to use TOLSURA Capsules in these patients only if it is determined that the potential benefit outweighs the potential risks. In general, it is recommended that the dose selection for an elderly patient should be taken into consideration, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
Reversible or permanent hearing loss has been reported in elderly patients receiving treatment with itraconazole. Several of these reports included concurrent administration of quinidine which is contraindicated [see Boxed Warning, Contraindications (4.1) and Drug Interactions (7.1)].
8.6 Renal Impairment
Limited data are available on the use of oral itraconazole in patients with renal impairment. It is recommended that patients with renal impairment be carefully monitored when taking TOLSURA [see Clinical Pharmacology (12) and Warnings and Precautions (5.1)].
8.7 Hepatic Impairment
Limited data are available on the use of oral itraconazole in patients with hepatic impairment. It is recommended that patients with impaired hepatic function be carefully monitored when taking TOLSURA. It is recommended that the prolonged elimination half-life of itraconazole observed in the single oral dose clinical trial with itraconazole capsules in cirrhotic patients be considered when deciding to initiate therapy with other medications metabolized by CYP3A4 [see Clinical Pharmacology (12.3)].
In patients with elevated or abnormal liver enzymes or active liver disease, or who have experienced liver toxicity with other drugs, treatment with TOLSURA is strongly discouraged unless there is a serious or life-threatening situation where the expected benefit exceeds the risk. It is recommended that liver function monitoring be done in patients with pre-existing hepatic function abnormalities or those who have experienced liver toxicity with other medications [see Clinical Pharmacology (12) and Warnings and Precautions (5.2)].
10 OVERDOSAGE
Itraconazole is not removed by dialysis. In the event of accidental overdosage, supportive measures should be employed. Activated charcoal may be given if considered appropriate.
11 DESCRIPTION
TOLSURA (itraconazole capsules) is an azole antifungal drug for oral use. Itraconazole is an equal mixture of four diastereomers (two enantiomeric pairs), each possessing three chiral centers. It may be represented by the following structural formula and nomenclature:
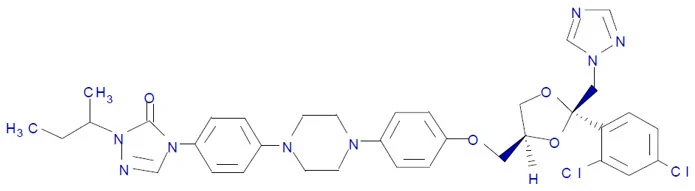 |
(±)-1-[(R*)-sec-butyl]-4-[p-[4-[p-[[(2R*,4S*)-2-(2,4-dichlorophenyl)-2-(1H-1,2,4-triazol-1-ylmethyl)-1,3-dioxolan-4-yl]methoxy]phenyl]-1-piperazinyl]phenyl]-Δ2-1,2,4-triazolin-5-one mixture with (±)-1-[(R*)-sec-butyl]-4-[p-[4-[p-[[(2S*,4R*)-2-(2,4-dichlorophenyl)-2-(1H-1,2,4-triazol-1-ylmethyl)-1,3-dioxolan-4-yl]methoxy]phenyl]-1-piperazinyl]phenyl]-Δ2-1,2,4-triazolin-5-one
or
(±)-1-[(RS)-sec-butyl]-4-[p-[4-[p-[[(2R,4S)-2-(2,4-dichlorophenyl)-2-(1H-1,2,4-triazol-1-ylmethyl)-1,3-dioxolan-4-yl]methoxy]phenyl]-1-piperazinyl]phenyl]-Δ2-1,2,4-triazolin-5-one.
Itraconazole has a molecular formula of C35H38Cl2N8O4 and a molecular weight of 705.64. It is a white to slightly yellowish powder. It is insoluble in water, very slightly soluble in alcohols, and freely soluble in dichloromethane. It has a pKa of 3.70 (based on extrapolation of values obtained from methanolic solutions) and a log (n-octanol/water) partition coefficient of 5.66 at pH 8.1.
Each TOLSURA capsule contains 65 mg of itraconazole dispersed in a polymer matrix and encapsulated in a hard gelatin capsule. The inactive ingredients are colloidal silicon dioxide, hypromellose phthalate, magnesium stearate and sodium starch glycolate.
12 CLINICAL PHARMACOLOGY
12.1 Mechanism of Action
Itraconazole is an azole antifungal drug [see Microbiology (12.4)].
12.3 Pharmacokinetics
General Pharmacokinetic Characteristics
The steady-state pharmacokinetics of itraconazole following administration of a 130 mg twice daily dose regimen of TOLSURA (2 × 65 mg) was compared with a 200 mg twice daily dose regimen of itraconazole capsules (2 × 100 mg) immediately after a meal for 14.5 days in 16 healthy volunteers; the results from this study are presented in Table 6 below
Table 6: Pharmacokinetics of Itraconazole Following Administration of TOLSURA and Itraconazole Capsules Given Twice Daily for 14.5 Days Under Fed ConditionsStandardized high-fat, high-calorie breakfast was given 30 minutes prior to dosing on the morning of Day 15; standardized meals given prior to all other doses. in 16 Healthy Subjects
| ParameterGeometric means ± standard deviation , Tmax presented as median (range) | TOLSURA 130 mg twice daily (2 × 65 mg Capsules) | Itraconazole 200 mg twice daily (2 × 100 mg Capsules) |
|---|---|---|
AUC0-tau (hr*mcg/ml) | 15.6 ± 3.7 | 14.9 ±3.8 |
Ctrough (mcg/ml) | 1.2 ±0.4 | 1.0±0.3 |
Cmax,ss (mcg/ml) | 1.6 ±0.4 | 1.5 ±0.4 |
Tmax,ss (h) | 7.0 (1-10) | 5.0 (1-8) |
Peak plasma concentrations of itraconazole after administration of a single dose of TOLSURA are reached within 2 to 6 hours following oral administration in either the fasted or fed states. As a consequence of non-linear pharmacokinetics, itraconazole accumulates in plasma during multiple dosing of TOLSURA. Steady-state concentrations are generally reached within about 15 days, with mean Cmax values of 0.6 mcg/ml and 1.7 mcg/ml after oral administration of 130 mg once daily and 130 mg twice daily, respectively
Absorption
Effect of Food
The effect of food on the steady-state pharmacokinetics of itraconazole following administration of a 130 mg twice daily dose regimen of TOLSURA (2 × 65 mg) for 14.5 days under fed and fasted conditions was evaluated in 20 healthy volunteers. A high-fat meal with total caloric content of 919 calories (526 fat calories, 260 carbohydrate calories and 133 protein calories) was used in the study. The results are shown in Table 7 below.
Table 7: Pharmacokinetic Parameters of Itraconazole Following Administration of TOLSURA 130 mg (2 × 65 mg capsules) Given Twice Daily for 14.5 Days Under Fed and Fasted Conditions in 20 Healthy Subjects
| Parameter | Treatment | Geometric Mean | Fed/Fasted Ratio (%) | 90% Confidence Interval |
Cmax_ss (mcg/mL) | Fed | 1.4 ± 0.6 | 73.7 | 69.0, 77.3 |
| Fasted | 1.9 ± 0.9 | |||
Ctrough,ss (mcg/mL) | Fed | 1.0 ± 0.3 | 90.0 | 86.4, 97.0 |
| Fasted | 1.1 ± 0.6 | |||
AUCtau (hr*mcg/mL) | Fed | 13.4 ± 5.0 | 78.4 | 74.5, 81.9 |
| Fasted | 17.1 ± 8.0 | |||
| Median | Range | |||
Tmax (hr) | Fed | 4.00 | 0.5 to 10 | |
| Fasted | 3.50 | 0.5 to 5 | ||
Distribution
Most of the itraconazole in plasma is bound to protein (99.8%), with albumin being the main binding component (99.6% for the hydroxy-metabolite). It has also a marked affinity for lipids. Only 0.2% of the itraconazole in plasma is present as free drug. Itraconazole is distributed in a large apparent volume in the body (>700 L), suggesting extensive distribution into tissues. Concentrations in lung, kidney, liver, bone, stomach, spleen and muscle were found to be two to three times higher than corresponding concentrations in plasma, and the uptake into keratinous tissues, skin in particular, up to four times higher. Concentrations in the cerebrospinal fluid are much lower than in plasma.
Elimination
The terminal half-life of itraconazole following repeated dose administration of TOLSURA ranges between 34 to 42 hours under fed conditions.
Metabolism
Itraconazole is extensively metabolized by the liver into a large number of metabolites. In vitro studies have shown that CYP3A4 is the major enzyme involved in the metabolism of itraconazole. The main metabolite is hydroxy-itraconazole, which has in vitro antifungal activity comparable to itraconazole; trough plasma concentrations of this metabolite are about twice those of itraconazole.
Excretion
Itraconazole is excreted mainly as inactive metabolites in urine (35%) and in feces (54%) within one week of an oral solution dose. Renal excretion of itraconazole and the active metabolite hydroxyitraconazole account for less than 1% of an intravenous dose. Based on an oral radiolabeled dose, fecal excretion of unchanged drug ranges from 3% to 18% of the dose.
As re-distribution of itraconazole from keratinous tissues appears to be negligible, elimination of itraconazole from these tissues is related to epidermal regeneration. Contrary to plasma, the concentration in skin persists for 2 to 4 weeks after discontinuation of a 4-week treatment and in nail keratin - where itraconazole can be detected as early as 1 week after start of treatment - for at least six months after the end of a 3-month treatment period.
Specific Populations
Patients with Renal Impairment
Limited data are available on the use of oral itraconazole in patients with renal impairment. A pharmacokinetic study using a single 200-mg oral dose of itraconazole was conducted in three groups of patients with renal impairment (uremia: n=7; hemodialysis: n=7; and continuous ambulatory peritoneal dialysis: n=5). In uremic subjects with a mean creatinine clearance of 13 mL/min. × 1.73 m2, the exposure, based on AUC, was slightly reduced compared with normal population parameters. This study did not demonstrate any significant effect of hemodialysis or continuous ambulatory peritoneal dialysis on the pharmacokinetics of itraconazole (tmax, Cmax, and AUC0-8h). Plasma concentration versus-time profiles showed wide intersubject variation in all three groups. After a single intravenous versus-time profiles showed wide intersubject variation in all three groups.
After a single intravenous dose, the mean terminal half-lives of itraconazole in patients with mild (defined in this study as CrCl 50-79 ml/min), moderate (defined in this study as CrCl 20-49 ml/min), and severe renal impairment (defined in this study as CrCl <20 ml/min) were similar to that in healthy subjects (range of means 42-49 hours vs 48 hours in renally impaired patients and healthy subjects, respectively). Overall exposure to itraconazole, based on AUC, was decreased in patients with moderate and severe renal impairment by approximately 30% and 40%, respectively, as compared with subjects with normal renal function. Data are not available in renally impaired patients during long-term use of itraconazole. Dialysis has no effect on the half-life or clearance of itraconazole or hydroxy-itraconazole.
Patients with Hepatic Impairment
Itraconazole is predominantly metabolized in the liver. A pharmacokinetic study was conducted in 6 healthy and 12 cirrhotic subjects who were administered a single 100-mg dose of itraconazole capsules. A statistically significant reduction in mean Cmax (47%) and a twofold increase in the elimination half-life (37 ± 17 hours vs. 16 ± 5 hours) of itraconazole were noted in cirrhotic subjects compared with healthy subjects. However, overall exposure to itraconazole, based on AUC, was similar in cirrhotic patients and in healthy subjects. Data are not available in cirrhotic patients during long-term use of itraconazole.
Drug Interaction Studies
Omeprazole
The effect of multiple daily oral 40 mg doses (steady-state conditions) of the proton pump inhibitor, omeprazole, on the exposure to itraconazole from a single 130 mg dose of TOLSURA (2 × 65 mg capsules) when dosed under fasted conditions was evaluated in 30 healthy adult subjects. As illustrated in Table 8 below, the mean itraconazole AUC∞ was 22% higher and mean Cmax 31% higher when TOLSURA was co-administered with omeprazole.
Table 8: Pharmacokinetics of Itraconazole Following Single Dose Administration of TOLSURA 130 mg (2 × 65mg capsules) Alone or with Omeprazole 40 mg QD Administered for 7 Days Under Fasted Conditions in Healthy Volunteers
| Parameter | Treatment ATreatment A: TOLSURA Mean ±SD | Treatment A + BTreatment B: Omeprazole Mean ±SD | Treatment A+B vs Treatment A Ratio % | 90% Confidence Interval |
|---|---|---|---|---|
AUC∞ (h∙ng/mL) | 2846.3 ±1644.4 | 3477.9 ± 1572.6 | 122.2 | 108.7, 137.3 |
Cmax (ng/mL) | 212.9 ± 119.1 | 278.8 ±106.8 | 130.9 | 111.4, 153.8 |
Tmax Tmax is given as median (Range) (h) | 3.5 (2.0 -5.0) | 3.3 (1.5 – 5.0) | - | - |
12.4 Microbiology
Mechanism of Action
In vitro studies have demonstrated that itraconazole inhibits the cytochrome P450-dependent, 14C-demethylation of ergosterol, which is a vital component of fungal cell membranes.
Resistance
Isolates from several fungal species with decreased susceptibility to itraconazole have been isolated in vitro and from patients receiving prolonged therapy. Several in vitro studies have reported that some fungal clinical isolates with reduced susceptibility to one azole antifungal agent may also be less susceptible to other azole derivatives. The finding of cross-resistance is dependent on a number of factors, including the species evaluated, its clinical history, the particular azole compounds compared, and the type of susceptibility test performed.
Itraconazole is not active against Zygomycetes (e.g., Rhizopus spp., Rhizomucor spp., Mucor spp. and Absidia spp.), Fusarium spp., Scedosporium spp. and Scopulariopsis spp.
Interaction with Other Antimicrobials
Studies (both in vitro and in vivo) suggest that the activity of amphotericin B may be suppressed by prior azole antifungal therapy. Ergosterol is the active site for amphotericin B. In one study, the antifungal activity of amphotericin B against Aspergillus fumigatus infections in mice was inhibited by ketoconazole therapy. The clinical significance of this finding is unknown.
Antifungal Activity
Itraconazole exhibits in vitro activity against Blastomyces dermatitidis, Histoplasma capsulatum, Histoplasma duboisii, Aspergillus flavus, Aspergillus fumigatus, and Trichophyton species [see Indications and Usage (1)]. Correlation between minimum inhibitory concentration (MIC) results in vitro and clinical outcome has yet to be established for azole antifungal agents.
13 NONCLINICAL TOXICOLOGY
13.1 Carcinogenesis, Mutagenesis, Impairment of Fertility
Carcinogenesis
Itraconazole showed no evidence of carcinogenicity potential in mice treated orally for 23 months at dosage levels up to 80 mg/kg/day (approximately 12×MRHD, based on mg/kg comparisons). Male rats treated with 25 mg/kg/day (4×MRHD) had a slightly increased incidence of soft tissue sarcoma. These sarcomas may have been a consequence of hypercholesterolemia, which is a response of rats, but not dogs or humans, to chronic itraconazole administration. Female rats treated with 50 mg/kg/day (8×MRHD) had an increased incidence of squamous cell carcinoma of the lung (2/50) as compared to the untreated group. Although the occurrence of squamous cell carcinoma in the lung is extremely uncommon in untreated rats, the increase in this study was not statistically significant.
Mutagenesis
Itraconazole produced no mutagenic effects when assayed in DNA repair test (unscheduled DNA synthesis) in primary rat hepatocytes, in Ames tests with Salmonella typhimurium (6 strains) and Escherichia coli, in the mouse lymphoma gene mutation tests, in a sex-linked recessive lethal mutation (Drosophila melanogaster) test, in chromosome aberration tests in human lymphocytes, in a cell transformation test with C3H/10T½ C18 mouse embryo fibroblasts cells, in a dominant lethal mutation test in male and female mice, and in micronucleus tests in mice and rats.
Impairment of Fertility
Itraconazole did not affect the fertility of male or female rats treated orally with dosage levels of up to 40 mg/kg/day (6×MRHD, based on mg/kg comparisons), even though parental toxicity was present at this dosage level.
13.2 Animal Toxicology and/or Pharmacology
When itraconazole was administered intravenously to anesthetized dogs, a dose-related negative inotropic effect was documented.
In three toxicology studies using rats, itraconazole (dosed in feed or via oral gavage) induced bone defects at dosage levels as low as 20 mg/kg/day (3×MRHD, based on mg/kg comparisons). The induced defects included reduced bone plate activity, thinning of the zona compacta of the large bones, and increased bone fragility. At a dosage level of 80 mg/kg/day (12×MRHD) over 1 year or 160 mg/kg/day (25×MRHD) for 6 months, itraconazole induced small tooth pulp with hypocellular appearance in some rats.
14 CLINICAL STUDIES
Overview of the Clinical Studies
Clinical studies in invasive mycoses listed in this section were conducted with itraconazole 100 mg capsules. Dosage for TOLSURA is different from that of other itraconazole formulations. TOLSURA is not interchangeable or substitutable with other itraconazole products [see Indications and Usage (1), Dosage and Administration (2) and Clinical Pharmacology (12.3)]
14.1 Blastomycosis
Analyses were conducted on data from two open-label, non-concurrently controlled studies (N=73 combined) in patients with normal or abnormal immune status treated with the100 mg itraconazole capsules. The median dose was 200 mg/day (2 × 100 mg). A response for most signs and symptoms was observed within the first 2 weeks, and all signs and symptoms cleared between 3 and 6 months. Results of these two studies demonstrated substantial evidence of the effectiveness of itraconazole for the treatment of blastomycosis compared with the natural history of untreated cases.
14.2 Histoplasmosis
Analyses were conducted on data from two open-label, non-concurrently controlled studies (N=34 combined) in patients with normal or abnormal immune status (not including HIV-infected patients) treated with the 100 mg itraconazole capsules. The median dose was 200 mg/day (2 × 100 mg). A response for most signs and symptoms was observed within the first 2 weeks, and all signs and symptoms cleared between 3 and 12 months. Results of these two studies demonstrated substantial evidence of the effectiveness of itraconazole for the treatment of histoplasmosis, compared with the natural history of untreated cases.
14.3 Histoplasmosis in HIV-infected Patients
Data from a small number of HIV-infected patients treated with the 100 mg itraconazole capsules suggested that the response rate of histoplasmosis in HIV-infected patients is similar to that of non-HIV-infected patients. The clinical course of histoplasmosis in HIV-infected patients is more severe and usually requires maintenance therapy to prevent relapse.
14.4 Aspergillosis
Analyses were conducted on data from an open-label, "single-patient-use" protocol designed to make itraconazole available in the U.S. for patients who either failed or were intolerant of amphotericin B therapy (N=190). The findings were corroborated by two smaller open-label studies (N=31 combined) in the same patient population. Most adult patients were treated with a daily dose of 200 (2 × 100 mg) to 400 (4 × 100 mg) mg, with a median duration of 3 months. Results of these studies demonstrated substantial evidence of effectiveness of the 100 mg itraconazole capsules as a second-line therapy for the treatment of aspergillosis compared with the natural history of the disease in patients who either failed or were intolerant of amphotericin B therapy.
16 HOW SUPPLIED/STORAGE AND HANDLING
TOLSURA (itraconazole capsules) is supplied in a size 1, hard gelatin capsules with light blue cap and white body, imprinted with "i-65" in black on the cap and containing 65 mg of itraconazole.
TOLSURA capsules are supplied as follows:
| Bottles of 8 capsules | Bottles of 60 capsules |
| NDC 51862-462-88 | NDC 51862-462-60 |
Store at 25°C (77°F); excursions permitted 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature]. Dispense in a tight, light resistant container.
17 PATIENT COUNSELING INFORMATION
Advise the patient to read the FDA-approved patient labeling (Patient Information).
Important Administration Instructions
Instruct the patients that TOLSURA:
- Cannot be interchanged or substituted with other itraconazole products.
- Must be swallowed whole and administered with food.
Congestive Heart Failure
Inform patients about the signs and symptoms of congestive heart failure. Instruct them to discontinue TOLSURA and contact their healthcare provider immediately, if these signs or symptoms occur during TOLSURA administration [see Warnings and Precautions (5.1)].
Hepatoxicity
Instruct patients to stop TOLSURA treatment immediately and contact their healthcare provider if any signs and symptoms suggestive of liver dysfunction develop. Such signs and symptoms may include unusual fatigue, anorexia, nausea and/or vomiting, jaundice, dark urine, or pale stools [see Warnings and Precautions (5.2)].
Use with Proton Pump Inhibitors and Potential Drug Interactions
Advise patients to discuss with their physician the use of TOLSURA with proton pump inhibitors, such as omeprazole. Instruct patients to contact their physician before taking any other concomitant medications with TOLSURA to ensure there are no potential drug interactions [see Contraindications (4.1, 4.2), Warnings and Precautions (5.5) and Drug interactions (7.2)].
Hearing Loss
Instruct patients that hearing loss can occur with the use of TOLSURA. The hearing loss usually resolves when treatment is stopped but can persist in some patients. Advise patients to inform their healthcare provider if any hearing loss symptoms occur [see Warnings and Precautions (5.7)].
Vision Problem
Instruct patients that dizziness or blurred/double vision can sometimes occur with TOLSURA. Advise patients that if they experience these dizziness or blurred/double vision, they should contact their healthcare provider, and instruct the patient not to drive or use machines [see Adverse Reactions (6.1)].
Pregnancy
Advise patients to notify their physician if they become pregnant or intend to become pregnant during therapy [see Use in Specific Populations (8.1)].
Mayne Pharma
Raleigh, NC 27609
TOLSURA is a registered trademark of Mayne Pharma.