


Prescribing information (package insert) - Revtorpyk
1 INDICATIONS AND USAGE
REVTORPYK is indicated in combination with fulvestrant, with or without palbociclib, for the treatment of adult patients with hormone receptor (HR)-positive, human epidermal growth factor receptor 2 (HER2)-negative locally advanced or metastatic breast cancer without a PIK3CA mutation detected following progression on or after treatment with at least one line of endocrine therapy in the metastatic setting [see Dosage and Administration (2.1) and Clinical Studies (14)].
2 DOSAGE AND ADMINISTRATION
2.1 Patient Selection
Select patients for treatment of HR-positive, HER2-negative locally advanced or metastatic breast cancer with REVTORPYK based on the absence of detected PIK3CA mutations in breast cancer [see Clinical Studies (14)].
An FDA-authorized test for the determination of PIK3CA mutation status in patients with HR-positive, HER2-negative locally advanced or metastatic breast cancer is not available.
2.2 Recommended Dosage and Administration
The recommended dosage of REVTORPYK is 180 mg as an intravenous infusion over 30 minutes once weekly on Days 1, 8, and 15 of every 28-day cycle, in combination with fulvestrant, with or without palbociclib, until disease progression or unacceptable toxicity.
If a planned dose is delayed or missed, administer as soon as possible thereafter. Do not wait until the next planned dose in the cycle. Adjust the timing of the subsequent dose to maintain the 3 weeks on followed by 1 week off schedule.
Refer to the Prescribing Information for fulvestrant and palbociclib administered in combination with REVTORPYK for additional dosing information.
2.3 Stomatitis Prophylaxis
Initiate steroid-containing alcohol-free mouthwash when starting REVTORPYK. Continue to administer steroid-containing alcohol-free mouthwash 4 times daily for the first 8 weeks of treatment and longer if needed [see Warnings and Precautions (5.1) and Patient Counseling Information (17)].
2.4 Dosage Modifications for Adverse Reactions
The recommended dosage reduction levels for adverse reactions are listed in Table 1.
Table 1: Recommended Dosage Reductions of REVTORPYK for Adverse Reactions
| Dose Reductions | Recommended Dose |
| First | 150 mg |
| Second | 130 mg |
Permanently discontinue REVTORPYK in patients who are unable to tolerate 130 mg intravenously once weekly on Days 1, 8, and 15 of every 28-day cycle.
The recommended dosage modifications for adverse reactions are described in Table 2.
Table 2: Recommended Dosage Modifications of REVTORPYK for Adverse Reactions
| Abbreviations: FBG, fasting blood glucose; FPG, fasting plasma glucose; ULN, upper limit of normal. | ||
| Adverse Reaction | SeverityAdverse reactions graded by the National Cancer Institute Common Terminology Criteria for Adverse Events (NCI-CTCAE) version 5.0. | Dosage Modification |
Stomatitis [see Warnings and Precautions (5.1)] | Grade 3 |
|
| Grade 4 |
| |
Hematologic Toxicities [see Adverse Reactions (6.1)] | Grade 4 |
|
Dermatologic Adverse Reactions [see Warnings and Precautions (5.2)] | Grade 3 rash (both maculopapular and acneiform) |
|
| Grade 4 rash (acneiform) |
| |
| Any Grade of Stevens-Johnson Syndrome (SJS)/Toxic Epidermal Necrolysis (TEN) or other SJS/TEN-like severe skin reactions |
| |
Hyperglycemia (Fasting Glucose [FG]) [see Warnings and Precautions (5.3)] | FG levels (FPG or FBG) > ULN-160 mg/dL (>ULN-8.9 mmol/L) |
|
| FG levels 161-250 mg/dL (9-13.9 mmol/L) |
| |
251-500 mg/dL (14-27.8 mmol/L) |
| |
| >500 mg/dL (>27.8 mmol/L) |
| |
Other Adverse Reactions [see Adverse Reactions (6.1)] | Grade 2 |
|
| Grade 3 |
| |
| Grade 4 |
| |
2.5 Preparation and Administration
Reconstitute and further dilute REVTORPYK prior to intravenous infusion. Use appropriate aseptic technique.
Reconstitution
- Add 20 mL of Sterile Water for Injection or 5% Dextrose Injection to the REVTORPYK vial.
- Swirl the vial until completely dissolved for up to 5 minutes. Minor foaming and opalescence may be observed.
- If not used immediately, store the reconstituted solution in the vial for up to 4 hours at room temperature at 20°C to 25°C (68°F to 77°F). Do not freeze or refrigerate.
- REVTORPYK does not contain a preservative. Discard unused reconstituted REVTORPYK vial after 4 hours.
- DO NOT use common chloride-containing infusion solutions (for example: normal saline, Ringer’s solution, Lactated Ringer’s solution).
Dilution
- Withdraw the appropriate volume of the reconstituted solution from the REVTORPYK vial (See Table 3) using a sterile syringe. Inspect visually for particulate matter and discoloration prior to administration. The solution should be free of visible particulates, be clear (minor opalescence is acceptable) and colorless to pale yellow. Discard the vial if particles or discoloration are observed.
Table 3: Volume to Withdraw from Reconstituted Vial Based on Dose
| Dose | Volume of Reconstituted REVTORPYK |
| 180 mg | 20 mL |
| 150 mg | 17 mL |
| 130 mg | 14 mL |
- Dilute the reconstituted REVTORPYK in an infusion bag containing 250 mL of 5% Dextrose Injection.
- Gently invert the infusion bag to thoroughly mix the solution. Do not shake.
- If not used immediately, store the diluted REVTORPYK infusion solution at room temperature at 20°C to 25°C (68°F to 77°F) for up to 24 hours. Do not freeze or refrigerate.
- Discard any unused portion left in the vial.
Administration
- Flush the intravenous line with 5% Dextrose Injection before REVTORPYK administration.
Administer REVTORPYK by intravenous infusion over 30 minutes through a dedicated infusion line equipped with a sterile, non-pyrogenic, in-line or add-on polyether sulfone filter (0.2- or 0.22-micron pore size) and catheter.
- DO NOT administer any chloride-containing solutions (e.g., Sodium Chloride for Injection, Ringer’s Injection, Lactated Ringer’s Injection) or other medications concomitantly via the same intravenous line.
- Upon completion of the infusion, flush the intravenous line with 5% Dextrose Injection.
- Discard any unused portions left in the infusion set.
3 DOSAGE FORMS AND STRENGTHS
REVTORPYK is supplied as a sterile, white to off-white lyophilized powder for injection containing 180 mg gedatolisib in a single-dose vial for reconstitution and further dilution.
4 CONTRAINDICATIONS
None.
5 WARNINGS AND PRECAUTIONS
5.1 Stomatitis
REVTORPYK can cause severe stomatitis, including ulcers and oral mucositis.
In Study 1 of VIKTORIA-1, stomatitis occurred in 72% of patients treated with REVTORPYK with fulvestrant and palbociclib, including Grade 3 events in 22% of patients. Prophylactic steroid-containing alcohol-free mouthwash was required for a minimum of 8 weeks. The median time to onset was 7 days (range: 1 to 457 days). Stomatitis led to REVTORPYK dose reduction in 19% and permanent discontinuation in 3.8% of patients. Stomatitis occurred in 58% of patients treated with REVTORPYK with fulvestrant, including Grade 3 events in 12% of patients. The median time to onset was 4 days (range: 1 to 524 days). Stomatitis led to REVTORPYK dose reduction in 9% and permanent discontinuation in 1.5% of patients.
Prophylactically initiate steroid-containing alcohol-free mouthwash to reduce the incidence and severity of stomatitis [see Dosage and Administration (2.3)].
If stomatitis occurs, increase the frequency of mouthwash and administer other topical treatments as clinically indicated. Withhold, reduce dose, or permanently discontinue REVTORPYK based on severity [see Dosage and Administration (2.4)].
5.2 Dermatologic Adverse Reactions
REVTORPYK can cause severe rash.
In Study 1 of VIKTORIA-1, rash occurred in 30% of patients treated with REVTORPYK in combination with fulvestrant and palbociclib, including Grade 3 events in 6% of patients. The median time to onset was 21 days (range: 3 to 260 days) after starting REVTORPYK. Rash led to REVTORPYK dose reduction in 5% and permanent discontinuation in 0.8% of patients. Rash occurred in 40% of patients treated with REVTORPYK in combination with fulvestrant, including Grade 3 events in 5% of patients. Rash led to REVTORPYK dose reduction in 6% and permanent discontinuation in 0.8% of patients. The median time to onset was 31.5 days (range: 2 to 407 days) after starting REVTORPYK.
Monitor patients receiving REVTORPYK for rash and infectious sequelae. Instruct patients to limit sun exposure during REVTORPYK treatment.
Withhold, reduce dose, or permanently discontinue REVTORPYK based on severity [see Dosage and Administration (2.4)].
5.3 Hyperglycemia
Severe hyperglycemia can occur in patients treated with REVTORPYK. Hyperglycemia is associated with drugs that inhibit the PI3K/AKT/mTOR pathway.
In Study 1 of VIKTORIA-1, increased fasting glucose (FG) from baseline occurred in 46% of patients treated with REVTORPYK in combination with fulvestrant and palbociclib, including Grade 1 (FG >ULN to 160 mg/dL) in 36% of patients, Grade 2 (FG >160 to 250 mg/dL) in 8% of patients and Grade 3 (FG >250 to 500 mg/dL) in 0.9% of patients. Increased fasting glucose from baseline occurred in 57% of patients treated with REVTORPYK in combination with fulvestrant, including Grade 1 in 44% of patients, Grade 2 in 11% of patients and Grade 3 in 1.8% of patients.
The safety of REVTORPYK in patients with Type 1 or uncontrolled Type 2 diabetes mellitus has not been established as these patients were excluded from Study 1 of VIKTORIA-1 [see Clinical Studies (14)].
Before initiating treatment with REVTORPYK, test fasting glucose levels (FPG or FBG), HbA1c levels, and optimize fasting glucose. Achieve optimal glucose control before starting each REVTORPYK infusion [see Dosage and Administration (2.4)]. Manage hyperglycemia with anti-hyperglycemic medications. Patients with a history of well-controlled Type 2 diabetes mellitus may require intensified anti-hyperglycemic treatment and close monitoring of FG levels. Consider consultation with a healthcare professional experienced in the treatment of hyperglycemia. Initiate at-home glucose monitoring for patients with HbA1c level >6.4%. Advise patients of the signs and symptoms of hyperglycemia and counsel patients on lifestyle changes.
Withhold, reduce dose, or permanently discontinue REVTORPYK based on severity [see Dosage and Administration (2.4)].
5.4 Embryo-Fetal Toxicity
Based on its mechanism of action, REVTORPYK can cause fetal harm when administered to a pregnant woman [see Clinical Pharmacology (12.1)]. Inhibition of PI3K and mTOR pathways have been associated with adverse embryo-fetal growth and lethality in animals.
Advise patients of the potential risk to a fetus. Advise females of reproductive potential to use effective contraception during treatment with REVTORPYK and for 2 weeks after the last dose. Advise male patients with female partners of reproductive potential to use effective contraception during treatment with REVTORPYK and for 2 weeks after the last dose [see Use in Specific Populations (8.1, 8.3)].
REVTORPYK is used in combination with fulvestrant, with or without palbociclib. Refer to the Prescribing Information of fulvestrant and palbociclib for pregnancy and contraception information. When REVTORPYK is used in combination, advise patients to use effective contraception during treatment and for the longest post-treatment duration recommended in the Prescribing Information of any of the individual products.
6 ADVERSE REACTIONS
The following clinically significant adverse reactions are described elsewhere in the labeling:
- Stomatitis [see Warnings and Precautions (5.1)]
- Dermatologic adverse reactions [see Warnings and Precautions (5.2)]
- Hyperglycemia [see Warnings and Precautions (5.3)]
6.1 Clinical Trials Experience
Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice.
The safety of REVTORPYK was evaluated in 383 adult patients with HR-positive, HER2-negative locally advanced or metastatic breast cancer without a detectable PIK3CA mutation in Study 1 of VIKTORIA-1 [see Clinical Studies (14)].
Patients received either Arm A: REVTORPYK 180 mg intravenously once weekly for 3 weeks on followed by 1 week off (Days 1, 8, 15 for each 28-day cycle) in combination with fulvestrant 500 mg intramuscularly on cycle 1 Days 1 and 15, and then at Day 1 of each subsequent 28-day cycle and palbociclib 125 mg orally once daily for 21 days followed by 7 days off treatment for each 28-day cycle (n = 130); or Arm B: REVTORPYK in combination with fulvestrant (n = 130); or Arm C: fulvestrant alone (n = 123). The dose, route of administration, and frequency of each drug in Arms B and C were the same as Arm A. The median duration of exposure for REVTORPYK plus fulvestrant and palbociclib was 6.2 months (range: 0.5 to 25 months) and 5.7 months (range: 0 to 26 months) for REVTORPYK plus fulvestrant.
REVTORPYK in Combination with Fulvestrant and Palbociclib
Serious adverse reactions occurred in 25% of patients who received REVTORPYK in combination with fulvestrant and palbociclib. Serious adverse reactions in ≥1% of patients included pneumonia (3.8%), thrombosis (3.8%), and stomatitis (1.5%). Fatal adverse reactions occurred in 2.3% of patients who received REVTORPYK in combination with fulvestrant and palbociclib, including (0.8% each) pneumonia, multiorgan failure, and hepatic failure.
Permanent discontinuation of REVTORPYK due to an adverse reaction occurred in 12% of patients receiving REVTORPYK in combination with fulvestrant and palbociclib. Adverse reactions that resulted in permanent discontinuation of REVTORPYK were stomatitis, nausea, rash, pneumonitis, diplopia, hypertension, vomiting, breast ulceration, and squamous cell carcinoma of the lung.
Dosage interruptions of REVTORPYK due to an adverse reaction occurred in 64% of patients receiving REVTORPYK in combination with fulvestrant and palbociclib. Adverse reactions which required dosage interruption of REVTORPYK in ≥2% of patients included neutropenia, stomatitis, decreased neutrophil count, fatigue, anemia, leukopenia, increased aspartate aminotransferase (AST), increased alanine aminotransferase (ALT), pyrexia, rash, thrombosis, pneumonia, diarrhea, hyperglycemia, thrombocytopenia, upper respiratory tract infection, pruritus, and urinary tract infection.
Dose reductions of REVTORPYK due to an adverse reaction occurred in 41% of patients receiving REVTORPYK in combination with fulvestrant and palbociclib. Adverse reactions which required dose reduction of REVTORPYK in ≥2% of patients included stomatitis, neutropenia, rash, nausea, increased AST, and increased ALT.
The most common (≥20%) adverse reactions, including laboratory abnormalities, in the REVTORPYK in combination with fulvestrant and palbociclib arm were decreased white blood cell, decreased neutrophils, decreased hemoglobin, decreased lymphocytes, stomatitis, nausea, decreased platelets, increased fasting glucose, fatigue, vomiting, rash, constipation, diarrhea, increased ALT, increased AST, musculoskeletal pain, decreased sodium, and increased eosinophils.
REVTORPYK in Combination with Fulvestrant
Serious adverse reactions occurred in 19% of patients who received REVTORPYK in combination with fulvestrant. Serious adverse reactions in ≥1% of patients included pneumonia (3.8%), thrombosis (2.3%), pleural effusion (1.5%), and pneumonitis (1.5%). Fatal adverse reactions occurred in 2.3% of patients who received REVTORPYK in combination with fulvestrant, including (0.8% each) acute respiratory failure, bronchopulmonary hemorrhage, and cardiac arrest.
Permanent discontinuation of REVTORPYK due to an adverse reaction occurred in 9% of patients receiving REVTORPYK in combination with fulvestrant. Adverse reactions that resulted in permanent discontinuation of REVTORPYK were stomatitis, nausea, rash, pneumonitis, acute respiratory failure, myocarditis, angina pectoris, fatigue, infusion-related reaction, peripheral neuropathy, and oral pain.
Dosage interruptions of REVTORPYK due to an adverse reaction occurred in 37% of patients receiving REVTORPYK in combination with fulvestrant. Adverse reactions which required dosage interruption of REVTORPYK in ≥2% of patients included fatigue, increased AST, increased ALT, stomatitis, pneumonia, pyrexia, and diarrhea.
Dose reductions of REVTORPYK due to an adverse reaction occurred in 22% of patients receiving REVTORPYK in combination with fulvestrant. Adverse reactions which required dose reduction of REVTORPYK in ≥2% of patients included stomatitis, rash, and nausea.
The most common (≥20%) adverse reactions, including laboratory abnormalities, in the REVTORPYK in combination with fulvestrant arm were stomatitis, increased fasting glucose, increased eosinophils, decreased hemoglobin, nausea, rash, increased ALT, fatigue, musculoskeletal pain, decreased lymphocytes, vomiting, increased AST, pruritus, and diarrhea.
Tables 4 and 5 summarize the adverse reactions and laboratory abnormalities in Study 1 of VIKTORIA-1, respectively.
Table 4: Adverse Reactions (≥10%) in Patients Who Received REVTORPYK plus Fulvestrant and Palbociclib in Study 1 of VIKTORIA-1
Grading according to CTCAE 5.0. N=number of patients | ||||||
| Adverse Reaction | REVTORPYK + Fulvestrant + Palbociclib (N=130) | REVTORPYK + Fulvestrant (N=130) | Fulvestrant (N=123) | |||
| All Grades | Grade 3 or 4No Grade 4 events were reported. | All Grades | Grade 3 or 4 | All Grades | Grade 3 or 4 | |
| % | % | % | % | % | % | |
| Gastrointestinal Disorders | ||||||
| StomatitisIncludes multiple related terms. | 72 | 22 | 58 | 12 | 2.4 | 0 |
| Nausea | 51 | 3.8 | 44 | 0.8 | 13 | 0.8 |
| Vomiting | 35 | 1.5 | 24 | 0 | 4.1 | 0 |
| Diarrhea | 26 | 1.5 | 20 | 1.5 | 4.9 | 0 |
| Constipation | 26 | 0 | 16 | 0 | 3.3 | 0 |
| Abdominal pain | 13 | 0 | 9 | 0 | 8 | 4.1 |
| General Disorders and Administration Site Conditions | ||||||
| Fatigue | 43 | 2.3 | 34 | 0.8 | 13 | 0.8 |
| Pyrexia | 14 | 0 | 10 | 0 | 1.6 | 0 |
| Mucosal dryness | 11 | 0 | 10 | 0 | 1.6 | 0 |
| Skin and Subcutaneous Tissue Disorders | ||||||
| Rash | 30 | 6 | 40 | 5 | 0 | 0 |
| Pruritus | 19 | 0.8 | 22 | 0 | 1.6 | 0 |
| Musculoskeletal and Connective Tissue Disorders | ||||||
| Musculoskeletal pain | 24 | 0.8 | 26 | 3.1 | 24 | 2.4 |
| Nervous System Disorders | ||||||
| Dysgeusia | 19 | 0 | 17 | 0 | 0.8 | 0 |
| Dizziness | 10 | 0 | 9 | 0 | 3.3 | 0 |
| Metabolism and nutrition disorder | ||||||
| Decreased appetite | 19 | 0.8 | 11 | 0.8 | 4.1 | 0.8 |
| Infections and Infestations | ||||||
| Urinary Tract Infection | 13 | 0 | 15 | 0 | 4.1 | 0 |
| Respiratory, Thoracic and Mediastinal Disorders | ||||||
| Cough | 11 | 0 | 18 | 0 | 7 | 0 |
| Vascular Disorders | ||||||
| Thrombosis | 10 | 3.1 | 3.1 | 2.3 | 0 | 0 |
Table 5: Select Laboratory Abnormalities (≥10%) in Patients Who Received REVTORPYK plus Fulvestrant and Palbociclib in Study 1 of VIKTORIA-1
| N=number of patients; WBC = white blood cells; AST = aspartate aminotransferase; ALT = alanine aminotransferase; CPK = creatine phosphokinase; ALP = alkaline phosphatase. | ||||||
| Laboratory Abnormality | REVTORPYK + Fulvestrant + Palbociclib (N=130) | REVTORPYK + Fulvestrant (N=130) | Fulvestrant (N=123) | |||
| All Grades | Grade 3 or 4 | All Grades | Grade 3 or 4 | All Grades | Grade 3 or 4 | |
| % | % | % | % | % | % | |
| Hematology | ||||||
| WBC decreased | 93 | 45 | 16 | 0.8No Grade 4 events were reported. | 13 | 0.8 |
| Neutrophils decreased | 85 | 65 | 14 | 1.6 | 10 | 0.8 |
| Hemoglobin decreased | 84 | 12 | 46 | 0.8 | 19 | 2.5 |
| Lymphocytes decreased | 73 | 27 | 25 | 2.6 | 21 | 5.4 |
| Platelets decreased | 49 | 6 | 5 | 0.8 | 11 | 0.8 |
| Eosinophils increased | 20 | 0 | 53 | 0 | 11 | 0 |
| Chemistry | ||||||
| Glucose (fasting) increasedGlucose results were graded per CTCAE v4.03. | 46 | 0.9 | 57 | 1.8 | 17 | 0 |
| ALT increased | 25 | 0.8 | 35 | 2.3 | 21 | 0 |
| AST increased | 24 | 2.4 | 23 | 3.1 | 18 | 1.7 |
| Sodium decreased | 21 | 1.6 | 16 | 0.8 | 13 | 1.7 |
| Magnesium decreased | 19 | 0 | 16 | 0 | 3.4 | 0 |
| Potassium decreased | 19 | 1.6 | 14 | 1.6 | 9 | 1.7 |
| Glucose decreased | 17 | 3.1 | 9 | 1.5 | 2.6 | 0.9 |
| CPK increased | 15 | 0.9 | 12 | 2.5 | 11 | 0.9 |
| Creatinine increased | 14 | 0.8 | 10 | 1.6 | 8 | 0.8 |
| Serum amylase increased | 14 | 0.8 | 10 | 2.3 | 9 | 0 |
| ALP increased | 12 | 0 | 18 | 0 | 21 | 1.7 |
| Potassium increased | 10 | 0.8 | 5 | 0 | 8 | 0.8 |
8 USE IN SPECIFIC POPULATIONS
8.1 Pregnancy
Risk Summary
REVTORPYK is used in combination with fulvestrant, with or without palbociclib. Refer to the Prescribing Information for fulvestrant and palbociclib for pregnancy information. When used in combination with REVTORPYK, advise patients to use effective contraception during treatment and for the longest post-treatment duration recommended in the Prescribing Information of any of the individual products.
Based on its mechanism of action, REVTORPYK can cause fetal harm when administered to a pregnant woman [see Clinical Pharmacology (12.1)]. There are no available data in pregnant women to inform the drug-associated risk. Animal reproductive toxicity studies have not been conducted with REVTORPYK. Inhibition of PI3K and mTOR pathways have been associated with adverse embryo-fetal growth and lethality in animals (see Data).
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Data
Animal Data
PIK3CA knockout mice experienced developmental delay at embryonic day 9.5 and mortality between embryonic day 9.5 and 10.5. mTOR knockout mice experienced early lethality by embryonic day 7.5. In both animal models, early embryonic death was a result of impaired cell proliferation and structural development.
8.2 Lactation
Risk Summary
REVTORPYK is used in combination with fulvestrant, with or without palbociclib. Refer to the Prescribing Information for fulvestrant and palbociclib for lactation information. When used in combination with REVTORPYK, advise patients to not breastfeed during treatment and for the longest post-treatment duration recommended in the Prescribing Information of any of the individual products.
There are no data on the presence of gedatolisib or its metabolites in human milk, its effects on milk production, or a breastfed child. Because of the potential for serious adverse reactions in a breastfed child, advise lactating women to not breastfeed during treatment with REVTORPYK and for 2 weeks after the last dose.
8.3 Females and Males of Reproductive Potential
REVTORPYK is used in combination with fulvestrant, with or without palbociclib. Refer to the Prescribing Information for fulvestrant and palbociclib for contraception and infertility information. When used in combination with REVTORPYK, advise patients to use effective contraception during treatment and for the longest post-treatment duration recommended in the Prescribing Information of any of the individual products.
Based on its mechanism of action, REVTORPYK can cause fetal harm when administered to a pregnant woman [see Use in Specific Populations (8.1)].
Pregnancy Testing
Verify the pregnancy status of females of reproductive potential prior to initiating treatment with REVTORPYK.
Contraception
Females
Advise females of reproductive potential to use effective contraception during treatment with REVTORPYK and for 2 weeks after the last dose.
Males
Advise male patients with female partners of reproductive potential to use effective contraception during treatment with REVTORPYK and for 2 weeks after the last dose.
Infertility
Based on animal studies, REVTORPYK may impair fertility in females and males of reproductive potential. Findings in animals were reversible [see Nonclinical Toxicology (13.1)].
8.4 Pediatric Use
The safety and efficacy of REVTORPYK in pediatric patients have not been established.
8.5 Geriatric Use
Of 260 patients who received REVTORPYK, 55 patients (21%) were ≥65 and <75 years of age and 17 patients (6.5%) were ≥75 years of age [see Clinical Studies (14)].
In patients treated with REVTORPYK in combination with fulvestrant and palbociclib, the incidence of Grade ≥3 stomatitis and rash was higher in patients ≥65 years of age (37% and 11%, respectively) compared to younger patients (16% and 4.3%, respectively). In patients treated with REVTORPYK in combination with fulvestrant, the incidence of Grade ≥3 stomatitis and rash was higher in patients ≥65 years of age (18% and 12%, respectively) compared to younger patients (10% and 3.1%, respectively). No overall differences in effectiveness of REVTORPYK were observed between patients ≥65 years of age and younger patients.
11 DESCRIPTION
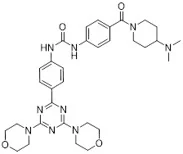
REVTORPYK for injection contains gedatolisib, a kinase inhibitor. The chemical name of gedatolisib is 1-[4-(4-dimethylaminopiperidine-1-carbonyl)phenyl]-3-[4-(4,6-dimorpholin-4-yl-[1,3,5]triazin2-yl)phenyl]urea. The molecular formula for gedatolisib is C32H41N9O4 and the molecular weight is 615.74 g/mol. Gedatolisib is a white to off-white crystalline solid that is insoluble in water. The chemical structure of gedatolisib is shown below:
REVTORPYK for injection is a sterile, preservative-free, lyophilized white to off-white cake or powder with cake supplied in a single-dose vial. Each vial delivers 180 mg of gedatolisib. The lyophilized powder also contains 720 mg of hydroxypropyl β cyclodextrin and 48.6 mg of lactic acid and may include hydrochloric acid and/or sodium hydroxide for pH adjustment.
12 CLINICAL PHARMACOLOGY
12.1 Mechanism of Action
Gedatolisib is a kinase inhibitor of class I PI3K isoforms (α, β, δ, γ) and mTOR complexes mTORC1 and mTORC2, resulting in downstream inhibition of multiple effectors, including AKT. In estrogen receptor (ER)-positive breast cancer cell lines and xenograft models harboring wild-type or mutant PIK3CA, gedatolisib induced apoptosis and anti-proliferative effects in vitro and reduced tumor cell growth in vivo. In a human ER-positive breast cancer xenograft model harboring a PIK3CA mutation, the combination of gedatolisib with palbociclib and fulvestrant increased tumor growth inhibition compared to each treatment alone or the doublet combinations.
12.2 Pharmacodynamics
Exposure-Response Relationships
The exposure-response relationship and time course of pharmacodynamic response for the effectiveness of gedatolisib have not been fully characterized. An increased incidence of stomatitis or mucositis (Grade 3 and 4), nausea, vomiting, hyperglycemia, and adverse reaction leading to dosage modification or discontinuation was observed with higher gedatolisib exposure at the dose range of 10 mg to 319 mg (0.06 to 1.8 times the approved recommended dose).
Cardiac Electrophysiology
At weekly doses up to 319 mg (1.8 times the recommended dose), clinically significant QTc interval prolongation was not observed.
12.3 Pharmacokinetics
Gedatolisib pharmacokinetic parameters were observed at the approved recommended dosage in patients with breast cancer and are presented as mean (% coefficient of variation [%CV]), unless otherwise specified. Gedatolisib maximum plasma concentration (Cmax) is 13,700 (29%) ng/mL and area under the curve (AUC) is 21,400 (21%) ng·h/mL. Gedatolisib Cmax and AUC values increase dose proportionally in the dose range 10 mg to 319 mg (0.06 to 1.8 times the recommended dose). No accumulation of gedatolisib is observed after once-weekly administration.
Distribution
Gedatolisib plasma protein binding is 98%, and is not concentration dependent, in vitro. Gedatolisib blood-to-plasma ratio is 0.87, in vitro. Gedatolisib volume of distribution is 393 L.
Elimination
Gedatolisib elimination half-life (t1/2) is 36 hours with an estimated clearance of 8 (23%) L/hour.
Excretion
After a single dose of radiolabeled gedatolisib 89 mg to healthy subjects, approximately 67.4% of the dose was recovered in feces (67% unchanged) and 12.2% in urine (11.6% unchanged).
Specific Populations
No clinically significant effects on the pharmacokinetics of gedatolisib were observed based on age (21 to 84 years), sex, race (White [78%], Asian [9.1%], Black or African American [4.1%]) body weight (35 to 168 kg), mild hepatic impairment (total bilirubin ≤1.5 × ULN and any AST) or estimated glomerular filtration rate (eGFR) ≥ 45 mL/min/1.73 m2 (MDRD equation). The effect of moderate (total bilirubin >1.5 to 3 times ULN with any AST) or severe (total bilirubin >3 x ULN with any AST) hepatic impairment, eGFR <45 mL/min/1.73 m2, or dialysis on gedatolisib pharmacokinetics is unknown.
Drug Interactions
Clinical Studies and Model-Informed Approaches
No clinically significant differences in the pharmacokinetics of the following drugs were observed when used concomitantly with gedatolisib: metformin (MATE1, MATE2-K, and OCT1 substrate), rosuvastatin (BCRP substrate), or repaglinide (CYP2C8 sensitive substrate).
In Vitro Studies
CYP450 Enzymes: Gedatolisib is not an inhibitor of CYP1A2, CYP2A6, or CYP2B6.
The ability of gedatolisib to induce CYP450 enzymes is unknown given the results of the vitro studies were inconclusive due to decreased viability of hepatocytes.
Transporter Systems: Gedatolisib is a substrate of P-gp and BCRP and is not a substrate for OATP1B1, OATP1B3, OCT1, NTCP, MRP2, or MRP3.
Gedatolisib did not inhibit P-gp, OATP1B1, OATP1B3, OAT1, OAT3, OCT2, and BSEP.
13 NONCLINICAL TOXICOLOGY
13.1 Carcinogenesis, Mutagenesis, Impairment of Fertility
Carcinogenesis
Carcinogenicity studies have not been conducted with gedatolisib.
Mutagenesis
Gedatolisib was not mutagenic in vitro in a bacterial reverse mutation (Ames) assay and was not clastogenic in an in vitro human lymphocyte chromosomal aberration assay. Gedatolisib was not genotoxic in an in vivo rat bone marrow micronucleus assay.
Impairment of Fertility
Fertility studies with gedatolisib have not been conducted. In repeated-dose toxicity studies, gedatolisib was administered intravenously once weekly on a 3 weeks on/1 week off schedule for 3 months in rats and dogs. Degeneration/atrophy of seminiferous tubules in testes was observed in male rats and dogs at ≥ 5 mg/kg and 0.5 mg/kg, respectively, and atrophy of prostate was observed in male rats at ≥ 1 mg/kg. In female rats, atrophy in the vagina and uterus was observed at ≥ 5 mg/kg. All findings occurred at exposures ≤ 0.2 times the human AUC at the recommended dose. Findings in males and females were reversible following a 12-week recovery period.
14 CLINICAL STUDIES
The efficacy of REVTORPYK in combination with fulvestrant, with or without palbociclib, was evaluated in Study 1 of VIKTORIA-1 (NCT05501886), an open label, randomized, multicenter clinical trial that enrolled 392 adult patients with locally advanced (inoperable) or metastatic HR-positive, HER2-negative (defined as immunohistochemistry (IHC) 0 or 1+, or IHC 2+/in situ hybridization (ISH-)) breast cancer without a detectable PIK3CA mutation. The PIK3CA status was assessed centrally for the following PIK3CA mutations: C420R, E542K, E545A, E545D [1635G>T only], E545G, E545K, Q546E, H1047L, H1047R, and H1047Y.
All patients were required to have progression on or after treatment with a CDK4/6 inhibitor and a non-steroidal aromatase inhibitor (AI) therapy. Patients could have received up to two prior lines of endocrine therapy for locally advanced (inoperable) or metastatic disease. Patients were excluded from the trial if they had Type 1 or uncontrolled Type 2 diabetes mellitus (requiring systemic insulin therapy), HbA1c >6.4%, and prior treatment with a PI3K inhibitor, AKT inhibitor, or mTOR inhibitor.
Patients were randomized (1:1:1) to three arms as follows:
- Arm A (N=131): REVTORPYK 180 mg intravenously once weekly for 3 weeks on followed by 1 week off (Days 1, 8, 15 for each 28-day cycle) in combination with fulvestrant 500 mg intramuscularly on cycle 1 Days 1 and 15, and then at Day 1 of each subsequent 28-day cycle, and palbociclib 125 mg orally once daily for 21 days followed by 7 days off treatment for each 28-day cycle (G+F+P), or
- Arm B (N=130): REVTORPYK 180 mg intravenously once weekly for 3 weeks on followed by 1 week off (Days 1, 8, 15 for each 28-day cycle) in combination with fulvestrant 500 mg intramuscularly on cycle 1 Days 1 and 15, and then at Day 1 of each subsequent 28-day cycle (G+F), or
- Arm C (N=131): Fulvestrant 500 mg intramuscularly on cycle 1 Days 1 and 15, and then at Day 1 of each subsequent 28-day cycle (F).
In addition, all pre/perimenopausal women were required to receive a gonadotropin-releasing hormone (GnRH) agonist. Randomization was stratified by presence of visceral metastases (yes or no), duration on immediate prior therapy (≤6 months or >6 months) and geographical region (Region 1: US or Region 2: Rest of World). Patients received treatment until disease progression or unacceptable toxicity. Patients on Arm C had the option to cross over to study Arm A or Arm B at the time of disease progression.
The major efficacy outcome was comparison of progression-free survival (PFS) assessed by blinded independent central review between patients enrolled in Arm A (G+F+P) and Arm C (F), and between patients enrolled in Arm B (G+F) and Arm C (F) evaluated according to Response Evaluation Criteria in Solid Tumors (RECIST), version 1.1. Additional efficacy outcome measures were overall survival (OS), objective response rate (ORR) and duration of response (DoR).
The baseline demographic and disease characteristics were: median age 56 years (range: 28 to 83 years); 99% female, of which 26% were pre/perimenopausal; 70% White, 16% Asian, 7% unknown, 2% Black or African American; 65% Not Hispanic/Latino, 28% Hispanic or Latino, 7% not reported/unknown; 100% had Stage IV breast cancer; all patients had prior endocrine therapy and prior CDK4/6 inhibitor therapy; 79% had visceral metastases; and Eastern Cooperative Oncology Group (ECOG) performance status of 0 (59%) or 1 (41%).
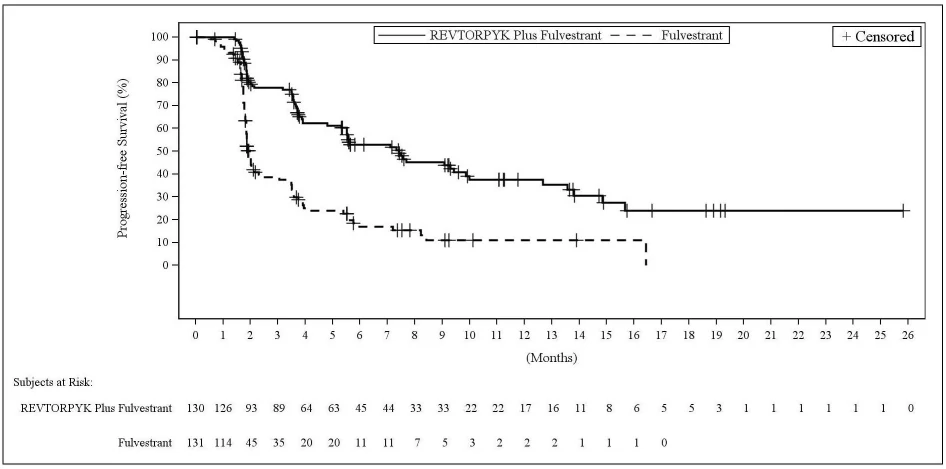
Efficacy results are summarized in Table 6 and Figures 1 and 2. At the time of the PFS analysis, OS data were not mature with 25% deaths in the overall population.
Table 6: Efficacy Results in Patients with Locally Advanced or Metastatic Breast Cancer in Study 1 of VIKTORIA-1
| CI = confidence interval; CR = complete response; PR = partial response, NE = not estimable | |||
REVTORPYK + Fulvestrant+ Palbociclib N=131 | REVTORPYK + Fulvestrant N=130 | Fulvestrant N=131 | |
| Progression-Free Survival (PFS) | |||
| Patients with events, n (%) | 59 (45) | 69 (53) | 89 (68) |
| MedianBased on Kaplan-Meier estimates., months (95% CI) | 9.3 (7.2, 16.6) | 7.4 (5.5, 9.9) | 2.0 (1.8, 2.3) |
| Hazard ratio (95% CI)Stratified Cox regression model, confidence intervals for hazard ratio is based on the score test (D.Y. Lin 2016). | 0.24Arm A (REVTORPYK plus fulvestrant and palbociclib) versus Arm C (fulvestrant). (0.17, 0.35) | 0.33Arm B (REVTORPYK plus fulvestrant) versus Arm C (fulvestrant). (0.24, 0.48) | N/A |
| p-value | <0.0001 | <0.0001 | N/A |
| Objective Response Rate (ORR) | |||
| Patients with measurable disease | 124 | 113 | 105 |
| Patients with CR or PR, n (%) | 39 (32) | 32 (28) | 1 (1.0) |
| 95% CI | 23, 40 | 20, 38 | 0, 5 |
| Duration of Response (DoR) | |||
| Median, months (95% CI) | 17.5 (8.8, NE) | 12.0 (8.1, NE) | NE (NE, NE) |
Figure 1: Kaplan-Meier Plot of Progression-Free Survival in Study 1 of VIKTORIA-1: REVTORPYK Plus Fulvestrant and Palbociclib versus Fulvestrant
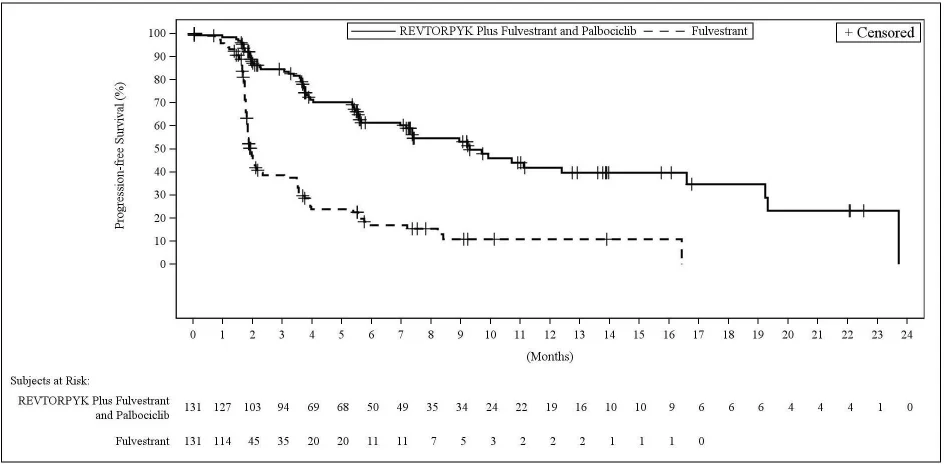
Figure 2: Kaplan-Meier Plot of Progression-Free Survival in Study 1 of VIKTORIA-1: REVTORPYK Plus Fulvestrant versus Fulvestrant
16 HOW SUPPLIED/STORAGE AND HANDLING
How Supplied
REVTORPYK for injection is a white to off-white lyophilized powder supplied as:
| Carton Content | NDC |
| One 180 mg single-dose vial | NDC 84577-751-01 |
Storage and Handling
Store at 20°C to 25°C (68°F to 77°F), excursions permitted 15°C to 30°C (59°F to 86°F). Store vial in original carton until time of reconstitution.
17 PATIENT COUNSELING INFORMATION
Advise the patient to read the FDA-approved patient labeling (Patient Information).
Stomatitis
Inform patients of the risk of stomatitis. Advise patients to contact their healthcare provider if they experience any symptoms (e.g., painful redness, swelling, or sores in the mouth). Inform patients to use steroid-containing mouthwash for prophylaxis and treatment of stomatitis. Instruct patients not to eat or drink for at least 1 hour after administration of the steroid-containing mouthwash [see Warnings and Precautions (5.1)].
Dermatologic Adverse Reactions
Inform patients of the risks of dermatologic adverse reactions, including rash. Advise patients to limit sun exposure during treatment. Advise patients to contact their healthcare provider immediately if they develop a new rash [see Warnings and Precautions (5.2)].
Hyperglycemia
Inform patients of the risks of hyperglycemia and the need for monitoring of fasting blood glucose and HbA1c periodically during treatment. Advise patients to contact their healthcare provider immediately for signs and symptoms of hyperglycemia (e.g., excessive thirst, urinating more often, blurred vision, confusion, difficulty breathing, or increased appetite with weight loss) [see Warnings and Precautions (5.3)].
Embryo-Fetal Toxicity
- Inform pregnant women and females of reproductive potential of the potential risk to a fetus. Advise females to inform their healthcare provider of a known or suspected pregnancy [see Warnings and Precautions (5.4) and Use in Specific Populations (8.1)].
- Advise females of reproductive potential to use effective contraception during treatment with REVTORPYK and for 2 weeks after the last dose [see Use in Specific Populations (8.3)].
- Advise male patients with female partners of reproductive potential to use effective contraception during treatment with REVTORPYK and for 2 weeks after the last dose [see Use in Specific Populations (8.3)].
- Refer to the Prescribing Information of palbociclib and fulvestrant for pregnancy and contraception information. When used in combination with REVTORPYK, advise patients to use effective contraception during treatment and for the longest post-treatment duration recommended in the Prescribing Information of any of the individual products.
Lactation
Advise women not to breastfeed during treatment with REVTORPYK and for 2 weeks after the last dose [see Use in Specific Populations (8.2)]. Refer to the Prescribing Information of palbociclib and fulvestrant for lactation information. When used in combination, advise patients not to breastfeed during treatment and for the longest post-treatment duration recommended in the Prescribing Information of any of the individual products.
Infertility
Advise females and males of reproductive potential that REVTORPYK may impair fertility [see Use in Specific Populations (8.3)]. Refer to the Prescribing Information of palbociclib and fulvestrant for infertility information.
This product's labeling may have been updated. For full prescribing information, please visit www.celcuity.com.
Manufactured for:
Celcuity Inc.
2800 Campus Dr, Suite 140
Minneapolis, MN 55441