


Prescribing information (package insert) - Rasonque
1 INDICATIONS AND USAGE
RASONQUE is indicated for the treatment of adult patients with metastatic pancreatic adenocarcinoma who have received at least one prior systemic therapy or who are not candidates for multiagent systemic therapy.
2 DOSAGE AND ADMINISTRATION
2.1 Prophylactic and Concomitant Medication
When initiating RASONQUE and throughout treatment, prophylactic and concomitant medications are recommended to reduce the risk of dermatologic reactions [see Warnings and Precautions (5.1)]:
- administer a topical corticosteroid (applied to the face and chest) and emollient creams
- advise patients to limit sun exposure and use broad-spectrum sunscreen (SPF 30 or higher)
- consider prophylactic oral antibiotics (e.g., doxycycline or minocycline)
2.2 Recommended Dosage
The recommended dosage of RASONQUE is 300 mg orally once daily until disease progression or unacceptable toxicity.
- Take RASONQUE at the same time each day with or without food.
- Swallow tablets whole. Do not chew, crush, or split tablets.
- If a dose is missed for more than 4 hours, skip the missed dose, and take the next dose at the next regularly scheduled time.
- If vomiting occurs after taking the dose, do not take an additional dose. Resume dosing at the next regularly scheduled time.
2.3 Dosage Modifications for Adverse Reactions
Recommended dosage reductions for adverse reactions are provided in Table 1. Permanently discontinue RASONQUE in patients who are unable to tolerate 150 mg orally once daily.
Table 1: Recommended Dosage Reductions for Adverse Reactions
| Dose Reduction Level | Dosage |
|---|---|
| First dose reduction | 200 mg once daily |
| Second dose reduction | 150 mg once daily |
Recommended dosage modifications for adverse reactions are provided in Table 2.
Table 2: Recommended Dosage Modifications for Adverse Reactions
| Adverse Reaction | SeverityGraded per National Cancer Institute Common Terminology Criteria for Adverse Events (NCI CTCAE) Version 5.0. | Dosage Modification |
|---|---|---|
| Dermatologic Toxicity (rash) [see Warnings and Precautions (5.1)] | Grade 2 |
|
| Grade 3 |
| |
| Grade 4 |
| |
| Stomatitis [see Warnings and Precautions (5.2)] | Grade 2 |
|
| Grade 3 |
| |
| Grade 4 |
| |
| Diarrhea [see Warnings and Precautions (5.3)] | Grade 2 |
|
| Grade 3 |
| |
| Grade 4 |
| |
| Gastrointestinal Perforation [see Warnings and Precautions (5.4)] | Grade 3 |
|
| Grade 4 |
| |
| Interstitial Lung Disease/Pneumonitis [see Warnings and Precautions (5.5)] | Grade 2 |
|
| Recurrent Grade 2, or Grade 3-4 |
| |
| Nausea or Vomiting [see Adverse Reactions (6.1)] | Grade 3 |
|
| Grade 4 |
| |
| Other Adverse Reactions [see Adverse Reactions (6.1)] | Grade 3 |
|
| Grade 4 |
|
2.4 Dosage Modifications for Drug Interactions
Strong CYP3A Inhibitors without P-gp Inhibition
Reduce the dosage of RASONQUE from 300 mg once daily to 150 mg once daily when used concomitantly with a strong CYP3A inhibitor without P-gp inhibition [see Drug Interactions (7.1)].
After the strong CYP3A inhibitor without P-gp inhibition has been discontinued for 5 days or 3 to 5 half-lives, whichever is longer, resume the RASONQUE dosage taken prior to initiating the inhibitor.
Moderate CYP3A Inhibitors with P-gp Inhibition
Reduce the dosage of RASONQUE from 300 mg once daily to 100 mg once daily when used concomitantly with a moderate CYP3A inhibitor with P-gp inhibition [see Drug Interactions (7.1)].
After the moderate CYP3A inhibitor with P-gp inhibition has been discontinued for 3 to 5 half-lives, resume the RASONQUE dosage taken prior to initiating the inhibitor.
Moderate CYP3A Inhibitors without P-gp Inhibition
Reduce the dosage of RASONQUE from 300 mg once daily to 200 mg once daily when used concomitantly with a moderate CYP3A inhibitor without P-gp inhibition [see Drug Interactions (7.1)].
After the moderate CYP3A inhibitor without P-gp inhibition has been discontinued for 3 to 5 half-lives, resume the RASONQUE dosage taken prior to initiating the inhibitor.
P-gp Inhibitors
Reduce the dosage of RASONQUE from 300 mg once daily to 150 mg once daily when used concomitantly with a P-gp inhibitor [see Drug Interactions (7.1)].
After the P-gp inhibitor has been discontinued, resume the RASONQUE dosage taken prior to initiating the inhibitor.
Strong CYP3A Inducers
If a strong CYP3A inducer cannot be avoided, increase the dosage of RASONQUE from 300 mg once daily to 400 mg once daily when used concomitantly with a strong CYP3A inducer [see Drug Interactions (7.1)].
After discontinuing use of the strong CYP3A inducer, resume RASONQUE dosage (7 to 14 days after discontinuing the strong CYP3A inducer) that was taken prior to initiating the inducer.
Moderate CYP3A Inducers
Increase the dosage of RASONQUE from 300 mg once daily to 400 mg once daily when used concomitantly with a moderate CYP3A inducer [see Drug Interactions (7.1)].
After discontinuing use of the moderate CYP3A inducer, resume RASONQUE dosage (7 to 14 days after discontinuing the moderate CYP3A inducer) that was taken prior to initiating the inducer.
3 DOSAGE FORMS AND STRENGTHS
- Tablets: 100 mg, blue, oval, biconvex, film-coated, debossed with “R” on one side and “100 M” on the other side.
- Tablets: 150 mg, blue, oval, biconvex, film-coated, debossed with “R” on one side and “150 M” on the other side.
4 CONTRAINDICATIONS
None.
5 WARNINGS AND PRECAUTIONS
5.1 Dermatologic and Soft Tissue Toxicity
RASONQUE can cause dermatologic toxicity, which may be severe. Clinical manifestations included, but were not limited to, rash, pruritus, paronychia, dry skin, and skin fissures. In clinical trials of patients with pancreatic adenocarcinoma, dermatologic toxicity occurred in 86% of patients treated with RASONQUE, of which 10% were Grade 3. The median time to first onset was 13 days (range: 1 to 106 days). The median time to improvement from Grade 3 to Grade 1 or resolution was 16 days (range: 8 to 218 days). Dermatologic toxicity led to interruption of RASONQUE in 24% of patients, dose reduction in 16% of patients, and dose discontinuation in 0.5% of patients.
Monitor patients who develop dermatologic or soft tissue toxicities while receiving RASONQUE. Initiate prophylactic measures (e.g., topical corticosteroids, emollient creams, sunscreen, oral antibiotics) prior to the first dose of RASONQUE to reduce the risk of moderate to severe dermatologic reactions. Advise patients to limit sun exposure while taking RASONQUE. Initiate supportive measures (e.g., oral corticosteroids) as clinically indicated, and consider dermatologic consultation. Withhold, reduce the dose, or permanently discontinue RASONQUE based on severity [see Dosage and Administration (2.3)].
5.2 Stomatitis and Oral Disorders
RASONQUE can cause stomatitis, including mouth ulcers and oral mucositis. In clinical trials of patients with pancreatic adenocarcinoma, stomatitis occurred in 57% of patients, of which 9% were Grade 3. The median time to first onset was 22 days (range: 1 to 343 days). The median time to improvement from Grade 3 to Grade 1 or resolution was 12 days (range: 1 to 127 days). Stomatitis led to interruption of RASONQUE in 17% of patients and dose reduction in 8% of patients.
Monitor patients for signs and symptoms of stomatitis while receiving RASONQUE. Initiate a steroid-containing mouthwash for treatment of stomatitis and administer other topical treatments (e.g., chlorhexidine mouthwash, 2% lidocaine viscous) as clinically indicated. Withhold, reduce the dose, or permanently discontinue RASONQUE based on severity [see Dosage and Administration (2.3)].
5.3 Diarrhea
RASONQUE can cause diarrhea. In clinical trials of patients with pancreatic adenocarcinoma, diarrhea occurred in 63% of patients, of which 6% were Grade 3. The median time to first onset was 3 days (range: 1 to 260 days). The median time to improvement from Grade 3 to Grade 1 or resolution was 3 days (range: 1 to 21 days). Diarrhea led to interruption of RASONQUE in 8% of patients and dose reduction in 4% of patients.
If diarrhea occurs, administer antidiarrheal treatment as clinically indicated. Withhold, reduce the dose, or permanently discontinue RASONQUE based on severity [see Dosage and Administration (2.3)].
5.4 Gastrointestinal Perforation
RASONQUE can cause gastrointestinal perforation. In clinical trials of patients with pancreatic adenocarcinoma, gastrointestinal perforation occurred in 0.9% of patients treated with RASONQUE, of which 0.5% were Grade 3, one event was Grade 4, and one event was fatal. The median time to first onset was 134 days (range: 17 to 254 days). The median time to improvement from Grade ≥ 3 to resolution was 8 days (range: 7 to 9 days).
Monitor patients for gastrointestinal perforation. Withhold RASONQUE if gastrointestinal perforation is suspected. Reduce the dose or permanently discontinue RASONQUE if no other potential causes of gastrointestinal perforation are identified [see Dosage and Administration (2.3)].
5.5 Interstitial Lung Disease (ILD)/Pneumonitis
RASONQUE can cause interstitial lung disease or pneumonitis. In clinical trials of patients with pancreatic adenocarcinoma, ILD/pneumonitis occurred in 2.4% of patients treated with RASONQUE, of which 0.9% were Grade 3, and one event was fatal. The median time to first onset was 111 days (range: 22 to 242 days). The median time to improvement from Grade 3 to resolution was 12 days (range: 12 to 47 days).
Monitor patients for new or worsening pulmonary symptoms. Withhold RASONQUE if ILD/pneumonitis is suspected. Reduce the dose or permanently discontinue RASONQUE if no other potential causes of ILD/pneumonitis are identified [see Dosage and Administration (2.3)].
5.6 Embryo-Fetal Toxicity
Based on findings in animals, RASONQUE can cause fetal harm when administered to a pregnant woman. In an animal reproduction study, oral administration of daraxonrasib to pregnant female mice during the period of organogenesis resulted in adverse developmental outcomes including mortality, alterations to growth, and structural abnormalities at exposures ≥ 2.5 times the recommended dose based on area under the curve (AUC).
Advise females of reproductive potential to use effective contraception during treatment with RASONQUE and for 1 week after the last dose. Advise males with female partners of reproductive potential to use effective contraception during treatment with RASONQUE and for 1 week after the last dose [see Use in Specific Populations (8.1), (8.3)].
6 ADVERSE REACTIONS
The following clinically significant adverse reactions are described elsewhere in the labeling:
- Dermatologic and Soft Tissue Toxicity [see Warnings and Precautions (5.1)]
- Stomatitis and Oral Disorders [see Warnings and Precautions (5.2)]
- Diarrhea [see Warnings and Precautions (5.3)]
- Gastrointestinal Perforation [see Warnings and Precautions (5.4)]
- Interstitial Lung Disease (ILD)/Pneumonitis [see Warnings and Precautions (5.5)]
6.1 Clinical Trials Experience
Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice.
The pooled safety population of RASONQUE described in the WARNINGS AND PRECAUTIONS section reflects exposure to RASONQUE 300 mg once daily in 241 patients with pancreatic adenocarcinoma enrolled in RASolute 302 and 184 patients with pancreatic adenocarcinoma enrolled in the open-label trial RMC-6236-001.
Metastatic Pancreatic Adenocarcinoma
The safety of RASONQUE was evaluated in RASolute 302 [see Clinical Studies (14)]. Patients with metastatic pancreatic adenocarcinoma received either RASONQUE 300 mg once daily (N = 241) or physician’s choice of standard of care (SOC) chemotherapy regimens (N = 214). Among patients who received RASONQUE, 52% were exposed for 6 months or longer and 2% were exposed for greater than one year.
Serious adverse reactions occurred in 30% of patients treated with RASONQUE. Serious adverse reactions occurring in ≥ 2% of patients treated with RASONQUE were diarrhea (3.7%), pyrexia (3.3%), sepsis (2.9%), fatigue (2.1%), and hemorrhage (2.1%).
Adverse reactions leading to permanent discontinuation of RASONQUE occurred in 2.9% of patients, including two patients who discontinued due to rash (0.8%).
Adverse reactions leading to dose interruptions occurred in 69% of patients who received RASONQUE. Adverse reactions which required dose interruptions in ≥ 5% of patients were rash (27%), stomatitis (20%), fatigue (9%), diarrhea (8%), vomiting (8%), nausea (7%), and pyrexia (6%).
Adverse reactions leading to dose reductions occurred in 37% of patients who received RASONQUE. Adverse reactions which required dose reductions in ≥ 5% of patients were rash (18%), stomatitis (8%), and diarrhea (5%).
The most common (≥ 20%) adverse reactions in patients treated with RASONQUE were rash, diarrhea, stomatitis, nausea, fatigue, vomiting, abdominal pain, edema, decreased appetite, and hemorrhage.
Table 3 and Table 4 summarize adverse reactions and laboratory abnormalities in RASolute 302, respectively.
Table 3: Adverse Reactions (≥ 10%) in Patients Who Received RASONQUE in RASolute 302
| Adverse ReactionGraded per NCI CTCAE Version 5.0. | RASONQUE N = 241 | Physician’s Choice SOC Chemotherapy RegimensChemotherapy: mFOLFIRINOX, gemcitabine and nab-paclitaxel, FOLFOX, or nal-IRI+5-FU/LV. N = 214 | ||
|---|---|---|---|---|
| All Grades (%) | Grade 3 or 4 (%) | All Grades (%) | Grade 3 or 4 (%) | |
| Skin and subcutaneous tissue disorders | ||||
| RashIncludes multiple related terms. | 87 | 13 | 9 | 0 |
| Dry skin | 14 | 0 | 3 | 0 |
| Pruritus | 11 | 0.4 | 4 | 0 |
| Gastrointestinal disorders | ||||
| Diarrhea | 67 | 7 | 44 | 8 |
| Stomatitis | 56 | 12 | 19 | 3 |
| Nausea | 52 | 3 | 42 | 2 |
| Vomiting | 42 | 1 | 25 | 1 |
| Abdominal pain | 27 | 2 | 26 | 2 |
| Constipation | 16 | 0.4 | 21 | 0.5 |
| General disorders and administration site conditions | ||||
| Fatigue | 47 | 5 | 61 | 10 |
| Edema | 25 | 0.8 | 22 | 0 |
| Pyrexia | 19 | 1 | 23 | 0.9 |
| Metabolism and nutrition disorders | ||||
| Decreased appetite | 24 | 2 | 27 | 0.9 |
| Vascular disorders | ||||
| Hemorrhage | 22 | 3 | 12 | 4 |
| Musculoskeletal and connective tissue disorders | ||||
| Musculoskeletal pain | 19 | 0.8 | 27 | 1 |
| Infections and infestations | ||||
| Paronychia | 17 | 0 | 0 | 0 |
| Nervous system disorders | ||||
| Neuropathy peripheral | 10 | 0 | 29 | 4 |
Other clinically important adverse reactions occurring in less than 10% of patients who received RASONQUE in RASolute 302 included renal-limited thrombotic microangiopathy (0.4%).
Table 4: Select Laboratory Abnormalities (≥ 20%) that Worsened from Baseline in Patients Who Received RASONQUE in RASolute 302The denominator used to calculate the percentage varied from 234 to 237 in the RASONQUE arm and from 207 to 208 in the SOC chemotherapy arm, based on the number of patients with a baseline value and at least one post-baseline value.
| Laboratory AbnormalityGraded per NCI CTCAE Version 5.0. | RASONQUE | Physician’s Choice SOC Chemotherapy Regimens | ||
|---|---|---|---|---|
All Grades (%) | Grade 3 or 4 (%) | All Grades (%) | Grade 3 or 4 (%) | |
| Chemistry | ||||
| Albumin decreased | 71 | 3 | 51 | 1 |
| Calcium (corrected) decreased | 64 | 2 | 47 | 3 |
| Aspartate aminotransferase increased | 51 | 3 | 36 | 2 |
| Alanine aminotransferase increased | 36 | 4 | 39 | 0.5 |
| Sodium decreased | 36 | 6 | 30 | 5 |
| Magnesium decreased | 34 | 1 | 22 | 1 |
| Alkaline phosphatase increased | 29 | 2 | 24 | 0.5 |
| Creatinine increased | 24 | 0.8 | 9 | 0 |
| Potassium decreased | 20 | 3 | 33 | 7 |
| Hematology | ||||
| Hemoglobin decreased | 52 | 10 | 68 | 20 |
| Lymphocyte cell count decreased | 49 | 11 | 56 | 19 |
| Platelet count decreased | 45 | 3 | 58 | 10 |
| White blood cell count decreased | 35 | 3 | 58 | 17 |
7 DRUG INTERACTIONS
7.1 Effects of Other Drugs on RASONQUE
Table 5: Effects of Other Drugs on RASONQUE
| Strong or Moderate CYP3A Inhibitors with or without P-gp Inhibition | |
| Prevention or Management |
|
| Mechanism and Clinical Effect | Daraxonrasib is a CYP3A and P-gp substrate. Moderate or strong CYP3A inhibitors with or without P-gp inhibition increase daraxonrasib exposure [see Clinical Pharmacology (12.3)], which may increase the risk of adverse reactions. |
| P-gp Inhibitors | |
| Prevention or Management | Reduce RASONQUE dosage to 150 mg once daily [see Dosage and Administration (2.4)]. |
| Mechanism and Clinical Effect | Daraxonrasib is a P-gp substrate. P-gp inhibitors increase daraxonrasib exposure [see Clinical Pharmacology (12.3)], which may increase the risk of adverse reactions. |
| Cyclosporine A | |
| Prevention or Management | Avoid concomitant use of RASONQUE with systemic cyclosporine A or its derivatives. |
| Mechanism and Clinical Effect | Cyclosporine A or its derivatives and daraxonrasib bind to cyclophilin A. Coadministration of systemic cyclosporine A or its derivatives and RASONQUE may have the potential to alter daraxonrasib pharmacokinetics, efficacy, and safety. |
| Strong or Moderate CYP3A Inducers | |
| Prevention or Management |
|
| Mechanism and Clinical Effect | Daraxonrasib is a CYP3A substrate. Strong CYP3A inducers reduce daraxonrasib exposure [see Clinical Pharmacology (12.3)], which may reduce the effectiveness of RASONQUE. |
7.2 Effects of RASONQUE on Other Drugs
P-gp Substrates
Take a P-gp substrate at least 4 hours apart from RASONQUE.
Daraxonrasib is a P-gp inhibitor. Coadministration with RASONQUE increases exposure of P-gp substrates [see Clinical Pharmacology (12.3)], which may increase the risk of adverse reactions related to these substrates.
8 USE IN SPECIFIC POPULATIONS
8.1 Pregnancy
Risk Summary
Based on findings in animals, RASONQUE can cause fetal harm when administered to pregnant women. There are no available data on RASONQUE use in pregnant women to inform a drug-associated risk. In an animal reproduction study, oral administration of daraxonrasib to pregnant female mice during the period of organogenesis resulted in adverse developmental outcomes including mortality, alterations to growth, and structural abnormalities at exposures ≥ 2.5 times the recommended dose based on AUC (see Data). Advise pregnant women of the potential risk to a fetus.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Data
Animal Data
Daraxonrasib was administered orally to pregnant female mice during the period of organogenesis at doses of 25, 50, and 75 mg/kg/day. Daraxonrasib at a dose of ≥ 50 mg/kg/day (≥ 2.5 times the exposure at the recommended dose based on AUC) was associated with post-implantation loss, reduced number of live fetuses, decreased fetal body weights, and malformations including eyes, limbs, palate, gonads, great vessels, kidneys, and bones.
8.2 Lactation
Risk Summary
There are no data on the presence of daraxonrasib or its metabolites in human milk, the effects on the breastfed child, or the effects on milk production. Because of the potential for serious adverse reactions in the breastfed child, advise women not to breastfeed during treatment with RASONQUE and for 1 week after the last dose.
8.3 Females and Males of Reproductive Potential
RASONQUE can cause fetal harm when administered to pregnant women [see Use in Specific Populations (8.1)].
Pregnancy Testing
Verify pregnancy status in females of reproductive potential prior to initiating RASONQUE.
Contraception
Females
Advise females of reproductive potential to use effective contraception during treatment with RASONQUE and for 1 week after the last dose.
Males
Advise males with female partners of reproductive potential to use effective contraception during treatment with RASONQUE and for 1 week after the last dose.
8.4 Pediatric Use
The safety and effectiveness of RASONQUE have not been established in pediatric patients.
8.5 Geriatric Use
Of the 248 patients with pancreatic adenocarcinoma randomized to the RASONQUE arm in the RASolute 302 study, 54% (134 patients) were ≥ 65 years of age and 18% (45 patients) were ≥ 75 years of age. No overall differences in safety or efficacy were observed between patients who were ≥ 65 years of age and younger patients.
11 DESCRIPTION
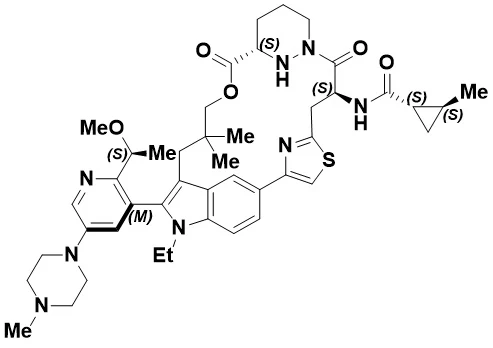
Daraxonrasib is an inhibitor of the RAS GTPase family. The molecular formula is C44H58N8O5S and the molecular weight is 811.06 g/mol. The chemical name is Cyclopropanecarboxamide, N-[(2R,14S,18S)-1-ethyl-18,19,20,21-tetrahydro-2-[2-[(1S)-1-methoxyethyl]-5-(4-methyl-1-piperazinyl)-3-pyridinyl]-25,25-dimethyl-15,22-dioxo-17H-5,3-([4,2]-endo-thiazolopropano[1,3]-endo-pyridazinomethanoxypropano)-1H-indol-14-yl]-2-methyl-, (1S,2S)-. Daraxonrasib has the following chemical structure:
 |
Daraxonrasib is a white to yellow crystalline solid; formulated as a spray-dried dispersion (SDD) and incorporated into a tablet for oral use. Daraxonrasib shows a pH-dependent aqueous solubility across the physiological pH range. Daraxonrasib thermodynamic solubility at 24 hours is greater than 10 mg/mL at pH 1.2, while daraxonrasib solubility is approximately 0.009 mg/mL at pH 6.8.
RASONQUE (daraxonrasib) is supplied as film-coated tablets for oral use containing 150 mg or 100 mg of daraxonrasib. Inactive ingredients in the tablet core are butylated hydroxytoluene, colloidal silicon dioxide, croscarmellose sodium, hydroxypropyl cellulose, hydroxypropyl methylcellulose acetate succinate, magnesium stearate, mannitol, and microcrystalline cellulose. The tablet film coating contains FD&C blue #2/indigo carmine aluminum lake, glyceryl mono and dicaprylocaprate, polyvinyl alcohol, sodium lauryl sulfate, talc, and titanium dioxide.
12 CLINICAL PHARMACOLOGY
12.1 Mechanism of Action
Daraxonrasib is an inhibitor of the RAS GTPase family. Daraxonrasib binds to cyclophilin A, resulting in a binary complex that binds to the active, GTP-bound state of RAS. The tri-complex inhibits RAS signaling by blocking interactions with downstream effectors and promoting GTP hydrolysis to the inactive GDP-bound state of RAS. Daraxonrasib inhibition of wild-type and mutant variants of KRAS, NRAS, and HRAS induces tumor growth suppression and apoptosis. In RAS-dependent models of pancreatic adenocarcinoma, daraxonrasib treatment led to tumor growth inhibition and regression and is associated with antitumor immunity.
12.2 Pharmacodynamics
Exposure-Response Relationships
Daraxonrasib exposure-response relationships and time course of pharmacodynamic response have not been fully characterized.
Based on exposure and safety data from patients with pancreatic adenocarcinoma receiving 10 to 400 mg once daily of daraxonrasib (n = 466), higher daraxonrasib exposure was associated with higher incidence of dose interruption/reduction/discontinuation, Grade ≥ 3 adverse reactions, Grade ≥ 2 dermatologic reactions, mucositis/stomatitis, nausea/vomiting, and diarrhea.
Cardiac Electrophysiology
At the recommended dosage, a mean increase in the QTc interval > 20 msec was not observed.
12.3 Pharmacokinetics
The pharmacokinetics of daraxonrasib were studied in healthy subjects and patients with advanced solid tumors, including patients with pancreatic adenocarcinoma treated with 300 mg once daily, and are presented as geometric mean (geometric percent coefficient of variation), unless otherwise specified.
Daraxonrasib maximum concentration is 365 ng/mL (50%) and total systemic exposure (AUC) is 3760 ng·h/mL (46%). Daraxonrasib AUC increases in an approximately dose proportional manner whereas Cmax increases in a less than dose proportional manner over the dose range of 80 mg (0.27 times the recommended dose) to 300 mg. Minimal to no accumulation was observed for AUC.
Absorption
Daraxonrasib median (min, max) time to reach maximum concentration (Tmax) is approximately 2.2 hours (0.67, 8.0).
Effect of Food
No clinically significant differences in daraxonrasib pharmacokinetics were observed following administration of a high-fat, high-calorie meal (800 to 1000 calories, 50% from fat).
Distribution
Daraxonrasib apparent (oral) volume of distribution during the terminal elimination phase is 1060 L (48%).
Daraxonrasib plasma protein binding is approximately 98% in vitro and is not concentration-dependent. Daraxonrasib blood to plasma ratio is concentration-dependent and ranges from 1.7 to 2.6 in healthy subjects.
Elimination
Daraxonrasib mean (SD) terminal elimination half-life is 9.2 (±2.7) hours with an apparent (oral) clearance (CL/F) of 80.4 L/h (44%).
Metabolism
Daraxonrasib is primarily metabolized by CYP3A.
Excretion
After a single oral dose of radiolabeled daraxonrasib 220 mg to healthy subjects, approximately 93% of the dose was recovered in feces (51% unchanged) and approximately 1% was recovered in urine (1% unchanged).
Specific Populations
No clinically significant differences in the pharmacokinetics of daraxonrasib were observed based on age (19 to 87 years old), sex, race (72% White, 11% Asian, 4% Black or African American), body weight (37 to 171 kg), ECOG PS (0, 1), tumor burden, CLcr 30 to 89 mL/min, or mild (total bilirubin > ULN to 1.5 × ULN or AST > ULN (with bilirubin normal)) or moderate (total bilirubin > 1.5 to 3 × ULN (with any AST level)) hepatic impairment per NCI-ODWG classification. The effects of CLcr < 30 mL/min or severe hepatic impairment (total bilirubin > 3 to 10 × ULN (with any AST level)) on daraxonrasib pharmacokinetics are unknown.
Drug Interaction Studies
Clinical Studies and Model-Informed Approaches
Strong CYP3A Inhibitors with P-gp Inhibition : Daraxonrasib AUC was observed to increase 5.1-fold following concomitant use of itraconazole 200 mg once daily (a strong CYP3A inhibitor with P-gp inhibition).
Strong CYP3A Inhibitors without P-gp Inhibition : Daraxonrasib AUC is predicted to increase 2.0-fold following concomitant use of voriconazole 200 mg twice daily (a strong CYP3A inhibitor without P-gp inhibition).
Moderate CYP3A Inhibitors with P-gp Inhibition : Daraxonrasib AUC is predicted to increase 2.6-fold following concomitant use of verapamil 80 mg three times daily (a moderate CYP3A inhibitor with P-gp inhibition).
Moderate CYP3A Inhibitors without P-gp Inhibition : Daraxonrasib AUC is predicted to increase 1.5-fold following concomitant use of fluconazole 200 mg once daily (a moderate CYP3A inhibitor without P-gp inhibition).
P-gp Inhibitors : Daraxonrasib AUC was observed to increase 1.8-fold following concomitant use of quinidine 300 mg three times daily (a P-gp inhibitor).
Strong CYP3A Inducers : Daraxonrasib AUC was observed to decrease to 50% following concomitant use of phenytoin 100 mg three times daily (a strong CYP3A inducer) and is predicted to decrease to 30% following concomitant use of rifampin 600 mg once daily (a strong CYP3A inducer).
Moderate CYP3A Inducers : Daraxonrasib AUC is predicted to decrease to 50% to 84% following concomitant use of efavirenz 600 mg once daily and modafinil 400 mg once daily (moderate CYP3A inducers).
P-gp Substrates : Free dabigatran Cmax and AUC are predicted to increase 2.5-fold and 2.1-fold, respectively, following concomitant use of RASONQUE 300 mg once daily. No clinically significant differences in free dabigatran pharmacokinetics are predicted when RASONQUE 300 mg once daily is given 4 hours apart from dabigatran etexilate.
Other Drugs : No clinically significant differences in daraxonrasib pharmacokinetics were observed when used concomitantly with esomeprazole (a proton pump inhibitor).
No clinically significant differences in the pharmacokinetics of the following drugs were observed or predicted when used concomitantly with RASONQUE: midazolam (a sensitive CYP3A substrate), rosuvastatin (a BCRP/OATP1B3 substrate), and pravastatin (an OATP1B3 substrate).
13 NONCLINICAL TOXICOLOGY
13.1 Carcinogenesis, Mutagenesis, Impairment of Fertility
Carcinogenesis
Carcinogenesis studies have not been conducted with daraxonrasib.
Mutagenesis
Daraxonrasib was not mutagenic in an in vitro bacterial reverse mutation (Ames) assay, not clastogenic in an in vitro micronucleus assay in human peripheral blood lymphocytes, and not genotoxic in an in vivo mouse bone marrow micronuclei test.
Impairment of Fertility
No fertility studies have been conducted with daraxonrasib. In general toxicology studies in mice and monkeys, there were no remarkable findings in male or female reproductive organs.
13.2 Animal Toxicology and/or Pharmacology
In a 4-week toxicity study in mice, increased bone remodeling was observed at ≥ 10 mg/kg/day (exposures at or greater than the recommended dose based on AUC) and was partially reversible. The finding was characterized by increased number and size of osteoclasts (metaphyseal cut-back zone and diaphyseal periosteum) and structural bone changes (wider cortical walls, wider Haversian canals, larger osteocytes/lacunae).
14 CLINICAL STUDIES
The efficacy of RASONQUE was evaluated in a global, randomized, open-label, multicenter study (RASolute 302; NCT06625320). Patients were required to have metastatic pancreatic adenocarcinoma with disease progression after receiving one prior line of systemic therapy, which included either a fluoropyrimidine-based or gemcitabine-based regimen, an Eastern Cooperative Oncology Group Performance Status (ECOG PS) of 0 or 1, investigator-assessed measurable disease as defined by Response Evaluation Criteria in Solid Tumors (RECIST v1.1), and documentation of locally available RAS mutation status (mutant or wild-type).
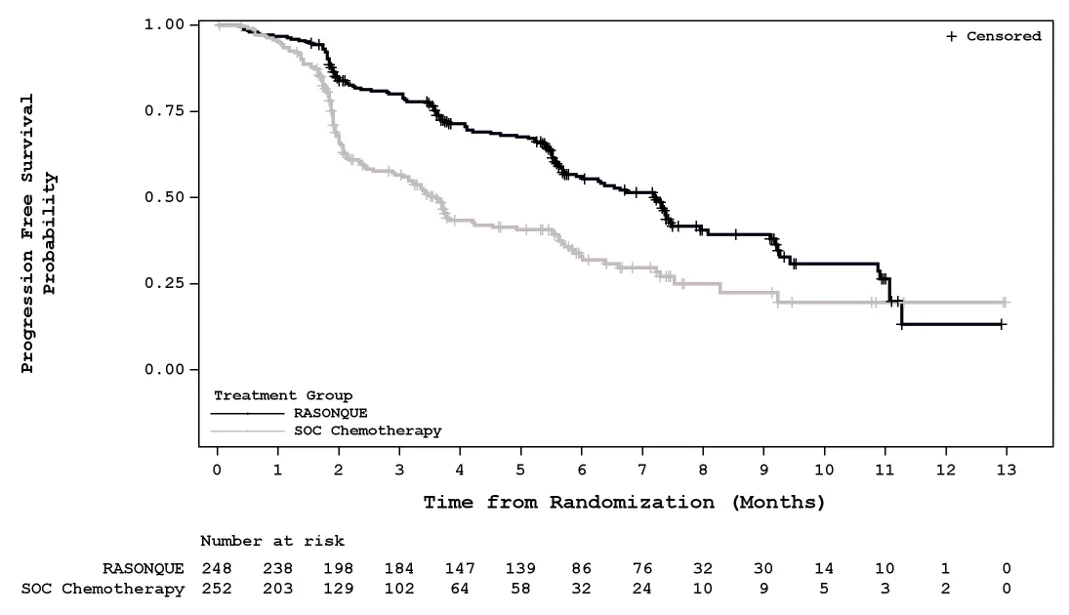
A total of 500 patients were randomized 1:1 to receive either RASONQUE 300 mg orally once daily (N = 248) or physician’s choice of standard of care (SOC) chemotherapy regimens (mFOLFIRINOX, gemcitabine and nab-paclitaxel, FOLFOX, or nal-IRI+5-FU/LV) (N = 252). Patients were treated until disease progression or unacceptable toxicity. The major efficacy outcomes were overall survival (OS) and progression-free survival (PFS) as assessed by blinded independent central review (BICR) in patients with a RAS G12 mutation (RAS G12 population). Additional efficacy outcomes included OS and PFS as assessed by BICR in the overall population and objective response rate (ORR) as assessed by BICR in the RAS G12 population and overall population.
The baseline demographics and disease characteristics were: median age 66 years (range: 30 to 88); 45% Female; 68% White, 11% Asian, 4% Black or African American; 50% ECOG PS 1; and 70% had liver metastases. Of the 500 patients randomized in the study, 92% of patients had KRAS G12 mutations, 5% had KRAS mutations at locations other than G12 (i.e., G13 and Q61), and 3% of patients did not have a RAS mutation detected by local testing.
RASolute 302 demonstrated a statistically significant improvement in OS, PFS, and ORR for patients treated with RASONQUE compared to SOC chemotherapy in the RAS G12 population and in the overall population.
Efficacy results for the overall population are summarized in Table 6 and Figures 1 and 2.
Table 6: Efficacy Results from RASolute 302 (Overall Population)
| Efficacy Parameter | RASONQUE N = 248 | Physician’s Choice SOC Chemotherapy RegimensChemotherapy: mFOLFIRINOX, gemcitabine and nab-paclitaxel, FOLFOX, or nal-IRI+5-FU/LV. N = 252 |
|---|---|---|
| CI = confidence interval; NE = not estimable | ||
| Overall Survival | ||
| Number of events (%) | 79 (32%) | 141 (56%) |
| Median, months (95% CI) | 13.2 (10.0, NE) | 6.7 (5.8, 8.0) |
| Hazard Ratio (95% CI)Based on the stratified Cox proportional hazard model. | 0.40 (0.30, 0.53) | |
| p-valueTwo-sided p-value based on stratified log-rank test. | < 0.0001 | |
| Progression-Free SurvivalAssessed by BICR in all randomized patients. | ||
| Number of events (%) | 127 (51%) | 130 (52%) |
| Median, months (95% CI) | 7.2 (5.7, 7.5) | 3.6 (2.9, 4.2) |
| Hazard Ratio (95% CI) | 0.49 (0.38, 0.64) | |
| p-value | < 0.0001 | |
| Objective Response Rate, % (95% CI) | 30 (25, 36) | 11 (7, 15) |
| Complete response, % | 1.2 | 0.8 |
| Partial response, % | 29 | 10 |
| p-valueTwo-sided p-value based on stratified Cochran-Mantel-Haenszel chi-square test comparing response rate by BICR in patients with measurable disease by BICR at baseline. | < 0.0001 | |
In the RAS G12 population (n = 459), median OS was 13.2 months in the RASONQUE arm vs. 6.6 months in the SOC chemotherapy arm [HR: 0.40 (95% CI: 0.30, 0.54), p-value < 0.0001] and median PFS assessed by BICR was 7.3 months in the RASONQUE arm vs. 3.5 months in the SOC chemotherapy arm [HR: 0.45 (95% CI: 0.34, 0.59), p-value < 0.0001]. Additionally, in the RAS G12 population, ORR assessed by BICR in all randomized patients was 32% (95% CI: 26%, 38%) in the RASONQUE arm vs. 11% (95% CI: 7%, 16%) in the SOC chemotherapy arm [p-value < 0.0001].
Figure 1: Kaplan-Meier Curve of Overall Survival in RASolute 302 (Overall Population)
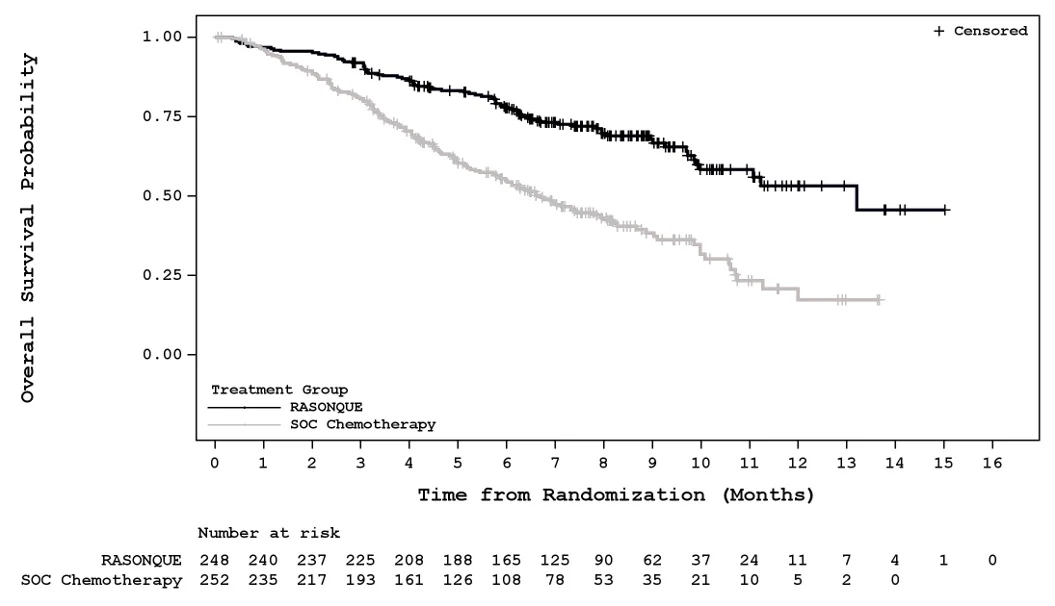 |
Figure 2: Kaplan-Meier Curve of Progression-Free Survival by BICR in RASolute 302 (Overall Population)
 |
16 HOW SUPPLIED/STORAGE AND HANDLING
RASONQUE tablets are packaged in a bottle containing one desiccant and a child-resistant cap, available as follows:
| Strength | Description | Bottle | NDC Number |
|---|---|---|---|
| 100 mg | blue, oval, biconvex, film-coated, debossed with “R” on one side and “100 M” on the other side | 30 tablets | 85219-101-01 |
| 150 mg | blue, oval, biconvex, film-coated, debossed with “R” on one side and “150 M” on the other side | 30 tablets | 85219-104-01 |
Store at 20°C to 25°C (68°F to 77°F), excursions permitted between 15°C and 30°C (59°F and 86°F) [see USP Controlled Room Temperature].
17 PATIENT COUNSELING INFORMATION
Advise the patient to read the FDA-approved patient labeling (Medication Guide).
Dermatologic Reactions
Advise patients of the risk of dermatologic reactions including rash and to use prophylactic measures. Advise patients to limit sun exposure and contact their healthcare provider if they experience dermatologic reactions [see Dosage and Administration (2.1) and Warnings and Precautions (5.1)].
Stomatitis
Advise patients of the risk of stomatitis. Advise patients to contact their healthcare provider for new onset or worsening stomatitis [see Warnings and Precautions (5.2)].
Diarrhea
Advise patients to contact their healthcare provider if they experience new onset or worsening diarrhea [see Warnings and Precautions (5.3)].
Gastrointestinal Perforation
Advise patients to contact their healthcare provider immediately if they experience severe abdominal pain or other symptoms of gastrointestinal perforation [see Warnings and Precautions (5.4)].
Interstitial Lung Disease (ILD)/Pneumonitis
Advise patients to contact their healthcare provider immediately if they experience new or worsening respiratory symptoms [see Warnings and Precautions (5.5)].
Embryo-Fetal Toxicity
Advise females to inform their healthcare provider if they are pregnant or become pregnant. Inform females of the potential risk to a fetus [see Warnings and Precautions (5.6)].
Advise females of reproductive potential to use effective contraception during treatment with RASONQUE and for 1 week after the last dose [see Warnings and Precautions (5.6) and Use in Specific Populations (8.3)].
Advise males with female partners of reproductive potential to use effective contraception during treatment with RASONQUE and for 1 week after the last dose [see Warnings and Precautions (5.6) and Use in Specific Populations (8.3)].
Lactation
Advise women not to breastfeed during treatment with RASONQUE and for 1 week after the last dose [see Use in Specific Populations (8.2)].
Drug Interactions
Advise patients to inform their healthcare provider of all concomitant medications, including prescription medicines, over-the-counter drugs, vitamins, and herbal products [see Drug Interactions (7.1)].
Manufactured for:
Revolution Medicines, Inc.
Redwood City, CA 94063 USA
RASONQUE™ is a trademark of Revolution Medicines, Inc.
© 2026 Revolution Medicines, Inc.
Pat.: http://www.revmed.com/patents/