


Prescribing information (package insert) - Qnasl
1. INDICATIONS AND USAGE
1.1 Treatment of Nasal Symptoms of Allergic Rhinitis
QNASL® Nasal Aerosol is indicated for the treatment of the nasal symptoms associated with seasonal and perennial allergic rhinitis in patients 4 years of age and older.
2. DOSAGE AND ADMINISTRATION
Administer QNASL Nasal Aerosol by the intranasal route only. The dose counter should read “120” for QNASL 80 mcg Nasal Aerosol 120-actuation product and “60” for QNASL 40 mcg Nasal Aerosol 60-actuation product. QNASL Nasal Aerosol does not require priming. See accompanying illustrated Patient Information and Instructions for Use leaflet for proper use of QNASL Nasal Aerosol.
2.1 Allergic Rhinitis
Adults and Adolescents (12 Years of Age and Older): The recommended dose of QNASL Nasal Aerosol is 320 mcg per day administered as 2 actuations in each nostril (QNASL 80 mcg Nasal Aerosol) once daily (maximum total daily dose of 4 actuations per day).
Children (4 to 11 Years of Age): The recommended dose of QNASL Nasal Aerosol is 80 mcg per day administered as 1 actuation in each nostril (QNASL 40 mcg Nasal Aerosol) once daily (maximum total daily dose of 2 actuations per day).
3. DOSAGE FORMS AND STRENGTHS
QNASL Nasal Aerosol is a nonaqueous nasal spray solution.
Each actuation of QNASL 80 mcg Nasal Aerosol delivers 80 mcg of beclomethasone dipropionate and each actuation of QNASL 40 mcg Nasal Aerosol delivers 40 mcg of beclomethasone dipropionate. QNASL 80 mcg Nasal Aerosol is supplied in a 10.6 g canister containing 120 actuations; QNASL 40 mcg Nasal Aerosol is supplied in a 6.8 g canister containing 60 actuations.
4. CONTRAINDICATIONS
QNASL Nasal Aerosol is contraindicated in patients with a history of hypersensitivity to beclomethasone dipropionate and/or any other QNASL Nasal Aerosol ingredients [see Warnings and Precautions (5.3)].
5. WARNINGS AND PRECAUTIONS
5.1 Local Nasal Effects
Nasal Discomfort, Epistaxis, and Nasal Ulceration: In clinical trials of 2 to 52 weeks duration, epistaxis and nasal ulcerations were observed more frequently and some epistaxis events were more severe in patients treated with QNASL Nasal Aerosol than those who received placebo. In the 52-week safety trial in patients with perennial allergic rhinitis, nasal erosions were identified in 4 of 415 patients and a nasal ulceration was identified in 1 of 415 patients treated with QNASL Nasal Aerosol. No nasal erosions or ulcerations were reported for patients who received placebo. In clinical trials conducted in pediatric patients ages 4 to 11 years, the local nasal effect was similar to those reported in patients 12 years of age and older. Patients using QNASL Nasal Aerosol over several months or longer should be examined periodically for possible changes in the nasal mucosa. If an adverse reaction (e.g., erosion, ulceration) is noted, discontinue QNASL Nasal Aerosol [see Adverse Reactions (6.1)].
Candida Infection: In previous clinical trials with an aqueous formulation of beclomethasone dipropionate administered intranasally, localized infections of the nose and pharynx with Candida albicans had been reported. There were no instances of similar infections observed in clinical trials with QNASL Nasal Aerosol. If such an infection develops, it may require treatment with appropriate local therapy and discontinuation of QNASL Nasal Aerosol treatment. Thus, patients using QNASL Nasal Aerosol over several months or longer should be examined periodically for evidence of Candida infection.
Nasal Septal Perforation: Instances of nasal septal perforation have been reported in patients following the intranasal application of beclomethasone dipropionate. There were no nasal septal perforations reported during clinical trials in the indicated dose of QNASL 80 mcg Nasal Aerosol administered as 320 mcg once daily in adults and adolescents. There was one report of nasal septal perforation observed in the dose-ranging pediatric clinical trial.
Impaired Wound Healing: Because of the inhibitory effect of corticosteroids on wound healing, patients who have experienced recent nasal septal ulcers, nasal surgery, or nasal trauma should not use QNASL Nasal Aerosol until healing has occurred.
5.2 Eye Disorders
Use of intranasal and inhaled corticosteroids may result in the development of increased intraocular pressure, blurred vision, glaucoma and/or cataracts. Therefore, close monitoring is warranted in patients with a change in vision or with a history of increased intraocular pressure, blurred vision, glaucoma, and/or cataracts.
Glaucoma and cataract formation was evaluated with ocular assessments that included intraocular pressure measurements and slit lamp examinations in 245 adolescent and adult patients (12 years of age and older) with perennial allergic rhinitis who were treated with QNASL Nasal Aerosol 320 mcg daily (N=197) or placebo (N=48) for up to 52 weeks. In 94% of patients, intraocular pressure (IOP) remained within the normal range (<21 mmHg) during the treatment portion of the trial. There were 10 patients (5%) treated with QNASL Nasal Aerosol and 1 patient (2%) treated with placebo that had intraocular pressure that increased above normal levels (≥21 mmHg) and greater than baseline during the treatment portion of the trial. Two of these occurrences in patients treated with QNASL Nasal Aerosol were reported as adverse reactions, one serious. No instances of cataract formation or other clinically significant ocular incidents were reported in this 52-week safety trial [see Adverse Reactions (6.1)].
5.3 Hypersensitivity Reactions Including Anaphylaxis
Hypersensitivity reactions including anaphylaxis, angioedema, urticaria, and rash have been reported following administration of beclomethasone dipropionate nasally administered and inhalationally administered products. Angioedema, urticaria, and rash have been reported following administration of QNASL Nasal Aerosol. Discontinue QNASL Nasal Aerosol if any such reactions occur [see Contraindications (4)].
5.4 Immunosuppression
Persons who are using drugs that suppress the immune system (e.g., corticosteroids) are more susceptible to infections than healthy individuals. Chickenpox and measles, for example, can have a more serious or even fatal course in susceptible children or adults using corticosteroids. In children or adults who have not had these diseases or been properly immunized, particular care should be taken to avoid exposure. How the dose, route, and duration of corticosteroid administration affect the risk of developing a disseminated infection is not known. The contribution of the underlying disease and/or prior corticosteroid treatment to the risk is also not known. If a patient is exposed to chickenpox, prophylaxis with varicella zoster immune globulin (VZIG) may be indicated. If a patient is exposed to measles, prophylaxis with pooled intramuscular immunoglobulin (IG) may be indicated (see the respective package inserts for complete VZIG and IG prescribing information). If chickenpox or measles develops, treatment with antiviral agents may be considered.
Corticosteroids should be used with caution, if at all, in patients with active or quiescent tuberculous infections of the respiratory tract, untreated local or systemic fungal or bacterial infections, systemic viral or parasitic infections, or ocular herpes simplex because of the potential for worsening of these infections.
5.5 Hypothalamic-Pituitary-Adrenal Axis Effect
When intranasal steroids are used at higher-than-recommended dosages or in susceptible individuals at recommended dosages, systemic corticosteroid effects such as hypercorticism and adrenal suppression may appear. If such changes occur, the dosage of QNASL Nasal Aerosol should be discontinued slowly, consistent with accepted procedures for discontinuing oral corticosteroid therapy.
The replacement of a systemic corticosteroid with a topical corticosteroid can be accompanied by signs of adrenal insufficiency. In addition, some patients may experience symptoms of corticosteroid withdrawal (e.g., joint and/or muscular pain, lassitude, and depression). Patients previously treated for prolonged periods with systemic corticosteroids and transferred to topical corticosteroids should be carefully monitored for acute adrenal insufficiency in response to stress. In patients who have asthma or other clinical conditions requiring long-term systemic corticosteroid treatment, rapid decreases in systemic corticosteroid dosages may cause a severe exacerbation of their symptoms.
5.6 Effect on Growth
Corticosteroids may cause a reduction in growth velocity when administered to pediatric patients. Routinely monitor the growth of pediatric patients receiving QNASL Nasal Aerosol [see Use in Specific Populations (8.4)].
6 ADVERSE REACTIONS
Systemic and local corticosteroid use may result in the following:
- Epistaxis, nasal discomfort, nasal ulcerations, Candida albicans infection, and impaired wound healing [see Warnings and Precautions (5.1)]
- Eye Disorders [see Warnings and Precautions (5.2)]
- Hypercorticism, adrenal suppression, and growth reduction [see Warnings and Precautions (5.5) (5.6) , Use in Specific Populations (8.4)]
- Immunosuppression [see Warnings and Precautions (5.4)]
6.1 Clinical Trials Experience
Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared with rates in the clinical trials of another drug and may not reflect the rates observed in practice.
Adults and Adolescents 12 Years of Age and Older:
The safety data described below for adults and adolescents 12 years of age and older with seasonal or perennial allergic rhinitis are based on 4 placebo-controlled clinical trials of 2 to 6 weeks duration evaluating doses of beclomethasone nasal aerosol from 80 to 320 mcg once daily. These short-term trials included a total of 1394 patients with either seasonal or perennial allergic rhinitis. Of these, 575 (378 female and 197 male) received at least one dose of QNASL Nasal Aerosol, 320 mcg once daily and 578 (360 female and 218 male) received placebo. Patient ages ranged from 12 to 82 years and the racial distribution of patients was 81% white, 16% black, and 4% other.
Short-Term (2–6 Weeks) Trials: Less than 2% of patients in the clinical trials discontinued treatment because of adverse reactions with the rate of withdrawal among patients who received QNASL Nasal Aerosol similar to or lower than the rate among patients who received placebo. Table 1 displays the common adverse reactions (≥ 1% and greater than placebo-treated patients).
| Table 1. Adverse Events With ⊃; 1% Incidence and Greater than Placebo in QNASL Nasal Aerosol-Treated Adult and Adolescent Patients with Seasonal or Perennial Allergic Rhinitis in Controlled Clinical Trials of 2 to 6 Weeks Duration (Safety Population) | ||
|---|---|---|
| Adult and Adolescent Patients 12 Years of Age and Older | ||
| QNASL Nasal Aerosol320 mcg(N=575)n (%) | Placebo(N=578)n (%) | |
| Nasal Discomfort | 30 (5.2) | 28 (4.8) |
| Epistaxis | 11 (1.9) | 7 (1.2) |
| Headache | 13 (2.3) | 9 (1.6) |
Nasal ulcerations occurred in 2 patients treated with placebo and in 1 patient treated with QNASL Nasal Aerosol. There were no differences in the incidence of adverse reactions based on gender or race. Clinical trials did not have sufficient numbers of patients aged 65 years and older to determine whether they respond differently than younger patients.
Long-Term 52-Week Safety Trial: In a 52-week placebo-controlled long-term safety trial in patients with PAR, 415 patients (128 males and 287 females, aged 12 to 74 years) were treated with QNASL Nasal Aerosol at a dose of 320 mcg once daily and 111 patients (44 males and 67 females, aged 12 to 67 years) were treated with placebo. Of the 415 patients treated with QNASL Nasal Aerosol, 219 patients were treated for 52 weeks and 196 patients were treated for 30 weeks. While most adverse events were similar in type and rate between the treatment groups, epistaxis occurred more frequently in patients who received QNASL Nasal Aerosol (45 out of 415, 11%) than in patients who received placebo (2 out of 111, 2%). Epistaxis also tended to be more severe in patients treated with QNASL Nasal Aerosol. In 45 reports of epistaxis in patients who received QNASL Nasal Aerosol, 27, 13, and 5 cases were of mild, moderate, and severe intensity, respectively, while the reports of epistaxis in patients who received placebo were of mild (1) and moderate (1) intensity. Seventeen patients treated with QNASL Nasal Aerosol experienced adverse reactions that led to withdrawal from the trial compared to 3 patients treated with placebo. There were 4 nasal erosions and 1 nasal septum ulceration which occurred in patients who received QNASL Nasal Aerosol, and no erosions or ulcerations noted in patients who received placebo. No patient experienced a nasal septum perforation during the trial.
Pediatric Patients Aged 4 to 11 Years:
The safety data described below for pediatric patients 4 to 11 years of age with seasonal or perennial allergic rhinitis are based on 3 placebo-controlled clinical trials. These trials were 2 to 12 weeks in duration, evaluated doses of beclomethasone nasal aerosol 80 mcg to 160 mcg once daily and included a total of 1360 patients with either seasonal or perennial allergic rhinitis. Of these, 668 (312 female and 356 male) received at least one dose of QNASL Nasal Aerosol, 80 mcg once daily, 241 (116 female and 125 male) received QNASL Nasal Aerosol 160 mcg once daily, and 451 (203 female and 248 male) received placebo. The racial distribution of patients was 73% white, 20% black, and 6% other. Based on the results from the dose ranging trial, 80 mcg once daily was chosen as the dose in pediatric patients.
Less than 1.5% of patients in the clinical trials discontinued treatment because of adverse reactions with the rate of withdrawal among patients who received QNASL Nasal Aerosol 80 mcg once daily similar to or lower than the rate among patients who received placebo. Table 2 displays the common adverse reactions (≥ 2% and greater than placebo-treated patients). Additionally, epistaxis was reported at a rate of 4% for both QNASL Nasal Aerosol 80 mcg once daily and placebo-treated patients.
| Table 2. Adverse Events With ≥ 2% Incidence and Greater than Placebo in QNASL Nasal Aerosol-Treated Pediatric Patients with Seasonal or Perennial Allergic Rhinitis in Controlled Clinical Trials of 2 to 12 weeks Duration (Safety Population) | ||
| Pediatric Patients 4 to 11 Years of Age | ||
QNASL Nasal Aerosol 80 mcg (N=668) n (%) | Placebo (N=451) n (%) | |
| Headache | 23 (3.4) | 15 (3.3) |
| Pyrexia | 19 (2.8) | 7 (1.6) |
| Upper respiratory tract infection | 17 (2.5) | 8 (1.8) |
| Nasopharyngitis | 15 (2.2) | 6 (1.3) |
6.2 Postmarketing Experience
In addition to adverse reactions reported from clinical trials for QNASL Nasal Aerosol, the following adverse events have been reported during postmarketing use of QNASL Nasal Aerosol or other intranasal and inhaled formulations of beclomethasone dipropionate. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. These events have been chosen for inclusion due to either their seriousness, frequency of reporting, or causal connection to beclomethasone dipropionate or a combination of these factors.
QNASL Nasal Aerosol: sneezing, burning sensation
Intranasal beclomethasone dipropionate: Nasal septal perforation, blurred vision, glaucoma, cataracts, central serous chorioretinopathy (CSC), loss of taste and smell, and hypersensitivity reactions including anaphylaxis, angioedema, rash, and urticaria have been reported following intranasal administration of beclomethasone dipropionate.
Inhaled beclomethasone dipropionate: Hypersensitivity reactions, including anaphylaxis, angioedema, rash, urticaria, and bronchospasm have been reported following the oral inhalation of beclomethasone dipropionate.
7 DRUG INTERACTIONS
No drug interaction studies have been performed with QNASL Nasal Aerosol.
8 USE IN SPECIFIC POPULATIONS
8.1 Pregnancy
Risk Summary
There are no adequate and well-controlled studies with QNASL Nasal Aerosol or beclomethasone dipropionate in pregnant women. No published studies, including studies of large birth registries, have to date related the use of inhaled corticosteroids (ICS) or intranasal corticosteroids to any increases in congenital malformations or other adverse perinatal outcomes. Thus, available human data do not establish the presence or absence of drug‑associated risk to the fetus. In animal reproduction studies, beclomethasone dipropionate resulted in adverse developmental effects in mice and rabbits at subcutaneous doses equal to or greater than approximately 1.5 times the maximum recommended human dose (MRHD) in adults (0.32 mg/day) (see Data). In rats exposed to beclomethasone dipropionate by inhalation, dose‑related gross injury to the fetal adrenal glands was observed at doses greater than 350 times the MRHD, but there was no evidence of external or skeletal malformations or embryolethality at inhalation doses of up to 860 times the MRHD.
The estimated background risk of major birth defects and miscarriage for the indicated population(s) are unknown. In the US general population, the estimated risk of major birth defects and miscarriage in clinically recognized pregnancies is 2‑4% and 15‑20%, respectively.
Clinical Considerations
Labor or Delivery
There are no specific human data regarding any adverse effects of intranasal beclomethasone dipropionate on labor and delivery.
Data
Animal Data
In an embryofetal development study in pregnant rats, beclomethasone dipropionate administration during organogenesis from gestation days 6 to 15 at inhaled doses 350 times the MRHD in adults and higher (on a mg/m2 basis at maternal doses of 11.5 and 28.3 mg/kg/day) produced dose‑dependent gross injury (characterized by red foci) of the adrenal glands in fetuses. There were no findings in the adrenal glands of rat fetuses at an inhaled dose that was 75 times the MRHD in adults (on a mg/m2 basis at a maternal dose of 2.4 mg/kg/day). There was no evidence of external or skeletal malformations or embryolethality in rats at inhaled doses up to 860 times the MRHD (on a mg/m2 basis at maternal doses up to 28.3 mg/kg/day).
In an embryofetal development study in pregnant mice, beclomethasone dipropionate administration from gestation days 1 to 18 at subcutaneous doses equal to and greater than 1.5 times the MRHD in adults (on a mg/m2 basis at maternal doses of 0.1 mg/kg/day and higher) produced adverse developmental effects (increased incidence of cleft palate). A no-effect dose in mice was not identified. In a second embryofetal development study in pregnant mice, beclomethasone dipropionate administration from gestation days 1 to 13 at subcutaneous doses equal to and greater than 5 times the MRHD in adults (on a mg/m2 basis at a maternal dose of 0.3 mg/kg/day) produced embryolethal effects (increased fetal resorptions) and decreased pup survival.
In an embryofetal development study in pregnant rabbits, beclomethasone dipropionate administration during organogenesis from gestation days 7 to 16 at subcutaneous doses equal to and greater than 1.5 times the MRHD in adults (on a mg/m2 basis at maternal doses of 0.025 mg/kg/day and higher) produced external and skeletal malformations and embryolethal effects (increased fetal resorptions). There were no effects in fetuses of pregnant rabbits administered a subcutaneous dose 0.4 times the MRHD in adults (on a mg/m2 basis at a maternal dose of 0.006 mg/kg/day).
8.2 Lactation
Risk Summary
There are no data available on the presence of beclomethasone dipropionate in human milk, the effects on the breastfed child, or the effects on milk production. However, other corticosteroids have been detected in human milk. The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for QNASL and any potential adverse effects on the breastfed child from beclomethasone dipropionate or from the underlying maternal condition.
8.3 Females and Males of Reproductive Potential
Impairment of fertility was observed in rats and dogs at oral doses of beclomethasone dipropionate corresponding to 500 and 50 times the MRHD for adults on a mg/m2 basis, respectively. [see Nonclinical Toxicology (13.1)].
8.4 Pediatric Use
The safety and effectiveness of QNASL Nasal Aerosol in children 4 years and older have been established [see Adverse Reactions (6.1), Clinical Pharmacology (12.3), Clinical Studies (14)]. The safety and effectiveness of QNASL Nasal Aerosol in children younger than 4 years of age have not been established. Controlled pediatric clinical trials with QNASL Nasal Aerosol included 909 children 4 to 11 years of age and 188 adolescent patients 12 to 17 years of age [see Clinical Studies (14)].
Controlled clinical trials have shown that intranasal corticosteroids may cause a reduction in growth velocity in pediatric patients. This effect has been observed in the absence of laboratory evidence of hypothalamic-pituitary-adrenal (HPA) axis suppression, suggesting that growth velocity is a more sensitive indicator of systemic corticosteroid exposure in pediatric patients than some commonly used tests of HPA-axis function. The long-term effects of reduction in growth velocity associated with intranasal corticosteroids, including the impact on final adult height, are unknown. The potential for "catch-up" growth following discontinuation of treatment with intranasal corticosteroids has not been adequately studied. The growth of pediatric patients receiving intranasal corticosteroids, including QNASL Nasal Aerosol, should be monitored routinely (e.g., via stadiometry).
A 12-month, randomized, controlled clinical trial evaluated the effects of QVAR®, an orally inhaled HFA beclomethasone dipropionate product, without spacer versus chlorofluorocarbon-propelled (CFC) beclomethasone dipropionate with large volume spacer on growth in children with asthma ages 5 to 11 years. A total of 520 patients were enrolled, of whom 394 received HFA-beclomethasone dipropionate (100 to 400 mcg/day ex-valve) and 126 received CFC-beclomethasone dipropionate (200 to 800 mcg/day ex-valve). When comparing results at month 12 to baseline, the mean growth velocity in children treated with HFA-beclomethasone dipropionate was approximately 0.5 cm/year less than that noted with children treated with CFC-beclomethasone dipropionate via large volume spacer. The potential growth effects of prolonged treatment should be weighed against the clinical benefits obtained and the risks/benefits of treatment alternatives.
The potential for QNASL Nasal Aerosol to cause reduction in growth velocity in susceptible patients or when given at higher than recommended dosages cannot be ruled out.
8.5 Geriatric Use
Clinical trials of QNASL Nasal Aerosol did not include sufficient numbers of subjects aged 65 years and older to determine whether they responded differently than younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. In general, administration to elderly patients should be cautious, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
10 OVERDOSAGE
Chronic overdosage may result in signs/symptoms of hypercorticism [see Warnings and Precautions (5.5)]. There are no data available on the effects of acute or chronic overdosage with QNASL Nasal Aerosol.
11 DESCRIPTION
Beclomethasone dipropionate USP, the active component of QNASL Nasal Aerosol, is an anti-inflammatory steroid having the chemical name 9-chloro-11β,17,21-trihydroxy-16β-methylpregna-1,4-diene-3,20-dione 17, 21-dipropionate and the following chemical structure:
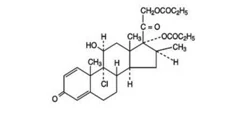
Beclomethasone dipropionate, a di-ester of beclomethasone (a synthetic corticosteroid chemically related to dexamethasone), is a white to almost white, odorless powder with a molecular formula of C28H37ClO7 and a molecular weight of 521.1. It is practically insoluble in water, very soluble in chloroform, and soluble in acetone and in dehydrated alcohol.
QNASL Nasal Aerosol is a pressurized, nonaqueous solution in a metered-dose aerosol device intended ONLY for intranasal use. It contains a solution of beclomethasone dipropionate in propellant HFA‑134a (1,1,1,2‑tetrafluoroethane) and dehydrated ethanol. QNASL 40 mcg Nasal Aerosol delivers 40 mcg of beclomethasone dipropionate from the nasal actuator and 50 mcg from the valve. QNASL 80 mcg Nasal Aerosol delivers 80 mcg of beclomethasone dipropionate from the nasal actuator and 100 mcg from the valve. Each strength delivers 59 mg of solution from the valve with each actuation. Each QNASL 80 mcg Nasal Aerosol canister contains 10.6 g of drug and excipients and provides 120 actuations. Each QNASL 40 mcg Nasal Aerosol canister contains 6.8 g of drug and excipients and provides 60 actuations.
12 CLINICAL PHARMACOLOGY
12.1 Mechanism of Action
Beclomethasone dipropionate is a prodrug that is extensively converted to the active metabolite, beclomethasone-17-monopropionate. The precise mechanism through which beclomethasone dipropionate affects rhinitis symptoms is unknown. Corticosteroids have been shown to have multiple anti-inflammatory effects, inhibiting both inflammatory cells (e.g., mast cells, eosinophils, basophils, lymphocytes, macrophages, and neutrophils) and the release of inflammatory mediators (e.g., histamine, eicosanoids, leukotrienes, and cytokines).
Beclomethasone-17-monopropionate has been shown in vitro to exhibit a binding affinity for the human glucocorticoid receptor which is approximately 13 times that of dexamethasone, 6 times that of triamcinolone acetonide, 1.5 times that of budesonide and 25 times that of beclomethasone dipropionate. The clinical significance of these findings is unknown.
12.2 Pharmacodynamics
Adrenal Function: The effects of QNASL Nasal Aerosol on the HPA axis were evaluated in two 6-week, randomized, double-blind, parallel-group perennial allergic rhinitis trials – one in adult and adolescent patients 12 to 45 years of age and another in children 6 to 11 years of age. In the first study with adolescent and adult patients aged 12 to 45, QNASL Nasal Aerosol 320 mcg, once daily, was compared with both placebo nasal aerosol and a positive control (a placebo/prednisone group that received prednisone 10 mg orally once daily for the final 7 days of the treatment period). In the second study with pediatric patients aged 6 to 11, QNASL Nasal Aerosol 80 mcg once daily was compared to placebo nasal aerosol. HPA-axis function was assessed by 24-hour serial serum cortisol levels prior to the first dose and after 6 weeks of treatment. Patients were domiciled for the 24-hour serum cortisol assessments. The change from baseline in the 24-hour serum cortisol weighted mean for QNASL Nasal Aerosol and placebo after 6 weeks of treatment were compared.
In the HPA–axis study in patients 12 to 45 years of age, baseline geometric mean serum cortisol weighted mean values were similar in the QNASL Nasal Aerosol 320 mcg/day and placebo treatment groups (9.04 and 8.45 mcg/dL, respectively). After 6 weeks of treatment, the geometric mean values were 8.18 and 8.01 mcg/dL, respectively, with a change from baseline in 24-hour serum cortisol weighted mean for the QNASL Nasal Aerosol and placebo groups of 0.86 and 0.44, resulting in a difference of 0.42. The geometric mean ratio for QNASL Nasal Aerosol 320 mcg/day to placebo was 0.96 (95% CI: 0.87, 1.06). For comparison, in the positive-control (prednisone) treatment group, the geometric mean ratio for placebo to placebo/prednisone 10 mg/day was 3.17 (95% CI: 2.68, 3.74).
In the HPA-axis study in patients 6 to 11 years of age, baseline geometric mean serum cortisol weighted mean values were similar in the QNASL Nasal Aerosol 80 mcg/day and placebo treatment groups (5.97 and 6.47 mcg/dL, respectively). After 6 weeks of treatment the geometric mean values were 6.19 and 7.13 mcg/dL, respectively with no decrease from baseline values in both treatment groups. The geometric mean ratio for QNASL Nasal Aerosol 80 mcg/day to placebo was 0.91 (95% CI; 0.81, 1.03).
12.3 Pharmacokinetics
Absorption
Following intranasal administration, most of the beclomethasone dipropionate undergoes extensive conversion to its active metabolite, beclomethasone-17-monopropionate, during absorption. Plasma concentrations of beclomethasone dipropionate and beclomethasone-17-monopropionate have been measured with QNASL Nasal Aerosol in 2 adult and/or adolescent clinical trials and 1 pediatric clinical trial.
The single-dose pharmacokinetics of QNASL Nasal Aerosol were evaluated in a randomized, open-label, 3-period, crossover trial in healthy adult volunteers. Systemic levels of beclomethasone-17-monopropionate and beclomethasone dipropionate after single-dose intranasal administration of beclomethasone dipropionate at doses of 80 and 320 mcg were compared with the systemic levels of beclomethasone-17-monopropionate and beclomethasone dipropionate after administration of orally inhaled beclomethasone dipropionate HFA at a dose of 320 mcg (QVAR® Inhalation Aerosol). The results of this trial demonstrated that the systemic bioavailability of QNASL Nasal Aerosol 320 mcg was approximately 27.5% (approximately 4-fold lower) of that of orally inhaled beclomethasone dipropionate HFA 320 mcg/day based on the plasma concentrations of beclomethasone-17-monopropionate (AUClast: 1139.7 vs 4140.3 hr*pg/mL; GMR: 0.275; 90% CI for the GMR: 0.214, 0.354). The peak exposure to QNASL Nasal Aerosol 320 mcg/day was approximately 19.5% (approximately 5-fold lower) of that of orally inhaled beclomethasone dipropionate HFA 320 mcg/day as measured by beclomethasone-17-monopropionate (Cmax: 262.7 vs 1343.7 pg/mL; GMR: 0.195; 90% CI for the GMR: 0.158, 0.241).
Following repeated once-daily administration of QNASL Nasal Aerosol, there was no accumulation or increase in plasma exposure to beclomethasone-17-monopropionate or beclomethasone dipropionate, most likely due to the short plasma half-life relative to the dosing frequency.
Distribution
The in vitro protein binding for beclomethasone-17-monopropionate was reported to be 94% to 96% over the concentration range of 1000 to 5000 pg/mL. The volume of distribution at steady state for beclomethasone dipropionate is moderate (20 L) but more extensive for beclomethasone-17-monopropionate (424 L).
Metabolism
Beclomethasone dipropionate undergoes extensive first-pass metabolism, forming three metabolites via CYP3A4, beclomethasone-17-monopropionate, beclomethasone-21-monopropionate, and beclomethasone. Beclomethasone-17-monopropionate is the major and most active metabolite.
Elimination
The major route of elimination of inhaled beclomethasone dipropionate appears to be via metabolism. More than 90% of inhaled beclomethasone dipropionate is found as beclomethasone-17-monopropionate in the systemic circulation. The mean elimination half-life of beclomethasone-17-monopropionate is 2.8 hours. The terminal elimination half-lives of beclomethasone dipropionate and beclomethasone-17-monopropionate following intranasal dosing with QNASL Nasal Aerosol (320 mcg) were approximately 0.3 hours and 4.5 hours, respectively. Irrespective of the route of administration (injection, oral, or inhalation), beclomethasone dipropionate and its metabolites are mainly excreted in the feces. Less than 10% of the drug and its metabolites are excreted in the urine. It is likely that intranasal beclomethasone dipropionate follows a similar elimination pathway.
Special Populations
Formal pharmacokinetic studies using QNASL Nasal Aerosol were not conducted in any special populations.
13 NONCLINICAL TOXICOLOGY
13.1 Carcinogenesis, Mutagenesis, Impairment of Fertility
The carcinogenicity of beclomethasone dipropionate was evaluated in rats which were exposed for a total of 95 weeks: 13 weeks at inhalation doses up to 0.4 mg/kg/day and the remaining 82 weeks at combined oral and inhalation doses up to 2.4 mg/kg/day. There was no evidence of treatment-related increases in the incidence of tumors in this study at the highest dose, which is approximately 75 and 130 times the MRHD in adults and children, respectively, on a mg/m2 basis.
Beclomethasone dipropionate did not induce gene mutation in bacterial cells or mammalian Chinese hamster ovary (CHO) cells in vitro. No significant clastogenic effect was seen in cultured CHO cells in vitro or in the mouse micronucleus test in vivo.
In rats, beclomethasone dipropionate caused decreased conception rates at an oral dose of 16 mg/kg/day (approximately 500 times the MRHD in adults on a mg/m2 basis). Impairment of fertility, as evidenced by inhibition of the estrous cycle in dogs was observed following treatment by the oral route at a dose of 0.5 mg/kg/day (approximately 50 times the MRHD in adults on a mg/m2 basis). No inhibition of the estrous cycle in dogs was seen following 12 months of exposure to beclomethasone dipropionate by the inhalation route at an estimated daily dose of 0.33 mg/kg (approximately 35 times the MRHD in adults on a mg/m2 basis).
14 CLINICAL STUDIES
14.1 Seasonal and Perennial Allergic Rhinitis
Adult and Adolescent Patients Aged 12 Years and Older: The efficacy and safety of QNASL Nasal Aerosol have been evaluated in 3 randomized, double-blind, parallel-group, multicenter, placebo-controlled clinical trials of 2 to 6 weeks duration in adult and adolescent patients 12 years and older with symptoms of seasonal or perennial allergic rhinitis. The 3 clinical trials included one 2-week dose-ranging trial in patients with seasonal allergic rhinitis, one 2-week efficacy trial in patients with seasonal allergic rhinitis, and one 6-week efficacy trial in patients with perennial allergic rhinitis. The trials included a total of 1049 patients (366 males and 683 females). About 81% of patients were Caucasian and 17% African American, the mean age was approximately 38 years. Of these patients 521 received QNASL Nasal Aerosol 320 mcg once daily administered as 2 actuations in each nostril.
Assessment of efficacy was based on the total nasal symptom score (TNSS). TNSS is calculated as the sum of the patients' scoring of the 4 individual nasal symptoms (rhinorrhea, sneezing, nasal congestion, and nasal itching) on a 0 to 3 categorical severity scale (0 = absent, 1 = mild, 2 = moderate, 3 = severe) as reflective (rTNSS) or instantaneous (iTNSS). rTNSS required the patients to record symptom severity over the previous 12 hours; iTNSS required the patients to record symptom severity over the previous 10 minutes. Morning and evening TNSS scores were averaged over the treatment period and the difference from placebo in the change from baseline rTNSS was the primary efficacy endpoint. The morning iTNSS reflects the TNSS at the end of the 24-hour dosing interval and is an indication of whether the effect was maintained over the 24-hour dosing interval.
Dose-Ranging Trial: The dose-ranging trial was a 2-week trial that evaluated the efficacy of 3 doses of beclomethasone dipropionate nasal aerosol (80, 160, and 320 mcg, once daily) in patients with seasonal allergic rhinitis. In this trial, only treatment with beclomethasone dipropionate nasal aerosol at the dose of 320 mcg/day resulted in statistically significant improvements compared with placebo in the primary efficacy endpoint, rTNSS (Table 3).
| Table 3. Mean Changes from Baseline in Reflective Total Nasal Symptom Score Over 2 Weeks in Adult and Adolescent Patients with Seasonal Allergic Rhinitis (ITT Population) | |||||
|---|---|---|---|---|---|
| Treatment | N | Baseline (SD) | LS Mean (SE) Change from Baseline | Difference From Placebo | |
| LS Mean | 95% CI | ||||
Beclomethasone dipropionate 320 mcg/day | 122 | 9.17 (1.66) | -2.22 (0.18) | -0.63 | -1.13, 0.13 |
Beclomethasone dipropionate 160 mcg/day | 123 | 9.24 (1.57) | -1.87 (0.18) | -0.29 | -0.78, 0.21 |
Beclomethasone dipropionate 80 mcg/day | 118 | 9.33 (1.72) | -1.88 (0.18) | -0.29 | -0.80, 0.21 |
| Placebo | 123 | 8.98 (1.47) | -1.59 (0.18) | ||
The 320 mcg dose also demonstrated a statistically significant decrease in morning iTNSS than placebo, indicating that the effect was maintained over the 24-hour dosing interval.
Seasonal and Perennial Allergic Rhinitis Trials: In 2 randomized, double-blind, parallel-group, multicenter, placebo-controlled efficacy trials, once-daily treatment with QNASL Nasal Aerosol for 2 weeks in patients with seasonal allergic rhinitis and for 6 weeks in patients with perennial allergic rhinitis resulted in statistically significant greater decreases from baseline in the rTNSS and morning iTNSS than placebo (Table 4).
| Table 4. Mean Changes From Baseline in Reflective and Instantaneous Total Nasal Symptom Scores in Adult and Adolescent Patients with Seasonal or Perennial Allergic Rhinitis (ITT Population) | |||||
|---|---|---|---|---|---|
| Treatment | N | Baseline (SD) | LS Mean (SE) Change from Baseline | Difference From Placebo | |
| LS Mean | 95% CI | ||||
| Seasonal Allergic Rhinitis | |||||
| Reflective Total Nasal Symptom Scores (rTNSS) | |||||
Beclomethasone dipropionate 320 mcg/day | 167 | 9.6 (1.51) | -2.0 (0.16) | -0.91 | -1.3, -0.5 |
| Placebo | 171 | 9.5 (1.54) | -1.0 (0.15) | ||
| Instantaneous Total Nasal Symptom Scores (iTNSS) | |||||
Beclomethasone dipropionate 320 mcg/day | 167 | 9.0 (1.74) | -1.7 (0.15) | -0.92 | -1.3, -0.5 |
| Placebo | 171 | 8.7 (1.81) | -0.8 (0.15) | ||
| Perennial Allergic Rhinitis | |||||
| Reflective Total Nasal Symptom Scores (rTNSS) | |||||
Beclomethasone dipropionate 320 mcg/day | 232 | 8.9 (1.70) | -2.5 (0.14) | -0.84 | -1.2, -0.5 |
| Placebo | 234 | 9.0 (1.73) | -1.6 (0.14) | ||
| Instantaneous Total Nasal Symptom Scores (iTNSS) | |||||
Beclomethasone dipropionate 320 mcg/day | 232 | 8.1 (1.98) | -2.1 (0.13) | -0.78 | -1.1, -0.4 |
| Placebo | 234 | 8.3 (1.96) | -1.4 (0.13) | ||
Pediatric Patients 4 to 11 Years of Age: The efficacy and safety of QNASL Nasal Aerosol have been evaluated in 2 randomized, double-blind, parallel-group, multicenter, placebo-controlled clinical trials of 2 to 12 weeks duration in pediatric patients 4 to 11 years of age with symptoms of seasonal or perennial allergic rhinitis. The 2 clinical trials included one 2-week dose-ranging trial in patients with seasonal allergic rhinitis (6 - 11 years of age), and one 12-week efficacy trial in patients with perennial allergic rhinitis (4 - 11 years of age). The trials included a total of 1255 patients (680 males and 575 females). About 73% of patients were Caucasian and 20% African American, the mean age was approximately 8 years for one study and 9 years for the second study. Of these patients 596 received QNASL Nasal Aerosol 80 mcg once daily administered as 1 actuation of QNASL 40 mcg Nasal Aerosol in each nostril.
Assessment of efficacy was based on the total nasal symptom score (TNSS) as described in adult and adolescents efficacy studies.
Dose-Ranging Seasonal Allergic Rhinitis Trial: The dose-ranging trial was a 2-week trial that evaluated the efficacy of 2 doses of beclomethasone dipropionate nasal aerosol (80 and 160 mcg, once daily) in patients with seasonal allergic rhinitis. In this trial, treatment with beclomethasone dipropionate nasal aerosol at the dose of 80 mcg/day resulted in statistically significant improvements compared with placebo in the primary efficacy endpoint, rTNSS (Table 5).
| Table 5. Mean Changes from Baseline in Reflective and Instantaneous Total Nasal Symptom Scores Over 2 Weeks in Pediatric Patients with Seasonal Allergic Rhinitis (ITT Population) | |||||
| Treatment | N | Baseline (SD) | LS Mean (SE) Change from Baseline | Difference From Placebo | |
| LS Mean | 95% CI | ||||
| Reflective Total Nasal Symptom Scores (rTNSS) | |||||
| Beclomethasone dipropionate 80 mcg/day | 239 | 8.9 (1.62) | -1.9 (0.14) | -0.71 | -1.1, -0.3 |
| Beclomethasone dipropionate 160 mcg/day | 241 | 9.0 (1.71) | -2.0 (0.14) | -0.76 | -1.1, -0.4 |
| Placebo | 234 | 9.0 (1.70) | -1.2 (0.14) | - | - - |
| Instantaneous Total Nasal Symptom Scores (iTNSS) | |||||
| Beclomethasone dipropionate 80 mcg/day | 238 | 8.1 (1.99) | -1.6 (0.13) | -0.63 | -1.0, -0.3 |
| Beclomethasone dipropionate 160 mcg/day | 241 | 8.1 (2.13) | -1.7 (0.13) | -0.73 | -1.1, -0.4 |
| Placebo | 234 | 8.2 (2.10) | -1.0 (0.13) | - | - |
The 80 mcg daily dose also demonstrated a statistically significant decrease in morning iTNSS than placebo, indicating that the effect was maintained over the 24-hour dosing interval. Based on the results from the dose ranging trial, 80 mcg once daily was chosen as the dose for pediatric patients 4-11 years of age.
Perennial Allergic Rhinitis Trial: In a randomized, double-blind, parallel-group, multicenter, placebo-controlled efficacy trial, treatment with QNASL Nasal Aerosol 80 mcg once daily in patients with perennial allergic rhinitis resulted in statistically significant greater decreases from baseline in the rTNSS (the primary endpoint) and iTNSS than placebo over the first six weeks of treatment (Table 6).
| Table 6. Mean Changes from Baseline in Reflective Total Nasal Symptom Score Over 6 Weeks in Pediatric Patients 6 to 11 Years of Age with Perennial Allergic Rhinitis (FAS) | |||||
| Treatment | N | Baseline (SD) | LS Mean (SE) Change from Baseline | Difference From Placebo | |
| LS Mean | 95% CI | ||||
| Reflective Total Nasal Symptom Scores (rTNSS) | |||||
| Beclomethasone dipropionate 80 mcg/day | 296 | 8.6 (1.56) | -2.26 (0.12) | -0.66 | -1.08, -0.24 |
| Placebo | 153 | 8.6 (1.60) | -1.60 (0.17) | - | - |
| Instantaneous Total Nasal Symptom Scores (iTNSS) | |||||
| Beclomethasone dipropionate 80 mcg/day | 296 | 7.9 (2.05) | -1.98 (0.12) | -0.58 | -0.99, -0.18 |
| Placebo | 153 | 7.8 (2.12) | -1.39 (0.17) | - | - |
FAS=full analysis set
For pediatric patients 4-11 years of age, improvements in average patient-reported rTNSS and iTNSS were also significantly greater in QNASL Nasal Aerosol 80 mcg per day treated patients compared with placebo.
16 HOW SUPPLIED/STORAGE AND HANDLING
QNASL Nasal Aerosol is supplied in 2 strengths and supplied as a pressurized aluminum canister inserted into a blue and white plastic nasal actuator with a built-in dose counter and white dust cap, as follows:
QNASL 80 mcg Nasal Aerosol contains 10.6 g of drug and excipients and provides 120 actuations (NDC 59310-410-12). Each actuation delivers 80 mcg of beclomethasone dipropionate from the nasal actuator and 100 mcg from the valve.
QNASL 40 mcg Nasal Aerosol contains 6.8 g of drug and excipients and provides 60 actuations (NDC 59310-406-06). Each actuation delivers 40 mcg of beclomethasone dipropionate from the nasal actuator and 50 mcg from the valve.
Each canister of QNASL Nasal Aerosol has a dose counter, which initially reads 60 sprays or 120 sprays for the respective products, and counts down each time a spray is released. The correct amount of medication in each intranasal dose cannot be ensured after the counter reads 0; therefore, the device should be discarded when the counter reads 0.
Do not remove the QNASL Nasal Aerosol canister from the actuator. The QNASL Nasal Aerosol canister should only be used with the QNASL Nasal Aerosol actuator and the actuator should not be used with any other drug product.
CONTENTS UNDER PRESSURE
Do not puncture. Do not store near heat or open flame. Do not expose to temperatures higher than 49°C (120°F) as this may cause bursting of the canister. Never throw the device into a fire or an incinerator.
Store at temperature between 20° and 25°C (68° and 77°F); excursions are permitted between 15° and 30°C (59° and 86°F).
Keep out of reach of children.
17 PATIENT COUNSELING INFORMATION
See FDA-Approved Patient Labeling accompanying the product.
17.1 Local Nasal Effects
Inform patients that treatment with QNASL Nasal Aerosol may lead to adverse reactions, including epistaxis, nasal ulceration, and nasal discomfort. Candida infection may also occur with treatment with QNASL Nasal Aerosol. In addition, nasal beclomethasone dipropionate products are known to be associated with nasal septal perforation and impaired wound healing. Patients who have experienced recent nasal ulcers, nasal surgery, or nasal trauma should not use QNASL Nasal Aerosol until healing has occurred [see Warnings and Precautions (5.1)].
17.2 Eye Disorders
Inform patients that blurred vision, glaucoma and cataracts are associated with nasal and inhaled corticosteroid use. Patients should inform their healthcare providers if a change in vision is noted while using QNASL Nasal Aerosol [see Warnings and Precautions (5.2)].
17.3 Hypersensitivity Reactions Including Anaphylaxis
Hypersensitivity reactions including anaphylaxis, angioedema, urticaria, and rash have been reported following administration of beclomethasone dipropionate nasally administered and inhalationally administered products. Angioedema, urticaria, and rash have been reported following administration of QNASL Nasal Aerosol. If any such reactions occur, patients should discontinue use of QNASL Nasal Aerosol [see Warnings and Precautions (5.3)].
17.4 Immunosuppression
Patients who are on immunosuppressant doses of corticosteroids should be warned to avoid exposure to chickenpox or measles and, if exposed, to consult their physician without delay. Patients should be informed of potential worsening of existing tuberculosis; fungal, bacterial, viral, or parasitic infections; or ocular herpes simplex [see Warnings and Precautions (5.4)].
17.5 Use Daily for Best Effect
Patients should use QNASL Nasal Aerosol on a regular, once-daily basis since its effectiveness depends on its regular use. QNASL Nasal Aerosol may not have an immediate effect on rhinitis symptoms. The patient should not increase the prescribed dosage but should contact their physician if symptoms do not improve or if the condition worsens.
17.6 Keep Spray Out of Eyes or Mouth
Patients should be informed to avoid spraying QNASL Nasal Aerosol in their eyes or mouth.
Distributed by:
Teva Pharmaceuticals USA, Inc.
Parsippany, NJ 07054
©2020, Teva Respiratory, LLC. All rights reserved.
United States Patent No. 7,780,038

QNSPI-002