


Prescribing information (package insert) - Pulmozyme
1 INDICATIONS AND USAGE
PULMOZYME® is indicated, in conjunction with standard therapies, for the management of pediatric and adult patients with cystic fibrosis (CF) to improve pulmonary function.
In CF patients with an FVC ≥ 40% of predicted, daily administration of PULMOZYME has also been shown to reduce the risk of respiratory tract infections requiring parenteral antibiotics.
2 DOSAGE AND ADMINISTRATION
2.1 Recommended Dosage
The recommended dosage, in most cystic fibrosis patients, is 2.5 mg (one single-dose ampule) inhaled once daily using a recommended jet nebulizer connected to an air compressor system or via a vibrating mesh nebulizer [see Dosage and Administration (2.2)].
Some patients may benefit from twice daily administration [see Clinical Studies (14)].
2.2 Administration Instructions
Nebulizer Information
- Administer PULMOZYME via a jet nebulizer connected to an air compressor with an adequate air flow and equipped with a mouthpiece or suitable face mask, or via a vibrating mesh nebulizer. Refer to Table 1 for the recommended Jet Nebulizers or Vibrating Mesh Nebulizers for use with PULMOZYME. No data are currently available to support the administration of PULMOZYME with other nebulizer systems.
- The eRapid Nebulizer System should only be used by adults and pediatric patients who can use a mouthpiece, and not by younger patients who need a mask to inhale PULMOZYME.
- Use the selected nebulizer in accordance with the manufacturer's instruction manual.
- Refer to the manufacturer's instruction manual on the use, maintenance, and replacement of the equipment, including cleaning and disinfection procedures for the selected nebulizer.
- For additional information, refer to the selected nebulizer manufacturer's instruction manual.
Table 1. Recommended Jet Nebulizers or Vibrating Mesh Nebulizers for Use with PULMOZYME
| Jet Nebulizer Follow the selected nebulizer manufacturer's instruction manual. | Compressor |
|---|---|
| Hudson T Up-draft II® | Pulmo-Aide® or legally marketed compressor of identical pressure and flow rate (maximum 30 psi, 12 LPM). |
| Marquest Acorn II® | |
| PARI LC® Plus | PARI PRONEB® or legally marketed compressor of identical pressure and flow rate (maximum 24 psi, 9 LPM). |
| PARI BABY™ Patients who are unable to inhale or exhale orally throughout the entire nebulization period may use the PARI BABY™ nebulizer. | |
| Durable Sidestream® | MOBILAIRE™, Porta-NEB® or legally marketed compressor of identical pressure and flow rate (maximum 45 psi, 7 LPM). |
| Vibrating Mesh Nebulizers | |
| eRapid® Nebulizer SystemConsisting of the eRapid® Nebulizer Handset with eBase™ Controller. Avoid use in patients who need a mask to inhale PULMOZYME. | |
| Innospire Go | |
| Pulmogine Vibrating Mesh Nebulizer | |
| AireHealth Nebulizer™ | |
| Intelligent Mesh Nebulizer | |
PULMOZYME Information
- Each PULMOZYME ampule should be squeezed prior to use in order to check for leaks. Discard ampules if the solution is cloudy or discolored. Once opened, the entire contents of the ampule must be used or discarded.
- Do not dilute or mix PULMOZYME with other drugs in the nebulizer. Mixing of PULMOZYME with other drugs could lead to adverse physicochemical and/or functional changes in PULMOZYME or the admixed compound.
3 DOSAGE FORMS AND STRENGTHS
Inhalation solution: 2.5 mg/2.5 mL (1 mg/mL) clear, colorless solution in single-dose ampules.
4 CONTRAINDICATIONS
PULMOZYME is contraindicated in patients with known hypersensitivity to dornase alfa, Chinese Hamster Ovary cell products, or any component of the product.
5 WARNINGS AND PRECAUTIONS
None.
6 ADVERSE REACTIONS
6.1 Clinical Trials Experience
Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice.
The data described below reflect exposure to PULMOZYME in 902 patients, with exposures ranging from 2 weeks of daily administration up to once or twice daily administration for six months. PULMOZYME was studied in both placebo-controlled (n=804) and uncontrolled trials (n=98). The population of patients in placebo-controlled trials was with FVC ≥ 40% of predicted (n=643) or with more advanced pulmonary disease, FVC < 40% of predicted (n=161). The population in the uncontrolled trial included 98 pediatric patients with CF ranging from 3 months to 10 years of age. More than half of the patients received PULMOZYME 2.5 mg by inhalation once a day (n=581), while the rest of patients (n=321) received PULMOZYME 2.5 mg by inhalation twice a day.
Placebo-Controlled Trials
Trial 1: Trial 1 was a randomized, placebo-controlled clinical trial in patients with FVC ≥ 40% of predicted. In this trial, over 600 patients received PULMOZYME once or twice daily for six months. The most common adverse reaction (risk difference ≥5%) was voice alteration. The proportion of most adverse events was similar for patients on PULMOZYME and on placebo, probably reflecting the sequelae of the underlying lung disease. In most cases reactions that were increased were mild, transient in nature, and did not require alterations in dosing. Few patients experienced adverse reactions resulting in permanent discontinuation from PULMOZYME, and the proportion of discontinuations were similar for placebo (2%) and PULMOZYME (3%). Adverse reactions occurring in a higher proportion (greater than 3%) of PULMOZYME treated patients than in placebo-treated patients are listed in Table 2.
Trial 2: Trial 2 was a randomized, placebo-controlled trial in patients with more advanced pulmonary disease (FVC < 40% of predicted) who were treated for 12 weeks. In this trial, the safety profile of PULMOZYME was similar to that reported in patients with less advanced pulmonary disease (FVC ≥ 40% of predicted). Adverse reactions that were reported in this trial with a higher proportion (greater than 3%) in the PULMOZYME treated patients are listed in Table 2.
Table 2. Adverse Reactions Increased 3% or More in PULMOZYME Treated Patients Over Placebo in CF Clinical Trials
Adverse Reactions (of any severity or seriousness) | Trial 1 CF Patients with FVC ≥ 40% of predicted treated for 24 weeks | Trial 2 CF Patients with FVC <40% of predicted treated for 12 weeks | |||
|---|---|---|---|---|---|
Placebo n=325 | Pulmozyme QD n=322 | Pulmozyme BID n=321 | Placebo n=159 | Pulmozyme QD n=161 | |
| Voice alteration | 7% | 12% | 16% | 6% | 18% |
| Pharyngitis | 33% | 36% | 40% | 28% | 32% |
| Rash | 7% | 10% | 12% | 1% | 3% |
| Laryngitis | 1% | 3% | 4% | 1% | 3% |
| Chest Pain | 16% | 18% | 21% | 23% | 25% |
| Conjunctivitis | 2% | 4% | 5% | 0% | 1% |
| Rhinitis | Differences were less than 3% | 24% | 30% | ||
| FVC decrease of ≥ 10% of predictedSingle measurement only, does not reflect overall FVC changes. | 17% | 22% | |||
| Fever | 28% | 32% | |||
| Dyspepsia | 0% | 3% | |||
| Dyspnea (when reported as serious) | Differences were less than 3% | 12%Total reports of dyspnea (regardless of severity or seriousness) had a difference of less than 3% in Trial 2. | 17% | ||
Mortality rates observed in controlled trials were similar for the placebo and PULMOZYME treated patients. Causes of death were consistent with progression of cystic fibrosis and included apnea, cardiac arrest, cardiopulmonary arrest, cor pulmonale, heart failure, massive hemoptysis, pneumonia, pneumothorax, and respiratory failure.
Uncontrolled Trial
Trial 3: The safety of PULMOZYME, 2.5 mg by inhalation, was studied with 2 weeks of daily administration in 98 pediatric patients with cystic fibrosis 3 months to 10 years of age (65 aged 3 months to < 5 years, 33 aged 5 to ≤ 10 years). The PARI BABY™ reusable nebulizer (which uses a facemask instead of a mouthpiece) was utilized in patients unable to demonstrate the ability to inhale or exhale orally throughout the entire treatment period (54/65, 83% of the younger and 2/33, 6% of the older patients). Overall, the nature of adverse reactions was similar to that seen in the placebo-controlled trials. The number of patients reporting cough was higher in the younger age group as compared to the older age group (29/65, 45% compared to 10/33, 30%) as was the number reporting moderate to severe cough (24/65, 37% as compared to 6/33, 18%). The number of patients reporting rhinitis was higher in the younger age group as compared to the older age group (23/65, 35% compared to 9/33, 27%) as was the number reporting rash (4/65, 6% as compared to 0/33).
Allergic Reactions
There have been no reports of anaphylaxis attributed to the administration of PULMOZYME. Urticaria, mild to moderate, and mild skin rash have been observed and have been transient. Within all of the studies, a small percentage (average of 2-4%) of patients treated with PULMOZYME developed serum antibodies to PULMOZYME. None of these patients developed anaphylaxis, and the clinical significance of serum antibodies to PULMOZYME is unknown.
7 DRUG INTERACTIONS
Available data indicate there are no clinically important drug-drug interactions with PULMOZYME.
8 USE IN SPECIFIC POPULATIONS
8.1 Pregnancy
Risk Summary
There are no adequate and well-controlled studies with PULMOZYME in pregnant women. However, animal reproduction studies have been conducted with dornase alfa. In these studies, no evidence of fetal harm was observed in rats and rabbits at doses of dornase alfa up to approximately 600 times the maximum recommended human dose (MRHD).
The background risk of major birth defects and miscarriage for the cystic fibrosis population is unknown. However, the background risk in the U.S. general population of major birth defects is 2-4% and of miscarriage is 15-20% of clinically recognized pregnancies.
Data
Animal Data
Reproductive studies have been performed in rats and rabbits at intravenous doses of dornase alfa up to 10 mg/kg/day (approximately 600 times the MRHD in adults). In a combined embryo-fetal development and pre- and post-natal development study, no evidence of maternal toxicity, embryotoxicity, or teratogenicity was observed when dornase alfa was administered to dams throughout organogenesis (Gestation days 6 to 17). Dornase alfa did not elicit adverse effects on fetal or neonatal growth when administered to dams throughout most of gestation and delivery (Gestation days 6 to 25) and nursing (Post-partum days 6 to 21).
A pharmacokinetic study in Cynomolgus monkeys found no detectable levels of dornase alfa in fetal blood or amniotic fluid on gestation day 150 (end of gestation) from mothers that were administered an intravenous bolus dose (0.1 mg/kg) followed by an intravenous infusion dose (0.080 mg/kg) over a 6-hour period during pregnancy.
8.2 Lactation
Risk Summary
It is not known whether PULMOZYME is present in human milk. In a pharmacokinetic study in Cynomolgus monkeys, levels of dornase alfa detected in milk were less than 0.1% of the maternal serum concentration at 24 hours after dosing [intravenous bolus dose (0.1 mg/kg) of dornase alfa followed by an intravenous infusion (0.080 mg/kg/hr) over a 6-hour period] on post-partum day 14. The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for PULMOZYME and any potential adverse effects on the breastfed child from PULMOZYME or from the underlying maternal condition.
8.4 Pediatric Use
The safety and effectiveness of PULMOZYME in conjunction with standard therapies for cystic fibrosis have been established in pediatric patients. Use of PULMOZYME in pediatric patients is supported by evidence in the following age groups:
- Patients 5 to 17 years of age: Use of PULMOZYME in patients 5 to 17 years of age is supported by evidence from a randomized, placebo-controlled trial of 303 of clinically stable cystic fibrosis patients 5 to 17 years of age who received PULMOZYME [see Clinical Studies (14)].
- Patients less than 5 years: Use of PULMOZYME in patients less than 5 years of age is supported by extrapolation of efficacy data in patients 5 years of age and older with additional safety data in 65 pediatric patients aged 3 months to less than 5 years who received PULMOZYME 2.5 mg daily by inhalation for 2 weeks [see Adverse Reactions (6.1) and Clinical Studies (14)].
8.5 Geriatric Use
Cystic fibrosis is primarily a disease of children and young adults. Clinical studies of PULMOZYME did not include sufficient numbers of subjects aged 65 or older to determine whether they respond differently from younger subjects.
11 DESCRIPTION
Dornase alfa is a recombinant human deoxyribonuclease I (rhDNase) an enzyme which selectively cleaves DNA. The protein is produced by genetically engineered Chinese Hamster Ovary (CHO) cells containing DNA encoding for the native human protein, deoxyribonuclease I (DNase). The product is purified by column chromatography and tangential flow filtration. The purified glycoprotein contains 260 amino acids with an approximate molecular weight of 37,000 daltons. The primary amino acid sequence is identical to that of the native human enzyme.
PULMOZYME (dornase alfa) inhalation solution is administered by inhalation of an aerosol mist produced by a compressed air driven nebulizer or a recommended nebulizer system [see Clinical Studies (14) and Dosage and Administration (2.2)]. PULMOZYME is a sterile, clear, colorless, highly purified solution in single-dose ampules. Each ampule delivers 2.5 mL of the solution to the nebulizer bowl. Each mL of aqueous solution contains 1 mg dornase alfa, calcium chloride dihydrate (0.15 mg) and sodium chloride (8.77 mg). The solution contains no preservative. The nominal pH of the solution is 6.3.
12 CLINICAL PHARMACOLOGY
12.1 Mechanism of Action
PULMOZYME is recombinant human deoxyribonuclease I (rhDNase), an enzyme which selectively cleaves DNA. In preclinical in vitro studies, PULMOZYME hydrolyzes the DNA in sputum of CF patients and reduces sputum viscoelasticity. In CF patients, retention of viscous purulent secretions in the airways contributes both to reduced pulmonary function and to exacerbations of infection. Purulent pulmonary secretions contain very high concentrations of extracellular DNA released by degenerating leukocytes that accumulate in response to infection.
12.3 Pharmacokinetics
When 2.5 mg PULMOZYME was administered by inhalation to eighteen CF patients, mean sputum concentrations of 3 µg/mL DNase were measurable within 15 minutes. Mean sputum concentrations declined to an average of 0.6 µg/mL two hours following inhalation. Inhalation of up to 10 mg TID of PULMOZYME by 4 CF patients for six consecutive days, did not result in a significant elevation of serum concentrations of DNase above normal endogenous levels. After administration of up to 2.5 mg of PULMOZYME twice daily for six months to 321 CF patients, no accumulation of serum DNase was noted. Dornase alfa is expected to be metabolized by proteases present in biological fluids. A human intravenous dose study suggested an elimination half-life of 3-4 hours for dornase alfa.
PULMOZYME, 2.5 mg by inhalation, was administered daily to 98 patients aged 3 months to ≤ 10 years, and bronchoalveolar lavage (BAL) fluid was obtained within 90 minutes of the first dose. BAL DNase concentrations were detectable in all patients but showed a broad range, from 0.007 to 1.8 µg/mL. Over an average of 14 days of exposure, serum DNase concentrations (mean ± s.d.) increased by 1.1 ± 1.6 ng/mL for the 3 months to < 5 year age group and by 0.8 ± 1.2 ng/mL for the 5 to ≤ 10 year age group. The relationship between BAL or serum DNase concentration and adverse experiences and clinical outcomes is unknown.
13 NONCLINICAL TOXICOLOGY
13.1 Carcinogenesis, Mutagenesis, Impairment of Fertility
PULMOZYME produced no treatment-related increases in the incidence of tumors in a lifetime study in Sprague Dawley rats that were administered inhaled doses up to 0.246 mg/kg/day (approximately 30 times the MRHD in adults). There was no increase in the development of benign or malignant neoplasms and no occurrence of unusual tumor types in rats after lifetime exposure.
PULMOZYME tested negative in the following genotoxicity assays: the in vitro Ames assay, in vitro mouse lymphoma assay, and in vivo mouse bone marrow micronucleus assay. No evidence of impairment of fertility was observed in male and female rats that received intravenous doses up to 10 mg/kg/day (approximately 600 times the MRHD in adults).
14 CLINICAL STUDIES
Trial in CF Patients with FVC ≥40% of Predicted
PULMOZYME has been evaluated in a randomized, placebo-controlled trial of clinically stable cystic fibrosis patients, 5 years of age and older, with baseline forced vital capacity (FVC) greater than or equal to 40% of predicted and receiving standard therapies for cystic fibrosis. Patients were treated with placebo (325 patients), 2.5 mg of PULMOZYME once a day (322 patients), or 2.5 mg of PULMOZYME twice a day (321 patients) for six months administered via a Hudson T Up-draft II® nebulizer with a Pulmo-Aide® compressor.
Both doses of PULMOZYME resulted in significant reductions in the number of patients experiencing respiratory tract infections requiring use of parenteral antibiotics compared with the placebo group. Administration of PULMOZYME reduced the relative risk of developing a respiratory tract infection by 27% and 29% for the 2.5 mg daily dose and the 2.5 mg twice daily dose, respectively (see Table 3). The data suggest that the effects of PULMOZYME on respiratory tract infections in older patients ( > 21 years) may be smaller than in younger patients, and that twice daily dosing may be required in the older patients. Patients with baseline FVC > 85% may also benefit from twice a day dosing (see Table 3). The reduced risk of respiratory infection observed in PULMOZYME treated patients did not directly correlate with improvement in FEV1 during the initial two weeks of therapy.
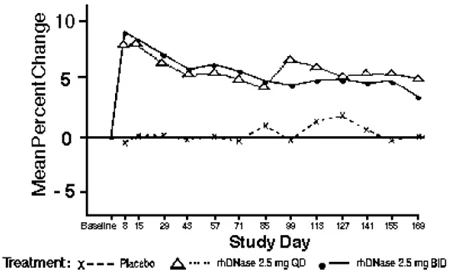
Within 8 days of the start of treatment with PULMOZYME, mean FEV1 increased 7.9% in those treated once a day and 9.0% in those treated twice a day compared to the baseline values. The overall mean FEV1 during long-term therapy increased 5.8% from baseline at the 2.5 mg daily dose level and 5.6% from baseline at the 2.5 mg twice daily dose level. Placebo recipients did not show significant mean changes in pulmonary function testing (see Figure 1).
For patients 5 years of age or older, with baseline FVC greater than or equal to 40%, administration of PULMOZYME decreased the incidence of occurrence of first respiratory tract infection requiring parenteral antibiotics, and improved mean FEV1, regardless of age or baseline FVC.
Table 3. Incidence of First Respiratory Tract Infection Requiring Parenteral Antibiotics in Patients with FVC ≥40% of Predicted
Placebo N=325 | 2.5 mg QD N=322 | 2.5 mg BID N=321 | |
| Percent of Patients Infected | 43% | 34% | 33% |
| Relative Risk (vs placebo) | 0.73 | 0.71 | |
| p-value (vs placebo) | 0.015 | 0.007 | |
| Subgroup by Age and Baseline FVC | Placebo % (N) | 2.5 mg QD % (N) | 2.5 mg BID % (N) |
| Age | |||
| 5-20 years | 42% (201) | 25% (199) | 28% (184) |
| 21 years and older | 44% (124) | 48% (123) | 39% (137) |
| Baseline FVC | |||
| 40-85% Predicted | 54% (194) | 41% (201) | 44% (203) |
| > 85% Predicted | 27% (131) | 21% (121) | 14% (118) |
Figure 1. Mean Percent Change from Baseline FEV1 in Patients with FVC ≥40% of Predicted
 |
Trial in CF Patients with FVC <40% of Predicted
PULMOZYME has also been evaluated in a second randomized, placebo-controlled trial in clinically stable patients with baseline FVC < 40% of predicted. Patients were enrolled and treated with placebo (162 patients) or PULMOZYME 2.5 mg QD (158 patients) for twelve weeks. In patients who received PULMOZYME, there was an increase in mean change (as percent of baseline) compared to placebo in FEV1 (9.4% vs. 2.1%, p < 0.001) and in FVC (12.4% vs. 7.3%, p < 0.01). PULMOZYME did not significantly reduce the risk of developing a respiratory tract infection requiring parenteral antibiotics (54% of PULMOZYME patients vs. 55% of placebo patients had experienced a respiratory tract infection by 12 weeks, relative risk = .93, p = 0.62).
The effect of PULMOZYME on exercise tolerance has not been established in adult and pediatric patients.
Other Studies
Clinical trials have indicated that PULMOZYME therapy can be continued or initiated during an acute respiratory exacerbation.
Short-term dose ranging studies demonstrated that doses in excess of 2.5 mg BID did not provide further improvement in FEV1. Patients who have received drug on a cyclical regimen (i.e., administration of PULMOZYME 10 mg BID for 14 days, followed by a 14 day wash out period) showed rapid improvement in FEV1 with the initiation of each cycle and a return to baseline with each PULMOZYME withdrawal.
16 HOW SUPPLIED/STORAGE AND HANDLING
PULMOZYME (dornase alfa) inhalation solution is a sterile, clear, colorless solution supplied in:
- 30 unit cartons containing 5 foil pouches of 6 single-dose ampules. Each 2.5 mL ampule contains 2.5 mg of dornase alfa (1 mg/mL): NDC 50242-100-40.
Storage and Handling
Store PULMOZYME ampules at a refrigerated temperature between 2°C to 8°C (36°F to 46°F) in their protective foil to protect from light and heat. Once the protective foil pouch is opened, the unused ampules must be kept refrigerated in the protective foil pouch to protect from light and heat. Do not use beyond the expiration date stamped on the ampule. During transport, keep the ampules refrigerated in their protective foil pouch to protect from light and heat. Do not use if the ampules are exposed to room temperature (22°C to 28°C [72°F to 82°F]) for more than a total of 60 hours. Avoid excessive heat and light.
17 PATIENT COUNSELING INFORMATION
Advise patients to read the FDA-approved patient labeling (Instructions for Use).
Preparation
Advise patients to squeeze each ampule prior to use in order to check for leaks. The solution should be discarded if it is cloudy or discolored. Once opened, the entire contents of the ampule must be used or discarded [see Dosage and Administration (2.2)].
Drug Incompatibilities
Instruct patients not to dilute or mix PULMOZYME with other drugs in the nebulizer. Mixing of PULMOZYME with other drugs could lead to adverse physicochemical and/or functional changes in PULMOZYME or the admixed compound [see Dosage and Administration (2.2)].
Storage
Instruct patients on the proper techniques to store and handle PULMOZYME [see How Supplied/Storage and Handling (16)].
Manufacturer's Instruction Manual
Instruct patients to read and follow the manufacturer's instruction manual for the proper use and maintenance of the jet nebulizer/compressor system, or the vibrating mesh nebulizer used in PULMOZYME delivery.
Pulmozyme® (dornase alfa)
Inhalation Solution
Manufactured by:
Genentech, Inc.
A Member of the Roche Group
1 DNA Way
South San Francisco, CA 94080-4990
US License No. 1048
©2024 Genentech, Inc. All rights reserved
©2024 Genentech, Inc.
Pulmozyme® is a registered trademark of Genentech, Inc.