


Prescribing information (package insert) - Omtryg
1 INDICATIONS AND USAGE
OMTRYG™ (omega-3-acid ethyl esters) capsules, USP, is indicated as an adjunct to diet to reduce triglyceride (TG) levels in adult patients with severe (≥500 mg/dL) hypertriglyceridemia.
Usage Considerations: Patients should be placed on an appropriate lipid-lowering diet before receiving OMTRYG and should continue this diet during treatment with OMTRYG.
Laboratory studies should be done to ascertain that the lipid levels are consistently abnormal before instituting OMTRYG therapy. Every attempt should be made to control serum lipids with appropriate diet, exercise, weight loss in obese patients, and control of any medical problems, such as diabetes mellitus and hypothyroidism, that are contributing to the lipid abnormalities. Medications known to exacerbate hypertriglyceridemia (such as beta blockers, thiazides, estrogens) should be discontinued or changed if possible prior to consideration of triglyceride-lowering drug therapy.
Limitations of Use:
The effect of OMTRYG on the risk for pancreatitis has not been determined.
The effect of OMTRYG on cardiovascular mortality and morbidity has not been determined.
2 DOSAGE AND ADMINISTRATION
- Assess triglyceride levels carefully before initiating therapy. Identify other causes (e.g., diabetes mellitus, hypothyroidism, or medications) of high triglyceride levels and manage as appropriate. [see Indications and Usage (1)].
- Patients should be placed on an appropriate lipid-lowering diet before receiving OMTRYG and should continue this diet during treatment with OMTRYG.
The daily dose of OMTRYG is 4 capsules per day taken as a single dose (4 capsules) or as 2 capsules given twice daily. OMTRYG should be taken with meals. [see Clinical Pharmacology (12.3)]
Patients should be advised to swallow OMTRYG capsules whole. Do not break open, crush, dissolve or chew OMTRYG.
3 DOSAGE FORMS AND STRENGTHS
OMTRYG (omega-3-acid ethyl esters) capsules, USP, are supplied as 1.2-gram, transparent, soft-gelatin capsules filled with light-yellow oil and bearing the designation TP0001.
4 CONTRAINDICATIONS
OMTRYG is contraindicated in patients with known hypersensitivity (e.g., anaphylactic reaction) to omega-3-acid ethyl esters or any component of OMTRYG.
5 WARNINGS AND PRECAUTIONS
5.1 Monitoring: Laboratory Tests
In patients with hepatic impairment, alanine aminotransferase (ALT) and aspartate aminotransferase (AST) levels should be monitored periodically during therapy with OMTRYG. In some patients, increases in ALT levels without a concurrent increase in AST levels were observed.
In some patients, OMTRYG increases LDL-cholesterol levels. LDL-cholesterol levels should be monitored periodically during therapy with OMTRYG.
5.2 Fish Allergy
OMTRYG contains ethyl esters of omega-3 fatty acids (EPA and DHA) obtained from the oil of several fish sources. It is not known whether patients with allergies to fish and/or shellfish are at increased risk of an allergic reaction to OMTRYG. OMTRYG should be used with caution in patients with known hypersensitivity to fish and/or shellfish.
5.3 Recurrent Atrial Fibrillation (AF) or Flutter
In a double-blind, placebo-controlled trial of 663 patients with symptomatic paroxysmal AF (n=542) or persistent AF (n=121), recurrent AF or flutter was observed in patients randomized to omega-3-acid ethyl esters who received 8 capsules/day for 7 days and 4 capsules/day thereafter for 23 weeks at a higher rate relative to placebo. Patients in this trial had median baseline triglycerides of 127 mg/dL, had no substantial structural heart disease, were taking no anti-arrhythmic therapy (rate control permitted), and were in normal sinus rhythm at baseline.
At 24 weeks, in the paroxysmal AF stratum, there were 129 (47%) first recurrent symptomatic AF or flutter events on placebo and 141 (53%) on omega-3-acid ethyl esters [primary endpoint, HR 1.19; 95% CI 0.93, 1.35]. In the persistent AF stratum, there were 19 (35%) events on placebo and 34 (52%) events on omega-3-acid ethyl esters [HR 1.63; 95% CI 0.91, 2.18]. For both strata combined, the HR was 1.25; 95% CI 1.00, 1.40. Although the clinical significance of these results is uncertain, there is a possible association between omega-3-acid ethyl esters and more frequent recurrences of symptomatic atrial fibrillation or flutter in patients with paroxysmal or persistent atrial fibrillation, particularly within the first 2 to 3 months of initiating therapy.
OMTRYG is not indicated for the treatment of AF or flutter.
6 ADVERSE REACTIONS
6.1 Clinical Trials Experience
Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice.
Adverse reactions reported in at least 3% and at a greater rate than placebo for patients treated with omega-3-acid ethyl esters based on pooled data across 23 clinical studies are listed in Table 1.
Table 1. Adverse Reactions Occurring at Incidence ≥3% and Greater than Placebo in Clinical Studies of Omega-3-Acid Ethyl Esters
* Studies included subjects with HTG and severe HTG. † OMTRYG and omega-3-acid ethyl esters each contain, among other components, at least 900 mg per capsule of ethyl esters from omega-3 fatty acids sourced from fish oils. | ||||
| Body System | Omega-3-Acid Ethyl Esters† (N = 655) | Placebo (N = 370) | ||
| Adverse Reaction* | n | % | n | % |
| Eructation | 29 | 4 | 5 | 1 |
| Dyspepsia | 22 | 3 | 6 | 2 |
| Taste perversion | 27 | 4 | 1 | <1 |
Additional adverse reactions from clinical studies are listed below:
Digestive System: Constipation, gastrointestinal disorder and vomiting.
Metabolic and Nutritional Disorders: Increased ALT and increased AST.
Skin: Pruritus and rash.
6.2 Postmarketing Experience
The following adverse reactions have been identified during post-approval use of omega-3-acid ethyl esters. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
The following events have been reported: anaphylactic reaction, hemorrhagic diathesis.
7 DRUG INTERACTIONS
7.1 Anticoagulants or Other Drugs Affecting Coagulation
Some studies with omega-3-acids demonstrated prolongation of bleeding time. The prolongation of bleeding time reported in these studies has not exceeded normal limits and did not produce clinically significant bleeding episodes. Clinical studies have not been done to thoroughly examine the effect of OMTRYG and concomitant anticoagulants. Patients receiving treatment with OMTRYG and an anticoagulant or other drug affecting coagulation (e.g., anti-platelet agents) should be monitored periodically.
8 USE IN SPECIFIC POPULATIONS
8.1 Pregnancy
Pregnancy Category C: There are no adequate and well-controlled studies in pregnant women. It is unknown whether OMTRYG can cause fetal harm when administered to a pregnant woman or can affect reproductive capacity. OMTRYG should be used during pregnancy only if the potential benefit to the patient justifies the potential risk to the fetus.
Animal Data: Omega-3-acid ethyl esters have been shown to have an embryocidal effect in pregnant rats when given in doses resulting in exposures 7 times the recommended human dose of 4 capsules/day based on a body surface area comparison.
In female rats given oral gavage doses of 100, 600, and 2,000 mg/kg/day beginning 2 weeks prior to mating and continuing through gestation and lactation, no adverse effects were observed in the high dose group (5 times human systemic exposure following an oral dose of 4 capsules/day based on body surface area comparison).
In pregnant rats given oral gavage doses of 1,000, 3,000, and 6,000 mg/kg/day from gestation day 6 through 15, no adverse effects were observed (14 times human systemic exposure following an oral dose of 4 capsules/day based on a body surface area comparison).
In pregnant rats given oral gavage doses of 100, 600, and 2,000 mg/kg/day from gestation day 14 through lactation day 21, no adverse effects were seen at 2,000 mg/kg/day (5 times the human systemic exposure following an oral dose of 4 capsules/day based on a body surface area comparison). However, decreased live births (20% reduction) and decreased survival to postnatal day 4 (40% reduction) were observed in a dose-ranging study using higher doses of 3,000 mg/kg/day (7 times human systemic exposure following an oral dose of 4 capsules/day based on a body surface area comparison).
In pregnant rabbits given oral gavage doses of 375, 750, and 1,500 mg/kg/day from gestation day 7 through 19, no findings were observed in the fetuses in groups given 375 mg/kg/day (2 times human systemic exposure following an oral dose of 4 capsules/day based on a body surface area comparison). However, at higher doses, evidence of maternal toxicity was observed (4 times human systemic exposure following an oral dose of 4 capsules /day based on a body surface area comparison).
8.3 Nursing Mothers
Studies with omega-3-acid ethyl esters have demonstrated excretion in human milk. The effect of this excretion on the infant of a nursing mother is unknown; caution should be exercised when OMTRYG is administered to a nursing mother. An animal study in lactating rats given oral gavage 14 C-ethyl EPA demonstrated that drug levels were 6 to 14 times higher in milk than in plasma.
8.4 Pediatric Use
Safety and effectiveness in pediatric patients have not been established.
8.5 Geriatric Use
A limited number of patients older than 65 years were enrolled in the clinical studies of omega‑3‑acid ethyl esters. Safety and efficacy findings in subjects older than 60 years did not appear to differ from those of subjects younger than 60 years.
9 DRUG ABUSE AND DEPENDENCE
OMTRYG does not have any known drug abuse or withdrawal effects.
11 DESCRIPTION
OMTRYG, a lipid-regulating agent, is supplied as a liquid-filled gel capsule for oral administration. Each OMTRYG capsule contains 1.2 grams of omega-3-acid ethyl esters type A, USP, liquid concentrate consisting of at least 900 mg omega-3-acid ethyl esters sourced from fish oils. These are predominantly a combination of ethyl esters of eicosapentaenoic acid (EPA - approximately 465 mg) and docosahexaenoic acid (DHA - approximately 375 mg).
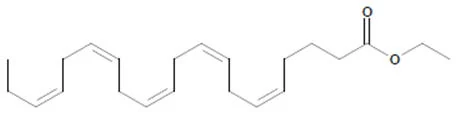
The empirical formula of EPA ethyl ester is C22H34O2, and the molecular weight of EPA ethyl ester is 330.51. The structural formula of EPA ethyl ester is:
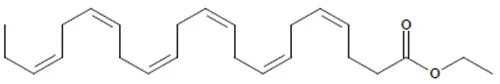
The empirical formula of DHA ethyl ester is C24H36O2, and the molecular weight of DHA ethyl ester is 356.55. The structural formula of DHA ethyl ester is:
OMTRYG capsules also contain the following inactive ingredients: 4.6 mg α-tocopherol (in a carrier of sunflower oil), gelatin, glycerol, and purified water (components of the capsule shell).
12 CLINICAL PHARMACOLOGY
12.1 Mechanism of Action
The mechanism of action of OMTRYG is not completely understood. Potential mechanisms of action include inhibition of acyl-CoA:1,2-diacylglycerol acyltransferase, increased mitochondrial and peroxisomal ß-oxidation in the liver, decreased lipogenesis in the liver, and increased plasma lipoprotein lipase activity. Omega-3-acid ethyl esters may reduce the synthesis of triglycerides in the liver because EPA and DHA are poor substrates for the enzymes responsible for TG synthesis, and EPA and DHA inhibit esterification of other fatty acids.
12.3 Pharmacokinetics
Systemic Bioavailability: When OMTRYG was administered under fasted condition, on average the peak (Cmax) and total (AUC0-72h) exposure were lower by up to 20 to 80-fold, respectively, for total plasma EPA, and lower by up to 2 to 4-fold, respectively, for total plasma DHA, in comparison to those observed under fed condition (high-fat high-calorie meal). Therefore, OMTRYG should be taken with food.
In healthy volunteers and in patients with hypertriglyceridemia, EPA and DHA were absorbed when administered as ethyl esters orally. Omega-3-acids administered as ethyl esters induced significant, dose-dependent increases in serum phospholipid EPA content, though increases in DHA content were less marked and not dose-dependent when administered as ethyl esters.
Specific Populations:
Age: Uptake of EPA and DHA into serum phospholipids in subjects treated with omega-3-acid ethyl esters was independent of age (<49 years versus ≥49 years).
Gender: Females tended to have more uptake of EPA into serum phospholipids than males. The clinical significance of this is unknown.
Pediatric: Pharmacokinetics of OMTRYG have not been studied.
Renal or Hepatic Impairment: OMTRYG has not been studied in patients with renal or hepatic impairment.
Drug-Drug Interactions: Simvastatin: In a 14-day study of 24 healthy adult subjects, daily co-administration of simvastatin 80 mg with 4 capsules of omega-3-acid ethyl esters did not affect the extent (AUC) or rate (Cmax) of exposure to simvastatin or the major active metabolite, beta-hydroxy simvastatin, at steady state.
Atorvastatin: In a 14-day study of 50 healthy adult subjects, daily co‑administration of atorvastatin 80 mg with 4 capsules of omega-3-acid ethyl esters did not affect AUC or Cmax of exposure to atorvastatin, 2‑hydroxyatorvastatin, or 4-hydroxyatorvastatin at steady state.
Rosuvastatin: In a 14-day study of 48 healthy adult subjects, daily co‑administration of rosuvastatin 40 mg with 4 capsules of omega-3-acid ethyl esters did not affect AUC or Cmax of exposure to rosuvastatin at steady state.
In vitro studies using human liver microsomes indicated that clinically significant cytochrome P450 mediated inhibition by EPA/DHA combinations are not expected in humans.
13 NONCLINICAL TOXICOLOGY
13.1 Carcinogenesis, Mutagenesis, Impairment of Fertility
In a rat carcinogenicity study with oral gavage doses of 100, 600, and 2,000 mg/kg/day, males were treated with omega-3-acid ethyl esters for 101 weeks and females for 89 weeks without an increased incidence of tumors (up to 5 times human systemic exposures following an oral dose of 4 capsules/day based on a body surface area comparison). Standard lifetime carcinogenicity bioassays were not conducted in mice.
Omega-3-acid ethyl esters were not mutagenic or clastogenic with or without metabolic activation in the bacterial mutagenesis (Ames) test with Salmonella typhimurium and Escherichia coli or in the chromosomal aberration assay in Chinese hamster V79 lung cells or human lymphocytes. Omega-3-acid ethyl esters were negative in the in vivo mouse micronucleus assay.
In a rat fertility study with oral gavage doses of 100, 600, and 2,000 mg/kg/day, males were treated for 10 weeks prior to mating and females were treated for 2 weeks prior to and throughout mating, gestation, and lactation. No adverse effect on fertility was observed at 2,000 mg/kg/day (5 times human systemic exposure following an oral dose of 4 capsules/day based on a body surface area comparison).
14 CLINICAL STUDIES
14.1 Severe Hypertriglyceridemia
A randomized, double-blind, placebo-controlled study was conducted to evaluate the efficacy of OMTRYG compared with both placebo and an omega-3-acid ethyl esters product in 254 patients with severe hypertriglyceridemia (500-1500 mg/dL). Patients entered a 6-week wash-out/dietary lead-in period and then were randomized to 12-week treatment with either OMTRYG, omega-3-acid ethyl esters, or placebo (vegetable oil), each administered as 4 capsules once daily. Each capsule of both OMTRYG and omega-3-acid ethyl esters contains, among other components, at least 900 mg of ethyl esters from omega-3 fatty acids sourced from fish oils. The primary endpoint was percent change in serum triglycerides (TG) from baseline to Week 12. The secondary endpoints were percent change in non‑HDL‑C, VLDL‑C, LDL‑C, and HDL‑C from baseline to Week 12. Overall, the mean age was 51 years, 72% were men, 92% were Caucasian, the mean BMI was 33 kg/m2, and 21% were taking a statin. The baseline median TG level was 675 mg/dL, mean LDL‑C was 87 mg/dL, and mean HDL‑C was 30 mg/dL.
OMTRYG statistically significantly reduced TG at Week 12 compared with placebo (p-value <0.05). The changes in the major lipid parameters for the groups receiving OMTRYG, omega-3-acid ethyl esters, and placebo are shown in Table 2.
Table 2. Median Baseline and Percent Change From Baseline in Lipid Parameters in Patients with Severe Hypertriglyceridemia (≥500 mg/dL)
OMTRYG N = 104 | Omega-3-Acid Ethyl Esters N=103 | Placebo N = 43 | Median difference from Placebo | |||||
|---|---|---|---|---|---|---|---|---|
| Parameter | BL | % Change | BL | % Change | BL | % Change | OMTRYG vs. Placebo | Omega-3-Acid EE vs. Placebo |
BL = Baseline (mg/dL) median; % Change = Median Percent Change from Baseline; Median difference from placebo = Hodges Lehmann median of all pairwise differences from placebo * p<0.05, ** p<0.01, statistically significant difference between treatment groups based on the pre-specified Hommel method for controlling Type 1 error among the secondary endpoints. | ||||||||
| TG | 702 | -24.7 | 655 | -26.8 | 624 | -17.4 | -12.2* | -14.0* |
| Non-HDL-C | 237 | -9.2 | 210 | -3.6 | 222 | -0.8 | -8.5 | -3.5 |
| TC | 270 | -8.1 | 244 | -1.0 | 250 | -0.8 | -6.9 | -1.9 |
| VLDL-C | 153 | -21.2 | 117 | -18.0 | 114 | +5.6 | -28.7** | -23.7* |
| HDL-C | 28 | 0.0 | 30 | 0.0 | 30 | 0.0 | +3.9 | +5.2 |
| LDL-C | 78 | +20.3 | 85 | +12.8 | 94 | -5.9 | +24.7** | +18.9* |
The effects of omega-3-acid ethyl esters 4 capsules per day were assessed in 2 randomized, placebo-controlled, double-blind, parallel-group studies of 84 adult patients (42 on omega-3-acid ethyl esters, 42 on placebo) with severe hypertriglyceridemia. Patients whose baseline TG levels were between 500 and 2,000 mg/dL were enrolled in these 2 studies of 6 and 16 weeks duration. The median triglyceride and LDL-C levels in these patients were 792 mg/dL and 100 mg/dL, respectively. Median HDL-C level was 23.0 mg/dL.
The changes in the major lipoprotein lipid parameters for the groups receiving omega-3-acid ethyl esters or placebo are shown in Table 3.
Table 3. Median Baseline and Percent Change From Baseline in Lipid Parameters in Patients with Severe Hypertriglyceridemia (≥500 mg/dL)
| Parameter | Omega-3-Acid Ethyl Esters* N = 42 | Placebo N = 42 | Difference | |||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| BL | % Change | BL | % Change | |||||||||||
BL = Baseline (mg/dL); % Change = Median Percent Change from Baseline; Difference = Omega-3-acid ethyl esters Median % Change – Placebo Median % Change * OMTRYG and omega-3-acid ethyl esters each contain, among other components, at least 900 mg per capsule of ethyl esters from omega-3 fatty acids sourced from fish oils. | ||||||||||||||
| TG | 816 | -44.9 | 788 | +6.7 | -51.6 | |||||||||
| Non-HDL-C | 271 | -13.8 | 292 | -3.6 | -10.2 | |||||||||
| TC | 296 | -9.7 | 314 | -1.7 | -8.0 | |||||||||
| VLDL-C | 175 | -41.7 | 175 | -0.9 | -40.8 | |||||||||
| HDL-C | 22 | +9.1 | 24 | 0.0 | +9.1 | |||||||||
| LDL-C | 89 | +44.5 | 108 | -4.8 | +49.3 | |||||||||
Omega-3-acid ethyl esters reduced median TG, VLDL-C, and non-HDL-C levels and increased HDL-C from baseline relative to placebo. Treatment with omega-3-acid ethyl esters to reduce very high TG levels may result in elevations in LDL-C and non-HDL-C in some individuals. Patients should be monitored to ensure that the LDL-C level does not increase excessively.
The effect of OMTRYG on the risk of pancreatitis has not been evaluated.
The effect of OMTRYG on cardiovascular mortality and morbidity has not been determined.
16 HOW SUPPLIED/STORAGE AND HANDLING
OMTRYG (omega-3-acid ethyl esters) capsules, USP, 1.2 grams, are supplied as type A transparent soft-gelatin capsules filled with light-yellow oil and bearing the designation TP0001.
Bottles of 120: NDC 61112-001-01
Store at 25°C (77°F); excursions permitted to 15° to 30°C (59° to 86°F) [see USP Controlled Room Temperature]. Do not freeze.
Dispense in a tight, light-resistant container.
17 PATIENT COUNSELING INFORMATION
See FDA-approved Patient Labeling (Patient Information)
- Use OMTRYG with caution in patients with known sensitivity or allergy to fish and/or shellfish [see Warnings and Precautions (5.2)].
- Advise patients that use of lipid-regulating agents does not reduce the importance of adhering to diet [see Dosage and Administration (2)].
- Advise patients to take OMTRYG as prescribed. If a dose is missed, patients should take it as soon as they remember. However, if they miss one day of OMTRYG, they should not double the dose when they take it.
- Advise patients to take OMTRYG capsules with meals [see Dosage and Administration (2)].
- Advise patients to swallow OMTRYG capsules whole. Do not break, open, crush, dissolve or chew OMTRYG [see Dosage and Administration (2)].
Patient labeling is provided as a tear-off leaflet at the end of this full prescribing information.
Manufactured for:
Trygg Pharma, Inc.
1001 North 19th St.
Suite 1200
Arlington, VA 22209
OMTRYG is a registered trademark of Trygg Pharma Inc.