


Prescribing information (package insert) - Moxifloxacin Injection
WARNING: SERIOUS ADVERSE REACTIONS INCLUDING TENDINITIS, TENDON RUPTURE, PERIPHERAL NEUROPATHY, CENTRAL NERVOUS SYSTEM EFFECTS and EXACERBATION OF MYASTHENIA GRAVIS
Fluoroquinolones, including moxifloxacin, have been associated with disabling and potentially irreversible serious adverse reactions that have occurred together [see Warnings and Precautions (5.1)] , including:
- Tendinitis and tendon rupture [see Warnings and Precautions (5.2)]
- Peripheral neuropathy [see Warnings and Precautions (5.3)]
- Central nervous system effects [see Warnings and Precautions (5.4)]
Discontinue Moxifloxacin Injection immediately and avoid the use of fluoroquinolones, including Moxifloxacin Injection, in patients who experience any of these serious adverse reactions [see Warnings and Precautions (5.1)].
- Fluoroquinolones, including moxifloxacin, may exacerbate muscle weakness in patients with myasthenia gravis. Avoid Moxifloxacin Injection in patients with known history of myasthenia gravis [see Warnings and Precautions (5.5)].
Because fluoroquinolones, including moxifloxacin, have been associated with serious adverse reactions [see Warnings and Precautions (5.1 to 5.14)] , reserve Moxifloxacin Injection for use in patients who have no alternative treatment options for the following indications:
- Acute sinusitis [see Indications and Usage (1.5)]
- Acute bacterial exacerbation of chronic bronchitis [see Indications and Usage (1.6)]
1 INDICATIONS AND USAGE
1.1 Community Acquired Pneumonia
Moxifloxacin Injection is indicated in adults (18 years of age or older) for the treatment of Community Acquired Pneumonia caused by susceptible isolates of Streptococcus pneumoniae (including multi-drug resistant isolates*), Haemophilus influenzae, Moraxella catarrhalis, methicillin-susceptible Staphylococcus aureus, Klebsiella pneumoniae, Mycoplasma pneumoniae, or Chlamydophila pneumoniae.
* MDRSP, Multi-drug resistant Streptococcus pneumoniae includes isolates previously known as PRSP (Penicillin-resistant S. pneumoniae), and are isolates resistant to two or more of the following antibiotics: penicillin (minimum inhibitory concentrations [MIC] ≥ 2 mcg/mL), 2nd generation cephalosporins (for example, cefuroxime), macrolides, tetracyclines, and trimethoprim/sulfamethoxazole [see Clinical Studies (14.2)].
1.2 Uncomplicated Skin and Skin Structure Infections
Moxifloxacin Injection is indicated in adults (18 years of age or older) for the treatment of Uncomplicated Skin and Skin Structure Infections caused by susceptible isolates of methicillin-susceptible Staphylococcus aureus or Streptococcus pyogenes [see Clinical Studies (14.5)].
1.3 Complicated Skin and Skin Structure Infections
Moxifloxacin Injection is indicated in adults (18 years of age or older) for the treatment of Complicated Skin and Skin Structure Infections caused by susceptible isolates of methicillin-susceptible Staphylococcus aureus, Escherichia coli, Klebsiella pneumoniae, or Enterobacter cloacae [see Clinical Studies (14.6)].
1.4 Complicated Intra-Abdominal Infections
Moxifloxacin Injection is indicated in adults (18 years of age or older) for the treatment of Complicated Intra-Abdominal Infections including polymicrobial infections such as abscess caused by susceptible isolates of Escherichia coli, Bacteroides fragilis, Streptococcus anginosus, Streptococcus constellatus, Enterococcus faecalis, Proteus mirabilis, Clostridium perfringens, Bacteroides thetaiotaomicron, or Peptostreptococcus species [see Clinical Studies (14.7)].
1.5 Acute Bacterial Sinusitis
Moxifloxacin Injection is indicated in adults (18 years of age or older) for the treatment of Acute Bacterial Sinusitis (ABS) caused by susceptible isolates of Streptococcus pneumoniae, Haemophilus influenzae, or Moraxella catarrhalis [see Clinical Studies (14.4)].
Because fluoroquinolones, including Moxifloxacin Injection, have been associated with serious adverse reactions [see Warnings and Precautions (5.1 to 5.14)] and for some patients ABS is self-limiting, reserve Moxifloxacin Injection for treatment of ABS in patients who have no alternative treatment options.
1.6 Acute Bacterial Exacerbation of Chronic Bronchitis
Moxifloxacin Injection is indicated in adults (18 years of age or older) for the treatment of Acute Bacterial Exacerbation of Chronic Bronchitis (ABECB) caused by susceptible isolates of Streptococcus pneumoniae, Haemophilus influenzae, Haemophilus parainfluenzae, Klebsiella pneumoniae, methicillin-susceptible Staphylococcus aureus, or Moraxella catarrhalis [see Clinical Studies (14.1)].
Because fluoroquinolones, including Moxifloxacin Injection, have been associated with serious adverse reactions [see Warnings and Precautions (5.1 to 5.14)] and for some patients ABECB is self-limiting, reserve Moxifloxacin Injection for treatment of ABECB in patients who have no alternative treatment options.
1.7 Usage
To reduce the development of drug-resistant bacteria and maintain the effectiveness of Moxifloxacin Injection and other antibacterial drugs, Moxifloxacin Injection should be used only to treat or prevent infections that are proven or strongly suspected to be caused by susceptible bacteria. When culture and susceptibility information are available, they should be considered in selecting or modifying antibacterial therapy. In the absence of such data, local epidemiology and susceptibility patterns may contribute to the empiric selection of therapy.
2 DOSAGE AND ADMINISTRATION
2.1 Dosage in Adult Patients
The dose of Moxifloxacin Injection is 400 mg intravenously once every 24 hours. The duration of therapy depends on the type of infection as described in Table 1.
Table 1: Dosage and Duration of Therapy in Adult Patients
| a Due to the designated pathogens [see Indications and Usage (1), for IV use, see Use in Specific Populations (8.5)]. | ||
| b Sequential therapy (intravenous to oral) may be instituted at the discretion of the physician. | ||
| Type of Infection a | Dose Every 24 hours | Duration b (days) |
| Community Acquired Pneumonia (1.1) | 400 mg | 7 to 14 |
| Uncomplicated Skin and Skin Structure Infections (SSSI) (1.2) | 400 mg | 7 |
| Complicated SSSI (1.3) | 400 mg | 7 to 21 |
| Complicated Intra-Abdominal Infections (1.4) | 400 mg | 5 to 14 |
| Acute Bacterial Sinusitis (1.5) | 400 mg | 10 |
| Acute Bacterial Exacerbation of Chronic Bronchitis (1.6) | 400 mg | 5 |
When switching from intravenous to oral formulation, no dosage adjustment is necessary [see Clinical Pharmacology (12.4)]. Patients whose therapy is started with Moxifloxacin Injection may be switched to moxifloxacin tablets when clinically indicated at the discretion of the physician.
2.2 Administration Instructions
Moxifloxacin Injection Solution for Infusion
Parenteral drug products should be inspected visually for particulate matter and discoloration prior to administration, whenever solution and container permit.
Moxifloxacin Injection should be administered by intravenous infusion only. It is not intended for intra-arterial, intramuscular, intrathecal, intraperitoneal, or subcutaneous administration.
Moxifloxacin Injection should be administered by intravenous infusion over a period of 60 minutes by direct infusion or through a Y-type intravenous infusion set which may already be in place. Caution: rapid or bolus intravenous infusion must be avoided.
Because only limited data are available on the compatibility of moxifloxacin intravenous injection with other intravenous substances, additives or other medications should not be added to Moxifloxacin Injection or infused simultaneously through the same intravenous line. If the same intravenous line or a Y-type line is used for sequential infusion of other drugs, or if the “piggyback” method of administration is used, the line should be flushed before and after infusion of Moxifloxacin Injection with an infusion solution compatible with moxifloxacin injection as well as with other drug(s) administered via this common line.
Moxifloxacin Injection is compatible with the following intravenous solutions at ratios from 1:10 to 10:1
| 0.9% Sodium Chloride Injection, USP | Sterile Water for Injection, USP |
| 1 molar Sodium Chloride Injection | 10% Dextrose for Injection, USP |
| 5% Dextrose Injection, USP | Lactated Ringer's for Injection |
2.3 Preparation for Administration of Moxifloxacin Injection
To prepare Moxifloxacin Injection premix in flexible bags:
- 1. Close flow control clamp of administration set.
- 2. Remove cover from port at bottom of container.
- 3. Insert piercing pin from an appropriate transfer set (for example, one that does not require excessive force, such as ISO compatible administration set) into port with a gentle twisting motion until pin is firmly seated.
NOTE: Refer to complete directions that have been provided with the administration set.
Because the premix flexible bags are for single-dose only, any unused portion should be discarded.
3 DOSAGE FORMS AND STRENGTHS
Moxifloxacin Injection
Each single-dose flexible bag contains 400 mg of moxifloxacin in 250 mL, each mL contains 1.6 mg of moxifloxacin.
4 CONTRAINDICATIONS
Moxifloxacin is contraindicated in persons with a history of hypersensitivity to moxifloxacin or any member of the quinolone class of antimicrobial agents.
5 WARNINGS AND PRECAUTIONS
5.1 Disabling and Potentially Irreversible Serious Adverse Reactions Including Tendinitis and Tendon Rupture, Peripheral Neuropathy, and Central Nervous System Effects
Fluoroquinolones, including Moxifloxacin Injection, have been associated with disabling and potentially irreversible serious adverse reactions from different body systems that can occur together in the same patient. Commonly seen adverse reactions include tendinitis, tendon rupture, arthralgia, myalgia, peripheral neuropathy, and central nervous system effects (hallucinations, anxiety, depression, insomnia, severe headaches, and confusion).
These reactions can occur within hours to weeks after starting moxifloxacin. Patients of any age or without pre-existing risk factors have experienced these adverse reactions [see Warnings and Precautions (5.2, 5.3, 5.4)].
Discontinue Moxifloxacin Injection immediately at the first signs or symptoms of any serious adverse reaction. In addition, avoid the use of fluoroquinolones, including moxifloxacin, in patients who have experienced any of these serious adverse reactions associated with fluoroquinolones.
5.2 Tendinitis and Tendon Rupture
Fluoroquinolones, including moxifloxacin, have been associated with an increased risk of tendinitis and tendon rupture in all ages [see Warnings and Precautions (5.1) and Adverse Reactions (6.1)]. This adverse reaction most frequently involves the Achilles tendon, and has also been reported with the rotator cuff (the shoulder), the hand, the biceps, the thumb, and other tendons. Tendinitis or tendon rupture can occur within hours or days of starting moxifloxacin or as long as several months after completion of therapy. Tendinitis and tendon rupture can occur bilaterally.
The risk of developing fluoroquinolone-associated tendinitis and tendon rupture is increased in patients over 60 years of age, in patients taking corticosteroid drugs, and in patients with kidney, heart or lung transplants. Other factors that may independently increase the risk of tendon rupture include strenuous physical activity, renal failure, and previous tendon disorders such as rheumatoid arthritis. Tendinitis and tendon rupture have also occurred in patients taking fluoroquinolones who do not have the above risk factors. Discontinue moxifloxacin if the patient experiences pain, swelling, inflammation or rupture of a tendon. Patients should be advised to rest at the first sign of tendinitis or tendon rupture, and to contact their healthcare provider regarding changing to a non- quinolone antimicrobial drug [see Adverse Reactions (6.2) and Patient Counseling Information (17)]. Avoid fluoroquinolones, including moxifloxacin, in patients who have a history of tendon disorders or have experienced tendinitis or tendon rupture [see Adverse Reactions (6.1)].
5.3 Peripheral Neuropathy
Fluoroquinolones, including moxifloxacin, have been associated with an increased risk of peripheral neuropathy. Cases of sensory or sensorimotor axonal polyneuropathy affecting small and/or large axons resulting in paresthesias, hypoesthesias, dysesthesias and weakness have been reported in patients receiving fluoroquinolones including moxifloxacin. Symptoms may occur soon after initiation of moxifloxacin and may be irreversible in some patients [see Warnings and Precautions (5.1) and Adverse Reactions (6, 6.1, 6.2)].
Discontinue moxifloxacin immediately if the patient experiences symptoms of peripheral neuropathy including pain, burning, tingling, numbness, and/or weakness or other alterations of sensation including light touch, pain, temperature, position sense, and vibratory sensation. Avoid fluoroquinolones, including moxifloxacin, in patients who have previously experienced peripheral neuropathy [see Adverse Reactions (6.1, 6.2) and Patient Counseling Information (17)].
5.4 Central Nervous System Effects
Psychiatric Adverse Reactions
Fluoroquinolones, including moxifloxacin, have been associated with an increased risk of psychiatric adverse reactions, including: toxic psychosis, hallucinations, or paranoia; depression or suicidal thoughts or acts; anxiety, agitation, or nervousness; confusion, delirium, disorientation, or disturbances in attention; insomnia or nightmares; and memory impairment. These adverse reactions may occur following the first dose. If these reactions occur in patients receiving moxifloxacin, discontinue moxifloxacin immediately and institute appropriate measures [see Adverse Reactions (6.1, 6.2)].
Central Nervous System Adverse Reactions
Fluoroquinolones, including moxifloxacin, have been associated with an increased risk of seizures (convulsions), increased intracranial pressure (including pseudotumor cerebri), dizziness, and tremors. As with all fluoroquinolones, use moxifloxacin with caution in patients with known or suspected CNS disorders (for example, severe cerebral arteriosclerosis, epilepsy) or in the presence of other risk factors that may predispose to seizures or lower the seizure threshold. These adverse reactions may occur following the first dose. If these reactions occur in patients receiving moxifloxacin, discontinue moxifloxacin immediately and institute appropriate measures [see Drug Interactions (7.3), Adverse Reactions (6.1, 6.2) and Patient Counseling Information (17)].
5.5 Exacerbation of Myasthenia Gravis
Fluoroquinolones, including moxifloxacin, have neuromuscular blocking activity and may exacerbate muscle weakness in patients with myasthenia gravis. Postmarketing serious adverse reactions, including deaths and requirement for ventilatory support, have been associated with fluoroquinolone use in patients with myasthenia gravis. Avoid moxifloxacin in patients with known history of myasthenia gravis [see Patient Counseling Information (17)].
5.6 QT Prolongation
Moxifloxacin has been shown to prolong the QT interval of the electrocardiogram in some patients. Following oral dosing with 400 mg of moxifloxacin the mean (± SD) change in QTc from the pre-dose value at the time of maximum drug concentration was 6 msec (± 26) (n = 787). Following a course of daily intravenous dosing (400 mg; 1 hour infusion each day) the mean change in QTc from the Day 1 pre-dose value was 10 msec (± 22) on Day 1 (n = 667) and 7 msec (± 24) on Day 3 (n = 667).
The drug should be avoided in patients with known prolongation of the QT interval, patients with uncorrected hypokalemia and patients receiving Class IA (for example, quinidine, procainamide) or Class III (for example, amiodarone, sotalol) antiarrhythmic agents, due to the lack of clinical experience with the drug in these patient populations.
Pharmacokinetic studies between moxifloxacin and other drugs that prolong the QT interval such as cisapride, erythromycin, antipsychotics, and tricyclic antidepressants have not been performed. An additive effect of moxifloxacin and these drugs cannot be excluded; therefore caution should be exercised when moxifloxacin is given concurrently with these drugs. In premarketing clinical trials, the rate of cardiovascular adverse events was similar in 798 moxifloxacin and 702 comparator treated patients who received concomitant therapy with drugs known to prolong the QTc interval.
Moxifloxacin should be used with caution in patients with ongoing proarrhythmic conditions, such as clinically significant bradycardia, acute myocardial ischemia. The magnitude of QT prolongation may increase with increasing concentrations of the drug or increasing rates of infusion of the intravenous formulation. Therefore the recommended dose or infusion rate should not be exceeded. QT prolongation may lead to an increased risk for ventricular arrhythmias including torsades de pointes. No excess in cardiovascular morbidity or mortality attributable to QTc prolongation occurred with moxifloxacin treatment in over 15,500 patients in controlled clinical studies, including 759 patients who were hypokalemic at the start of treatment, and there was no increase in mortality in over 18,000 moxifloxacin tablet treated patients in a postmarketing observational study in which ECGs were not performed. Elderly patients using Moxifloxacin Injection may be more susceptible to drug-associated QT prolongation [see Use in Specific Populations (8.5)]. In addition, moxifloxacin should be used with caution in patients with mild, moderate, or severe liver cirrhosis [see Clinical Pharmacology (12.3) and Patient Counseling Information (17)].
5.7 Hypersensitivity Reactions
Serious anaphylactic reactions, some following the first dose, have been reported in patients receiving fluoroquinolone therapy, including moxifloxacin. Some reactions were accompanied by cardiovascular collapse, loss of consciousness, tingling, pharyngeal or facial edema, dyspnea, urticaria, and itching. Discontinue Moxifloxacin Injection at the first appearance of a skin rash or any other sign of hypersensitivity [see Warnings and Precautions (5.7), Adverse Reactions (6) and Patient Counseling Information (17)].
5.8 Other Serious and Sometimes Fatal Adverse Reactions
Other serious and sometimes fatal adverse reactions, some due to hypersensitivity, and some due to uncertain etiology, have been reported rarely in patients receiving therapy with quinolones, including moxifloxacin. These events may be severe and generally occur following the administration of multiple doses. Clinical manifestations may include one or more of the following:
- Fever, rash, or severe dermatologic reactions (for example, toxic epidermal necrolysis, Stevens-Johnson syndrome)
- Vasculitis; arthralgia; myalgia; serum sickness
- Allergic pneumonitis
- Interstitial nephritis; acute renal insufficiency or failure
- Hepatitis; jaundice; acute hepatic necrosis or failure
- Anemia, including hemolytic and aplastic; thrombocytopenia, including thrombotic thrombocytopenic purpura; leukopenia; agranulocytosis; pancytopenia; and/or other hematologic abnormalities
Discontinue Moxifloxacin Injection immediately at the first appearance of a skin rash, jaundice, or any other sign of hypersensitivity and supportive measures instituted [see Patient Counseling Information (17) and Adverse Reactions (6.2)].
5.9 Risk of Aortic Aneurysm and Dissection
Epidemiologic studies report an increased rate of aortic aneurysm and dissection within two months following use of fluoroquinolones, particularly in elderly patients. The cause for the increased risk has not been identified. In patients with a known aortic aneurysm or patients who are at greater risk for aortic aneurysms, reserve Moxifloxacin Injection for use only when there are no alternative antibacterial treatments available.
5.10 Clostridioides Difficile-Associated Diarrhea
Clostridioides difficile-associated diarrhea (CDAD) has been reported with use of nearly all antibacterial agents, including moxifloxacin, and may range in severity from mild diarrhea to fatal colitis. Treatment with antibacterial agents alters the normal flora of the colon leading to overgrowth of C. difficile.
C. difficile produces toxins A and B which contribute to the development of CDAD. Hypertoxin producing strains of C. difficile cause increased morbidity and mortality, as these infections can be refractory to antimicrobial therapy and may require colectomy. CDAD must be considered in all patients who present with diarrhea following antibiotic use. Careful medical history is necessary since CDAD has been reported to occur over two months after the administration of antibacterial agents.
If CDAD is suspected or confirmed, ongoing antibiotic use not directed against C. difficile may need to be discontinued. Appropriate fluid and electrolyte management, protein supplementation, antibiotic treatment of C. difficile, and surgical evaluation should be instituted as clinically indicated [see Adverse Reactions (6.1) and Patient Counseling Information (17)].
5.11 High Sodium Load
Each unit dose of Moxifloxacin Injection contains 52.5 mEq (1,207 mg) of sodium. Avoid use of Moxifloxacin Injection in patients with congestive heart failure, elderly, and those with restricted sodium intake [see Use in Specific Populations (8.5), Description (11)].
5.12 Arthropathic Effects in Animals
The oral administration of moxifloxacin caused lameness in immature dogs. Histopathological examination of the weight-bearing joints of these dogs revealed permanent lesions of the cartilage. Related quinolone-class drugs also produce erosions of cartilage of weight-bearing joints and other signs of arthropathy in immature animals of various species [see Nonclinical Toxicology (13.2)].
5.13 Blood Glucose Disturbances
As with all fluoroquinolones, disturbances in blood glucose, including both hypoglycemia and hyperglycemia have been reported with moxifloxacin. In moxifloxacin-treated patients, dysglycemia occurred predominantly in elderly diabetic patients receiving concomitant treatment with an oral hypoglycemic agent (for example, sulfonylurea) or with insulin. Severe cases of hypoglycemia resulting in coma or death have been reported. In diabetic patients, careful monitoring of blood glucose is recommended [see Adverse Reactions (6.1)]. If a hypoglycemic reaction occurs, discontinue moxifloxacin and initiate appropriate therapy immediately [see Adverse Reactions (6.1), Drug Interactions (7.2) and Patient Counseling Information (17)].
5.14 Photosensitivity/Phototoxicity
Moderate to severe photosensitivity/phototoxicity reactions, the latter of which may manifest as exaggerated sunburn reactions (for example, burning, erythema, exudation, vesicles, blistering, edema) involving areas exposed to light (typically the face, “V” area of the neck, extensor surfaces of the forearms, dorsa of the hands), can be associated with the use of quinolone antibiotics after sun or UV light exposure. Therefore, excessive exposure to these sources of light should be avoided. Drug therapy should be discontinued if phototoxicity occurs [see Adverse Reactions (6.2) and Clinical Pharmacology (12.3)].
5.15 Development of Drug Resistant Bacteria
Prescribing moxifloxacin in the absence of a proven or strongly suspected bacterial infection or a prophylactic indication is unlikely to provide benefit to the patient and increases the risk of the development of drug-resistant bacteria [see Patient Counseling Information (17)].
6 ADVERSE REACTIONS
The following serious and otherwise important adverse reactions are discussed in greater detail in the Warnings and Precautions section of the label:
- Disabling and Potentially Irreversible Serious Adverse Reactions Including Tendinitis and Tendon Rupture, Peripheral Neuropathy, and Central Nervous System Effects [see Warnings and Precautions (5.1)]
- Tendinitis and Tendon Rupture [see Warnings and Precautions (5.2)]
- Peripheral Neuropathy [see Warnings and Precautions (5.3)]
- Central Nervous System Effects [see Warnings and Precautions (5.4)]
- Exacerbation of Myasthenia Gravis [see Warnings and Precautions (5.5)]
- QT Prolongation [see Warnings and Precautions (5.6)]
- Hypersensitivity Reactions [see Warnings and Precautions (5.7)]
- Other Serious and Sometimes Fatal Adverse Reactions [see Warnings and Precautions (5.8)]
- Clostridioides Difficile-Associated Diarrhea [see Warnings and Precautions (5.10)]
- Blood Glucose Disturbances [see Warnings and Precautions (5.13)]
- Photosensitivity/Phototoxicity [see Warnings and Precautions (5.14)]
- Development of Drug Resistant Bacteria [see Warnings and Precautions (5.15)]
6.1 Clinical Trials Experience
Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice.
The data described below reflect exposure to moxifloxacin in 14,981 patients in 71 active controlled Phase II - IV clinical trials in different indications [see Indications and Usage (1)]. The population studied had a mean age of 50 years (approximately 73% of the population was < 65 years of age), 50% were male, 63% were Caucasian, 12% were Asian and 9% were Black. Patients received moxifloxacin 400 mg once daily PO, IV, or sequentially (IV followed by PO). Treatment duration was usually 6 to 10 days, and the mean number of days on therapy was 9 days.
Discontinuation of moxifloxacin due to adverse events occurred in 5% of patients overall, 4.1% of patients treated with 400 mg PO, 3.9% with 400 mg IV and 8.2% with sequential therapy 400 mg PO/IV. The most common adverse events leading to discontinuation with the 400 mg PO doses were nausea (0.8%), diarrhea (0.5%), dizziness (0.5%), and vomiting (0.4%). The most common adverse event leading to discontinuation with the 400 mg IV dose was rash (0.5%). The most common adverse events leading to discontinuation with the 400 mg IV/PO sequential dose were diarrhea (0.5%) and pyrexia (0.4%).
Adverse reactions occurring in ≥ 1% of moxifloxacin-treated patients and less common adverse reactions, occurring in 0.1 to < 1% of moxifloxacin-treated patients, are shown in Table 2 and Table 3, respectively. The most common adverse drug reactions (≥ 3%) are nausea, diarrhea, headache, and dizziness.
Table 2: Common (≥1%) Adverse Reactions Reported in Active-Controlled Clinical Trials with Moxifloxacin
| a MedDRA Version 12.0 | ||
| System Organ Class | Adverse Reactions a | % (N=14,981) |
| Blood and Lymphatic System Disorders | Anemia | 1.1 |
| Gastrointestinal Disorders | Nausea | 6.9 |
| Diarrhea | 6 | |
| Vomiting | 2.4 | |
| Constipation | 1.9 | |
| Abdominal pain | 1.5 | |
| Abdominal pain upper | 1.1 | |
| Dyspepsia | 1 | |
| General Disorders and Administration Site Conditions | Pyrexia | 1.1 |
| Investigations | Alanine aminotransferase increased | 1.1 |
| Metabolism and Nutritional Disorder | Hypokalemia | 1 |
| Nervous System Disorders | Headache | 4.2 |
| Dizziness | 3 | |
| Psychiatric Disorders | Insomnia | 1.9 |
Table 3: Less Common (0.1 to < 1%) Adverse Reactions Reported in Active-Controlled Clinical Trials with Moxifloxacin (N=14,981)
| a MedDRA Version 12.0 | |
| System Organ Class | Adverse Reactions a |
| Blood and Lymphatic System Disorders | Thrombocythemia Eosinophilia Neutropenia Thrombocytopenia Leukopenia Leukocytosis |
| Cardiac Disorders | Atrial fibrillation Palpitations Tachycardia Cardiac failure congestive Angina pectoris Cardiac failure Cardiac arrest Bradycardia |
| Ear and Labyrinth Disorders | Vertigo Tinnitus |
| Eye Disorders | Vision blurred |
| Gastrointestinal Disorders | Dry mouth Abdominal discomfort Flatulence Abdominal distention Gastritis Gastroesophageal reflux disease |
| General Disorders and Administration Site Conditions | Fatigue Chest pain Asthenia Edema peripheral Pain Malaise |
| System Organ Class | Adverse Reactions a |
Infusion site extravasation Edema Chills Chest discomfort Facial pain | |
| Hepatobiliary Disorders | Hepatic function abnormal |
| Infections and Infestations | Vulvovaginal candidiasis Oral candidiasis Vulvovaginal mycotic infection Candidiasis Vaginal infection Oral fungal infection Fungal infection Gastroenteritis |
| Investigations | Aspartate aminotransferase increased Gamma-glutamyltransferase increased Blood alkaline phosphatase increased Hepatic enzyme increased Electrocardiogram QT prolonged Blood lactate dehydrogenase increased Platelet count increased Blood amylase increased Blood glucose increased Lipase increased Hemoglobin decreased Blood creatinine increased Transaminases increased White blood cell count increased Blood urea increased Liver function test abnormal Hematocrit decreased Prothrombin time prolonged Eosinophil count increased Activated partial thromboplastin time prolonged Blood bilirubin increased Blood triglycerides increased Blood uric acid increased Blood pressure increased |
| Metabolism and Nutrition Disorders | Hyperglycemia Anorexia Hypoglycemia Hyperlipidemia Decreased appetite Dehydration |
| Musculoskeletal and Connective Tissue Disorders | Back pain Pain in extremity Arthralgia Myalgia Muscle spasms Musculoskeletal chest pain Musculoskeletal pain |
| Nervous System Disorders | Dysgeusia Somnolence Tremor Lethargy |
| System Organ Class | Adverse Reactions a |
Paresthesia Tension headache Hypoesthesia Syncope | |
| Psychiatric Disorders | Anxiety Confusional state Agitation Depression Nervousness Restlessness Hallucination Disorientation |
| Renal and Urinary Disorders | Renal failure Dysuria Renal failure acute |
| Reproductive System and Breast Disorders | Vulvovaginal pruritus |
| Respiratory, Thoracic, and Mediastinal Disorders | Dyspnea Asthma Wheezing Bronchospasm |
| Skin and Subcutaneous Tissue Disorders | Rash Pruritus Hyperhidrosis Erythema Urticaria Dermatitis allergic Night sweats |
| Vascular Disorders | Hypertension Hypotension Phlebitis |
Laboratory Changes
Changes in laboratory parameters, without regard to drug relationship, which are not listed above and which occurred in ≥ 2% of patients and at an incidence greater than in controls included: increases in MCH, neutrophils, WBCs, PT ratio, ionized calcium, chloride, albumin, globulin, bilirubin; decreases in hemoglobin, RBCs, neutrophils, eosinophils, basophils, PT ratio, glucose, pO2, bilirubin, and amylase. It cannot be determined if any of the above laboratory abnormalities were caused by the drug or the underlying condition being treated.
6.2 Postmarketing Experience
Table 4 lists adverse reactions that have been identified during post-approval use of moxifloxacin. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
Table 4: Postmarketing Reports of Adverse Drug Reactions
| System/Organ Class | Adverse Reaction |
| Blood and Lymphatic System Disorders | Agranulocytosis Pancytopenia [see Warnings and Precautions (5.8)] |
| Cardiac Disorders | Ventricular tachyarrhythmias (including in very rare cases cardiac arrest and torsades de pointes, and usually in patients with concurrent severe underlying proarrhythmic conditions) |
| Ear and Labyrinth Disorders | Hearing impairment, including deafness (reversible in majority of cases) |
| Eye Disorders | Vision loss (especially in the course of CNS reactions, transient in majority of cases) |
| Hepatobiliary Disorders | Hepatitis (predominantly cholestatic) Hepatic failure (including fatal cases) Jaundice Acute hepatic necrosis [see Warnings and Precautions (5.8)] |
| Immune System Disorders | Anaphylactic reaction Anaphylactic shock Angioedema (including laryngeal edema) [see Warnings and Precautions (5.7, 5.8)] |
| Musculoskeletal and Connective Tissue Disorders | Tendon rupture [see Warnings and Precautions (5.2)] |
| Nervous System Disorders | Altered coordination Abnormal gait [see Warnings and Precautions (5.3)] Myasthenia gravis (exacerbation of) [see Warnings and Precautions (5.5)] Muscle weakness Peripheral neuropathy (that may be irreversible), polyneuropathy [see Warnings and Precautions (5.3)] |
| Psychiatric Disorders | Psychotic reaction (very rarely culminating in self- injurious behavior, such as suicidal ideation/thoughts or suicide attempts [see Warnings and Precautions (5.4)] |
| Renal and Urinary Disorders | Renal dysfunction Interstitial nephritis [see Warnings and Precautions (5.8)] |
| Respiratory, Thoracic and Mediastinal Disorders | Allergic pneumonitis [see Warnings and Precautions (5.8)] |
| Skin and Subcutaneous Tissue Disorders | Photosensitivity/phototoxicity reaction [see Warnings and Precautions (5.14)] Stevens-Johnson syndrome Toxic epidermal necrolysis [see Warnings and Precautions (5.8)] |
7 DRUG INTERACTIONS
7.1 Warfarin
Quinolones, including moxifloxacin, have been reported to enhance the anticoagulant effects of warfarin or its derivatives in the patient population. In addition, infectious disease and its accompanying inflammatory process, age, and general status of the patient are risk factors for increased anticoagulant activity. Therefore, the prothrombin time, International Normalized Ratio (INR), or other suitable anticoagulation tests should be closely monitored if a quinolone is administered concomitantly with warfarin or its derivatives [see Adverse Reactions (6, 6.1,), Clinical Pharmacology (12.3), and Patient Counseling Information (17)].
7.2 Antidiabetic Agents
Disturbances of blood glucose, including hyperglycemia and hypoglycemia, have been reported in patients treated concomitantly with fluoroquinolones and an antidiabetic agent. Therefore, careful monitoring of blood glucose is recommended when these agents are co-administered. If a hypoglycemic reaction occurs, moxifloxacin should be discontinued and appropriate therapy should be initiated immediately [see Warnings and Precautions (5.13), Adverse Reactions (6.1), and Patient Counseling Information (17)].
7.3 Nonsteroidal Anti-Inflammatory Drugs (NSAIDs)
Although not observed with moxifloxacin in preclinical and clinical trials, the concomitant administration of a nonsteroidal anti-inflammatory drug with a quinolone may increase the risks of CNS stimulation and convulsions [see Warnings and Precautions (5.4), and Patient Counseling Information (17)].
7.4 Drugs that Prolong QT
There is limited information available on the potential for a pharmacodynamic interaction in humans between moxifloxacin and other drugs that prolong the QTc interval of the electrocardiogram. Sotalol, a Class III antiarrhythmic, has been shown to further increase the QTc interval when combined with high doses of intravenous (IV) moxifloxacin in dogs. Therefore, moxifloxacin should be avoided with Class IA and Class III antiarrhythmics [see Warnings and Precautions (5.6), Nonclinical Toxicology (13.2), and Patient Counseling Information (17)].
8 USE IN SPECIFIC POPULATIONS
8.1 Pregnancy
Risk Summary
There are no available human data establishing a drug associated risk with the use of moxifloxacin.
Based on animal studies, Moxifloxacin Injection may cause fetal harm. Moxifloxacin did not cause fetal malformations when administered to pregnant rats (IV and oral), rabbits (IV) and monkeys (oral) at exposures that were 0.24-2.5 times of those at the human clinical dose (400mg/day moxifloxacin). However, when moxifloxacin was administered to rats and rabbits during pregnancy and throughout lactation (rats only) at doses associated with maternal toxicity, decreased neonatal body weights, increased incidence of skeletal variations (rib and vertebra combined), and increased fetal loss were observed (see Data). Advise pregnant women of the potential risk to the fetus.
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Data
Animal Data
Animal reproductive and development studies were done in rats, rabbits and cynomolgus macaques. Moxifloxacin did not cause fetal malformations when administered to pregnant rats during organogenesis (gestation days 6 to 17) at oral doses as high as 500 mg/kg/day or 0.24 times the maximum recommended human dose based on systemic exposure (AUC), but decreased fetal body weights and slightly delayed fetal skeletal development were observed. Intravenous administration of 80 mg/kg/day (approximately 2 times the maximum recommended human dose based on body surface area) to pregnant rats resulted in maternal toxicity and a marginal effect on fetal and placental weights and the appearance of the placenta (Gestation days 6 to 17). Fetal malformations were not observed at intravenous doses as high as 80 mg/kg/day (approximately 2 times the maximum recommended human dose based on body surface area) in litters of pregnant rats that received moxifloxacin during organogenesis (Gestation days 6 to 17).
Intravenous administration of 20 mg/kg/day (approximately equal to the maximum recommended human oral dose based upon systemic exposure) to pregnant rabbits during organogenesis (gestation days 6 to 20) resulted in decreased fetal body weights and delayed fetal skeletal ossification. When rib and vertebral malformations were combined, there was an increased fetal and litter incidence of these effects in rabbits. Signs of maternal toxicity in rabbits at this dose included mortality, abortions, marked reduction of food consumption, decreased water intake, body weight loss and hypoactivity. Fetal malformations were not observed when pregnant cynomolgus macaques were given oral doses as high as 100 mg/kg/day (2.5 times the maximum recommended human dose based upon systemic exposure) during organogenesis (gestation days 20 to 50). An increased incidence of smaller fetuses was observed at 100 mg/kg/day in macaques. In a pre- and postnatal development study conducted in rats given oral doses from Gestation day 6, throughout gestation and rearing to Postpartum day 21, effects observed at 500 mg/kg/day (0.24 times the maximum recommended human dose based on systemic exposure (AUC)) included slight increases in duration of pregnancy and prenatal loss, reduced pup birth weight and decreased neonatal survival. Treatment-related maternal mortality occurred during gestation at 500 mg/kg/day in this study.
8.2 Lactation
Risk Summary
It is not known if moxifloxacin is present in human milk. Based on animal studies in rats, moxifloxacin may be excreted in human milk (see Data). When a drug is present in animal milk, it is likely that the drug will be present in human milk.
The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for Moxifloxacin Injection and any potential adverse effects on the breastfed child from Moxifloxacin Injection or from the underlying maternal condition.
Data
In lactating rats given a single oral dose of 4.59 mg/kg moxifloxacin (approximately 9 times less than the recommended human dose based on body surface area) 8 days postpartum, there was very low excretion of substance-related radioactivity into the milk, amounting to approximately 0.03% of the dose.
8.4 Pediatric Use
Effectiveness in pediatric patients and adolescents less than 18 years of age has not been established. Moxifloxacin causes arthropathy in juvenile animals. Limited information on the safety of Moxifloxacin in 301 pediatric patients is available from the cIAI trial [see Boxed Warning, Warnings and Precautions (5.9) and Nonclinical Toxicology (13.2)].
Active Controlled Trial in Complicated Intra-Abdominal Infection (cIAI)
The safety and efficacy of Moxifloxacin Injection in pediatric patients for the treatment of cIAI has not been demonstrated.
Pediatric patients 3 months to <18 years of age (mean age of 12 ± 4 years) were enrolled in a single randomized, double-blind, active controlled trial in cIAI including appendicitis with perforation, abscesses and peritonitis.
Pediatric patients were randomized (2:1) to receive either Moxifloxacin or comparator. This study enrolled 451 patients who received study medication, 301 treated with moxifloxacin, and 150 with comparator. Of the 301 pediatric patients treated with Moxifloxacin, 15 were below the age of 6 years and 286 were between the ages of 6–18 years.
Patients received sequential intravenous/oral Moxifloxacin or comparator (intravenous ertapenem followed by oral amoxicillin/clavulanate) for 5 to 14 days (mean duration was 9 days with a range of 1 to 24 days).
The overall adverse reaction profile in pediatric patients was comparable to that of adult patients. The most frequently occurring adverse reactions in pediatric patients treated with Moxifloxacin were QT prolongation 9.3% (28/301), vomiting, 6.6% (20/301) diarrhea 3.7% (11/301), arthralgia 3.0% (9/301), and phlebitis 2.7% (8/301) (see Table 5). Discontinuation of study drug due to an adverse reaction was reported in 5.3% (16/301) of Moxifloxacin-treated patients versus 1.3% (2/150) of comparator-treated patients. The adverse reaction profile of Moxifloxacin or comparator was similar across all age groups studied.
Musculoskeletal adverse reactions were monitored and followed up to 5 years after the end of study treatment. The rates of musculoskeletal adverse reactions were 4.3% (13/301) in the Moxifloxacin-treated group versus 3.3% (5/150) in the comparator-treated group. The majority of musculoskeletal adverse reactions were reported between 12 and 53 weeks after start of study treatment with complete resolution at the end of the study [see Warnings and Precautions (5.12) and Nonclinical Toxicology (13.2)].
Table 5 Incidence (%) of Selected Adverse Reactions in ≥2.0% of Pediatric Patients Treated with Moxifloxacin Injection in cIAI Clinical Trial
| System Organ Class | Adverse Reactions | Moxifloxacin Injection N = 301 (%) | Comparator N = 150 (%) |
| Gastrointestinal disorders | Abdominal pain | 8 (2.7) | 3 (2.0) |
| Diarrhea | 11 (3.7) | 1 (0.7) | |
| Vomiting | 20 (6.6) | 12 (8.0) | |
| General disorders and administration site conditions | Pyrexia | 6 (2.0) | 4 (2.7) |
| Investigations | Aspartate aminotransferase increased | 2 (0.7) | 3 (2.0) |
| Electrocardiogram QT prolonged | 28 (9.3) | 4 (2.7) | |
| Musculoskeletal and connective tissue disorders | Arthralgia | 9 (3.0) | 2 (1.3) |
| Nervous system disorders | Headache | 6 (2.0) | 2 (1.3) |
| Vascular disorders | Phlebitis | 8 (2.7) | 0 (0) |
Clinical response was assessed at the test-of-cure visit (28 to 42 days after end of treatment). The clinical response rates observed in the modified intent to treat population were 83.9% (208/248) for Moxifloxacin and 95.5% (127/133) for comparator; see Table 6.
Table 6: Clinical Response Rates at 28-42 Days After End of Treatment in Pediatric Patients with cIAI
| 1The modified intent-to-treat (mITT) population is defined as all subjects who were treated with at least one dose of study medication and who have at least one pre-treatment causative organism from the intra- abdominal site of infection or from blood cultures. | |||
| 2Difference in clinical cure rates (Moxifloxacin - Comparator) and 95% confidence intervals, presented as percentages, are based on stratified analysis by age group using Mantel-Haenszel methods. | |||
Moxifloxacin n (%) | Comparator n (%) | Difference 2 (95% CI) | |
| mITT Population 1 | N=248 | N=133 | |
| Cure | 208 (83.9) | 127 (95.5) | -12.2 (-17.9, -6.4) |
| Failure | 17 (6.9) | 3 (2.3) | |
| Indeterminate | 21 (8.5) | 3 (2.3) | |
| Missing | 2 (0.8) | 0 | |
Safety and effectiveness of Moxifloxacin Injection in pediatric patients less than 18 years of age have not been established. Moxifloxacin causes arthropathy in juvenile animals [see Boxed Warning, Warnings and Precautions (5.12), and Clinical Pharmacology (12.3)].
8.5 Geriatric Use
Geriatric patients are at increased risk for developing severe tendon disorders including tendon rupture when being treated with a fluoroquinolone such as Moxifloxacin Injection. This risk is further increased in patients receiving concomitant corticosteroid therapy. Tendinitis or tendon rupture can involve the Achilles, hand, shoulder, or other tendon sites and can occur during or after completion of therapy; cases occurring up to several months after fluoroquinolone treatment have been reported. Caution should be used when prescribing Moxifloxacin Injection to elderly patients especially those on corticosteroids. Patients should be informed of this potential side effect and advised to discontinue Moxifloxacin Injection and contact their healthcare provider if any symptoms of tendinitis or tendon rupture occur [see Boxed Warning, Warnings and Precautions (5.1, 5.2), and Adverse Reactions (6.2)].
Epidemiologic studies report an increased rate of aortic aneurysm and dissection within two months following use of fluoroquinolones, particularly in elderly patients [see Warnings and Precautions (5.9)].
Moxifloxacin Injection contains 1,207 mg (52.5 mEq) of sodium per unit dose. The geriatric population may respond with a blunted natriuresis to salt loading. This may be clinically important with regard to such diseases as congestive heart failure [see Warnings and Precautions (5.11)].
In controlled multiple-dose clinical trials, 23% of patients receiving oral moxifloxacin were greater than or equal to 65 years of age and 9% were greater than or equal to 75 years of age. The clinical trial data demonstrate that there is no difference in the safety and efficacy of oral moxifloxacin in patients aged 65 or older compared to younger adults.
In trials of intravenous use, 42% of moxifloxacin patients were greater than or equal to 65 years of age, and 23% were greater than or equal to 75 years of age. The clinical trial data demonstrate that the safety of intravenous moxifloxacin in patients aged 65 or older was similar to that of comparator-treated patients. In general, elderly patients may be more susceptible to drug-associated effects of the QT interval. Therefore, Moxifloxacin Injection should be avoided in patients taking drugs that can result in prolongation of the QT interval (for example, Class IA or Class III antiarrhythmics) or in patients with risk factors for torsades de pointes (for example, known QT prolongation, uncorrected hypokalemia) [see Warnings and Precautions (5.6), Drug Interactions (7.4), and Clinical Pharmacology (12.3)].
8.6 Renal Impairment
The pharmacokinetic parameters of moxifloxacin are not significantly altered in mild, moderate, severe, or end-stage renal disease. No dosage adjustment is necessary in patients with renal impairment, including those patients requiring hemodialysis (HD) or continuous ambulatory peritoneal dialysis (CAPD) [see Dosage and Administration (2), and Clinical Pharmacology (12.3)].
8.7 Hepatic Impairment
No dosage adjustment is recommended for mild, moderate, or severe hepatic insufficiency (Child-Pugh Classes A, B, or C). However, due to metabolic disturbances associated with hepatic insufficiency, which may lead to QT prolongation, moxifloxacin should be used with caution in these patients [see Warnings and Precautions (5.6), and Clinical Pharmacology (12.3)].
10 OVERDOSAGE
Single oral overdoses up to 2.8 g were not associated with any serious adverse events.
In the event of acute overdose, the stomach should be emptied and adequate hydration maintained. ECG monitoring is recommended due to the possibility of QT interval prolongation. The patient should be carefully observed and given supportive treatment. The administration of activated charcoal as soon as possible after oral overdose may prevent excessive increase of systemic moxifloxacin exposure. About 3% and 9% of the dose of moxifloxacin, as well as about 2% and 4.5% of its glucuronide metabolite are removed by continuous ambulatory peritoneal dialysis and hemodialysis, respectively.
11 DESCRIPTION
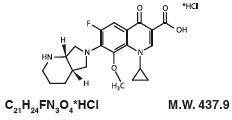
Moxifloxacin is a synthetic broad spectrum antibacterial agent for intravenous administration. Moxifloxacin, a fluoroquinolone, is available as a buffered monohydrochloride salt of 1-cyclopropyl-7-[(S,S)-2,8-diazabicyclo[4.3.0]non-8-yl]-6- fluoro-8-methoxy-1,4-dihydro-4-oxo-3 quinoline carboxylic acid. It is a slightly yellow to yellow crystalline substance. Its chemical structure is as follows:
Moxifloxacin Injection is sterile solution for infusion in a ready-to-use, single-dose flexible bag.
Moxifloxacin Injection
| * 400 mg moxifloxacin equivalent to 437.5 mg of moxifloxacin hydrochloride. | ||
| **The pH may have been adjusted with sulfuric acid. The pH is 5.0 to 6.0. | ||
| Component | Function | Dosage Formulation |
| Moxifloxacin* | Active ingredient | 400 mg* |
| Sodium acetate (added as a trihydrate) | Tonicity adjuster | 1,702.5 mg |
| Disodium sulfate | Tonicity adjuster | 2,840 mg |
| Sulfuric acid ** | pH adjustment | As needed |
| Water for injection | vehicle | q.s. 250 mL |
Each mL contains 1.6 mg of moxifloxacin.
The appearance of the intravenous solution is clear. The flexible bag is fabricated from a specially designed multilayer plastic (freeflex®). Solution is in contact with the polypropylene layer of this container and can leach out certain chemical components of the plastic in very small amounts within the expiration period. The leachable compounds were all within acceptable limits based on animal toxicology studies.
Moxifloxacin Injection contains approximately 52.5 mEq (1,207 mg) of sodium in 250 mL.
12 CLINICAL PHARMACOLOGY
12.1 Mechanism of Action
Moxifloxacin is a member of the fluoroquinolone class of antibacterial agents [see Microbiology (12.4)].
12.3 Pharmacokinetics
The mean (± SD) pharmacokinetic parameters of moxifloxacin following single and multiple dose of 400 mg moxifloxacin given by 1 hour intravenous infusion are summarized in Table 7. The mean (± SD) elimination half-life from plasma is 12 ± 1.3 hours; steady-state is achieved after at least three days with a 400 mg once daily regimen. The absolute bioavailability of moxifloxacin is approximately 90 percent. When switching from intravenous to oral formulation, no dosage adjustment is necessary [see Dosage and Administration (2.1)].
Table 7: Mean (± SD) Cmax and AUC Values Following Single and Multiple Doses of 400 mg Moxifloxacin Given by 1 Hour Intravenous Infusion
| a Range of means from different studies | |||
| b Expected Cmax (concentration obtained around the time of the end of the infusion) | |||
Cmax (mg/L) | AUC (mg•h/L) | Half-life (hr) | |
| Single Dose IV | |||
| Healthy young male/female (n = 56) | 3.9 ± 0.9 | 39.3 ± 8.6 | 8.2 to 15.4a |
| Patients (n = 118) | |||
| Male (n = 64) | 4.4 ± 3.7 | ||
| Female (n = 54) | 4.5 ± 2 | ||
| < 65 years (n = 58) | 4.6 ± 4.2 | ||
| ≥ 65 years (n = 60) | 4.3 ± 1.3 | ||
| Multiple Dose IV | |||
Healthy young male (n = 8) Healthy elderly (n =12; 8 male, 4 female) | 4.2 ± 0.8 6.1 ± 1.3 | 38 ± 4.7 48.2 ± 0.9 | 14.8 ± 2.2 10.1 ± 1.6 |
| Patientsb (n = 107) | |||
| Male (n = 58) | 4.2 ± 2.6 | ||
| Female (n = 49) | 4.6 ± 1.5 | ||
| < 65 years (n = 52) | 4.1 ± 1.4 | ||
| ≥ 65 years (n = 55) | 4.7 ± 2.7 | ||
Distribution
Moxifloxacin is approximately 30 to 50% bound to serum proteins, independent of drug concentration. The volume of distribution of moxifloxacin ranges from 1.7 to 2.7 L/kg. Moxifloxacin is widely distributed throughout the body, with tissue concentrations often exceeding plasma concentrations. Moxifloxacin has been detected in the saliva, nasal and bronchial secretions, mucosa of the sinuses, skin blister fluid, subcutaneous tissue, skeletal muscle, and abdominal tissues and fluids following oral or intravenous administration of 400 mg. Moxifloxacin concentrations measured post-dose in various tissues and fluids following a 400 mg oral or intravenous dose are summarized in Table 8. The rates of elimination of moxifloxacin from tissues generally parallel the elimination from plasma.
Table 8: Moxifloxacin Concentrations (mean ± SD) in Tissues and the Corresponding Plasma Concentrations After a Single 400 mg Oral or Intravenous Dosea
| a All moxifloxacin concentrations were measured 3 hours after a single 400 mg dose, except the abdominal tissue and exudate concentrations which were measured at 2 hours post-dose and the sinus concentrations which were measured 3 hours post-dose after 5 days of dosing. | ||||
| b N = 5 | ||||
| c N = 7 | ||||
| d N = 12 | ||||
| e Reflects only non-protein bound concentrations of drug. | ||||
| Tissue or Fluid | N | Plasma Concentration (mcg/mL) | Tissue or Fluid Concentration (mcg/mL or mcg/g) | Tissue Plasma Ratio |
| Respiratory | ||||
| Alveolar Macrophages | 5 | 3.3 ± 0.7 | 61.8 ± 27.3 | 21.2 ± 10 |
| Bronchial Mucosa | 8 | 3.3 ± 0.7 | 5.5 ± 1.3 | 1.7 ± 0.3 |
| Epithelial Lining Fluid | 5 | 3.3 ± 0.7 | 24.4 ± 14.7 | 8.7 ± 6.1 |
| Sinus | ||||
| Maxillary Sinus Mucosa | 4 | 3.7 ± 1.1b | 7.6 ± 1.7 | 2 ± 0.3 |
| Anterior Ethmoid Mucosa | 3 | 3.7 ± 1.1b | 8.8 ± 4.3 | 2.2 ± 0.6 |
| Nasal Polyps | 4 | 3.7 ± 1.1b | 9.8 ± 4.5 | 2.6 ± 0.6 |
| Skin, Musculoskeletal | ||||
| Blister Fluid | 5 | 3 ± 0.5c | 2.6 ± 0.9 | 0.9 ± 0.2 |
| Subcutaneous Tissue | 6 | 2.3 ± 0.4d | 0.9 ± 0.3e | 0.4 ± 0.6 |
| Skeletal Muscle | 6 | 2.3 ± 0.4d | 0.9 ± 0.2e | 0.4 ± 0.1 |
| Intra-Abdominal | ||||
| Abdominal tissue | 8 | 2.9 ± 0.5 | 7.6 ± 2 | 2.7 ± 0.8 |
| Abdominal exudate | 10 | 2.3 ± 0.5 | 3.5 ± 1.2 | 1.6 ± 0.7 |
| Abscess fluid | 6 | 2.7 ± 0.7 | 2.3 ± 1.5 | 0.8 ± 0.4 |
Metabolism
Approximately 52% of an oral or intravenous dose of moxifloxacin is metabolized via glucuronide and sulfate conjugation. The cytochrome P450 system is not involved in moxifloxacin metabolism and is not affected by moxifloxacin. The sulfate conjugate (M1) accounts for approximately 38% of the dose and is eliminated primarily in the feces. Approximately 14% of an oral or intravenous dose is converted to a glucuronide conjugate (M2), which is excreted exclusively in the urine. Peak plasma concentrations of M2 are approximately 40% those of the parent drug, while plasma concentrations of M1 are generally less than 10% those of moxifloxacin.
In vitro studies with cytochrome (CYP) P450 enzymes indicate that moxifloxacin does not inhibit CYP3A4, CYP2D6, CYP2C9, CYP2C19, or CYP1A2, suggesting that moxifloxacin is unlikely to alter the pharmacokinetics of drugs metabolized by these enzymes.
Excretion
Approximately 45% of an oral or intravenous dose of moxifloxacin is excreted as unchanged drug (~20% in urine and ~25% in feces). A total of 96% ± 4% of an oral dose is excreted as either unchanged drug or known metabolites. The mean (± SD) apparent total body clearance and renal clearance are 12 ± 2 L/hr and 2.6 ± 0.5 L/hr, respectively.
Pharmacokinetics in Specific Populations
Geriatric
Following oral administration of 400 mg moxifloxacin for 10 days in 16 elderly (8 male; 8 female) and 17 young (8 male; 9 female) healthy volunteers, there were no age-related changes in moxifloxacin pharmacokinetics. In 16 healthy male volunteers (8 young; 8 elderly) given a single 200 mg dose of oral moxifloxacin, the extent of systemic exposure (AUC and Cmax) was not statistically different between young and elderly males and elimination half-life was unchanged. No dosage adjustment is necessary based on age.
In large phase III studies, the concentrations around the time of the end of the infusion in elderly patients following intravenous infusion of 400 mg were similar to those observed in young patients [see Use in Specific Populations (8.5)].
Pediatric
The pharmacokinetics of moxifloxacin in pediatric subjects has not been studied [see Use in Specific Populations (8.4)].
Gender
Following oral administration of 400 mg moxifloxacin daily for 10 days to 23 healthy males (19 to 75 years) and 24 healthy females (19 to 70 years), the mean AUC and Cmax were 8% and 16% higher, respectively, in females compared to males. There are no significant differences in moxifloxacin pharmacokinetics between male and female subjects when differences in body weight are taken into consideration.
A 400 mg single dose study was conducted in 18 young males and females. The comparison of moxifloxacin pharmacokinetics in this study (9 young females and 9 young males) showed no differences in AUC or Cmax due to gender. Dosage adjustments based on gender are not necessary.
Race
Steady-state moxifloxacin pharmacokinetics in male Japanese subjects were similar to those determined in Caucasians, with a mean Cmax of 4.1 mcg/mL, an AUC24 of 47 mcg•h/mL, and an elimination half-life of 14 hours, following 400 mg p.o. daily.
Renal Insufficiency
The pharmacokinetic parameters of moxifloxacin are not significantly altered in mild, moderate, severe, or end-stage renal disease. No dosage adjustment is necessary in patients with renal impairment, including those patients requiring hemodialysis (HD) or continuous ambulatory peritoneal dialysis (CAPD).
In a single oral dose study of 24 patients with varying degrees of renal function from normal to severely impaired, the mean peak concentrations (Cmax) of moxifloxacin were reduced by 21% and 28% in the patients with moderate (CLCR ≥ 30 and ≤ 60 mL/min) and severe (CLCR < 30 mL/min) renal impairment, respectively. The mean systemic exposure (AUC) in these patients was increased by 13%. In the moderate and severe renally impaired patients, the mean AUC for the sulfate conjugate (M1) increased by 1.7-fold (ranging up to 2.8-fold) and mean AUC and Cmax for the glucuronide conjugate (M2) increased by 2.8-fold (ranging up to 4.8-fold) and 1.4-fold (ranging up to 2.5-fold), respectively [see Use in Specific Populations (8.6)].
The pharmacokinetics of single dose and multiple dose moxifloxacin were studied in patients with CLCR < 20 mL/min on either hemodialysis or continuous ambulatory peritoneal dialysis (8 HD, 8 CAPD). Following a single 400 mg oral dose, the AUC of moxifloxacin in these HD and CAPD patients did not vary significantly from the AUC generally found in healthy volunteers. Cmax values of moxifloxacin were reduced by about 45% and 33% in HD and CAPD patients, respectively, compared to healthy, historical controls. The exposure (AUC) to the sulfate conjugate (M1) increased by 1.4- to 1.5-fold in these patients. The mean AUC of the glucuronide conjugate (M2) increased by a factor of 7.5, whereas the mean Cmax values of the glucuronide conjugate (M2) increased by a factor of 2.5 to 3, compared to healthy subjects. The sulfate and the glucuronide conjugates of moxifloxacin are not microbiologically active, and the clinical implication of increased exposure to these metabolites in patients with renal disease including those undergoing HD and CAPD has not been studied.
Oral administration of 400 mg QD moxifloxacin for 7 days to patients on HD or CAPD produced mean systemic exposure (AUCss) to moxifloxacin similar to that generally seen in healthy volunteers. Steady-state Cmax values were about 22% lower in HD patients but were comparable between CAPD patients and healthy volunteers. Both HD and CAPD removed only small amounts of moxifloxacin from the body (approximately 9% by HD, and 3% by CAPD). HD and CAPD also removed about 4% and 2% of the glucuronide metabolite (M2), respectively.
Hepatic Insufficiency
No dosage adjustment is recommended for mild, moderate, or severe hepatic insufficiency (Child-Pugh Classes A, B, or C). However, due to metabolic disturbances associated with hepatic insufficiency, which may lead to QT prolongation, moxifloxacin should be used with caution in these patients [see Warnings and Precautions (5.6) and Use in Specific Populations (8.7)].
In 400 mg single oral dose studies in 6 patients with mild (Child-Pugh Class A) and 10 patients with moderate (Child-Pugh Class B) hepatic insufficiency, moxifloxacin mean systemic exposure (AUC) was 78% and 102%, respectively, of 18 healthy controls and mean peak concentration (Cmax) was 79% and 84% of controls.
The mean AUC of the sulfate conjugate of moxifloxacin (M1) increased by 3.9-fold (ranging up to 5.9-fold) and 5.7-fold (ranging up to 8-fold) in the mild and moderate groups, respectively. The mean Cmax of M1 increased by approximately 3-fold in both groups (ranging up to 4.7- and 3.9-fold). The mean AUC of the glucuronide conjugate of moxifloxacin (M2) increased by 1.5-fold (ranging up to 2.5-fold) in both groups. The mean Cmax of M2 increased by 1.6- and 1.3-fold (ranging up to 2.7- and 2.1-fold), respectively. The clinical significance of increased exposure to the sulfate and glucuronide conjugates has not been studied. In a subset of patients participating in a clinical trial, the plasma concentrations of moxifloxacin and metabolites determined approximately at the moxifloxacin Tmax following the first intravenous or oral moxifloxacin dose in the Child-Pugh Class C patients (n = 10) were similar to those in the Child-Pugh Class A/B patients (n = 5), and also similar to those observed in healthy volunteer studies.
Photosensitivity Potential
A study of the skin response to ultraviolet (UVA and UVB) and visible radiation conducted in 32 healthy volunteers (8 per group) demonstrated that moxifloxacin does not show phototoxicity in comparison to placebo. The minimum erythematous dose (MED) was measured before and after treatment with moxifloxacin (200 mg or 400 mg once daily), lomefloxacin (400 mg once daily), or placebo. In this study, the MED measured for both doses of moxifloxacin were not significantly different from placebo, while lomefloxacin significantly lowered the MED.
It is difficult to ascribe relative photosensitivity/phototoxicity among various fluoroquinolones during actual patient use because other factors play a role in determining a subject's susceptibility to this adverse event such as: a patient's skin pigmentation, frequency and duration of sun and artificial ultraviolet light (UV) exposure, wearing of sunscreen and protective clothing, the use of other concomitant drugs and the dosage and duration of fluoroquinolone therapy [see Warnings and Precautions (5.14), Adverse Reactions (6.1), and Patient Counseling Information (17)].
Drug-Drug Interactions
The following drug interactions were studied in healthy volunteers or patients.
Digoxin, itraconazole, morphine, probenecid, ranitidine, theophylline and warfarin did not significantly affect the pharmacokinetics of moxifloxacin. These results and the data from in vitro studies suggest that moxifloxacin is unlikely to significantly alter the metabolic clearance of drugs metabolized by CYP3A4, CYP2D6, CYP2C9, CYP2C19, or CYP1A2 enzymes.
Moxifloxacin had no clinically significant effect on the pharmacokinetics of atenolol, digoxin, glyburide, itraconazole, oral contraceptives, theophylline, cyclosporine and warfarin [see Drug Interactions (7.1)].
Atenolol
In a crossover study involving 24 healthy volunteers (12 male; 12 female), the mean atenolol AUC following a single oral dose of 50 mg atenolol with placebo was similar to that observed when atenolol was given concomitantly with a single 400 mg oral dose of moxifloxacin. The mean Cmax of single dose atenolol decreased by about 10% following co-administration with a single dose of moxifloxacin.
Digoxin
No significant effect of moxifloxacin (400 mg once daily for two days) on digoxin (0.6 mg as a single dose) AUC was detected in a study involving 12 healthy volunteers. The mean digoxin Cmax increased by about 50% during the distribution phase of digoxin. This transient increase in digoxin Cmax is not viewed to be clinically significant.
Moxifloxacin pharmacokinetics were similar in the presence or absence of digoxin. No dosage adjustment for moxifloxacin or digoxin is required when these drugs are administered concomitantly.
Glyburide
In diabetics, glyburide (2.5 mg once daily for two weeks pretreatment and for five days concurrently) mean AUC and Cmax were 12% and 21% lower, respectively, when taken with moxifloxacin (400 mg once daily for five days) in comparison to placebo.
Nonetheless, blood glucose levels were decreased slightly in patients taking glyburide and moxifloxacin in comparison to those taking glyburide alone, suggesting no interference by moxifloxacin on the activity of glyburide. These interaction results are not viewed as clinically significant.
Itraconazole
In a study involving 11 healthy volunteers, there was no significant effect of itraconazole (200 mg once daily for 9 days), a potent inhibitor of cytochrome P4503A4, on the pharmacokinetics of moxifloxacin (a single 400 mg dose given on the 7th day of itraconazole dosing). In addition, moxifloxacin was shown not to affect the pharmacokinetics of itraconazole.
Morphine
No significant effect of morphine sulfate (a single 10 mg intramuscular dose) on the mean AUC and Cmax of moxifloxacin (400 mg single dose) was observed in a study of 20 healthy male and female volunteers.
Oral Contraceptives
A placebo-controlled study in 29 healthy female subjects showed that moxifloxacin 400 mg daily for 7 days did not interfere with the hormonal suppression of oral contraception with 0.15 mg levonorgestrel/0.03 mg ethinylestradiol (as measured by serum progesterone, FSH, estradiol, and LH), or with the pharmacokinetics of the administered contraceptive agents.
Probenecid
Probenecid (500 mg twice daily for two days) did not alter the renal clearance and total amount of moxifloxacin (400 mg single dose) excreted renally in a study of 12 healthy volunteers.
Ranitidine
No significant effect of ranitidine (150 mg twice daily for three days as pretreatment) on the pharmacokinetics of moxifloxacin (400 mg single dose) was detected in a study involving 10 healthy volunteers.
Theophylline
No significant effect of moxifloxacin (200 mg every twelve hours for 3 days) on the pharmacokinetics of theophylline (400 mg every twelve hours for 3 days) was detected in a study involving 12 healthy volunteers. In addition, theophylline was not shown to affect the pharmacokinetics of moxifloxacin. The effect of co-administration of a 400 mg dose of moxifloxacin with theophylline has not been studied, but it is not expected to be clinically significant based on in vitro metabolic data showing that moxifloxacin does not inhibit the CYP1A2 isoenzyme.
Warfarin
No significant effect of moxifloxacin (400 mg once daily for eight days) on the pharmacokinetics of R- and S-warfarin (25 mg single dose of warfarin sodium on the fifth day) was detected in a study involving 24 healthy volunteers. No significant change in prothrombin time was observed [see Adverse Reactions (6.1) and Drug Interactions (7.1)].
12.4 Microbiology
Mechanism of Action
The bactericidal action of moxifloxacin results from inhibition of the topoisomerase II (DNA gyrase) and topoisomerase IV required for bacterial DNA replication, transcription, repair, and recombination.
Resistance
The mechanism of action for fluoroquinolones, including moxifloxacin, is different from that of macrolides, beta-lactams, aminoglycosides, or tetracyclines; therefore, microorganisms resistant to these classes of drugs may be susceptible to moxifloxacin.
Resistance to fluoroquinolones occurs primarily by a mutation in topoisomerase II (DNA gyrase) or topoisomerase IV genes, decreased outer membrane permeability or drug efflux. In vitro resistance to moxifloxacin develops slowly via multiple-step mutations. Resistance to moxifloxacin occurs in vitro at a general frequency of between 1.8 x 10⁻⁹ to < 1 x 10-11 for Gram-positive bacteria.
Cross-Resistance
Cross-resistance has been observed between moxifloxacin and other fluoroquinolones against Gram-negative bacteria. Gram-positive bacteria resistant to other fluoroquinolones may, however, still be susceptible to moxifloxacin. There is no known cross-resistance between moxifloxacin and other classes of antimicrobials.
Antimicrobial Activity
Moxifloxacin has been shown to be active against most isolates of the following bacteria, both in vitro and in clinical infections [see Indications and Usage (1)].
Gram-positive bacteria
Enterococcus faecalis
Staphylococcus aureus
Streptococcus anginosus
Streptococcus constellatus
Streptococcus pneumoniae (including multi-drug resistant isolates [MDRSP]**)
Streptococcus pyogenes
**MDRSP, Multi-drug resistant Streptococcus pneumoniae includes isolates previously known as PRSP (Penicillin-resistant S. pneumoniae), and are isolates resistant to two or more of the following antibacterial drugs: penicillin (MIC) ≥ 2 mcg/mL), 2nd generation cephalosporins (for example, cefuroxime), macrolides, tetracyclines, and trimethoprim/sulfamethoxazole.
Gram-negative bacteria
Enterobacter cloacae
Escherichia coli
Haemophilus influenzae
Haemophilus parainfluenzae
Klebsiella pneumoniae
Moraxella catarrhalis
Proteus mirabilis
Anaerobic bacteria
Bacteroides fragilis
Bacteroides thetaiotaomicron
Clostridium perfringens
Peptostreptococcus species
Other microorganisms
Chlamydophila pneumoniae
Mycoplasma pneumoniae
The following in vitro data are available, but their clinical significance is unknown. At least 90 percent of the following bacteria exhibit an in vitro minimum inhibitory concentration (MIC) less than or equal to the susceptible breakpoint for moxifloxacin against isolates of similar genus or organism group. However, the efficacy of moxifloxacin in treating clinical infections due to these bacteria has not been established in adequate and well controlled clinical trials.
Gram-positive bacteria
Staphylococcus epidermidis
Streptococcus agalactiae
Streptococcus viridans group
Gram-negative bacteria
Citrobacter freundii
Klebsiella oxytoca
Legionella pneumophila
Anaerobic bacteria
Fusobacterium species
Prevotella species
Susceptibility Tests Methods
For specific information regarding susceptibility test interpretive criteria and associated test methods and quality control standards recognized by FDA for this drug, please see: https://www.fda.gov/STIC.
13 NONCLINICAL TOXICOLOGY
13.1 Carcinogenesis, Mutagenesis, Impairment of Fertility
Long term studies in animals to determine the carcinogenic potential of moxifloxacin have not been performed.
Moxifloxacin was not mutagenic in 4 bacterial strains (TA 98, TA 100, TA 1535, TA 1537) used in the Ames Salmonella reversion assay. As with other quinolones, the positive response observed with moxifloxacin in strain TA 102 using the same assay may be due to the inhibition of DNA gyrase. Moxifloxacin was not mutagenic in the CHO/HGPRT mammalian cell gene mutation assay. An equivocal result was obtained in the same assay when v79 cells were used. Moxifloxacin was clastogenic in the v79 chromosome aberration assay, but it did not induce unscheduled DNA synthesis in cultured rat hepatocytes. There was no evidence of genotoxicity in vivo in a micronucleus test or a dominant lethal test in mice.
Moxifloxacin had no effect on fertility in male and female rats at oral doses as high as 500 mg/kg/day, (approximately 12 times the maximum recommended human dose based on body surface area), or at intravenous doses as high as 45 mg/kg/day, (approximately equal to the maximum recommended human dose based on body surface area). At 500 mg/kg orally there were slight effects on sperm morphology (head-tail separation) in male rats and on the estrous cycle in female rats.
13.2 Animal Toxicology and/or Pharmacology
Quinolones have been shown to cause arthropathy in immature animals. In studies in juvenile dogs oral doses of moxifloxacin ≥ 30 mg/kg/day (approximately 1.5 times the maximum recommended human dose based upon systemic exposure) for 28 days resulted in arthropathy. There was no evidence of arthropathy in mature monkeys and rats at oral doses up to 135 and 500 mg/kg/day, respectively.
Moxifloxacin at an oral dose of 300 mg/kg did not show an increase in acute toxicity or potential for CNS toxicity (for example, seizures) in mice when used in combination with NSAIDs such as diclofenac, ibuprofen, or fenbufen. Some quinolones have been reported to have proconvulsant activity that is exacerbated with concomitant use of non- steroidal anti-inflammatory drugs (NSAIDs).
A QT-prolonging effect of moxifloxacin was found in dog studies, at plasma concentrations about five times the human therapeutic level. The combined infusion of sotalol, a Class III antiarrhythmic agent, with moxifloxacin induced a higher degree of QTc prolongation in dogs than that induced by the same dose (30 mg/kg) of moxifloxacin alone. Electrophysiological in vitro studies suggested an inhibition of the rapid activating component of the delayed rectifier potassium current (IKr) as an underlying mechanism.
No signs of local intolerability were observed in dogs when moxifloxacin was administered intravenously. After intra-arterial injection, inflammatory changes involving the peri-arterial soft tissue were observed suggesting that intra-arterial administration of moxifloxacin should be avoided.
14 CLINICAL STUDIES
14.1 Acute Bacterial Exacerbation of Chronic Bronchitis
Moxifloxacin tablets (400 mg once daily for five days) were evaluated for the treatment of acute bacterial exacerbation of chronic bronchitis in a randomized, double-blind, controlled clinical trial conducted in the US. This study compared moxifloxacin with clarithromycin (500 mg twice daily for 10 days) and enrolled 629 patients. Clinical success was assessed at 7 to 17 days post-therapy. The clinical success for moxifloxacin was 89% (222/250) compared to 89% (224/251) for clarithromycin.
Table 9: Clinical Success Rates at Follow-Up Visit for Clinically Evaluable Patients by Pathogen (Acute Bacterial Exacerbation of Chronic Bronchitis)
| Pathogen | Moxifloxacin | Clarithromycin |
| Streptococcus pneumoniae | 16/16 (100%) | 20/23 (87%) |
| Haemophilus influenzae | 33/37 (89%) | 36/41 (88%) |
| Haemophilus parainfluenzae | 16/16 (100%) | 14/14 (100%) |
| Moraxella catarrhalis | 29/34 (85%) | 24/24 (100%) |
| Staphylococcus aureus | 15/16 (94%) | 6/8 (75%) |
| Klebsiella pneumoniae | 18/20 (90%) | 10/11 (91%) |
The microbiological eradication rates (eradication plus presumed eradication) in moxifloxacin-treated patients were Streptococcus pneumoniae 100%, Haemophilus influenzae 89%, Haemophilus parainfluenzae 100%, Moraxella catarrhalis 85%, Staphylococcus aureus 94%, and Klebsiella pneumoniae 85%.
14.2 Community Acquired Pneumonia
A randomized, double-blind, controlled clinical trial was conducted in the US to compare the efficacy of moxifloxacin tablets (400 mg once daily) to that of high-dose clarithromycin (500 mg twice daily) in the treatment of patients with clinically and radiologically documented community acquired pneumonia. This study enrolled 474 patients (382 of whom were valid for the efficacy analysis conducted at the 14 to 35 day follow-up visit). Clinical success for clinically evaluable patients was 95% (184/194) for moxifloxacin and 95% (178/188) for high dose clarithromycin.
A randomized, double-blind, controlled trial was conducted in the US and Canada to compare the efficacy of sequential IV/PO moxifloxacin 400 mg QD for 7 to 14 days to an IV/PO fluoroquinolone control (trovafloxacin or levofloxacin) in the treatment of patients with clinically and radiologically documented community acquired pneumonia. This study enrolled 516 patients, 362 of whom were valid for the efficacy analysis conducted at the 7 to 30 day post-therapy visit. The clinical success rate was 86% (157/182) for moxifloxacin therapy and 89% (161/180) for the fluoroquinolone comparators.
An open-label ex-US study that enrolled 628 patients compared moxifloxacin to sequential IV/PO amoxicillin/clavulanate (1.2 g IV q8h/625 mg PO q8h) with or without high-dose IV/PO clarithromycin (500 mg BID). The intravenous formulations of the comparators are not FDA approved. The clinical success rate at Day 5 to 7 for moxifloxacin therapy was 93% (241/258) and demonstrated superiority to amoxicillin/clavulanate ± clarithromycin (85%, 239/280) [95% C.I. of difference in success rates between moxifloxacin and comparator (2.9%, 13.2%)]. The clinical success rate at the 21 to 28 days post-therapy visit for moxifloxacin was 84% (216/258), which also demonstrated superiority to the comparators (74%, 208/280) [95% C.I. of difference in success rates between moxifloxacin and comparator (2.6%, 16.3%)].
The clinical success rates by pathogen across four CAP studies are presented in Table 10.
Table 10: Clinical Success Rates by Pathogen (Pooled CAP Studies)
| Pathogen | Moxifloxacin | |
| Streptococcus pneumoniae | 80/85 | (94%) |
| Staphylococcus aureus | 17/20 | (85%) |
| Klebsiella pneumoniae | 11/12 | (92%) |
| Haemophilus influenzae | 56/61 | (92%) |
| Chlamydophila pneumoniae | 119/128 | (93%) |
| Mycoplasma pneumoniae | 73/76 | (96%) |
| Moraxella catarrhalis | 11/12 | (92%) |
14.3 Community Acquired Pneumonia Caused by Multi-Drug Resistant Streptococcus pneumoniae (MDRSP)*
Moxifloxacin was effective in the treatment of community acquired pneumonia (CAP) caused by multi-drug resistant MDRSP* isolates. Of 37 microbiologically evaluable patients with MDRSP isolates, 35 patients (95%) achieved clinical and bacteriological success post-therapy. The clinical and bacteriological success rates based on the number of patients treated are shown in Table 11.
* MDRSP, Multi-drug resistant Streptococcus pneumoniae includes isolates previously known as PRSP (Penicillin-resistant S. pneumoniae), and are isolates resistant to two or more of the following antibiotics: penicillin (MIC ≥ 2 mcg/mL), 2nd generation cephalosporins (for example, cefuroxime), macrolides, tetracyclines, and trimethoprim/sulfamethoxazole.
Table 11: Clinical and Bacteriological Success Rates for Moxifloxacin-Treated MDRSP CAP Patients (Population: Valid for Efficacy)
| a n = number of patients successfully treated; N = number of patients with MDRSP (from a total of 37 patients) | ||||
| b n = number of patients successfully treated (presumed eradication or eradication); N = number of patients with MDRSP (from a total of 37 patients) | ||||
| c One patient had a respiratory isolate that was resistant to penicillin and cefuroxime but a blood isolate that was intermediate to penicillin and cefuroxime. The patient is included in the database based on the respiratory isolate. | ||||
| d Azithromycin, clarithromycin, and erythromycin were the macrolide antimicrobials tested. | ||||
| Screening Susceptibility | Clinical Success | Bacteriological Success | ||
| n/Na | % | n/Nb | % | |
| Penicillin-resistant | 21/21 | 100%c | 21/21 | 100%c |
| 2nd generation cephalosporin-resistant | 25/26 | 96%c | 25/26 | 96%c |
| Macrolide-resistantd | 22/23 | 96% | 22/23 | 96% |
| Trimethoprim/sulfamethoxazole-resistant | 28/30 | 93% | 28/30 | 93% |
| Tetracycline-resistant | 17/18 | 94% | 17/18 | 94% |
Not all isolates were resistant to all antimicrobial classes tested. Success and eradication rates are summarized in Table 12.
Table 12: Clinical Success Rates and Microbiological Eradication Rates for Resistant Streptococcus pneumoniae (Community Acquired Pneumonia)
| a One patient had a respiratory isolate resistant to 5 antimicrobials and a blood isolate resistant to 3 antimicrobials. The patient was included in the category resistant to 5 antimicrobials. | ||
| S. pneumoniae with MDRSP | Clinical Success | Bacteriological Eradication Rate |
| Resistant to 2 antimicrobials | 12/13 (92.3%) | 12/13 (92.3%) |
| Resistant to 3 antimicrobials | 10/11 (90.9%)a | 10/11 (90.9%)a |
| Resistant to 4 antimicrobials | 6/6 (100%) | 6/6 (100%) |
| Resistant to 5 antimicrobials | 7/7 (100%)a | 7/7 (100%)a |
| Bacteremia with MDRSP | 9/9 (100%) | 9/9 (100%) |
14.4 Acute Bacterial Sinusitis
In a controlled double-blind study conducted in the US, moxifloxacin tablets (400 mg once daily for ten days) were compared with cefuroxime axetil (250 mg twice daily for ten days) for the treatment of acute bacterial sinusitis. The trial included 457 patients valid for the efficacy analysis. Clinical success (cure plus improvement) at the 7 to 21 day post-therapy test of cure visit was 90% for moxifloxacin and 89% for cefuroxime.
An additional non-comparative study was conducted to gather bacteriological data and to evaluate microbiological eradication in adult patients treated with moxifloxacin 400 mg once daily for seven days. All patients (n = 336) underwent antral puncture in this study. Clinical success rates and eradication/presumed eradication rates at the 21 to 37 day follow-up visit were 97% (29 out of 30) for Streptococcus pneumoniae, 83% (15 out of 18) for Moraxella catarrhalis, and 80% (24 out of 30) for Haemophilus influenzae.
14.5 Uncomplicated Skin and Skin Structure Infections
A randomized, double-blind, controlled clinical trial conducted in the US compared the efficacy of moxifloxacin 400 mg once daily for seven days with cephalexin HCl 500 mg three times daily for seven days. The percentage of patients treated for uncomplicated abscesses was 30%, furuncles 8%, cellulitis 16%, impetigo 20%, and other skin infections 26%. Adjunctive procedures (incision and drainage or debridement) were performed on 17% of the moxifloxacin-treated patients and 14% of the comparator treated patients. Clinical success rates in evaluable patients were 89% (108/122) for moxifloxacin and 91% (110/121) for cephalexin HCl.
14.6 Complicated Skin and Skin Structure Infections
Two randomized, active controlled trials of cSSSI were performed. A double-blind trial was conducted primarily in North America to compare the efficacy of sequential IV/PO moxifloxacin 400 mg QD for 7 to 14 days to an IV/PO beta-lactam/beta-lactamase inhibitor control in the treatment of patients with cSSSI. This study enrolled 617 patients, 335 of which were valid for the efficacy analysis. A second open-label International study compared moxifloxacin 400 mg QD for 7 to 21 days to sequential IV/PO beta-lactam/beta-lactamase inhibitor control in the treatment of patients with cSSSI. This study enrolled 804 patients, 632 of which were valid for the efficacy analysis. Surgical incision and drainage or debridement was performed on 55% of the moxifloxacin-treated and 53% of the comparator treated patients in these studies and formed an integral part of therapy for this indication. Success rates varied with the type of diagnosis ranging from 61% in patients with infected ulcers to 90% in patients with complicated erysipelas. These rates were similar to those seen with comparator drugs. The overall success rates in the evaluable patients and the clinical success by pathogen are shown in Tables 13 and 14.
Table 13: Overall Clinical Success Rates in Patients with Complicated Skin and Skin Structure Infections
| * of difference in success rates between moxifloxacin and comparator (moxifloxacin - comparator) | |||
| Study | Moxifloxacin n/N (%) | Comparator n/N (%) | 95% Confidence Interval* |
| North America | 125/162 (77.2%) | 141/173 (81.5%) | (-14.4%, 2%) |
| International | 254/315 (80.6%) | 268/317 (84.5%) | (-9.4%, 2.2%) |
Table 14: Clinical Success Rates by Pathogen in Patients with Complicated Skin and Skin Structure Infections
| a methicillin susceptibility was only determined in the North American Study | ||
| Pathogen | Moxifloxacin n/N (%) | Comparator n/N (%) |
Staphylococcus aureus (methicillin-susceptible isolates)a | 106/129 (82.2%) | 120/137 (87.6%) |
| Escherichia coli | 31/38 (81.6%) | 28/33 (84.8%) |
| Klebsiella pneumoniae | 11/12 (91.7%) | 7/10 (70%) |
| Enterobacter cloacae | 9/11 (81.8%) | 4/7 (57.1%) |
14.7 Complicated Intra-Abdominal Infections
Two randomized, active controlled trials of cIAI were performed. A double-blind trial was conducted primarily in North America to compare the efficacy of sequential IV/PO moxifloxacin 400 mg QD for 5 to 14 days to IV/piperacillin/tazobactam followed by PO amoxicillin/clavulanic acid in the treatment of patients with cIAI, including peritonitis, abscesses, appendicitis with perforation, and bowel perforation. This study enrolled 681 patients, 379 of which were considered clinically evaluable. A second open-label international study compared moxifloxacin 400 mg QD for 5 to 14 days to IV ceftriaxone plus IV metronidazole followed by PO amoxicillin/clavulanic acid in the treatment of patients with cIAI. This study enrolled 595 patients, 511 of which were considered clinically evaluable. The clinically evaluable population consisted of subjects with a surgically confirmed complicated infection, at least 5 days of treatment and a 25 to 50 day follow-up assessment for patients at the Test of Cure visit. The overall clinical success rates in the clinically evaluable patients are shown in Table 15.
Table 15: Clinical Success Rates in Patients with Complicated Intra-Abdominal Infections
| a of difference in success rates between moxifloxacin and comparator (moxifloxacin – comparator) | |||
| b Excludes 2 patients who required additional surgery within the first 48 hours. | |||
| c NA – not applicable | |||
| Study | Moxifloxacin n/N (%) | Comparator n/N (%) | 95% Confidence Interval a |
| North America (overall) | 146/183 (79.8%) | 153/196 (78.1%) | (-7.4%, 9.3%) |
| Abscess | 40/57 (70.2%) | 49/63 (77.8%)b | NAc |
| Non-abscess | 106/126 (84.1%) | 104/133 (78.2%) | NA |
| International (overall) | 199/246 (80.9%) | 218/265 (82.3%) | (-8.9%, 4.2%) |
| Abscess | 73/93 (78.5%) | 86/99 (86.9%) | NA |
| Non-abscess | 126/153 (82.4%) | 132/166 (79.5%) | NA |
16 HOW SUPPLIED/STORAGE AND HANDLING
How Supplied
Moxifloxacin Injection 400 mg/250 mL is a sterile solution available in a single-dose, ready-to-use flexible bag.
No further dilution is necessary.
Product Code | Unit of Sale | Strength | Unit of Use |
| 850174 | NDC 63323-850-74 Package of 12 freeflex® bags | 400 mg per 250 mL (1.6 mg per mL) | NDC 63323-850-04 250 mL fill in a 300 mL free flex® Bag |
Parenteral drug products should be inspected visually for particulate matter prior to administration. Samples containing visible particulates should not be used.
Storage and Handling
Store at 20°C to 25°C (68°F to 77°F) [see USP Controlled Room Temperature].
Do not refrigerate - Product precipitates upon refrigeration.
Retain in overwrap to protect from light. Use immediately once removed from the overwrap.
The container closure is not made with natural rubber latex. Non-PVC, Non-DEHP. Sterile.
17 PATIENT COUNSELING INFORMATION
Advise patients to read the FDA-approved patient labeling (Medication Guide).
Serious Adverse Reactions
Advise patients to stop taking moxifloxacin if they experience an adverse reaction and to call their healthcare provider for advice on completing the full course of treatment with another antibacterial drug.
Inform patients of the following serious adverse reactions that have been associated with moxifloxacin or other fluoroquinolone use:
- Disabling and potentially irreversible serious adverse reactions that may occur together: Inform patients that disabling and potentially irreversible serious adverse reactions, including tendinitis and tendon rupture, peripheral neuropathies, and central nervous system effects, have been associated with use of moxifloxacin and may occur together in the same patient. Inform patients to stop taking moxifloxacin immediately if they experience an adverse reaction and to call their healthcare provider.
- Tendinitis and Tendon Rupture: Instruct patients to contact their healthcare provider if they experience pain, swelling, or inflammation of a tendon, or weakness or inability to use one of their joints; rest and refrain from exercise; and discontinue moxifloxacin treatment. Symptoms may be irreversible. The risk of severe tendon disorder with fluoroquinolones is higher in older patients usually over 60 years of age, in patients taking corticosteroid drugs, and in patients with kidney, heart or lung transplants.
- Peripheral Neuropathies: Inform patients that peripheral neuropathies have been associated with moxifloxacin use, symptoms may occur soon after initiation of therapy and may be irreversible. If symptoms of peripheral neuropathy including pain, burning, tingling, numbness and/or weakness develop, immediately discontinue moxifloxacin and tell them to contact their physician.
- Central nervous system effects (for example, convulsions, dizziness, lightheadedness, increased intracranial pressure): Inform patients that convulsions have been reported in patients receiving fluoroquinolones, including moxifloxacin. Instruct patients to notify their physician before taking this drug if they have a history of convulsions. Inform patients that they should know how they react to moxifloxacin before they operate an automobile or machinery or engage in other activities requiring mental alertness and coordination. Instruct patients to notify their physician if persistent headache with or without blurred vision occurs.
- Exacerbation of Myasthenia Gravis: Instruct patients to inform their physician of any history of myasthenia gravis. Instruct patients to notify their physician if they experience any symptoms of muscle weakness, including respiratory difficulties.
- Hypersensitivity Reactions: Inform patients that moxifloxacin can cause hypersensitivity reactions, even following a single dose, and to discontinue the drug at the first sign of a skin rash, hives or other skin reactions, a rapid heartbeat, difficulty in swallowing or breathing, any swelling suggesting angioedema (for example, swelling of the lips, tongue, face, tightness of the throat, hoarseness), or other symptoms of an allergic reaction.
- Hepatotoxicity: Inform patients that severe hepatotoxicity (including acute hepatitis and fatal events) has been reported in patients taking moxifloxacin. Instruct patients to inform their physician if they experience any signs or symptoms of liver injury including: loss of appetite, nausea, vomiting, fever, weakness, tiredness, right upper quadrant tenderness, itching, yellowing of the skin and eyes, light colored bowel movements or dark colored urine.
- Aortic aneurysm and dissection: Inform patients to seek emergency medical care if they experience sudden chest, stomach, or back pain.
- Diarrhea: Diarrhea is a common problem caused by antibiotics which usually ends when the antibiotic is discontinued. Sometimes after starting treatment with
- antibiotics, patients can develop watery and bloody stools (with or without stomach cramps and fever) even as late as two or more months after having taken the last dose of the antibiotic. If this occurs, instruct patients to contact their physician as soon as possible.
- Prolongation of the QT Interval: Instruct patients to inform their physician of any personal or family history of QT prolongation or proarrhythmic conditions such as hypokalemia, bradycardia, or recent myocardial ischemia; if they are taking any Class IA (quinidine, procainamide), or Class III (amiodarone, sotalol) antiarrhythmic agents. Instruct patients to notify their physician if they have any symptoms of prolongation of the QT interval, including prolonged heart palpitations or a loss of consciousness.
- Photosensitivity/Phototoxicity: Inform patients that photosensitivity/phototoxicity has been reported in patients receiving fluoroquinolones. Inform patients to minimize or avoid exposure to natural or artificial sunlight (tanning beds or UVA/B treatment) while taking quinolones. If patients need to be outdoors while using quinolones, instruct them to wear loose-fitting clothes that protect skin from sun exposure and discuss other sun protection measures with their physician. If a sunburn-like reaction or skin eruption occurs, instruct patients to contact their physician.
- Blood Glucose Disturbances: Inform the patients that if they are diabetic and are being treated with insulin or an oral hypoglycemic agent and a hypoglycemic reaction occurs, they should discontinue moxifloxacin and consult a physician.
Antibacterial Resistance
Antibacterial drugs including moxifloxacin should only be used to treat bacterial infections. They do not treat viral infections (for example, the common cold). When moxifloxacin is prescribed to treat a bacterial infection, patients should be told that although it is common to feel better early in the course of therapy, the medication should be taken exactly as directed. Skipping doses or not completing the full course of therapy may (1) decrease the effectiveness of the immediate treatment and (2) increase the likelihood that bacteria will develop resistance and will not be treatable by moxifloxacin or other antibacterial drugs in the future.
The brand names mentioned in this document are the trademarks of their respective owners.
Manufactured for:

Lake Zurich, IL 60047
Made in Norway
www.fresenius-kabi.com/us
451325G