


Prescribing information (package insert) - Lisraya
WARNING: SERIOUS INFECTIONS, MORTALITY, MALIGNANCY, MAJOR ADVERSE CARDIOVASCULAR EVENTS, and THROMBOSIS
SERIOUS INFECTIONS
Patients treated with LISRAYA are at increased risk of developing serious bacterial, fungal, viral, and opportunistic infections that may lead to hospitalization or death.
Reported infections with use of Janus kinase (JAK) inhibitors, including LISRAYA:
- Active tuberculosis (TB), which may present with pulmonary or extrapulmonary disease. Evaluate and test patients for latent and active TB infection prior to and during LISRAYA treatment. If positive, treat for TB. Monitor all patients for active TB during treatment including patients who tested negative of a latent TB infection prior to LISRAYA treatment.
- Invasive fungal infections. Patients with invasive fungal infections may present with disseminated, rather than localized, disease.
- Bacterial, viral, including herpes zoster, and other infections due to opportunistic pathogens.
Avoid use of LISRAYA in patients with an active, serious infection, including localized infections. Consider the risks and benefits of LISRAYA in patients with chronic or recurrent infection prior to initiating treatment. Closely monitor patients for signs and symptoms of infection during and after treatment with LISRAYA. If a serious infection occurs, interrupt LISRAYA treatment until the infection resolves or is adequately treated [see Warnings and Precautions (5.1)] .
MORTALITY
A higher rate of all-cause mortality, including sudden cardiovascular death was observed with another Janus kinase (JAK) inhibitor when compared to tumor necrosis factor (TNF) blockers in patients with rheumatoid arthritis (RA) [see Warnings and Precautions (5.2)]. LISRAYA is not approved for use in patients with RA.
MALIGNANCY
Malignancies have occurred in patients treated with LISRAYA. A higher rate of malignancies (excluding non-melanoma skin cancer), lymphomas, and lung cancers was observed with another JAK inhibitor when compared to TNF blockers in patients with RA . LISRAYA is not approved for use in patients with RA. Patients who are current or past smokers are at additional increased risk [see Warnings and Precautions (5.3)] .
MAJOR ADVERSE CARDIOVASCULAR EVENTS
Major adverse cardiovascular events (MACE) (defined as cardiovascular death, myocardial infarction, and stroke) have occurred in patients treated with LISRAYA. A higher rate of MACE was observed with another JAK inhibitor when compared to TNF blockers in patients with RA. LISRAYA is not approved for use in patients with RA. Patients who are current or past smokers are at additional increased risk. Discontinue LISRAYA in patients who have experienced a myocardial infarction or stroke [see Warnings and Precautions (5.4)] .
THROMBOSIS
Thromboses, including deep venous thrombosis, pulmonary embolism, and arterial thrombosis, have occurred in patients treated for inflammatory conditions with JAK inhibitors, including LISRAYA. Many of these adverse reactions were serious and some resulted in death. A higher rate of thromboses was observed with another JAK inhibitor when compared to TNF blockers in patients with RA. LISRAYA is not approved for use in patients with RA. Avoid LISRAYA in patients who may be at risk of thrombosis. If symptoms of thrombosis occur, discontinue LISRAYA, promptly evaluate, and appropriately treat [see Warnings and Precautions (5.5)].
1 INDICATIONS AND USAGE
LISRAYA is indicated for the treatment of dermatomyositis in adult patients.
Limitations of Use
LISRAYA is not recommended for use in combination with other JAK inhibitors, other TYK2 inhibitors, or biologic DMARDs.
2 DOSAGE AND ADMINISTRATION
2.1 Recommended Evaluations and Immunizations Prior to Treatment Initiation
Prior to LISRAYA treatment initiation, consider performing the following:
- Active and latent tuberculosis (TB) infection evaluation: If positive, treat for TB prior to LISRAYA treatment [see Warnings and Precautions (5.1)].
- Viral hepatitis screening in accordance with clinical guidelines: LISRAYA is not recommended in patients with active hepatitis B or hepatitis C [see Warnings and Precautions (5.1)].
- A complete blood count: Avoid LISRAYA in patients with an absolute lymphocyte count less than 500 cells/mm3, absolute neutrophil count less than 1,000 cells/mm3, or hemoglobin level less than 8 g/dL [see Warnings and Precautions (5.9)].
- Baseline hepatic and renal function tests: LISRAYA is not recommended in patients with severe hepatic or severe renal impairment [see Use in Specific Populations (8.6 , 8.7) and Clinical Pharmacology (12.3)].
- Pregnancy Status: Verify the pregnancy status of females of reproductive potential prior to treatment with LISRAYA [see Warnings and Precautions (5.11) and Use in Specific Populations (8.1, 8.3)].
- Update immunizations according to current immunization guidelines [see Warnings and Precautions (5.10)].
2.2 Recommended Dosage and Administration
The recommended dosage of LISRAYA is 30 mg once daily, administered orally with or without food [see Clinical Pharmacology (12.3)].
2.3 Recommended Dosage Interruption
Infections
If a patient develops a serious infection, including serious opportunistic infection, interrupt LISRAYA treatment until the infection resolves or is adequately treated. [see Warnings and Precautions (5.1)].
Laboratory Abnormalities
Interruption of LISRAYA treatment may be needed for management of laboratory abnormalities as described in Table 1 [see Warnings and Precautions (5.9)].
Table 1: Recommended Dosage Interruptions for Laboratory Abnormalities
| Laboratory Measure | Action |
|---|---|
| Absolute Neutrophil Count (ANC) | Interrupt LISRAYA treatment if ANC is less than 1,000 cells/mm3; treatment may be restarted once ANC returns above this value |
| Absolute Lymphocyte Count (ALC) | Interrupt LISRAYA treatment if ALC is less than 500 cells/mm3; treatment may be restarted once ALC returns above this value |
| Hemoglobin (Hb) | Interrupt LISRAYA treatment if Hb is less than 8 g/dL; treatment may be restarted once Hb returns above this value |
| Hepatic transaminases (ALT/AST) | Interrupt LISRAYA treatment if drug-induced liver injury is suspected, until this diagnosis is excluded. |
3 DOSAGE FORMS AND STRENGTHS
Tablets: 30 mg of brepocitinib; pink, capsule-shaped, immediate-release, film-coated, and debossed with “BT30” on one side
4 CONTRAINDICATIONS
LISRAYA is contraindicated in patients with a history of hypersensitivity reactions to brepocitinib or any of the excipients in LISRAYA [see Warnings and Precautions (5.6)].
5 WARNINGS AND PRECAUTIONS
5.1 Serious Infections
LISRAYA increases the risk of infections, including serious bacterial, fungal, viral, and opportunistic infections that may lead to hospitalization or death. The most common serious infections reported with LISRAYA were pneumonia and sepsis [see Adverse Reactions (6.1)]. Other reported infections with use of JAK inhibitors, including LISRAYA, were tuberculosis, which may present with pulmonary or extrapulmonary disease, invasive fungal infections which may present with disseminated rather than localized disease, bacterial infections, viral infections (including herpes zoster), and other infections due to opportunistic pathogens.
Avoid use of LISRAYA in patients with an active, serious infection, including localized infections. Consider the risks and benefits of treatment prior to initiating LISRAYA in patients:
- with chronic or recurrent infection
- who have been exposed to TB
- with a history of a serious or an opportunistic infection
- who have resided or traveled in areas of endemic TB or endemic mycoses; or
- with underlying conditions that may predispose them to infection.
Closely monitor patients for signs and symptoms of infection during and after treatment with LISRAYA. If a patient develops a serious infection, including a serious opportunistic infection, interrupt LISRAYA treatment until the infection resolves or is adequately treated. In patients who develop a new infection during treatment with LISRAYA, promptly complete diagnostic testing, initiate appropriate antimicrobial therapy, and monitor the patients closely. LISRAYA may be resumed once the infection resolves or is adequately treated.
Tuberculosis
Evaluate and test patients for latent and active TB infection prior to and during administration of LISRAYA. If positive, treat for TB prior to LISRAYA treatment.
Consider anti-TB therapy prior to initiation of LISRAYA in patients with a past history of latent or active TB in whom an adequate course of treatment cannot be confirmed. Consultation with a physician with expertise in the treatment of TB is recommended to aid in the decision about whether initiating anti-TB therapy is appropriate for an individual patient.
Monitor patients, including patients who tested negative for latent TB infection prior to LISRAYA treatment, for signs and symptoms of active TB during LISRAYA treatment.
Viral Reactivation
Viral reactivation, including cases of herpes virus reactivation (e.g., herpes zoster) were reported in patients who received LISRAYA. If a patient develops herpes zoster, consider interrupting LISRAYA until the episode resolves.
Prior to initiating LISRAYA treatment, perform viral hepatitis screening in accordance with clinical guidelines. Monitor patients for viral hepatitis reactivation during therapy with LISRAYA. Patients who were positive for hepatitis C antibody and hepatitis C virus RNA were excluded from clinical trials. Patients who were positive for hepatitis B surface antigen or hepatitis B virus DNA were excluded from clinical trials. If hepatitis B virus DNA is detected during LISRAYA treatment, consult a liver specialist. LISRAYA is not recommended in patients with active hepatitis B or hepatitis C.
5.2 Mortality
In a large, randomized, postmarketing safety study of another JAK inhibitor in patients with rheumatoid arthritis (RA) 50 years of age and older with at least one cardiovascular risk factor, a higher rate of all-cause mortality, including sudden cardiovascular death, was observed in patients treated with the JAK inhibitor compared with TNF blockers. Consider the benefits and risks for the individual patient prior to initiating or continuing LISRAYA treatment. LISRAYA is not approved for the treatment of RA.
5.3 Malignancy and Lymphoproliferative Disorders
Malignancies were observed in clinical trials of LISRAYA.
In a large, randomized, postmarketing safety study of another JAK inhibitor in patients with RA, a higher rate of malignancies (excluding non-melanoma skin cancer [NMSC]) and lymphomas were observed in patients treated with the JAK inhibitor compared to those treated with TNF blockers. A higher rate of lung cancers was observed in current or past smokers treated with the JAK inhibitor compared to those treated with TNF blockers. In this study, current or past smokers had an additional increased risk of overall malignancies. LISRAYA is not approved for the treatment of RA.
Consider the benefits and risks for the individual patient prior to initiating or continuing LISRAYA treatment, particularly in patients with a known malignancy (other than a successfully treated NMSC) and patients who develop a malignancy during treatment with LISRAYA.
Advise patients to limit exposure to ultraviolet (UV) light (natural or artificial) by wearing protective clothing and using a broad-spectrum sunscreen. Periodic skin examination is recommended for patients who are at increased risk for skin cancer.
5.4 Major Adverse Cardiovascular Events
Major adverse cardiovascular events (MACE), defined as cardiovascular death, non-fatal myocardial infarction (MI), and non-fatal stroke, were observed in patients treated with LISRAYA during clinical trials. In the dermatomyositis clinical trial, referred to as “Trial DM,” inclusive of open-label treatment, adjudicated MACE occurred in 3 patients (1.1 per 100 patient-years) treated with LISRAYA.
In a large, randomized, postmarketing safety study of another JAK inhibitor in patients with RA 50 years of age and older with at least one cardiovascular risk factor, a higher rate of MACE was observed with the JAK inhibitor compared to those treated with TNF blockers. Patients who are current or past smokers are at additional increased risk. LISRAYA is not approved for the treatment of RA.
Consider the benefits and risks for the individual patient prior to initiating or continuing LISRAYA treatment, particularly in patients who are current or past smokers and patients with other cardiovascular risk factors. Inform patients about the symptoms of serious cardiovascular events and the steps to take if they occur. Discontinue LISRAYA in patients who have experienced a myocardial infarction or stroke.
5.5 Thrombosis
Thromboses, including deep venous thrombosis (DVT), pulmonary embolism (PE), and arterial thrombosis, have occurred in patients treated for inflammatory conditions with JAK inhibitors, including LISRAYA. Many of these adverse reactions were serious and some resulted in death. In a large, randomized, postmarketing safety study of another JAK inhibitor in patients with RA 50 years of age and older with at least one cardiovascular risk factor, higher rates of overall thrombosis, DVT, and PE were observed compared to those treated with TNF blockers. LISRAYA is not approved for the treatment of RA.
Avoid LISRAYA in patients who may be at increased risk of thrombosis. If a patient develops symptoms of thrombosis, discontinue LISRAYA, promptly evaluate, and appropriately treat.
5.6 Hypersensitivity Reactions
Hypersensitivity reactions were reported in patients who received LISRAYA. Some events were serious. If a clinically significant hypersensitivity reaction occurs, discontinue LISRAYA, and institute appropriate therapy.
5.7 Gastrointestinal Perforations
Gastrointestinal perforation has been reported in patients treated with JAK inhibitors, including LISRAYA.
Monitor LISRAYA-treated patients who may be at risk for gastrointestinal perforation (e.g., patients with a history of diverticulitis and those taking concomitant drugs that increases the risk for gastrointestinal perforation, including NSAIDs or corticosteroids). If a patient presents with new onset abdominal pain during LISRAYA treatment, promptly evaluate for gastrointestinal perforation.
5.8 Hypoglycemia in Patients with Diabetes
LISRAYA may cause hypoglycemia in patients with diabetes. Hypoglycemia, including severe hypoglycemia, has been reported following initiation of JAK inhibitors in patients with diabetes. During treatment with LISRAYA, consider increased monitoring of blood glucose as clinically indicated in patients with diabetes. Advise patients with diabetes to notify their healthcare provider if they develop signs or symptoms of hypoglycemia.
5.9 Laboratory Abnormalities
Neutropenia
Treatment with LISRAYA was associated with an increased incidence of neutropenia (i.e., ANC less than 1,000 cells/mm3).
Evaluate neutrophil counts at baseline and thereafter according to routine patient management. Avoid LISRAYA initiation, and interrupt LISRAYA treatment in patients with a low neutrophil count (i.e., ANC less than 1,000 cells/mm3) [see Dosage and Administration (2.1)].
Lymphopenia
ALC less than 500 cells/mm3 were reported in patients who received LISRAYA.
Evaluate lymphocyte counts at baseline and thereafter according to routine patient management. Avoid LISRAYA initiation or interrupt LISRAYA treatment in patients with a low lymphocyte count (i.e., less than 500 cells/mm3) [see Dosage and Administration (2.1)].
Anemia
Decreases in hemoglobin levels less than 8 g/dL were reported in LISRAYA-treated patients in clinical trials.
Evaluate hemoglobin at baseline and thereafter according to routine patient management. Avoid LISRAYA initiation or interrupt LISRAYA treatment in patients with a low hemoglobin level (i.e., less than 8 g/dL) [see Dosage and Administration (2.1)].
Lipids
Treatment with LISRAYA was associated with increases in lipid parameters, including total cholesterol, low-density lipoprotein (LDL) cholesterol, and high-density lipoprotein (HDL) cholesterol [see Adverse Reactions (6.1)]. The effect of these lipid parameter elevations on cardiovascular morbidity and mortality has not been determined. Assess lipid parameters approximately 12 weeks after initiation of LISRAYA treatment. Manage patients according to clinical guidelines for hyperlipidemia.
Liver Enzyme Elevations
Treatment with LISRAYA was associated with increased incidence of liver enzyme elevations compared to treatment with placebo. Evaluate liver enzymes, including AST, ALT, and gamma-glutamyl transferase (GGT), at baseline and according to routine patient management thereafter. In patients with dermatomyositis, elevations in AST and ALT may reflect underlying dermatomyositis disease activity, and therefore, it is important to obtain GGT. Promptly evaluate the cause of liver enzyme elevation to identify potential cases of drug-induced liver injury (DILI). If increases in ALT or AST are observed during routine patient management and DILI is suspected, interrupt LISRAYA treatment until DILI is excluded.
5.10 Immunizations
Avoid use of live vaccines immediately prior to and during LISRAYA treatment. Prior to initiating LISRAYA treatment, update immunizations, including prophylactic varicella zoster or herpes zoster vaccinations, according to current immunization guidelines.
5.11 Embryofetal Toxicity
Based on findings in animal studies, LISRAYA may cause fetal harm when administered to a pregnant woman. Administration of brepocitinib to pregnant rats and rabbits at exposures 1.6 and 3 times the exposure at the maximum recommended human dose (MRHD), respectively, during organogenesis resulted in fetal skeletal malformations and increased post-implantation loss. Verify the pregnancy status of females of reproductive potential prior to starting treatment. Advise pregnant women and females of reproductive potential of the potential risk to the fetus. Advise females of reproductive potential to use effective contraception during treatment with LISRAYA and for 3 days following the last dose [see Use in Specific Populations (8.1, 8.3)].
6 ADVERSE REACTIONS
The following clinically significant adverse reactions are described elsewhere in the labeling:
- Serious Infections [see Warnings and Precautions (5.1)]
- Mortality [see Warnings and Precautions (5.2)]
- Malignancy and Lymphoproliferative Disorders [see Warnings and Precautions (5.3)]
- Major Adverse Cardiovascular Events (MACE) [see Warnings and Precautions (5.4)]
- Thrombosis [see Warnings and Precautions (5.5)]
- Hypersensitivity Reactions [see Warnings and Precautions (5.6)]
- Gastrointestinal Perforations [see Warnings and Precautions (5.7)]
- Hypoglycemia in Patients with Diabetes [see Warnings and Precautions (5.8)]
- Laboratory Abnormalities [see Warnings and Precautions (5.9)]
6.1 Clinical Trials Experience
Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice.
The safety of LISRAYA in adult patients with dermatomyositis was evaluated in a 52-week Phase 3, double-blind, placebo-controlled trial (Trial DM) [see Clinical Studies (14)]. In this trial, 241 adult patients were randomized to receive LISRAYA 30 mg once daily (81 patients), brepocitinib 15 mg once daily (unapproved dosage) (81 patients), or placebo (79 patients) once daily for 52 weeks.
Table 2 summarizes the adverse reactions that occurred in ≥ 5% of LISRAYA-treated patients and ≥ 2% greater than placebo-treated patients in the 52-week placebo-controlled period. A total of 81 adult patients with dermatomyositis were exposed to LISRAYA during this period.
Table 2: Adverse Reactions Reported in ≥ 5% of Adult Patients with Dermatomyositis Who Received LISRAYA and ≥ 2% Greater Than Patients Who Received Placebo (Trial DM)
| Adverse Reaction (any severity) | Placebo | LISRAYA |
|---|---|---|
N= 79 (%) | N= 81 (%) | |
| Upper Respiratory Tract Infection | 11 | 15 |
| Headache | 3 | 15 |
| Fatigue | 3 | 12 |
| Urinary Tract Infection | 5 | 11 |
| Nausea | 4 | 11 |
| Bronchitis | 4 | 10 |
| Arthralgia | 8 | 10 |
| Diarrhea | 5 | 9 |
| Back pain | 6 | 9 |
| Fall | 3 | 7 |
| Influenza | 4 | 6 |
| Acne | 0 | 6 |
Specific Adverse Reactions
Thrombosis
Thromboses were observed in clinical trials of LISRAYA. During the open-label extension period of Trial DM, a case of peripheral arterial thrombosis was reported in a LISRAYA-treated patient.
Overall Infections
During the 52-week treatment period of Trial DM, infections were reported in 45 (57%) placebo-treated patients and 56 (69%) LISRAYA-treated patients. The most commonly reported infections with LISRAYA were upper respiratory tract infections, urinary tract infections, bronchitis, and COVID-19.
- Serious Infections: During the 52-week treatment period of Trial DM, serious infections were reported in one (1%) placebo-treated patient and 8 (10%) LISRAYA-treated patients. The most common serious infections in LISRAYA-treated patients were pneumonia (two patients) and sepsis (two patients).
- Viral Reactivation: During the 52-week treatment period of Trial DM, viral reactivations were reported in 4 (5%) LISRAYA-treated patients. All viral reactivations with LISRAYA were herpes zoster.
Laboratory Abnormalities
Hepatic Transaminase Elevations: During the 52-week treatment period of Trial DM,
- Alanine transaminase (ALT) ≥ 3 x upper limit of normal (ULN) were observed in 7 (9%) placebo-treated patients and 8 (9.9%) LISRAYA-treated patients.
- Aspartate transaminase (AST) elevations ≥ 3 x upper limit of normal (ULN) were observed in 3 (3.8%) placebo-treated patients and 4 (4.9%) LISRAYA-treated patients.
- One case of probable drug-induced liver injury (mixed pattern with marked GGT elevation, normal bilirubin, and low concurrent creatine kinase [CK]) was reported in a patient who received brepocitinib 15 mg. The event resolved following discontinuation of brepocitinib.
Lipid Elevations: During the 52-week treatment period of Trial DM, LISRAYA treatment was associated with increases in total cholesterol, HDL cholesterol, and LDL cholesterol. Elevation in LDL and HDL cholesterol peaked by Week 8 and remained stable thereafter. In the 52-week treatment period of Trial DM, changes from baseline in lipid parameters in LISRAYA-treated patients are summarized below:
- Mean LDL cholesterol increased by 3.8 mg/dL.
- Mean HDL cholesterol increased by 4.5 mg/dL.
- Mean LDL/HDL ratio remained stable.
7 DRUG INTERACTIONS
7.1 Effects of Other Drugs on LISRAYA
Smoking
Smoking causes induction of CYP1A1 and CYP1A2 levels. The exposure of brepocitinib in current smokers is lower than in non-current smokers, and therefore, the effectiveness of LISRAYA may be reduced in smokers [see Clinical Pharmacology (12.3)].
7.2 Effects of LISRAYA on Other Drugs
Substrates of P-gp and BCRP
Brepocitinib is a P-gp and BCRP inhibitor. Concomitant use of LISRAYA with an orally administered P-gp or BCRP substrate may increase the systemic exposure of the P-gp or BCRP substrate [see Clinical Pharmacology (12.3)].
Substrates of OCT2 or MATEs Transporters
Brepocitinib inhibits renal uptake transporters, OCT2 and MATEs (MATE1, MATE2-K) [see Clinical Pharmacology (12.3)]. Concomitant use of LISRAYA with drugs that are substrates of OCT2 and MATEs transporters may increase plasma concentrations of the substrates. Closely monitor patients when LISRAYA is concomitantly used with drugs that are substrates of OCT2 or MATEs transporters for which minimal concentration changes in substrate plasma concentration may lead to serious adverse reactions.
8 USE IN SPECIFIC POPULATIONS
8.1 Pregnancy
Risk Summary
Based on findings in animal studies, LISRAYA may cause fetal harm when administered to a pregnant woman. Available data from LISRAYA use in pregnant women are insufficient to establish a drug associated risk of major birth defects, miscarriage or adverse maternal or fetal outcomes.
In animal reproduction studies, fetal skeletal malformations, and post-implantation loss were observed when brepocitinib was administered to pregnant rats and rabbits during the period of organogenesis at 1.6- and 3-times the exposure at the MRHD, respectively. In a pre- and postnatal study in rats, brepocitinib did not cause adverse effects in maternal animals or offspring at exposures up to 5.5 times the MRHD.
The background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15 % to 20%, respectively.
There is a pregnancy safety study for LISRAYA. If LISRAYA is administered during pregnancy, healthcare providers or patients should report LISRAYA exposure to Priovant Therapeutics by calling 1-800-511-9141 or by emailing contactcenter@priovant.com.
Clinical Considerations
Disease-Associated Maternal and/or Embryo/Fetal Risk
Published data suggest that increased disease activity is associated with the risk of developing adverse pregnancy outcomes in women with dermatomyositis. Adverse pregnancy outcomes include preterm delivery (before 37 weeks of gestation), low birth weight (less than 2500 g) infants, and small for gestational age at birth.
Data
Animal Data
In rat embryofetal developmental studies, pregnant rats were administered brepocitinib orally during the period of organogenesis. Skeletal malformations, early and late resorptions, post-implantation loss, and lower mean numbers of viable fetuses were observed with exposures 1.6 times the MRHD. No adverse effects were observed at 1.3 times the MRHD.
In a rabbit embryofetal developmental study, pregnant rabbits were administered brepocitinib orally during the period of organogenesis. Increase of late resorptions, post-implantation loss, lower mean numbers of viable fetuses, and skeletal malformations were observed at 3 times the MRHD. No developmental toxicity was observed in rabbits at 0.8 times the MRHD.
In a pre- and postnatal development study, pregnant rats were administered brepocitinib orally from gestation day 6 through day 21 of lactation. No effects on postnatal developmental, neurobehavioral, or reproductive performance of offspring were noted at 5.5 times the MRHD.
8.2 Lactation
Risk Summary
There are no data on the presence of brepocitinib in human or animal milk, the effects on the breastfed infant, or the effects on milk production. Because of the potential for serious adverse reactions in the breastfed infant, including infections, GI perforation, and malignancy, advise patients that breastfeeding is not recommended during treatment with LISRAYA and for 3 days (approximately 5 half-lives) after the last dose.
8.3 Females and Males of Reproductive Potential
Based on animal studies, brepocitinib may cause fetal harm when administered to pregnant women [see Use in Specific Populations (8.1)].
Pregnancy Testing
Verify the pregnancy status of females of reproductive potential prior to starting treatment with LISRAYA [see Use in Specific Populations (8.1)].
Contraception
Females: Advise females of reproductive potential to use effective contraception during treatment with LISRAYA and for 3 days after the last dose.
8.4 Pediatric Use
The safety and effectiveness of LISRAYA have not been established in pediatric patients.
8.5 Geriatric Use
Of the 81 LISRAYA-treated patients, 14 (17%) were 65 years of age and older. No overall differences in effectiveness of LISRAYA have been observed between patients 65 years of age and older and younger adult patients.
During the 52-week treatment period of Trial DM, overall rates of adverse events were similar between patients 65 years of age and older and younger adult patients; however, older adults experienced higher rates of serious adverse events (SAEs). In the general study population, SAEs occurred in 16% of LISRAYA-treated patients compared to 13% of placebo-treated patients. Among patients 65 years of age and older, SAEs were reported in 2 placebo-treated patients (15%) compared to 3 LISRAYA-treated patients (21%), including one viral reactivation (herpes zoster).
Viral reactivations were reported in 2 LISRAYA-treated patients (15 per 100 patient-years) 65 years of age and older, compared to 2 LISRAYA-treated patients (3 per 100 patient-years) 18 to less than 65 years of age.
8.6 Renal Impairment
The recommended dosage in patients with mild (eGFR: 60 to 89 mL/min) or moderate (eGFR: 30 to 59 mL/min) renal impairment is the same as in patients without renal impairment.
LISRAYA is not recommended in patients with severe renal impairment (eGFR: < 30 mL/min).
8.7 Hepatic Impairment
The recommended dosage in patients with mild (Child-Pugh A) or moderate (Child-Pugh B) hepatic impairment is the same as in patients without hepatic impairment.
LISRAYA has not been evaluated in patients with severe hepatic impairment (Child-Pugh C) and therefore, is not recommended in this population.
10 OVERDOSAGE
There is no specific antidote for overdose with LISRAYA. If an overdose of LISRAYA occurs, consider contacting the Poison Help line (1-800-222-1222) or a medical toxicologist for overdose management recommendations.
11 DESCRIPTION
LISRAYA is formulated with the tosylate salt of brepocitinib, a TYK2/JAK1 inhibitor.
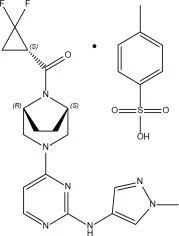
Brepocitinib tosylate is a white to off-white crystalline solid, slightly soluble in water and alcohol, with the following chemical name: [(1S)-2,2-difluorocyclopropyl][(1R,5S)-3-{2-[(1-methyl-1H-pyrazol-4-yl)amino]pyrimidin-4-yl}-3,8-diazabicyclo[3.2.1]oct-8-yl]methanone 4-methylbenzenesulfonate.
Brepocitinib tosylate has a molecular weight of 561.61 daltons (or 389.41 daltons as the free base) and a molecular formula of C25H29F2N7O4S. The chemical structure of brepocitinib tosylate is:
LISRAYA (brepocitinib) tablets are supplied for oral administration as 30 mg pink, capsule-shaped tablets. Each tablet of LISRAYA contains 30 mg of brepocitinib (equivalent to 43.27 mg brepocitinib tosylate) and the inactive ingredients hydroxypropyl methylcellulose, iron oxide red, lactose monohydrate, magnesium stearate, microcrystalline cellulose, sodium starch glycolate, titanium dioxide, and triacetin.
12 CLINICAL PHARMACOLOGY
12.1 Mechanism of Action
Brepocitinib is a Janus kinase (JAK) and tyrosine kinase 2 (TYK2) inhibitor. In a cell-free isolated enzyme assay, brepocitinib had greater inhibitory potency at TYK2 and JAK1 than JAK2 (≥ 3.4-fold) and JAK3 (≥ 286-fold). The JAK family comprises cytoplasmic tyrosine kinases that mediate signal transduction of cytokine receptors to influence immune cell function. Within the signaling pathway, JAKs phosphorylate and activate signal transducers and activators of transcription (STATs) which modulate intracellular activity including gene expression.
JAKs mediate cytokine signaling through hetero- or homodimeric pairing. In human cellular assays, brepocitinib inhibited signaling of TYK2- and JAK1-mediated cytokine-induced STAT phosphorylation, including signaling of TYK2/JAK1, TYK2/JAK2, JAK1/JAK3, and TYK2/JAK1/JAK2. The relevance of inhibition of specific JAK combinations to therapeutic effectiveness is not known.
12.2 Pharmacodynamics
Inhibition of Type I IFN and IL-6 induced STAT1 and STAT3 phosphorylation
In peripheral blood mononuclear cells isolated from dermatomyositis patients, brepocitinib resulted in concentration-dependent inhibition of Type I IFN induced and IL-6 induced phosphorylation of STAT1 and STAT3.
Inhibition of IFNγ, IL-10, IL-12, IL-13, and IL-23 induced STAT phosphorylation
In whole blood from healthy donors, brepocitinib resulted in concentration-dependent inhibition of IFNγ, IL-10, IL-12, IL-13, and IL-23 induced STAT1, STAT3, STAT4, STAT6, and STAT3 phosphorylation, respectively.
Gene Expression
After administration of LISRAYA 30 mg once daily to patients with dermatomyositis, expression of genes associated with Type I signaling were reduced by Week 12 and sustained through Week 52 in whole blood. The clinical relevance is unclear.
Cardiac Electrophysiology
LISRAYA caused concentration-dependent QTc interval prolongation with a supratherapeutic dose of 200 mg (6.67 times the approved recommended dose). At the maximum recommended LISRAYA oral dose of 30 mg once daily, clinically significant QTc interval prolongation is not expected.
12.3 Pharmacokinetics
Absorption
Following oral administration of LISRAYA, the median Tmax of brepocitinib is 1 hour. The absolute oral bioavailability of LISRAYA is approximately 75%.
Effect of Food
Coadministration of LISRAYA with a high-fat meal (approximately 50% fat and 800-1000 calories) resulted in 18% decrease in AUC and 36% decrease in Cmax [see Dosage and Administration (2.2)].
Distribution
Brepocitinib is 39% bound to plasma proteins. The blood to plasma partition ratio is 0.84.
Elimination
Metabolism
Brepocitinib is primarily cleared by metabolism, which is mediated mainly by cytochrome P450 (CYP)1A1 and CYP1A2 with minor contribution from CYP3A4. The pharmacologic activity of brepocitinib is attributed to the parent molecule. In a human radiolabeled study, unchanged brepocitinib and the major inactive metabolite M1 accounted for 48% and 37% of the total circulating radioactivity in plasma, respectively.
Excretion
Following oral administration of radiolabeled brepocitinib in healthy subjects, 88% (7.7% as unchanged and 51% as M1) and 8.7% (0.8% as unchanged and 0.7% as M1) of the total radioactivity was recovered in urine and feces, respectively. Brepocitinib mean terminal half-life ranged from 5.4 to 12 hours.
Specific Populations
Body Weight, Sex, Age, and Race
Based on population PK analysis, body weight (39-204 kg), sex, age (18-77 years) and race (White, Black, Asian, Native American, Pacific Islander, Other Race) did not have a clinically meaningful effect on brepocitinib exposure in adult patient populations.
Patients with Renal Impairment
Following a single oral administration of LISRAYA 30 mg, brepocitinib AUC was 29% lower, 48% higher, and 12% higher in subjects with mild (eGFR: 60 to 89 mL/min, based on Modification of Diet in Renal Disease formula), moderate (eGFR: 30 to 59 mL/min), and severe (eGFR: 15 to 29 mL/min) renal impairment, respectively. Cmax was 5% lower, 24% higher, and 10% higher in subjects with mild, moderate, and severe renal impairment, respectively, compared to subjects with normal renal function. Brepocitinib metabolite M1 AUC was 45% higher, 129% higher, and 346% higher in subjects with mild, moderate, and severe renal impairment, respectively. Cmax was 33% higher, 22% higher, and 78% higher in subjects with mild, moderate, and severe renal impairment, respectively, compared to subjects with normal renal function [see Use in Specific Populations (8.6)].
Patients with Hepatic Impairment
Following a single oral administration of LISRAYA 30 mg, brepocitinib AUC and Cmax was 19% higher and 27% lower, respectively, in subjects with moderate hepatic impairment (Child-Pugh B) compared to subjects with normal hepatic function. Brepocitinib metabolite M1 AUC and Cmax was 19% higher and 19% lower, respectively, in subjects with moderate hepatic impairment compared to subjects with normal hepatic function. LISRAYA was not evaluated in patients with severe hepatic impairment (Child-Pugh C) [see Use in Specific Populations (8.7)].
Drug Interaction Studies
Effects of Other Drugs on Pharmacokinetics of Brepocitinib
Smoking causes induction of CYP1A1 and CYP1A2 levels. Following the administration of LISRAYA 30 mg once daily, brepocitinib AUC and Cmax at steady state was estimated to be 45% and 33% lower, respectively, in current smokers compared to non-current smokers.
There was no clinically significant effect on the pharmacokinetics of brepocitinib when co-administered with multiple doses of itraconazole 200 mg once daily (CYP3A/P-gp inhibitor).
Effects of Brepocitinib on Pharmacokinetics of Other Drugs
Multiple doses of LISRAYA 60 mg once daily (2 times the approved recommended dosage) did not have a clinically significant effect on the PK of a combined oral contraceptive containing ethinylestradiol and levonorgestrel.
In vitro studies indicate that brepocitinib does not inhibit the activity of enzymes CYP1A2, CYP2B6, CYP2C8, CYP2C9, CYP2C19, CYP2D6, and CYP3A4/5, or human sulfotransferase enzymes or uridine 5'-diphospho-glucuronosyltransferases at clinically relevant concentrations.
In vitro studies indicate that brepocitinib does not induce CYP3A4, CYP2B6 or CYP1A2 at clinically relevant concentrations.
In vitro studies indicate that brepocitinib does not inhibit the transporters OATP1B1, OATP1B3, OAT1, OAT3, or BSEP. Brepocitinib inhibits OCT1, OCT2, MATE1, MATE2K, P-gp, and BCRP. The observed serum creatinine increase in clinical studies with brepocitinib is likely due to inhibition of tubular secretion of creatinine via OCT2, MATE1, and MATE2-K. The effect of brepocitinib on P-gp and BCRP has not been studied.
13 NONCLINICAL TOXICOLOGY
13.1 Carcinogenesis, Mutagenesis, Impairment of Fertility
Carcinogenesis
The carcinogenic potential of brepocitinib was evaluated in Wistar Han rats and Tg.rasH2 mice. No evidence of tumorigenicity was observed in mice administered brepocitinib orally up to 150 mg/kg/day. In male rats that received brepocitinib for 104 weeks at oral doses of 30 mg/kg/day (approximately 33 times the MRHD), brepocitinib caused benign Leydig cell tumors. The relevance of this finding to humans is not known. No evidence of tumorigenicity was observed in male or female rats that received brepocitinib for 104 weeks at oral doses up to 10 mg/kg/day or 30 mg/kg/day, respectively (approximately 10 or 33 times the MRHD).
Mutagenesis
Brepocitinib was negative for mutagenesis in the in vitro microbial reverse mutation assay (Ames assay). Brepocitinib was negative for mutagenesis in the in vivo micronucleus assay within rat peripheral blood cells.
Impairment of Fertility
In male rats, brepocitinib had no effect on fertility at oral doses up to 55 mg/kg/day (approximately 54 times the MRHD).
In female rats, brepocitinib reduced fertility at an oral dose of 10 mg/kg/day (approximately 10 times the MRHD) based upon higher early resorptions, higher post-implantation loss and a lower number of live embryos compared to control females. Additionally, maintenance of pregnancy was adversely affected at 55 mg/kg/day (approximately 50 times the MRHD) based upon findings of significantly lower corpora lutea and implantation sites and all pregnant females having total litter loss due to higher pre- and post-implantation loss. Brepocitinib had no effect on female fertility at 3 mg/kg/day (approximately 2 times the MRHD).
14 CLINICAL STUDIES
The efficacy of LISRAYA in the treatment of dermatomyositis in adults was assessed in a Phase 3 randomized, double-blind, multicenter, placebo-controlled trial in 241 adult patients with dermatomyositis (Trial DM; NCT05437263). Patients were randomized 1:1:1 to receive oral LISRAYA 30 mg once daily, brepocitinib 15 mg once daily (unapproved dosage), or placebo once daily for a 52-week double-blind treatment period. Enrolled patients were permitted to receive standard background therapies for dermatomyositis.
Patient demographics and disease characteristics were generally balanced across treatment arms. The study population was primarily female (78%) and White (72%), with a mean age of 51 years. At baseline, 65% of patients had at least one cardiovascular risk factor or history of atherosclerotic cardiovascular disease and 20% had interstitial lung disease. The majority of patients had active skin disease at baseline, with other baseline disease activity including a mean Physician Global Assessment score of 5.4, a mean Patient Global Assessment score of 6.0, a mean Manual Muscle Test-8 score of 122.6, and most abnormal muscle enzymes being lactate dehydrogenase (40%) and creatine kinase (36%); additionally, baseline dermatomyositis therapies included oral corticosteroids (76%), non-steroid immunosuppressive therapy (72%), and anti-malarials (27%). Patients were permitted to continue these therapies at a stable dosage throughout Trial DM.
Primary Efficacy Endpoint
In Trial DM, the primary endpoint was the mean Total Improvement Score (TIS) at Week 52. The TIS is a composite myositis improvement index reflecting changes in six core set measures (CSMs): Physician Global Assessment (PhGA), Patient Global Assessment (PtGA), Manual Muscle Testing of 8 Muscles (MMT-8), Extramuscular Global Assessment (EMGA), Health Assessment Questionnaire - Disability Index (HAQ-DI), and muscle enzymes (including aldolase, creatine kinase, alanine aminotransferase, aspartate aminotransferase, and lactate dehydrogenase). TIS values range from 0 to 100 with higher scores representing greater improvement.
Clinical Response
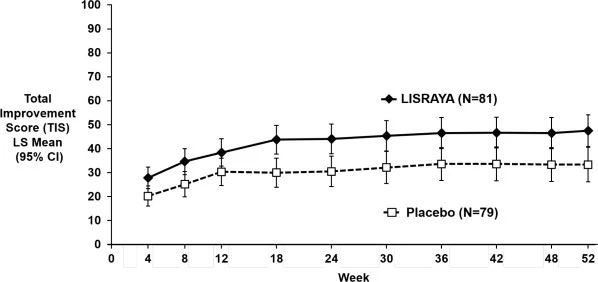
The LISRAYA group achieved a higher mean TIS at Week 52 compared to the placebo group, as shown in Table 3. Treatment with LISRAYA resulted in a higher proportion of patients who achieved a Major Improvement (TIS ≥ 60) at Week 52 compared to treatment with placebo (Table 3).
Table 3: TIS and TIS Responder Rates (% of Patients) at Week 52 in Adult Patients with Dermatomyositis in Trial DM
Placebo N = 79 | LISRAYA N = 81 | Difference vs. Placebo (95% CI) | |
|---|---|---|---|
| Abbreviations: LS: least squares; SE: standard error; CI: confidence interval | |||
| LS mean TIS, difference and 95% CI based on an analysis of covariance model adjusted for stratification factors. | |||
| Response rate (risk) differences calculated using the Cochran-Mantel-Haenszel method adjusted for stratification factors. | |||
LS Mean TIS (SE) (Primary Efficacy Endpoint) | 33.3 (3.7) | 47.5 (3.4) | 14.2 (5.5, 22.9) |
| TIS ≥ 20 | 63% | 82% | 19% (4.9, 33) |
| TIS ≥ 40 | 47% | 69% | 20% (5.1, 35) |
| TIS ≥ 60 | 26% | 48% | 22% (6.7, 37) |
The results for the Core Set Measures are presented in Table 4.
Table 4: Mean Change from Baseline in Core Set Measures (LS Means) at Week 52 in the Adult Patients with Dermatomyositis in Trial DM
| Abbreviations: LS: least squares; CI: confidence interval (LS means, difference and 95% CI based on an analysis of covariance model adjusting for stratification factors); PhGA: Physician Global Assessment; PtGA: Patient Global Assessment; EMGA: Extramuscular Global Assessment; MMT-8: Manual Muscle Testing of 8 Muscles; HAQ-DI: Health Assessment Questionnaire - Disability Index. | |||
| a Percent change from baseline for the most abnormal muscle enzymes including aldolase, creatine kinase, alanine aminotransferase, aspartate aminotransferase, and lactate dehydrogenase. | |||
| For all the individual measures except MMT-8, lower values represent improvement. For MMT-8, lower values represent worsening. | |||
| Measure (score range) | Placebo N=79 | LISRAYA N=81 | Difference vs. Placebo (95% CI) |
| PhGA (0 to 10) | -0.9 | -2.6 | -1.6 (-2.8, -0.5) |
| PtGA (0 to 10) | -0.6 | -2.5 | -1.9 (-2.9, -0.9) |
| EMGA (0 to 10) | -0.2 | -1.8 | -1.6 (-2.8, -0.4) |
| MMT-8 (0 to 150) | 5.9 | 12.3 | 6.4 (0.5, 12.3) |
| HAQ-DI (0 to 3) | 0.3 | -0.3 | -0.6 (-0.9, -0.3) |
| Most abnormal muscle enzymea | 36.8% | 16.9% | -19.9% (-46.9%, 7.1%) |
Figure 1 shows the mean TIS score through the 52-week double-blind treatment period.
Figure 1: TIS by Visit Through Week 52 in Adult Patients with Dermatomyositis in Trial DM
Abbreviations: LS: least squares; CI: confidence interval
Effect on Cutaneous Disease
In Trial DM, treatment with LISRAYA resulted in an improvement in skin disease activity, driven primarily by reductions in erythema.
Effect on Concomitant Corticosteroid Treatment
At baseline, 76% of patients received oral corticosteroids, with a mean dose of 11.4 mg/day of prednisone or equivalent in Trial DM. The proportion of patients who achieved TIS ≥ 40 with minimal-to-no corticosteroids (≤ 2.5 mg/day) at Week 52 in the LISRAYA and placebo groups was 55% and 30%, respectively, with a difference of 23.3% (95% CI: 8.3%, 38.2%).
Among patients who received ≥ 7.5 mg/day of corticosteroids at baseline, the proportion of patients who used a corticosteroid dose ≤ 2.5 mg/day at both Week 48 and Week 52 was 62% in the LISRAYA group and 38% in the placebo group, while the proportion of patients with no corticosteroid use (0 mg/day) at both Week 48 and Week 52 was 45% in the LISRAYA group and 29% in the placebo group.
Physical Function Response
In Trial DM, the LISRAYA group showed a higher observed improvement in physical function compared to the placebo group as assessed by HAQ-DI at Week 52.
16 HOW SUPPLIED/STORAGE AND HANDLING
LISRAYA (brepocitinib) tablets, 30 mg, are pink, capsule-shaped, film-coated, and debossed with “BT30” on one side. They are supplied as follows:
- 30 tablets in a bottle; NDC: 87211-030-30
Store below 30°C (86°F).
17 PATIENT COUNSELING INFORMATION
Advise patients and caregivers to read the FDA-approved patient labeling (Medication Guide).
Serious Infections
Inform patients that they may be more likely to develop infections when taking LISRAYA. Instruct patients to contact their healthcare provider immediately during treatment if they develop any signs or symptoms of an infection [see Warnings and Precautions (5.1)].
Advise patients that the risk of herpes zoster infection is increased in patients taking LISRAYA and some cases can be serious [see Warnings and Precautions (5.1)].
Malignancies
Inform patients that LISRAYA may increase their risk of certain cancers and that periodic skin examinations should be performed while using LISRAYA. Instruct patients to inform their healthcare provider if they have ever had any type of cancer [see Warnings and Precautions (5.3)].
Advise patients to limit exposure to ultraviolet light (natural or artificial) by wearing protective clothing and using a broad-spectrum sunscreen.
Major Adverse Cardiovascular Events
Inform patients that LISRAYA may increase their risk of major adverse cardiovascular events (MACE) including myocardial infarction, stroke, and cardiovascular death. Instruct all patients, especially current or past smokers or patients with other cardiovascular risk factors, to be alert for the development of signs and symptoms of cardiovascular events [see Warnings and Precautions (5.4)].
Thrombosis
Advise patients that LISRAYA may increase the risk of thromboembolic events. Instruct patients to seek immediate medical attention if they develop any signs or symptoms of a DVT or PE [see Warnings and Precautions (5.5)].
Hypersensitivity Reactions
Advise patients to discontinue LISRAYA and seek immediate medical attention if they develop any signs and symptoms of an allergic reaction [see Warnings and Precautions (5.6)].
Gastrointestinal Perforations
Inform patients that gastrointestinal perforation has been reported in clinical trials with LISRAYA and that risk factors include the use of NSAIDs, corticosteroids, and history of diverticulitis. Instruct patients to seek medical care immediately if they experience new onset of abdominal pain, fever, chills, nausea, or vomiting [see Warnings and Precautions (5.7)].
Hypoglycemia in Patients with Diabetes
Inform patients with diabetes that LISRAYA can cause hypoglycemia. Consider advising patients with diabetes to increase monitoring of blood glucose. Advise patients with diabetes to notify their healthcare provider if they develop signs or symptoms of hypoglycemia [see Warnings and Precautions (5.8)].
Laboratory Abnormalities
Inform patients that LISRAYA may affect certain lab tests, and that blood tests are required before and during LISRAYA treatment [see Warnings and Precautions (5.9)].
Immunizations
Advise patients to avoid use of live vaccines with LISRAYA. Instruct patients to inform their healthcare provider that they are taking LISRAYA prior to a potential vaccination [see Warnings and Precautions (5.10)].
Embryofetal Toxicity
Advise pregnant women and females of reproductive potential that exposure to LISRAYA during pregnancy may result in fetal harm. Advise females to inform their healthcare provider of a known or suspected pregnancy [see Warnings and Precautions (5.11) and Use in Specific Populations (8.1)].
Advise females of reproductive potential that effective contraception should be used during treatment and for 3 days following the final dose of LISRAYA [see Use in Specific Populations (8.1, 8.3)].
Inform patients to report their pregnancy to Priovant Therapeutics by calling 1-800-511-9141 or emailing contactcenter@priovant.com [see Use in Specific Populations (8.1)].
Lactation
Advise women not to breastfeed during treatment with LISRAYA and for 3 days after the last dose [see Use in Specific Populations (8.2)].
Manufactured for:
Priovant Therapeutics, Inc.
1007 Slater Road, Suite 250
Durham NC, 27703
LISRAYA™ is a trademark of Priovant Therapeutics, Inc.
U.S. Patent No. 9,663,526 and 11,197,867