


Prescribing information (package insert) - Kitabis Pak
1 INDICATIONS AND USAGE
KITABIS PAK (co-packaging of tobramycin inhalation solution and PARI LC PLUS Reusable Nebulizer) is indicated for the management of cystic fibrosis in adults and pediatric patients 6 years of age and older with P. aeruginosa. Safety and efficacy have not been demonstrated in patients under the age of 6 years, patients with FEV1 < 25% or > 75% predicted, or patients colonized with Burkholderia cepacia [see Clinical Studies (14)].
2 DOSAGE AND ADMINISTRATION
2.1 Dosing Information
- KITABIS PAK is a co-packaging of tobramycin inhalation solution ampules with a PARI LC PLUS Reusable Nebulizer. Administer as follows: One single-use ampule (300 mg/5 mL) of tobramycin inhalation solution twice a day by oral inhalation in alternating periods of 28 days on drug, followed by 28 days off drug.
- The 300 mg/5 mL dose of tobramycin inhalation solution is the same for all patients regardless of age or weight.
- The doses should be taken as close to 12 hours apart as possible; they should not be taken less than 6 hours apart.
2.2 Administration of Tobramycin Inhalation Solution
Each dose of tobramycin inhalation solution is administered by oral inhalation using only the co-packaged PARI LC PLUS Reusable Nebulizer (Model No. 022B81-T) included in the KITABIS PAK, along with a DeVilbiss Pulmo-Aide air compressor (Model No. 5650D).
Tobramycin inhalation solution is not for subcutaneous, intravenous or intrathecal administration.
Prior to administration, read the Patient Information/Instructions for Use for KITABIS PAK for detailed information on how to use KITABIS PAK and follow the manufacturer's instructions for use and care of the DeVilbiss Pulmo-Aide air compressor.
The entire tobramycin inhalation solution treatment should take approximately 15 minutes to complete. Continue treatment until all the tobramycin inhalation solution has been delivered, and there is no longer any mist being produced.
Tobramycin inhalation solution should not be diluted or mixed with other drugs including dornase alfa in the nebulizer. Instruct patients on multiple therapies to take their medications prior to inhaling the tobramycin inhalation solution, or as directed by their physician.
Tobramycin inhalation solution should not be used if it is cloudy, if there are particles in the solution, or if it has been stored at room temperature for more than 28 days.
3 DOSAGE FORMS AND STRENGTH
Inhalation solution: 300 mg/5 mL in a single-use ampule
4 CONTRAINDICATIONS
Tobramycin inhalation solution is contraindicated in patients with a known hypersensitivity to any aminoglycoside.
5 WARNINGS AND PRECAUTIONS
5.1 Bronchospasm
Bronchospasm can occur with inhalation of tobramycin inhalation solution. In clinical studies with tobramycin inhalation solution, changes in FEV1 measured after the inhaled dose were similar in tobramycin inhalation solution and placebo groups. Bronchospasm that occurs during the use of tobramycin inhalation solution should be treated as medically appropriate.
5.2 Ototoxicity
Ototoxicity with use of Tobramycin Inhalation Solution
Transient tinnitus occurred in eight tobramycin inhalation solution treated patients versus no placebo patients in the clinical studies. Tinnitus may be a sentinel symptom of ototoxicity, and therefore the onset of this symptom warrants further clinical investigation. In postmarketing experience, patients receiving tobramycin inhalation solution have reported hearing loss. Ototoxicity, manifested as both auditory and vestibular toxicity, has been reported with parenteral aminoglycosides. Vestibular toxicity may be manifested by vertigo, ataxia or dizziness. Patients with known or suspected auditory or vestibular dysfunction should be closely monitored when taking tobramycin inhalation solution. Monitoring might include obtaining audiometric evaluations and serum tobramycin levels. If ototoxicity is noted, the patient should be managed as medically appropriate, including potentially discontinuing tobramycin inhalation solution [see Adverse Reactions (6.2)].
Risk of Ototoxicity Due to Mitochondrial DNA Variants
Cases of ototoxicity with aminoglycosides have been observed in patients with certain variants in the mitochondrially encoded 12S rRNA gene (MT-RNR1), particularly the m.1555A>G variant. Ototoxicity occurred in some patients even when their aminoglycoside serum levels were within the recommended range. Mitochondrial DNA variants are present in less than 1% of the general US population, and the proportion of the variant carriers who may develop ototoxicity as well as the severity of ototoxicity is unknown. In case of known maternal history of ototoxicity due to aminoglycoside use or a known mitochondrial DNA variant in the patient, consider alternative treatments other than aminoglycosides unless the increased risk of permanent hearing loss is outweighed by the severity of infection and lack of safe and effective alternative therapies.
5.3 Nephrotoxicity
Nephrotoxicity was not seen during clinical studies with tobramycin inhalation solution but has been associated with aminoglycosides as a class. Patients with known or suspected renal dysfunction or taking concomitant nephrotoxic drugs along with tobramycin inhalation solution should have serum concentrations of tobramycin and laboratory measurements of renal function obtained at the discretion of the treating physician. If nephrotoxicity develops, the patient should be managed as medically appropriate, including potentially discontinuing tobramycin inhalation solution.
5.4 Neuromuscular Disorders
Aminoglycosides, including tobramycin, may aggravate muscle weakness because of a potential curare-like effect on neuromuscular function. Neuromuscular blockade, respiratory failure, and prolonged respiratory paralysis may occur more commonly in patients with underlying neuromuscular disorders, such as myasthenia gravis or Parkinson's disease. Prolonged respiratory paralysis may also occur in patients receiving neuromuscular blocking agents. If neuromuscular blockade occurs, it may be reversed by the administration of calcium salts but mechanical assistance may be necessary.
5.5 Embryo-Fetal Toxicity
Aminoglycosides can cause fetal harm when administered to a pregnant woman. Aminoglycosides cross the placenta, and streptomycin has been associated with several reports of total, irreversible, bilateral congenital deafness in pediatric patients exposed in utero. However, systemic absorption of tobramycin following inhaled administration is expected to be minimal [see Clinical Pharmacology (12.3)]. Patients who use KITABIS PAK during pregnancy, or become pregnant while taking tobramycin inhalation solution should be apprised of the potential hazard to the fetus [see Use in Specific Populations (8.1)].
5.6 Concomitant Use of Systemic Aminoglycosides
Patients receiving concomitant tobramycin inhalation solution and parenteral aminoglycoside therapy should be monitored as clinically appropriate for toxicities associated with aminoglycosides as a class. Serum tobramycin levels should be monitored.
6 ADVERSE REACTIONS
The following serious adverse reactions are described below and elsewhere in the labeling:
- Bronchospasm [see Warnings and Precautions (5.1)]
- Ototoxicity [see Warnings and Precautions (5.2)]
6.1 Clinical Trials Experience
Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice.
Tobramycin inhalation solution was studied in two clinical studies in 258 cystic fibrosis patients ranging in age from 6 to 48 years. Patients received tobramycin inhalation solution in alternating periods of 28 days on and 28 days off drug in addition to their standard cystic fibrosis therapy for a total of 24 weeks. Adverse reactions reported in these studies are described below:
- The most frequent adverse reactions in the tobramycin inhalation arm were cough, pharyngitis, and increased sputum (see Table 1).
- Thirty-three patients (13%) treated with tobramycin inhalation solution complained of voice alteration compared to 17 (7%) placebo patients. Voice alteration was more common in the on-drug periods.
- Eight patients from the tobramycin inhalation solution group (3%) reported tinnitus compared to no placebo patients. All episodes were transient, resolved without discontinuation of the tobramycin inhalation solution treatment regimen, and were not associated with loss of hearing in audiograms.
Table 1 lists the percent of patients with selected adverse reactions that occurred in > 5% of tobramycin inhalation solution patients during the two Phase III studies.
Table 1: Percent of Patients with Selected Adverse Reactions Occurring in > 5% of Tobramycin Inhalation Solution Patients
| 1 Includes reported decreases in pulmonary function tests or decreased lung volume on chest radiograph associated with intercurrent illness or study drug administration. | ||
| Adverse Reaction | Tobramycin Inhalation Solution (n=258) % | Placebo (n=262) % |
| Cough Increased | 46.1 | 47.3 |
| Pharyngitis | 38.0 | 39.3 |
| Sputum Increased | 37.6 | 39.7 |
| Dyspnea | 33.7 | 38.5 |
| Hemoptysis | 19.4 | 23.7 |
| Lung Function Decrease1 | 16.3 | 15.3 |
| Voice Alteration | 12.8 | 6.5 |
| Taste Perversion | 6.6 | 6.9 |
| Rash | 5.4 | 6.1 |
Selected adverse reactions that occurred in less than or equal to 5% of patients treated with tobramycin inhalation solution:
Ear and labyrinth disorders
Tinnitus
Musculoskeletal and connective tissue disorders
Myalgia
Infections and infestations
Laryngitis
6.2 Postmarketing Experience
The following adverse reactions have been identified during post approval use of tobramycin inhalation solution. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
Ear and labyrinth disorders
Hearing loss: Some of these reports occurred in patients with previous or concomitant treatment with systemic aminoglycosides. Patients with hearing loss frequently reported tinnitus. [see Warnings and Precautions (5.2)]
Skin and subcutaneous tissue disorders
Hypersensitivity, pruritus, urticaria, rash
Nervous system disorders
Aphonia, dysgeusia
Respiratory, thoracic, and mediastinal disorders
Bronchospasm [see Warnings and Precautions (5.1)], oropharyngeal pain
7 DRUG INTERACTIONS
7.1 Drugs with Neurotoxic, Nephrotoxic or Ototoxic Potential
Concurrent and/or sequential use of tobramycin inhalation solution with other drugs with neurotoxic, nephrotoxic, or ototoxic potential should be avoided if possible.
7.2 Diuretics
Some diuretics can enhance aminoglycoside toxicity by altering aminoglycoside concentrations in serum and tissue. Tobramycin inhalation solution should not be administered concomitantly with ethacrynic acid, furosemide, urea, or intravenous mannitol.
8 USE IN SPECIFIC POPULATIONS
8.1 Pregnancy
Risk Summary
Aminoglycosides can cause fetal harm. Published literature reports that use of streptomycin, an aminoglycoside, can cause total, irreversible, bilateral congenital deafness when administered to a pregnant woman [Warnings and Precautions (5.5)]. Although there are no available data on KITABIS PAK use in pregnant women to inform a drug-associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes, systemic absorption of tobramycin following inhaled administration is expected to be minimal [see Clinical Pharmacology (12.3)]. There are risks to the mother associated with cystic fibrosis in pregnancy (see Clinical Considerations).
In animal reproduction studies with subcutaneous administration of tobramycin in pregnant rats and rabbits during organogenesis there were no adverse developmental outcomes; however, ototoxicity was not evaluated in the offspring from these studies (see Data ). Advise pregnant women of the potential risk to a fetus.
The estimated background risk of major birth defects and miscarriage for the indicated populations are unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Clinical Considerations
Disease-Associated Maternal and/or Embryo/Fetal Risk
Cystic fibrosis may increase the risk for preterm delivery.
Data
Animal Data
No reproductive toxicity studies have been conducted with tobramycin inhalation solution. However, subcutaneous administration of tobramycin at doses of up to 100 (rat) or 20 (rabbit) mg/kg/day during organogenesis was not associated with adverse developmental outcomes. Subcutaneous doses of tobramycin ≥40 mg/kg/day were severely maternally toxic to rabbits and precluded the evaluation of adverse developmental outcomes. Ototoxicity was not evaluated in offspring during non-clinical reproductive toxicity studies with tobramycin.
8.2 Lactation
Risk Summary
There are no data on the presence of tobramycin inhalation solution in either human or animal milk, the effects on the breastfed infant, or the effects on milk production. Limited published data on other formulations of tobramycin in lactating women indicate that tobramycin is present in human milk. However, systemic absorption of tobramycin following inhaled administration is expected to be minimal [see Clinical Pharmacology (12.3)]. Tobramycin may cause alteration in the intestinal flora of the breastfeeding infant (see Clinical Considerations). The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for KITABIS PAK and any potential adverse effects on the breastfed infant from KITABIS PAK or from the underlying maternal condition.
Clinical Considerations
Tobramycin may cause intestinal flora alteration. Advise a woman to monitor the breastfed infant for loose or bloody stools and candidiasis (thrush, diaper rash).
8.4 Pediatric Use
The safety and efficacy of tobramycin inhalation solution have not been studied in pediatric patients under 6 years of age.
8.5 Geriatric Use
Clinical studies of tobramycin inhalation solution did not include patients aged 65 years and over. Tobramycin is known to be substantially excreted by the kidney, and the risk of adverse reactions to this drug may be greater in patients with impaired renal function. Because elderly patients are more likely to have decreased renal function, it may be useful to monitor renal function [see Warnings and Precautions (5.3)].
10 OVERDOSAGE
Signs and symptoms of acute toxicity from overdosage of IV tobramycin might include dizziness, tinnitus, vertigo, loss of high-tone hearing acuity, respiratory failure, and neuromuscular blockade. Administration by inhalation results in low systemic bioavailability of tobramycin. Tobramycin is not significantly absorbed following oral administration. Tobramycin serum concentrations may be helpful in monitoring overdosage.
11 DESCRIPTION
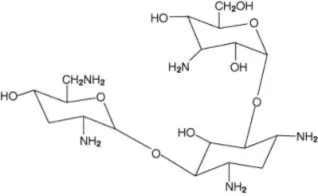
KITABIS PAK contains tobramycin inhalation solution, USP and the PARI LC PLUS Reusable Nebulizer (PARI LC PLUS). Tobramycin inhalation solution is a sterile, clear, slightly yellow, non-pyrogenic, aqueous solution with the pH and salinity adjusted specifically for administration by a compressed air driven PARI LC PLUS Reusable Nebulizer. The chemical formula for tobramycin is C18H37N5O9 and the molecular weight is 467.52. Tobramycin is O-3-amino-3-deoxy-α-D-glucopyranosyl-(1→4)-O-[2,6-diamino-2,3,6-trideoxy-a-D- ribo - hexopyranosyl-(1→6)]-2-deoxy-L-streptamine. The structural formula for tobramycin is:
Each single-use 5 mL ampule contains 300 mg tobramycin and 11.25 mg sodium chloride in sterile water for injection. Sulfuric acid and sodium hydroxide are added to adjust the pH to 6.0. Nitrogen is used for sparging. The formulation contains no preservatives. The inhalation solution has an osmolality in the range 135 to 200 mOsmol/kg.
The PARI LC PLUS Reusable Nebulizer has the following performance characteristics with tobramycin inhalation solution [measured using Next Generation Impactor (NGI) at 15 L/min continuous flow, standard conditions (50%RH, 23°C)]: (1) Delivered Dose: 174 mg; (2) Fine Particle Dose (< 5μm): 97 mg; (3) Nebulization Time: 13 min.; (4) Mass Median Aerodynamic Diameter: 4.3 μm; (5) Geometric Standard Deviation (GSD): 2.2 μm.
12 CLINICAL PHARMACOLOGY
12.1 Mechanism of Action
Tobramycin is an aminoglycoside antibacterial [see Microbiology (12.4) ].
12.3 Pharmacokinetics
Absorption
Tobramycin inhalation solution contains tobramycin, a cationic polar molecule that does not readily cross epithelial membranes.1 The bioavailability of tobramycin inhalation solution may vary because of individual differences in nebulizer performance and airway pathology.2 Following administration of tobramycin inhalation solution, tobramycin remains concentrated primarily in the airways.
Sputum Concentrations
Ten minutes after inhalation of the first 300 mg dose of tobramycin inhalation solution, the average concentration of tobramycin was 1237 mcg/g (ranging from 35 to 7414 mcg/g) in sputum. Tobramycin does not accumulate in sputum; after 20 weeks of therapy with the tobramycin inhalation solution regimen, the average concentration of tobramycin at ten minutes after inhalation was 1154 mcg/g (ranging from 39 to 8085 mcg/g) in sputum. High variability of tobramycin concentration in sputum was observed. Two hours after inhalation, sputum concentrations declined to approximately 14% of tobramycin levels at ten minutes after inhalation.
Serum Concentrations
The average serum concentration of tobramycin one hour after inhalation of a single 300 mg dose of tobramycin inhalation solution by cystic fibrosis patients was 0.95 mcg/mL. After 20 weeks of therapy on the tobramycin inhalation solution regimen, the average serum tobramycin concentration one hour after dosing was 1.05 mcg/mL.
Distribution
Following administration of tobramycin inhalation solution, tobramycin remains concentrated primarily in the airways. Binding of tobramycin to serum proteins is negligible.
Elimination
Metabolism
Tobramycin is not metabolized.
Excretion
The elimination half-life of tobramycin from serum is approximately 2 hours after intravenous (IV) administration. Assuming tobramycin absorbed following inhalation behaves similarly to tobramycin following IV administration, systemically absorbed tobramycin is eliminated principally by glomerular filtration. Unabsorbed tobramycin, following tobramycin inhalation solution administration, is likely eliminated primarily in expectorated sputum.
12.4 Microbiology
Mechanism of Action
Tobramycin is an aminoglycoside antibacterial produced by Streptomyces tenebrarius. It acts primarily by disrupting protein synthesis, leading to altered cell membrane permeability, progressive disruption of the cell envelope, and eventual cell death.3
Tobramycin has in vitro activity against Gram-negative bacteria including P. aeruginosa. It is bactericidal in vitro at peak concentrations equal to or slightly greater than the minimum inhibitory concentration.
Resistance
Treatment for 6 months with tobramycin inhalation solution in two clinical studies did not affect the susceptibility of the majority of P. aeruginosa isolates tested; however, increased minimum inhibitory concentrations (MICs) were noted in some patients. The clinical significance of this information has not been clearly established in the treatment of P. aeruginosa in cystic fibrosis patients [see Clinical Studies (14)].
Susceptibility Testing
Interpretive criteria for inhaled antibacterial products are not defined. The in vitro antimicrobial susceptibility test methods used for parenteral tobramycin therapy can be used to monitor the susceptibility of P. aeruginosa isolated from cystic fibrosis patients.4,5,6 If decreased susceptibility is noted, the results should be reported to the clinician. Susceptibility breakpoints established for parenteral administration of tobramycin do not apply to aerosolized administration of tobramycin inhalation solution. The relationship between in vitro susceptibility test results and clinical outcome with tobramycin inhalation solution therapy is not clear. A single sputum sample from a cystic fibrosis patient may contain multiple morphotypes of Pseudomonas aeruginosa and each morphotype may have a different level of in vitro susceptibility to tobramycin.
For specific information regarding susceptibility test interpretive criteria and associated test methods and quality control standards recognized by FDA for this drug, please see: https://www.fda.gov/STIC.
13 NONCLINICAL TOXICOLOGY
13.1 Carcinogenesis, Mutagenesis, Impairment of Fertility
A two-year rat inhalation toxicology study to assess carcinogenic potential of tobramycin inhalation solution has been completed. Rats were exposed to tobramycin inhalation solution for up to 1.5 hours per day for 95 weeks. The clinical formulation of the drug was used for this carcinogenicity study. Serum levels of tobramycin of up to 35 mcg/mL were measured in rats, in contrast to the average 1 mcg/mL levels observed in cystic fibrosis patients in clinical trials. There was no drug-related increase in the incidence of any variety of tumor.
Additionally, tobramycin has been evaluated for genotoxicity in a battery of in vitro and in vivo tests. The Ames bacterial reversion test, conducted with 5 tester strains, failed to show a significant increase in revertants with or without metabolic activation in all strains. Tobramycin was negative in the mouse lymphoma forward mutation assay, did not induce chromosomal aberrations in Chinese hamster ovary cells, and was negative in the mouse micronucleus test.
Subcutaneous administration of up to 100 mg/kg of tobramycin did not affect mating behavior or cause impairment of fertility in male or female rats.
14 CLINICAL STUDIES
Two identically designed, double-blind, randomized, placebo-controlled, parallel group, 24-week clinical studies (Study 1 and Study 2) at a total of 69 cystic fibrosis centers in the United States were conducted in cystic fibrosis patients with P. aeruginosa with tobramycin inhalation solution. Subjects who were less than 6 years of age, had a baseline creatinine of > 2 mg/dL, or had B. cepacia isolated from sputum were excluded. All subjects had baseline FEV1% predicted between 25% and 75%. In these clinical studies, 258 patients received tobramycin inhalation solution therapy on an outpatient basis (see Table 2) using a PARI LC PLUS nebulizer along with a DeVilbiss Pulmo-Aide compressor.
Table 2: Dosing Regimens in Clinical Studies
| Cycle 1 | Cycle 2 | Cycle 3 | ||||
| 28 days | 28 days | 28 days | 28 days | 28 days | 28 days | |
TOBRAMYCIN Inhalation Solution regimen n=258 | TOBRAMYCIN Inhalation Solution 300 mg twice daily | No drug | TOBRAMYCIN Inhalation Solution 300 mg twice daily | No drug | TOBRAMYCIN Inhalation Solution 300 mg twice daily | No drug |
Placebo regimen n=262 | Placebo twice daily | Placebo twice daily | Placebo twice daily | |||
All patients received either tobramycin inhalation solution or placebo (saline with 1.25 mg quinine for flavoring) in addition to standard treatment recommended for cystic fibrosis patients, which included oral and parenteral anti-pseudomonal therapy, Beta 2-agonists, cromolyn, inhaled steroids, and airway clearance techniques. In addition, approximately 77% of patients were concurrently treated with dornase alfa.
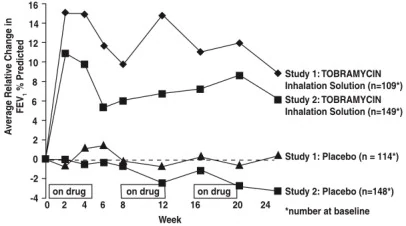
In each study, tobramycin inhalation solution-treated patients experienced significant improvement in pulmonary function. Improvement was demonstrated in the tobramycin inhalation solution group in Study 1 by an average increase in FEV1% predicted of about 11% relative to baseline (Week 0) during 24 weeks compared to no average change in placebo patients. In Study 2, tobramycin inhalation solution-treated patients had an average increase of about 7% compared to an average decrease of about 1% in placebo patients. Figure 1 shows the average relative change in FEV1% predicted over 24 weeks for both studies.
Figure 1: Relative Change From Baseline in FEV1% Predicted
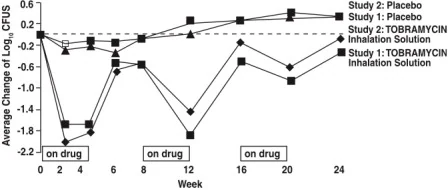
In each study, tobramycin inhalation solution therapy resulted in a significant reduction in the number of P. aeruginosa colony forming units (CFUs) in sputum during the on-drug periods. Sputum bacterial density returned to baseline during the off-drug periods. Reductions in sputum bacterial density were smaller in each successive cycle. (see Figure 2).
Figure 2: Absolute Change From Baseline in Log10 CFUs
Patients treated with tobramycin inhalation solution were hospitalized for an average of 5.1 days compared to 8.1 days for placebo patients. Patients treated with tobramycin inhalation solution required an average of 9.6 days of parenteral anti-pseudomonal antibiotic treatment compared to 14.1 days for placebo patients. During the 6 months of treatment, 40% of tobramycin inhalation solution patients and 53% of placebo patients were treated with parenteral anti-pseudomonal antibiotics.
The relationship between in vitro susceptibility test results and clinical outcome with tobramycin inhalation solution therapy is not clear. However, 4 tobramycin inhalation solution patients who began the clinical trial with P. aeruginosa isolates having MIC values ≥ 128 μg/mL did not experience an improvement in FEV1 or a decrease in sputum bacterial density.
15 REFERENCES
- 1. Neu HC. Tobramycin: an overview. [Review]. J Infect Dis 1976; Suppl 134:S3-19.
- 2. Weber A, Smith A, Williams-Warren J et al. Nebulizer delivery of tobramycin to the lower respiratory tract. Pediatr Pulmonol 1994; 17 (5):331-9.
- 3. Bryan LE. Aminoglycoside resistance. Bryan LE, Ed. Antimicrobial drug resistance. Orlando, FL: Academic Press, 1984: 241-77.
- 4. Clinical and Laboratory Standards Institute (CLSI). Methods for Dilution Antimicrobial Susceptibility Tests for Bacteria that Grow Aerobically; Approved Standard - Ninth Edition. CLSI document M07-A9, Clinical and Laboratory Standards Institute, 950 West Valley Road, Suite 2500, Wayne, Pennsylvania 19087, USA, 2012.
- 5. Clinical and Laboratory Standards Institute (CLSI). Performance Standards for Antimicrobial Disk Diffusion Susceptibility Tests; Approved Standard – Eleventh Edition. CLSI document M02-A11, Clinical and Laboratory Standards Institute, 950 West Valley Road, Suite 2500, Wayne, Pennsylvania 19087, USA, 2012.
- 6. Clinical and Laboratory Standards Institute (CLSI). Performance Standards for Antimicrobial Susceptibility Testing; Twenty-fourth Informational Supplement, CLSI document M100-S24, Clinical and Laboratory Standards Institute, 950 West Valley Road, Suite 2500, Wayne, Pennsylvania 19087, USA, 2014.
16 HOW SUPPLIED / STORAGE AND HANDLING
16.1 How Supplied
KITABIS PAK co-packaged kit (NDC 24492-850-56) is available in cartons containing one reusable PARI LC PLUS nebulizer (Model No.: 022B81-T) and 14 tobramycin inhalation solution pouches. Each pouch contains four 300 mg/5 ml ampules of tobramycin inhalation solution for a total of 56 ampules in each carton. Each carton constitutes a 28 day supply.
16.2 Storage
- Tobramycin inhalation solution should be stored under refrigeration at 2-8°C/36-46°F. Upon removal from the refrigerator, or if refrigeration is unavailable, tobramycin inhalation solution pouches (opened or unopened) may be stored at room temperature (up to 25°C/77°F) for up to 28 days. Tobramycin inhalation solution should not be used beyond the expiration date stamped on the ampule when stored under refrigeration (2-8°C/36-46°F) or beyond 28 days when stored at room temperature (25°C/77°F).
- Tobramycin inhalation solution ampules should not be exposed to intense light. The solution in the ampule is slightly yellow, but may darken with age if not stored in the refrigerator; however, the color change does not indicate any change in the quality of the product as long as it is stored within the recommended storage conditions.
17 PATIENT COUNSELING INFORMATION
Advise the patient to read the FDA-approved patient labeling (Patient Information and Instructions for Use).
Instructions for Administration
Instruct patients to read the Instructions for Use before starting KITABIS PAK. Instruct patients to use the tobramycin inhalation solution in KITABIS PAK only with the PARI LC PLUS Reusable Nebulizer included in the KITABIS PAK.
Difficulty Breathing
Advise patients to inform their physicians if they experience shortness of breath or wheezing after administration of tobramycin inhalation solution. Tobramycin inhalation solution can cause a narrowing of the airway [see Warnings and Precautions (5.1)].
Hearing Loss
Advise patients to inform their physician if they experience ringing in the ears, dizziness, or any changes in hearing because tobramycin inhalation solution has been associated with hearing loss [see Warnings and Precautions (5.2)].
Kidney Damage
Advise patients to inform their physician if they have any history of kidney problems because tobramycin inhalation solution is in a class of drugs that have caused kidney damage [see Warnings and Precautions (5.3)].
Embryo-Fetal Toxicity:
Advise pregnant women that aminoglycosides can cause irreversible congenital deafness when administered to a pregnant woman [see Warnings and Precautions (5.5) and Use in Specific Populations (8.1)].
Lactation:
Advise a woman to monitor their breastfed infants for diarrhea and/or bloody stools [see Use in Specific Populations (8.2)].
Additional Information
PARI LC PLUS® Reusable Nebulizer: 1-800-327-8632
DeVilbiss® Pulmo-Aide® Air Compressor: 1-800-338-1988
KITABIS PAK: 1-844-KITABIS (548-2247)
Manufactured by:
Woodstock Sterile Solutions, Inc.Woodstock, IL 60098
Distributed by:

PARI Respiratory Equipment, Inc.
2412 PARI Way, Midlothian, VA 23112
850D5601 Rev. F 08/2023 v5
©2023 PulmoFlow, Inc. All rights reserved.