


Prescribing information (package insert) - Endometrin
1 INDICATIONS AND USAGE
ENDOMETRIN® is indicated, as part of an Assisted Reproductive Technology (ART) treatment program, to support embryo implantation in infertile women less than 35 years of age by supplementation of corpus luteal function and to maintain pregnancy after implantation up to 10 weeks.
2 DOSAGE AND ADMINISTRATION
The recommended ENDOMETRIN dose is 100 mg administered vaginally two or three times daily starting the day after oocyte retrieval and continuing for up to 10 weeks total duration.
3 DOSAGE FORMS AND STRENGTHS
Vaginal insert: 100 mg - white to off-white oblong-shaped debossed with “FPI” on one side and “100” on the other side.
4 CONTRAINDICATIONS
ENDOMETRIN is contraindicated in women with any of the following conditions:
- Previous hypersensitivity reactions to progesterone or any of the ingredients of ENDOMETRIN [see Description (11)]
- Abnormal vaginal bleeding that has an undiagnosed etiology
- Known missed abortion or ectopic pregnancy
- Hepatic adenoma, hepatocellular carcinoma, acute hepatitis, or severe (decompensated) cirrhosis
- Current diagnosis of, or history of, a hormone-sensitive malignancy (e.g., breast cancer)
- Active arterial or venous thromboembolism or severe thrombophlebitis, or a history of these events
5 WARNINGS AND PRECAUTIONS
5.1 Cardiovascular or Cerebrovascular Disorders
Life-threatening arterial or venous thromboembolic disorders may occur during hormone treatment, including treatment with ENDOMETRIN.
The healthcare provider should be alert to earliest signs of myocardial infarction, cerebrovascular disorders, arterial or venous thromboembolism (venous thromboembolism or pulmonary embolism), thrombophlebitis, or retinal thrombosis. ENDOMETRIN should be discontinued if any of these are suspected.
5.2 Depression
ENDOMETRIN-treated women with a history of depression should be closely observed. Consider ENDOMETRIN discontinuation if symptoms worsen.
6 ADVERSE REACTIONS
6.1 Clinical Studies Experience
Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice.
The safety data reflect exposure to ENDOMETRIN in 808 infertile women in a single Assisted Reproductive Technology 10 week clinical study conducted in the U.S. [see Clinical Studies (14)]. ENDOMETRIN was studied at vaginally administered doses of 100 mg twice daily and 100 mg three times daily for 10 weeks and compared to a vaginally administered active comparator. The adverse reactions that occurred at a rate greater than or equal to 2% in either ENDOMETRIN group are summarized in Table 1.
Other less common reported adverse reactions in ENDOMETRIN-treated women included vaginal irritation, itching, burning, discomfort, urticaria, and peripheral edema.
Table 1: Number and Frequency of Reported Adverse Reactions in Infertile Women Treated with ENDOMETRIN in an Assisted Reproductive Technology Study
ENDOMETRIN 100 mg twice daily (N=404) | ENDOMETRIN 100 mg three times daily (N=404) | |
| Post-oocyte retrieval pain | 115 (28%) | 102 (25%) |
| Abdominal pain | 50 (12%) | 50 (12%) |
| Nausea | 32 (8%) | 29 (7%) |
| Ovarian hyperstimulation syndrome | 30 (7%) | 27 (7%) |
| Abdominal distension | 18 (4%) | 17 (4%) |
| Headache | 15 (4%) | 13 (3%) |
| Uterine spasm | 15 (4%) | 11 (3%) |
| Vaginal bleeding | 13 (3%) | 14 (3%) |
| Vomiting | 13 (3%) | 9 (2%) |
| Urinary tract infection | 9 (2%) | 4 (1%) |
| Constipation | 9 (2%) | 14 (3%) |
| Fatigue | 7 (2%) | 12 (3%) |
Adverse Reactions from Other Progesterone Products
Adverse reactions from other progesterone products included breast tenderness, bloating, mood swings, irritability, and drowsiness.
7 DRUG INTERACTIONS
Drugs known to induce the hepatic cytochrome-P450-3A4 system may increase the elimination of progesterone, lower progesterone exposure in ENDOMETRIN-treated women, and reduce the efficacy of ENDOMETRIN.
The effect of concomitant vaginal products on the exposure of progesterone from ENDOMETRIN has not been assessed. ENDOMETRIN is not recommended for use with other vaginal products (such as antifungal products) as this may alter progesterone release and absorption from the ENDOMETRIN vaginal insert.
8 USE IN SPECIFIC POPULATIONS
8.1 Pregnancy
Risk Summary
ENDOMETRIN is indicated, as part of an Assisted Reproductive Technology (ART) treatment program, to support embryo implantation in infertile women less than 35 years of age by supplementation of corpus luteal function and to maintain pregnancy after implantation up to 10 weeks.
Maternal risks of ENDOMETRIN use during pregnancy are discussed throughout the labeling.
In the US general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Data
Human Data: In one clinical study [see Clinical Studies (14)], ENDOMETRIN was vaginally administered to support embryo implantation during the first trimester of pregnancy and to maintain clinical pregnancy through week 10 of pregnancy when the placenta takes over production of progesterone. The live birth outcomes of these pregnancies were as follows:
- Among the 404 women treated with ENDOMETRIN twice daily, 143 (35%) women had live births consisting of 85 (59%) singletons, 56 (39%) twins, and 2 (1%) triplets. In this treatment group, 13 (3%) women had a spontaneous abortion, 1 (0.2%) woman had an ectopic pregnancy, and neonatal birth defects were reported in 7 infants (3% based on 203 live births).
- Among the 404 women treated with ENDOMETRIN three times daily, 155 (38%) women had live births consisting of 91 (59%) singletons, 60 (39%) twins, and 4 (3%) triplets. In this treatment group, 22 (5%) women had a spontaneous abortion, 4 (1%) women had an ectopic pregnancy, and neonatal birth defects were reported in 7 infants (3% based on 223 live births).
Birth defects reported in the ENDOMETRIN:
- Twice daily group included one neonate with a cleft palate and intrauterine growth retardation, one with spina bifida, three with congenital heart defects, one with an umbilical hernia, and one with an intestinal anomaly.
- Three times daily group included one neonate with an esophageal fistula, one with hypospadias and an underdeveloped right ear, one with Down Syndrome and an atrial septal defect, one with congenital heart anomalies, one with DiGeorge’s syndrome, one fetus with a hand deformity, and one with cleft palate.
For additional information on the pharmacology of ENDOMETRIN and pregnancy outcome information [see Clinical Pharmacology (12) and Clinical Studies (14)].
8.2 Lactation
Risk Summary
Detectable amounts of progesterone have been identified in the milk of nursing mothers. The effect of this on the nursing infant has not been determined. A published study reported no adverse effects of progesterone on milk production or infant growth during the first postpartum year.
The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for ENDOMETRIN and any potential adverse effects on the breastfed child from ENDOMETRIN or from the underlying maternal condition.
8.4 Pediatric Use
The safety and effectiveness of ENDOMETRIN in pediatric patients have not been established.
8.5 Geriatric Use
Clinical studies of ENDOMETRIN did not include women 65 years of age and older. ENDOMETRIN is not indicated for use in this population.
8.6 Body Mass Index
The safety and efficacy of ENDOMETRIN in women with a body mass index (BMI) >34 kg/m2 has not been studied.
8.7 Hepatic Impairment
ENDOMETRIN is contraindicated in women with hepatic adenoma, hepatocellular carcinoma, acute hepatitis, or severe (decompensated) cirrhosis.
10 OVERDOSAGE
Treatment of overdosage consists of discontinuation of ENDOMETRIN together with institution of appropriate symptomatic and supportive care. If an overdose of ENDOMETRIN occurs, consider contacting the Poison Help line (1-800-222-1222) or a medical toxicologist for additional overdose management recommendations.
11 DESCRIPTION
ENDOMETRIN (progesterone) vaginal insert contains micronized progesterone. ENDOMETRIN is supplied with polyethylene vaginal applicators.
The active ingredient, progesterone, is present (100 mg) along with inactive ingredients. The chemical name for progesterone is pregn-4-ene-3,20-dione, its empirical formula is C21H30O2, its molecular weight is 314.5. Progesterone exists in two polymorphic forms. The form used in ENDOMETRIN, the alpha-form, has a melting point of 127-131°C.
The structural formula is:
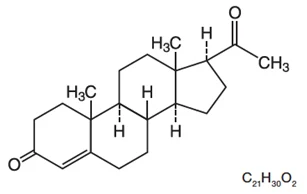
Each ENDOMETRIN vaginal insert delivers 100 mg of progesterone in a base containing lactose monohydrate, polyvinylpyrrolidone, adipic acid, sodium bicarbonate, sodium lauryl sulfate, magnesium stearate, pregelatinized starch, and colloidal silicon dioxide.
12 CLINICAL PHARMACOLOGY
12.1 Mechanism of Action
Progesterone is a naturally occurring steroid that is secreted by the ovary, placenta, and adrenal gland. In the presence of adequate estrogen, progesterone transforms a proliferative endometrium into a secretory endometrium. Progesterone is necessary to increase endometrial receptivity for implantation of an embryo. Once an embryo is implanted, progesterone acts to maintain a pregnancy.
12.2 Pharmacodynamics
The exposure-response relationship and time course of pharmacodynamic response for the safety and effectiveness of ENDOMETRIN have not been fully characterized.
12.3 Pharmacokinetics
Absorption
Progesterone serum concentrations increased following the administration of the ENDOMETRIN vaginal insert in 12 healthy premenopausal females. After 5 days of dosing, steady-state progesterone concentrations were attained within approximately 1 day after initiation of ENDOMETRIN treatment. Both ENDOMETRIN dosing regimens provided average serum progesterone concentrations that exceeded 10 ng/mL on Day 5. The pharmacokinetic results are summarized in Table 2.
Table 2: Mean (±Standard Deviation) Serum Progesterone Pharmacokinetic Parameters after ENDOMETRIN Vaginal Administration
| Pharmacokinetic Parameter (unit) | ENDOMETRIN 100 mg twice daily (N=6) | ENDOMETRIN 100 mg three times daily (N=6) |
| One Day of Dosing | ||
| Cmax (ng/mL) | 17 ± 6.5 | 19.8 ± 7.2 |
| Tmax (hr) | 24 ± 0 | 17.3 ± 7.4 |
| AUC0-24 (ng•hr/mL) | 217 ± 113 | 284 ± 143 |
| Day 5 of Multiple Dosing | ||
| Cmax (ng/mL) | 18.5 ± 5.5 | 24.1 ± 5.6 |
| Tmax (hr) | 18 ± 9.4 | 18 ± 9.4 |
| Cmin (ng/mL) | 8.9 ± 4.5 | 10.9 ± 6.7 |
| Cavg (ng/ml) | 14 ± 4.8 | 15.9 ± 4.3 |
| AUC0-24 (ng•hr/mL) | 327 ± 127 | 436 ± 106 |
Cmax Maximum progesterone serum concentration. Tmax Time to maximum progesterone serum concentration. Cavg Average progesterone serum concentration. AUC0-24 Area under the drug concentration versus time curve from 0-24 hours post dose. Cmin Minimum progesterone serum concentration. | ||
Distribution
Progesterone is approximately 96% to 99% bound to serum proteins, primarily to serum albumin and corticosteroid binding globulin.
Elimination
Metabolism: Progesterone is metabolized primarily by the liver, largely to pregnanediols and pregnanolones. Pregnanediols and pregnanolones are conjugated in the liver to glucuronide and sulfate metabolites. Progesterone metabolites that are excreted in the bile may be deconjugated and may be further metabolized in the gut via reduction, dehydroxylation, and epimerization.
Excretion: Progesterone undergoes renal and biliary elimination. Following injection of labeled progesterone, 50-60% of the excretion of metabolites occurs via the kidney; approximately 10% occurs via the bile and feces. Overall recovery of the labeled material accounts for 70% of an administered dose. Only a small portion of unchanged progesterone is excreted in the bile.
13 NONCLINICAL TOXICOLOGY
13.1 Carcinogenesis, Mutagenesis, Impairment of Fertility
Nonclinical toxicity studies to determine the potential of ENDOMETRIN to cause carcinogenicity or mutagenicity have not been performed. The effect of ENDOMETRIN on fertility has not been evaluated in animals.
14 CLINICAL STUDIES
A randomized, open-label, active-controlled study evaluated the efficacy of two different daily dosing regimens of ENDOMETRIN (100 mg twice daily administered vaginally or 100 mg three times daily administered vaginally for 10 weeks) and a vaginally administered active comparator to support embryo implantation (as part of an Assisted Reproductive Technology (ART) treatment program) in infertile women less than 35 years of age by supplementation of corpus luteal function and to maintain pregnancy after implantation up to 10 weeks.
Efficacy of the two ENDOMETRIN regimens was assessed by an endpoint of pregnancies, defined as the presence of at least one fetal heartbeat seen on ultrasound at 6 weeks post-embryo transfer. The study included 808 infertile women who were treated with one of the two ENDOMETRIN dosing regimens (75% White; 10% Hispanic, 5% Black, 5% Asian, and 5% other races) between 19 and 42 years of age (mean age 33 years old) who had a body mass index <34 kg/m2 at screening.
The ongoing pregnancy rates for infertile women treated with both dosing regimens of ENDOMETRIN were non-inferior (lower bounds of the 95% confidence interval of the difference between the two ENDOMETRIN dosing regimens and the active comparator excluded a difference greater than 10%) to the pregnancy rate for infertile women treated with the active comparator. The results of ENDOMETRIN treatment groups (but not the active comparator group) in this study are shown in Table 3.
Table 3: Pregnancy Rates* in Infertile Women Who Received ENDOMETRIN to Support Embryo Implantation by Supplementation of Corpus Luteal Function as Part of an ART Program
ENDOMETRIN 100 mg twice daily for 10 weeks | ENDOMETRIN 100 mg three times daily for 10 weeks | |
| Number of subjects | 404 | 404 |
| Pregnancy: n (%) | 156 (39%) | 171 (42%) |
| 95% Confidence Interval of pregnancy rate | [33.8, 43.6] | [37.5, 47.3] |
Pregnancy rate percentage difference between each ENDOMETRIN treatment group and the active comparator | -3.6% | 0.1% |
| 95% Confidence Interval for difference vs active comparator | [-10.3, 3.2] | [-6.7, 6.9] |
| *Pregnancy was defined as the presence of at least one fetal heartbeat seen on ultrasound at 6 weeks post-embryo transfer. | ||
Subjects participating in the study were stratified at randomization by age and ovarian reserve (as measured by serum FSH levels). The pregnancy rates for these subgroups in the ENDOMETRIN treatment groups (but not the active comparator group) are shown in Table 4. In subjects:
- Under the age of 35 or with serum FSH levels less than 10 IU/L, results from both ENDOMETRIN dosing regimens were non-inferior to the results from the active comparator with respect to pregnancy rates.
- Age 35 and older and in subjects with serum FSH levels between 10 and 15 IU/L, the results with respect to ongoing pregnancy rates for both ENDOMETRIN dosing regimens did not reach the criteria for non-inferiority.
Subjects who became pregnant received study medication for a total of 10 weeks. Patients over 34 kg/m2 were not studied; thus, the efficacy of ENDOMETRIN in these patients is unknown.
Table 4: Pregnancy Rates in Age- and Ovarian Reserve-Defined Subgroups Who Received ENDOMETRIN for Luteal Supplementation and Early Pregnancy While in an ART Program
ENDOMETRIN 100 mg twice daily | ENDOMETRIN 100 mg three times daily | |
Subjects age < 35 years (N) Pregnancy: n (%) Pregnancy rate percentage difference between ENDOMETRIN and the active comparator 95% Confidence Interval for difference vs. active comparator | 247 111 (45%) 0.5% [-8.3, 9.3] | 247 117 (47%) 2.9% [-5.9, 11.7] |
Subjects 35-42 years of age (N) Pregnancy: n (%) Pregnancy rate percentage difference between ENDOMETRIN and the active comparator 95% Confidence Interval for difference vs. active comparator | 157 45 (28%) -10.1% [-20.3, 0.3] | 157 54 (34%) -4.4% [-14.9, 6.3] |
Subjects with FSH < 10 IU/L (N) Ongoing pregnancy: n (%) Pregnancy rate percentage difference between ENDOMETRIN and the active comparator 95% Confidence Interval for difference vs. the active comparator | 350 140 (40%) -2.0% [-9.3, 5.3] | 347 150 (43%) 1.2% [-6.1, 8.5] |
Subjects with FSH between 10 and 15 IU/L (N) Pregnancy: n (%) Pregnancy rate percentage difference between ENDOMETRIN and the active comparator 95% Confidence Interval for difference vs. active comparator | 46 16 (35%) -12.2% [-31.0, 7.7] | 51 20 (39%) -7.7% [-26.6, 11.6] |
16 HOW SUPPLIED/STORAGE AND HANDLING
Each ENDOMETRIN vaginal insert is a white to off-white oblong-shaped debossed with “FPI” on one side and “100” on the other side. Each vaginal insert, 100 mg, is packed individually in a sealed foil pouch. These pouches are available in cartons packed:
- 21 vaginal inserts with 21 disposable vaginal applicators (NDC 55566-6500-3)
Store at 20 - 25˚C (68 - 77˚F); excursions permitted between 15 - 30°C (59 - 86°F).
17 PATIENT COUNSELING INFORMATION
Advise the patient to read the FDA-Approved patient labeling (Patient Information).
Vaginal Bleeding
Inform patients of the importance of reporting irregular vaginal bleeding to their health care provider as soon as possible.
Common Adverse Reactions with Progesterone
Inform patients of the possible adverse reactions of ENDOMETRIN therapy such as headaches, breast tenderness, bloating, mood swings, irritability, and drowsiness.
Coadministration of Other Vaginal Products
Inform patients that ENDOMETRIN is not recommended for use with other vaginal products.
Manufactured for:
Ferring Pharmaceuticals Inc
Parsippany, NJ 07054
XXXXXXXXXX