


Prescribing information (package insert) - Egrifta Sv
1 INDICATIONS AND USAGE
EGRIFTA WR is indicated for the reduction of excess abdominal fat in HIV-infected adult patients with lipodystrophy.
Limitations of Use:
- Long-term cardiovascular safety of EGRIFTA WR has not been established. Consider risk/benefit of continuation of treatment in patients who have not had a reduction in visceral adipose tissue.
- EGRIFTA WR is not indicated for weight loss management as it has a weight neutral effect.
- There are no data to support improved compliance with anti-retroviral therapies in HIV-positive patients taking EGRIFTA WR.
2 DOSAGE AND ADMINISTRATION
2.1 Recommended Dosage and Administration Instructions
- There are two EGRIFTA formulations (EGRIFTA WR and EGRIFTA SV) with different recommended dosages. These two formulations and strengths have differences in the dosage, the number of vials required to prepare a dose, reconstitution instructions, and storage requirements.
- EGRIFTA WR and EGRIFTA SV are not substitutable.
- The dosage and administration recommendations in this prescribing information only apply to EGRIFTA WR (tesamorelin) for injection 11.6 mg per vial formulation. For dosage and administration recommendations for tesamorelin for injection 2 mg per vial formulation, see the EGRIFTA SV prescribing information.
- The recommended dosage of EGRIFTA WR is 1.28 mg subcutaneously once daily.
- Inject EGRIFTA WR into the abdomen. Rotate injection sites to different areas of the abdomen [see Warnings and Precautions (5.6)]. Do not inject into scar tissue, bruises or the navel.
2.2 Reconstitution Procedure
- Instruct patients to read the Instructions for Use enclosed in the EGRIFTA WR Injection Box.
- Use only the diluent provided, Bacteriostatic Water for Injection, to reconstitute EGRIFTA WR.
- Reconstitute 1 vial of EGRIFTA WR lyophilized powder with 1.3 mL of diluent (8 mg per mL). Move the vial in a circle (swirl) to mix all the powder and liquid. Do not shake.
- Parenteral drug products should be inspected visually for particulate matter and discoloration prior to administration, whenever solution and container permit. EGRIFTA WR is a clear, colorless solution. Do not use if solid particles appear or if the solution is cloudy or colored.
- One reconstituted EGRIFTA WR vial provides daily doses for 7 consecutive days. One dose of EGRIFTA WR is 1.28 mg in 0.16 mL of the reconstituted solution.
- Store reconstituted EGRIFTA WR at room temperature at 20°C to 25°C (68°F to 77°F). Discard unused solution of EGRIFTA WR 7 days after mixing. Do not freeze.
3 DOSAGE FORMS AND STRENGTHS
For injection: 11.6 mg of tesamorelin as a white to off-white lyophilized powder in a single-patient-use vial for reconstitution and a diluent of 30 mL of multiple-dose Bacteriostatic Water for Injection, USP.
4 CONTRAINDICATIONS
EGRIFTA WR is contraindicated in:
- Patients with disruption of the hypothalamic-pituitary axis due to hypophysectomy, hypopituitarism, pituitary tumor/surgery, head irradiation or head trauma.
- Patients with active malignancy. Any preexisting malignancy should be inactive and its treatment complete prior to instituting therapy [see Warnings and Precautions (5.1)].
- Patients with known hypersensitivity to tesamorelin or the excipients in EGRIFTA WR [see Warnings and Precautions (5.5)].
- Pregnant women because modifying visceral adipose tissue offers no benefit in a pregnant woman and could result in fetal harm [see Use in Specific Populations (8.1)].
5 WARNINGS AND PRECAUTIONS
5.1 Increased Risk of Neoplasms
New Malignancy
Carefully consider the decision to start treatment with EGRIFTA WR based on the increased background risk of malignancies in HIV-positive patients.
Active Malignancy
EGRIFTA WR induces the release of endogenous growth hormone (GH), a known growth factor. Do not treat patients with active malignancy with EGRIFTA WR [see Contraindications (4)].
History of Malignancy
For patients with a history of non-malignant neoplasms, initiate EGRIFTA WR therapy after careful evaluation of the potential benefit of treatment. For patients with a history of treated and stable malignancies, initiate EGRIFTA WR therapy only after careful evaluation of the potential benefit of treatment relative to the risk of re-activation of the underlying malignancy. Discontinue EGRIFTA WR if there is any evidence of recurrent malignancy.
5.2 Elevated IGF-1 Levels
EGRIFTA WR stimulates GH production and increases serum IGF-1, a growth factor. The effects of prolonged elevations in IGF-1 levels are unknown. Monitor IGF-1 levels during EGRIFTA WR therapy. Consider discontinuing EGRIFTA WR in patients with persistent elevations of IGF-1 levels (e.g., >3 SDS), particularly if the efficacy response is not robust.
Among patients who received EGRIFTA for 26 weeks, 47% had IGF-1 levels greater than 2 standard deviation scores (SDS), and 36% had SDS >3, with this effect seen as early as 13 weeks of treatment. Among those patients who remained on EGRIFTA for a total of 52 weeks, at the end of treatment, 34% had IGF-1 SDS >2 and 23% had IGF-1 SDS >3.
5.3 Fluid Retention
Fluid retention may occur during EGRIFTA WR therapy and is thought to be related to the induction of GH secretion. This manifests as increased tissue turgor and musculoskeletal discomfort resulting in adverse reactions (e.g. edema, arthralgia, and carpal tunnel syndrome) which are either transient or resolve with discontinuation of treatment.
5.4 Glucose Intolerance or Diabetes Mellitus
EGRIFTA WR treatment can result in glucose intolerance. During clinical trials, the percentages of patients with elevated HbA1c (≥ 6.5%) from baseline to Week 26 were 5% and 1% in the EGRIFTA and placebo groups, respectively. An increased risk of developing diabetes with EGRIFTA (HbA1c level ≥ 6.5%) relative to placebo was observed [intent-to-treat hazard odds ratio of 3.3 (CI 1.4, 9.6)].
Evaluate glucose status prior to initiating EGRIFTA WR. Monitor all patients treated with EGRIFTA WR periodically to diagnose those who develop impaired glucose tolerance or diabetes. If patients treated with EGRIFTA WR develop glucose intolerance or diabetes, consider discontinuing EGRIFTA WR in patients who do not show a clear efficacy response.
EGRIFTA WR increases IGF-1, monitor patients with diabetes who are receiving treatment with TESAMORELIN for injection at regular intervals for potential development or worsening of retinopathy.
5.5 Hypersensitivity Reactions
Hypersensitivity reactions occurred in 4% of patients treated with EGRIFTA in clinical trials. Reactions included pruritus, erythema, flushing, urticaria, and rash. In cases of suspected hypersensitivity reactions, advise patients to seek prompt medical attention and immediately discontinue treatment with EGRIFTA WR.
5.6 Injection Site Reactions
EGRIFTA WR treatment may cause injection site reactions, including injection site erythema, pruritus, pain, irritation, and bruising. The incidence of injection site reactions was 25% in EGRIFTA treated patients and 14% in placebo-treated patients during the first 26 weeks of treatment in clinical trials. Rotate injection sites to different areas of the abdomen to decrease injection site reactions [see Dosage and Administration (2.1)].
5.7 Increased Mortality in Patients with Acute Critical Illness
Increased mortality in patients with acute critical illness due to complications following open heart surgery, abdominal surgery or multiple accidental trauma, or those with acute respiratory failure has been reported after treatment with pharmacologic amounts of growth hormone. EGRIFTA WR is a growth hormone-releasing hormone (GHRH) and since it stimulates growth hormone production, consider discontinuing EGRIFTA WR in critically ill patients.
6 ADVERSE REACTIONS
The following important adverse reactions are also described elsewhere in the labeling:
- Increased risk of neoplasms [see Warnings and Precautions (5.1)]
- Elevated IGF-1 levels [see Warnings and Precautions (5.2)]
- Fluid retention [see Warnings and Precautions (5.3)]
- Glucose intolerance or diabetes mellitus [see Warnings and Precautions (5.4)]
- Hypersensitivity reactions [see Warnings and Precautions (5.5)]
- Injection site reactions [see Warnings and Precautions (5.6)]
6.1 Clinical Trial Experience
Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice.
The safety of EGRIFTA WR (11.6 mg/vial formulation) has been established based on clinical trials conducted with EGRIFTA (1 mg/vial formulation). Adverse reactions for the 1.28 mg dose (11.6 mg/vial formulation) of EGRIFTA WR are expected to be similar to those observed with the 2 mg dose (1 mg/vial formulation) of EGRIFTA [see Clinical Pharmacology (12.3)].
Seven hundred and forty (740) HIV-infected patients with lipodystrophy and excess abdominal fat were treated with EGRIFTA in clinical trials; of these, 543 received EGRIFTA during the initial 26-week placebo-controlled phase.
The most commonly reported adverse reactions were hypersensitivity reactions (e.g., rash, urticaria), edema-related reactions (e.g., arthralgia, extremity pain, peripheral edema, and carpal tunnel syndrome), hyperglycemia, and injection site reactions (injection site erythema, pruritus, pain, urticaria, irritation, swelling, and hemorrhage).
Adverse reactions that occurred more frequently with EGRIFTA relative to placebo and had an incidence ≥1% during the first 26 weeks across all studies are presented in Table 1.
Table 1. Adverse Reactions Reported in ≥ 1% and More Frequent in EGRIFTA–treated than Placebo Patients during the 26-Week Phase (Combined Studies)
| * Injection site reaction includes: Injection site erythema, Injection site pruritus, Injection site rash, Injection site urticaria, Injection site pain, Injection site swelling, Injection site irritation, Injection site hemorrhage. | ||
| Preferred Term | Placebo (N=263) | EGRIFTA (N=543) |
Injection site reaction* Arthralgia Pain in extremity Myalgia Edema peripheral Paresthesia Hypoesthesia Rash Dyspepsia Musculoskeletal pain Pain Pruritus Vomiting Musculoskeletal stiffness Blood creatine phosphokinase increased Carpal tunnel syndrome Joint swelling Muscle strain Night sweats Palpitations | 6 11 5 2 2 2 2 2 1 1 1 1 0 0 0 0 0 0 0 0 | 17 13 6 6 6 5 4 4 2 2 2 2 3 2 1 1 1 1 1 1 |
In the EGRIFTA clinical trials, mean baseline HbA1c was 5.3% among patients in both the EGRIFTA and placebo groups. Patients receiving EGRIFTA had an increased risk of developing diabetes (HbA1c level ≥ 6.5%) compared with placebo (5% vs. 1%), with a hazard ratio of 3.3 (CI 1.4, 9.6).
7 DRUG INTERACTIONS
7.1 Cytochrome P450-Metabolized Drugs
Co-administration of tesamorelin with simvastatin, a CYP3A substrate had no significant impact on the pharmacokinetics profiles of simvastatin in healthy subjects [see Clinical Pharmacology (12.3)].
EGRIFTA WR stimulates GH production. Published data indicate that GH may modulate cytochrome P450 (CYP450) mediated antipyrine clearance. These data suggest that GH may alter the clearance of compounds known to be metabolized by CYP450 liver enzymes (e.g., corticosteroids, sex steroids, anticonvulsants, and cyclosporine). Monitor patients for potential interactions when administering EGRIFTA WR in combination with other drugs known to be metabolized by CYP450 liver enzymes.
7.2 Glucocorticoids
GH inhibits 11β-hydroxysteroid dehydrogenase type 1 (11βHSD-1), a microsomal enzyme required for conversion of cortisone to its active metabolite, cortisol, in hepatic and adipose tissue. EGRIFTA WR stimulates GH production; therefore, patients receiving glucocorticoid replacement for previously diagnosed hypoadrenalism may require an increase in maintenance or stress doses following initiation of EGRIFTA WR. Patients treated with cortisone acetate and prednisone may be affected more than others because conversion of these drugs to their biologically active metabolites is dependent on the activity of 11βHSD-1.
8 USE IN SPECIFIC POPULATIONS
8.1 Pregnancy
Risk Summary
EGRIFTA WR is contraindicated in pregnant women because modifying visceral adipose tissue offers no benefit in pregnant women and could result in fetal harm [see Clinical Considerations and Contraindications (4)]. Administration of tesamorelin acetate to rats during organogenesis resulted in hydrocephaly in offspring at a dose of approximately two and four times the clinical dose, based on measured drug exposure (AUC). If EGRIFTA WR is used during pregnancy, or if the patient becomes pregnant while taking it, discontinue EGRIFTA WR.
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Clinical Considerations
Disease-associated maternal and/or embryo/fetal risk
During pregnancy, visceral adipose tissue increases due to normal metabolic and hormonal changes. Modifying pregnancy-associated physiologic changes in visceral adipose tissue with EGRIFTA WR offers no known benefit and could result in fetal harm.
Data
Animal Data
Tesamorelin acetate administration to rats during organogenesis and lactation resulted in hydrocephaly in offspring at a dose of approximately two and four times the clinical dose, respectively, based on measured drug exposure (AUC). Actual animal dose was 1.2 mg/kg. During organogenesis, lower doses approximately 0.1 to 1-times the clinical dose caused delayed skull ossification in rats. Actual animal doses were 0.1 to 0.6 mg/kg. No adverse developmental effects occurred in rabbits using doses up to approximately 500 times the clinical dose.
8.2 Lactation
Risk Summary
The Centers for Disease Control and Prevention recommend that HIV-infected mothers in the United States not breastfeed their infants to avoid risking postnatal transmission of HIV-1 infection. There are no data on the presence of tesamorelin in human milk, the effects on the breastfed child, or the effects on milk production. Because of both the potential for (1) HIV-1 infection transmission (in HIV-negative infants), (2) developing viral resistance (in HIV-positive patients), and (3) any possible adverse effects of tesamorelin, mothers should not breastfeed if they receive EGRIFTA WR.
8.4 Pediatric Use
The safety and effectiveness of EGRIFTA WR in pediatric patients have not been established.
In pediatric patients with open epiphyses, treatment with EGRIFTA WR may result in linear growth acceleration and excessive growth. EGRIFTA WR is not indicated for use in pediatric patients with open or closed epiphyses.
8.5 Geriatric Use
There is no information on the use of EGRIFTA WR in patients greater than 65 years of age.
11 DESCRIPTION
Tesamorelin is a human growth hormone-releasing factor (GRF) analog produced synthetically. It is comprised of the 44 amino acid sequence of human GRF and a hexenoyl moiety, a C6 chain with a double bond at position 3, attached to the tyrosine residue at the N-terminal part of the molecule. Tesamorelin is prepared as an acetate salt. The molecular formula of tesamorelin acetate is C221H366N72O67S • x C2H4O2 (x ≈ 7) and its molecular weight (as free base equivalent) is 5135.9 Da. The structural formula of tesamorelin acetate is:

EGRIFTA WR (tesamorelin) for injection is a sterile, white to off-white, preservative-free lyophilized powder for subcutaneous injection. Each single-patient-use vial of EGRIFTA WR contains tesamorelin 11.6 mg (equivalent to approximately 11.9 mg of tesamorelin acetate) and the following inactive ingredients: 145 mg hydroxypropyl betadex, 43.5 mg mannitol. Hydrochloric acid and/or sodium hydroxide may be used to adjust the pH. The pH of EGRIFTA WR is between 4.5 and 7.4. After reconstitution with 1.3 mL of Bacteriostatic Water for Injection, USP, resultant concentration is 8 mg/mL and the solution is clear and colorless. Bacteriostatic Water for Injection, USP contains benzyl alcohol as preservative.
12 CLINICAL PHARMACOLOGY
12.1 Mechanism of Action
In vitro, tesamorelin binds and stimulates human GRF receptors with similar potency as the endogenous GRF [see Clinical Pharmacology (12.2)].
Growth hormone-releasing factor (GHRF), also known as growth hormone-releasing hormone (GHRH), is a hypothalamic peptide that acts on the pituitary somatotroph cells to stimulate the synthesis and pulsatile release of endogenous growth hormone (GH), which is both anabolic and lipolytic. GH exerts its effects by interacting with specific receptors on a variety of target cells, including chondrocytes, osteoblasts, myocytes, hepatocytes, and adipocytes, resulting in a host of pharmacodynamic effects. Some, but not all these effects, are primarily mediated by IGF-1 produced in the liver and in peripheral tissues.
12.2 Pharmacodynamics
Tesamorelin stimulates growth hormone secretion, and subsequently increases IGF-1 and IGFBP-3 levels. No clinically significant changes in the levels of other pituitary hormones, including thyroid-stimulating hormone (TSH), luteinizing hormone (LH), adrenocorticotropic hormone (ACTH) and prolactin, were observed in patients receiving EGRIFTA in clinical trials.
12.3 Pharmacokinetics
Absorption
The absolute bioavailability of tesamorelin after subcutaneous administration of a 2 mg dose of EGRIFTA (1 mg/vial formulation) was determined to be less than 4% in healthy adult subjects.
Single and multiple dose pharmacokinetics have been characterized in healthy subjects and HIV-infected patients without lipodystrophy using a 2 mg dose of EGRIFTA (1 mg/vial formulation). Tesamorelin mean extent of absorption (AUC) was 34% higher in HIV-infected patients than healthy subjects. Tesamorelin peak plasma concentration (Cmax) was similar in HIV-infected patients and healthy subjects. The median peak plasma tesamorelin concentration (Tmax) was 0.15 h in both populations.
Following single dose of subcutaneous administration of 1.28 mg of EGRIFTA WR (11.6 mg/vial formulation) in healthy subjects, the mean [coefficient of variation (CV)] AUC0-inf was 1172 (48%) pg.h/mL. The mean (CV) Cmax value was 3831 (40%) pg/mL and the median Tmax was 0.15 h.
The systemic exposure (Cmax and AUCs) of tesamorelin is similar between the 1.28 mg dose of EGRIFTA WR (11.6 mg/vial formulation) and the 2 mg dose of EGRIFTA (1 mg/vial formulation).
Distribution
The mean volume of distribution (±SD) of tesamorelin following a single subcutaneous administration of the 1.28 mg dose of EGRIFTA WR (11.6 mg/vial formulation) was 4.8 ± 1.9 L/kg in healthy subjects.
Metabolism
No formal metabolism studies have been performed in humans.
Elimination
Mean elimination half-life (t1/2) of tesamorelin was 11 minutes in healthy subjects after single dose subcutaneous administration of the 1.28 mg of EGRIFTA WR (11.6 mg/vial formulation).
Specific Populations
Pharmacokinetics of tesamorelin in patients with renal or hepatic impairment, in pediatric patients, or in elderly patients has not been established.
Drug Interactions
Simvastatin
The effect of multiple dose administration of EGRIFTA on the pharmacokinetics of simvastatin and simvastatin acid was evaluated in healthy subjects. Co-administration with simvastatin (a CYP3A substrate) resulted in 8% decrease in extent of absorption (AUCinf) and 5% increase in rate of absorption (Cmax) of simvastatin. For simvastatin acid there was a 15% decrease in AUCinf and 1% decrease in Cmax [see Drug Interactions (7.1)].
Ritonavir
The effect of multiple dose administration of EGRIFTA on the pharmacokinetics of ritonavir was evaluated in healthy subjects. Co-administration with ritonavir resulted in 9% decrease in AUCinf and 11% decrease in Cmax of ritonavir [see Drug Interactions (7.1)].
12.6 Immunogenicity
The observed incidence of anti-drug antibodies is highly dependent on the sensitivity and specificity of the assay. Differences in assay methods preclude meaningful comparisons of the incidence of anti-drug antibodies in the studies described below with the incidence of the anti-drug antibodies in other studies, including those of EGRIFTA WR or other growth hormone-releasing factor analog.
In the clinical trials with the EGRIFTA 1 mg/vial formulation, anti-tesamorelin IgG antibodies were detected in 50% of patients who received EGRIFTA for 26 weeks and 47% of patients who received EGRIFTA for 52 weeks. In the subset of patients with hypersensitivity reactions, anti-tesamorelin IgG antibodies were detected in 85%. Cross-reactivity to endogenous growth hormone-releasing hormone (GHRH) was observed in approximately 60% of patients who developed anti-tesamorelin antibodies. Patients with and without anti-tesamorelin IgG antibodies had similar mean reductions in visceral adipose tissue (VAT) and IGF-1 response. In a group of patients who had antibodies to tesamorelin after 26 weeks of treatment (56%) and were re-assessed 6 months later, after stopping EGRIFTA treatment, 18% were still antibody positive.
Neutralizing antibodies to tesamorelin and human GHRH (hGHRH) were detected in vitro at Week 52 in 10% and 5% of EGRIFTA-treated patients, respectively. Changes in VAT and IGF-1 levels in patients with or without in vitro neutralizing antibodies were comparable.
13 NONCLINICAL TOXICOLOGY
13.1 Carcinogenesis, Mutagenesis, Impairment of Fertility
Life-time carcinogenicity studies in rodents have not been conducted with tesamorelin acetate. No potential mutagenicity of tesamorelin acetate was revealed in a battery of tests including induction of gene mutations in bacteria (the Ames test), gene mutations in mammalian cells grown in vitro (hamster CHOK1 cells), and chromosomal damage in intact animals (bone marrow cells in mice). There was no effect on fertility in male or female rats following administration of tesamorelin acetate at doses up to 0.6 mg/kg (approximately equal to clinical exposure) for 28 days in males or 14 days in females.
14 CLINICAL STUDIES
The safety and effectiveness of EGRIFTA WR (11.6 mg/vial formulation) has been established based on adequate and well controlled studies with EGRIFTA (1 mg/vial formulation), as well as a demonstration of comparable bioavailability between the 1.28 mg EGRIFTA WR dose (11.6 mg/vial formulation) and the 2 mg EGRIFTA dose (1 mg/vial formulation) [see Clinical Pharmacology (12.3)] .
Two multicenter, randomized, double-blind, placebo-controlled studies were conducted in HIV-infected patients with lipodystrophy and excess abdominal fat (abdominal lipohypertrophy). Study 1 and Study 2 consisted of a 26-week Main Phase and a 26-week Extension Phase, respectively. Main inclusion criteria were age 18 to 65 years, a waist circumference ≥95 cm (37.4 inches) and a waist-to-hip ratio ≥0.94 for men and ≥94 cm (37.0 inches) and ≥0.88 for women, respectively, and fasting blood glucose (FBG) <150 mg/dL (8.33 mmol/L). Main exclusion criteria included BMI ≤ 20 kg/m2, type 1 diabetes mellitus, type 2 diabetes mellitus, previous treatment with insulin or with oral hypoglycemic or insulin-sensitizing agents, history of malignancy, and hypopituitarism. Patients were on a stable anti-retroviral regimen for at least 8 weeks prior to randomization. Patients meeting the inclusion/exclusion criteria were randomized in a 2:1 ratio to receive a 2 mg dose of EGRIFTA (1 mg/vial formulation) or placebo subcutaneously daily for 26 weeks. The primary efficacy assessment for each of these studies was the percent change from baseline to Week 26 in visceral adipose tissue (VAT), as assessed by computed tomography (CT) scan at L4-L5 vertebral level. Secondary endpoints included changes from baseline in patient-reported outcomes related to body image, triglycerides, ratio of total cholesterol to HDL cholesterol, IGF-1 levels, and safety parameters. Other endpoints included changes from baseline in waist circumference, abdominal subcutaneous tissue (SAT), trunk fat, and lean body mass. In both studies, EGRIFTA-treated patients completing the 26-week treatment period were re-randomized to blinded therapy with either daily placebo or a 2 mg dose of EGRIFTA (1 mg/vial formulation) for an additional 26-week treatment period (Extension Phase) in order to assess maintenance of VAT reduction and to gather long-term safety data. For inclusion in the Extension Phase studies, subjects must have completed the Main Phase with FBG ≤ 150 mg/dL.
Main Phase (Baseline to Week 26):
Study 1 (NCT 00123253)
This study randomized 412 HIV-infected patients with lipodystrophy and excess abdominal fat to receive either a 2 mg dose of EGRIFTA (1 mg/vial formulation) (N=273) or placebo (N=137). At baseline for the two groups combined, mean age was 48 years; 86% were male; 75% were white, 14% were Black/African American, and 8% were Hispanic; mean weight was 90 kg; mean BMI was 29 kg/m2; mean waist circumference was 104 cm; mean hip circumference was 100 cm; mean VAT was 176 cm2; mean CD4 cell count was 606 cells/mm3; 69% had undetectable viral load (<50 copies/mL); and 33.7% randomized to EGRIFTA and 36.6% randomized to placebo had impaired glucose tolerance, while 5.6% randomized to EGRIFTA and 6.7% randomized to placebo had diet-controlled diabetes mellitus. The twenty-six week completion rate in Study 1 was 80%.
Study 2 (NCT 00435136)
This study randomized 404 HIV-infected patients with lipodystrophy and excess abdominal fat to receive either a 2 mg dose of EGRIFTA (1 mg/vial formulation) (N=270) or placebo (N=126). At baseline for the two groups combined, mean age was 48 years; 84% were male; 77% were white, 12% were Black/African American, and 9% were Hispanic; mean weight was 88 kg; mean BMI was 29 kg/m2; mean waist circumference was 105 cm; mean hip circumference was 100 cm; mean VAT was 189 cm2; mean CD4 cell count was 592 cells/mm3; 83% had undetectable viral load (<50 copies/mL); and 44% randomized to EGRIFTA and 40% randomized to placebo had impaired glucose tolerance, while 9% randomized to EGRIFTA and 10% randomized to placebo had diet-controlled type 2 diabetes mellitus. The twenty-six week completion rate in Study 2 was 74%.
Results for the Main Phases of Studies 1 and 2 are presented in Tables 2 and 3.
Table 2: Changes from Baseline to Week 26 in Visceral Adipose Tissue (cm2) by Treatment Group (Intent-To-Treat Population with Last Observation Carried Forward)
| Baseline data are expressed as mean (SD); Change refers to least-squares mean (LSM); CI: confidence interval. | |||||
| 1 Results derived from the statistical model: Ln(VAT Week 26/VAT Baseline) = Ln(VAT Baseline) + treatment group | |||||
| MAIN PHASE (Baseline-Week 26) | |||||
| Study 1 | Study 2 | ||||
2 mg EGRIFTA (1 mg/vial) (N=273) | Placebo (N=137) | 2 mg EGRIFTA (1 mg/vial) (N=270) | Placebo (N=126) | ||
| Baseline (cm2) | 178 (77) | 171 (77) | 186 (87) | 195 (95) | |
| Change (cm2) | -27 | 4 | -21 | -0 | |
| Mean treatment difference (95% CI) | -31 (-39,-24) | -21 (-29,-12) | |||
| Mean change (%)1 | -18 | 2 | -14 | -2 | |
| Mean treatment difference (95% CI)1 | -20 (-24, -15) | -12 (-16, -7) | |||
Table 3: Changes from Baseline to Week 26 in IGF-1, IGFBP-3, Weight, and Waist Circumference by Treatment Group (Intent-To-Treat Population with Last Observation Carried Forward)
| Baseline data are expressed as mean (SD); Change refers to least-squares mean (LSM); CI: confidence interval. | |||||
| MAIN PHASE (Baseline-Week 26) | |||||
| Study 1 | Study 2 | ||||
2 mg EGRIFTA (1 mg/vial) (N=273) | Placebo (N=137) | 2 mg EGRIFTA (1 mg/vial) (N=270) | Placebo (N=126) | ||
IGF-1 (ng/mL) | Baseline | 161 (59) | 168 (75) | 146 (66) | 149 (59) |
| Change | 107 | -15 | 108 | 3 | |
| Mean treatment difference (95% CI) | 122 (101, 141) | 105 (85, 126) | |||
IGFBP-3 (mg/L) | Baseline | 3 (1) | 3 (1) | 3 (1) | 3 (1) |
| Change | 0.4 | -0.2 | 0.8 | -0.0 | |
| Mean treatment difference (95% CI) | 0.6 (0.5, 0.8) | 0.8 (0.5, 1.0) | |||
| Weight (kg) | Baseline | 90 (14) | 90 (14) | 89 (14) | 87 (16) |
| Change | -0.4 | 0.0 | 0.5 | 0.3 | |
| Mean treatment difference (95% CI) | -0.4 (-1.3, 0.5) | 0.2 (-0.7, 1.3) | |||
| Waist circumference (cm) | Baseline | 104 (10) | 105 (9) | 105 (9) | 105 (9) |
| Change | -3 (5) | -1 (4) | -2 (5) | -1 (5) | |
| Mean treatment difference (95% CI) | -2 (-2.8, -0.9) | -1 (-2.5, -0.3) | |||
At Week 26, treatment with a 2 mg dose of EGRIFTA (1 mg/vial formulation) resulted in a reduction from baseline in mean trunk fat of 1.0 kg in Study 1 and 0.8 kg in Study 2, respectively (compared with an increase of 0.4 kg in Study 1 and of 0.2 kg in Study 2, respectively, in patients receiving placebo). Treatment with EGRIFTA resulted in an increase from baseline in mean lean body mass of 1.3 kg in Study 1 and of 1.2 kg in Study 2, respectively (compared with a decrease of 0.2 kg in Study 1 and of 0.03 kg in Study 2, respectively, in patients receiving placebo).
Patient Reported Outcomes
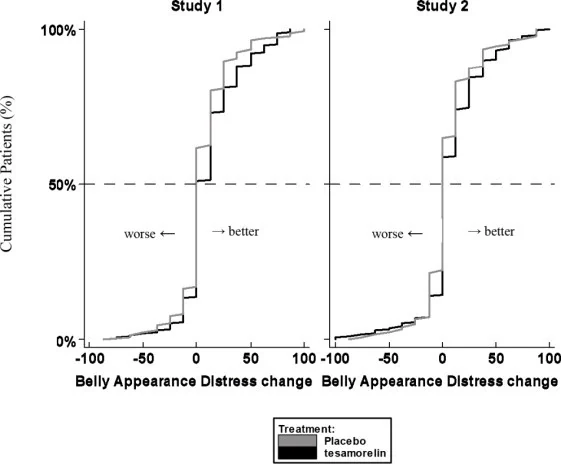
Patients rated the degree of distress associated with their belly appearance on a 9-point rating scale that was then transformed to a score from 0 (extremely upsetting and distressing) to 100 (extremely encouraging). A score of 50 indicated neutral (no feeling either way). A positive change from baseline score indicated improvement, i.e., less distress.
The cumulative distribution of response (change from baseline to 26 weeks) is shown in Figure 1 for both treatment groups. A curve shifted to the right on this scale indicates a greater percentage of patients reporting improvement.
Figure 1. Cumulative Distribution of Response for Belly Appearance Distress
Extension Phase (Weeks 26-52):
In the double-blind Extension Phase, patients on a 2 mg dose of EGRIFTA (1 mg/vial formulation) completing the 26-week Main Phase were re-randomized to receive a 2 mg dose of EGRIFTA (1 mg/vial formulation) or placebo.
Study 1 (NCT 00123253)
This study re-randomized 207 HIV-infected patients with lipodystrophy who completed a 2 mg dose of EGRIFTA (1 mg/vial formulation) treatment in the Main Phase to receive either EGRIFTA (N=154) or placebo (N=50) for an additional 26-week duration (3:1 randomization ratio). At baseline (Week 26) for the two groups combined, mean age was 48 years; 88% were male; 78% were white, 12% were Black/African American, and 8% were Hispanic; mean weight was 90 kg; mean BMI was 29 kg/m2; mean waist circumference was 102 cm; mean hip circumference was 100 cm; mean VAT was 145 cm2; mean CD4 cell count was 639 cells/mm3; 68% had undetectable viral load (<50 copies/mL); and for those EGRIFTA-treated patients completing the 26-week treatment period that were re-randomized to EGRIFTA (T-T group) or re-randomized to placebo, 37% and 32%, respectively, had impaired glucose tolerance, while 2% re-randomized to EGRIFTA and 6% re-randomized to placebo had diet-controlled type 2 diabetes mellitus. The completion rate for patients randomized into the extension phase of Study 1 was 83%.
Study 2 (NCT 00435136)
This study re-randomized 177 HIV-infected patients with lipodystrophy who completed EGRIFTA treatment in the Main Phase to receive either a 2 mg dose of EGRIFTA (1 mg/vial formulation) (N=92) or placebo (N=85) for an additional 26-week duration (1:1 randomization ratio). At baseline (Week 26) for the two groups combined, mean age was 48 years; 90% were male; 84% were white, 9% were Black/African American, and 7% were Hispanic; mean weight was 89 kg; mean BMI was 28 kg/m2; mean waist circumference was 105 cm; mean hip circumference was 100 cm; mean VAT was 172 cm2; mean CD4 cell count was 579 cells/mm3; 82% had undetectable viral load (<50 copies/mL); and for those EGRIFTA-treated patients completing the 26-week treatment period that were re-randomized to EGRIFTA (T-T group) or re-randomized to placebo, 49% and 51%, respectively, had impaired glucose tolerance, while 4% re-randomized to EGRIFTA and 13% re-randomized to placebo had diet-controlled diabetes mellitus. The completion rate for patients randomized into the extension phase of Study 2 was 81%.
Results for the Extension Phases of Studies 1 and 2 are presented in Tables 4 and 5.
Table 4: Changes from Week 26 Baseline to Week 52 in Visceral Adipose Tissue (cm2) by Treatment Group (Intent-To-Treat Population with Last Observation Carried Forward)
| Week 26 baseline data are expressed as mean (SD). Change refers to least-squares mean (LSM); CI: confidence interval. | ||||
| 1T-T = tesamorelin for Weeks 0-26 and tesamorelin for Weeks 26-52 | ||||
| 2T-P = tesamorelin for Weeks 0-26 and placebo for Weeks 26-52 | ||||
| 3Results derived from the statistical model: Ln(VAT Week 52/Week 26) = Ln(Week 26 VAT) + treatment group | ||||
| EXTENSION PHASE (Week 26-52) | ||||
| Study 1 | Study 2 | |||
T-T1 (Week 26-52) (N=154) | T-P2 (Week 26-52) (N=50) | T-T1 (Week 26-52) (N=92) | T-P2 (Week 26-52) (N=85) | |
| Week 26 (cm2) | 145 (72) | 144 (72) | 166 (89) | 177 (88) |
| Change (cm2) | 3 | 25 | -11 | 24 |
| Mean treatment difference (95% CI) | -22 (-34, -10) | -35 (-48, -22) | ||
| Mean change (%)3 | 0 | 22 | -5 | 16 |
| Mean treatment difference (95% CI)3 | -17 (-24, -10) | -18 (-24, -11) | ||
Figure 2 shows the percent change in VAT from baseline (Week 0) over time until 52 weeks in completer patients.
Figure 2. Percent Change from Baseline in VAT over Time
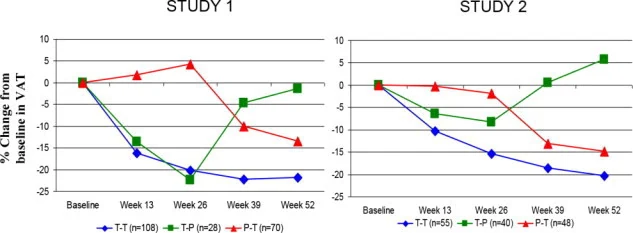
Data in Figure 2 are expressed as mean values. T-T (tesamorelin to tesamorelin) refers to the group of patients who received tesamorelin for Weeks 0-26 and were re-randomized to tesamorelin for Weeks 26-52. T-P (tesamorelin to placebo) refers to the group of patients who received tesamorelin for Weeks 0-26 and were re-randomized to placebo for Weeks 26-52. P-T (placebo to tesamorelin) refers to the group of patients who received placebo for Weeks 0-26 and were switched to tesamorelin (treated open label) for Weeks 26-52.
Table 5: Changes from Week 26 Baseline to Week 52 in IGF-1, IGFBP-3, Weight, and Waist Circumference by Treatment Group (Intent-To-Treat Population with Last Observation Carried Forward)
| Week 26 baseline data are expressed as mean (SD); Change refers to least-squares mean (LSM); CI: confidence interval. | |||||
| 1T-T = tesamorelin for Week 0-26 and tesamorelin for Week 26-52 | |||||
| 2T-P = tesamorelin for Week 0-26 and placebo for Week 26-52 | |||||
| EXTENSION PHASE (Weeks 26-52) | |||||
| Study 1 | Study 2 | ||||
T-T1 (Week 26-52) (N=154) | T-P2 (Week 26-52) (N=50) | T-T1 (Week 26-52) (N=92) | T-P2 (Week 26-52) (N=85) | ||
IGF-1 (ng/mL) | Week 26 | 291 (124) | 281 (105) | 280 (134) | 269 (110) |
| Change | -59 | -137 | -25 | -135 | |
| Mean treatment difference (95% CI) | 78 (50, 106) | 110 (87, 134) | |||
IGFBP-3 (mg/L) | Week 26 | 3 (1) | 3 (1) | 3 (1) | 3 (1) |
| Change | -0.2 | -0.5 | -0.3 | -0.9 | |
| Mean treatment difference (95% CI) | 0.3 (-0.0, 0.6) | 0.6 (0.3, 0.9) | |||
| Weight (kg) | Week 26 | 89 (14) | 92 (17) | 89 (13) | 90 (14) |
| Change | 0.2 | 0.6 | -0.5 | 0.1 | |
| Mean treatment difference (95% CI) | -0.4 (-2, 1) | -0.6 (-2, 1) | |||
| Waist circumference (cm) | Week 26 | 101 (10) | 102 (12) | 101 (9) | 103 (11) |
| Change | -0.2 | 2.4 | -1.1 | 0.2 | |
| Mean treatment difference (95% CI) | -2.6 (-4, -1) | -1.3 (-2, 0) | |||
Patients treated with a 2 mg dose of EGRIFTA (1 mg/formulation) for 52 weeks (T-T group) showed no change between Weeks 26 and 52 in mean trunk fat (increase of 0.1 kg in Study 1 and decrease of 0.5 kg in Study 2, respectively, compared with an increase of 1.4 kg in patients in the T-P group in Study 1 and an increase of 1.09 kg in Study 2, respectively) nor was there a change from Week 26 baseline in mean lean body mass (decrease of 0.1 kg in Study 1 and increase of 0.1 kg in Study 2, respectively, compared with a decrease of 1.8 kg in patients in the T-P group in Study 1 and a decrease of 1.7 kg in Study 2, respectively).
16 HOW SUPPLIED/STORAGE AND HANDLING
How Supplied
EGRIFTA WR (tesamorelin) for injection is supplied as a white to off-white lyophilized powder in a 11.6 mg single-patient-use vial with a 30 mL multiple-dose bottle of Bacteriostatic Water for Injection, USP, as diluent.
EGRIFTA WR (NDC 62064-381-04) is available in a package comprised of two boxes, containing 4 (four) 11.6 mg single-patient-use vials of EGRIFTA WR in the Medication Box and 1 (one) multiple-dose 30 mL bottles of Bacteriostatic Water for Injection, USP, diluent with a 28-day supply of disposable syringes, needles and alcohol swabs in the Injection Box.
Storage and Handling
Store EGRIFTA WR 11.6 mg vial at room temperature at 20°C to 25°C (68°F to 77°F) in the original box to protect from light; excursions permitted to 15°C to 30°C (59°F to 86°F) [See USP Controlled Room Temperature]. Store the Injection box (containing Bacteriostatic Water for Injection, syringes, needles and alcohol swabs) at room temperature at 20°C to 25°C (68°F to 77°F). Do not freeze.
17 PATIENT COUNSELING INFORMATION
Advise the patient to read the FDA-approved patient labeling (Patient Information and Instructions for Use).
Increased Risk of Malignancy
Inform patients about the increased background risk of malignancies in HIV-positive patients and for patients with a history of neoplasms, inform them about the risk of malignancy reoccurrence [see Warnings and Precautions (5.1)].
Elevated IGF-1 Levels
Inform patients that treatment with EGRIFTA WR increases IGF-1 levels and that they will need periodic monitoring of their IGF-1 levels [see Warnings and Precautions (5.2)].
Fluid Retention
Inform patients that treatment with EGRIFTA WR may cause fluid retention, resulting in adverse reactions including edema, arthralgia, and carpal tunnel syndrome [see Warnings and Precautions (5.3)].
Glucose Intolerance or Diabetes Mellitus
Inform patients that treatment with EGRIFTA WR may result in glucose intolerance or diabetes mellitus. Advise patients that they will need to be monitored to see if impaired glucose tolerance or diabetes mellitus develops, and that if they have pre-existing diabetes mellitus, they may need adjustments to their anti-diabetic medications [see Warnings and Precautions (5.4)].
Hypersensitivity Reactions
Inform patients that hypersensitivity reactions (e.g., rash, urticaria) may occur during treatment with EGRIFTA WR. Advise patients to seek prompt medical attention and to immediately discontinue treatment with EGRIFTA WR if a reaction occurs [see Warnings and Precautions (5.5)].
Injection Site Reactions
Inform patients that injection site reactions may occur with EGRIFTA WR, including injection site erythema, pruritus, pain, irritation, and bruising. Advise patients to rotate the site of injection to reduce the risk of injection site reactions [see Warnings and Precautions (5.6)].
Pregnancy
Advise women to discontinue EGRIFTA WR if pregnancy occurs, as the drug offers no known benefit to pregnant women and could result in fetal harm [see Contraindications (4) and Use in Specific Populations (8.1)].
Lactation
Because of both the potential for HIV-1 infection transmission and serious adverse reactions in nursing infants, mothers receiving EGRIFTA WR should be instructed not to breastfeed [see Use in Specific Populations (8.2)].
Administration
Counsel patients that they should never share an EGRIFTA WR syringe with another person, even if the needle is changed. Sharing of syringes or needles between patients may pose a risk of transmission of infection.

EGRIFTA WR is a trademark of Theratechnologies Inc.
Manufactured by Theratechnologies Inc., 2015 Peel Street, Suite 1100, Montréal, Québec, Canada H3A 1T8
US License No. 2091 for Theratechnologies Inc.