


Prescribing information (package insert) - Caverject
1 INDICATIONS AND USAGE
1.1 Erectile Dysfunction
CAVERJECT is indicated for the treatment of erectile dysfunction.
1.2 Diagnostic Test
CAVERJECT is indicated as an adjunct to other diagnostic tests in the diagnosis of erectile dysfunction.
2 DOSAGE AND ADMINISTRATION
2.1 Important Dosage and Administration Instructions
- Alprostadil is available in different strengths and presentations. Determine the most suitable dose and presentation for each patient.
- CAVERJECT is available in single-dose vials containing 20 mcg or 40 mcg of alprostadil. Make sure a new, correct strength vial of CAVERJECT is used for each patient dosage preparation.
- Titrate the dose of CAVERJECT for each patient to the lowest effective dose.
- CAVERJECT doses greater than 60 mcg are not recommended.
- Administer the first injections of CAVERJECT in the health care provider’s office by medically trained personnel.
- Instruct the patient on proper use and assess that they are well trained in the self-injection technique prior to initiation of home use. Refer to the Patient Information and Instructions for Use.
- Re-evaluate patients regularly (every 3 months or as clinically appropriate) and determine if dosage adjustments are needed.
2.2 Recommended Dosage for Erectile Dysfunction
Erectile Dysfunction of Vasculogenic, Psychogenic, or Mixed Etiology
- Initiate dosing with 2.5 mcg of CAVERJECT intracavernosally, as recommended [see Dosage and Administration (2.4)].
- If there is a partial response at 2.5 mcg, administer another dose of 2.5 mcg within 1 hour. Use a new vial for each dose of CAVERJECT.
- During titration, no more than 2 doses should be given within a 24-hour period.
- If additional titration is required, administer doses in increments of 5 to 10 mcg at least 24 hours apart.
- The optimal dose should produce an erection suitable for intercourse that does not exceed a duration of 1 hour.
- The patient must stay in the health care provider’s office until complete detumescence occurs.
Repeat the titration as necessary until the optimal dose is achieved. Doses greater than 60 mcg are not recommended.
Erectile Dysfunction of Pure Neurogenic Etiology (e.g., Spinal Cord Injury).
- Initiate dosing with 1.25 mcg of CAVERJECT intracavernosally, as recommended [see Dosage and Administration (2.4)].
- If there is a partial response at 1.25 mcg, administer another dose of 1.25 mcg within 1 hour. Use a new vial for each dose of CAVERJECT.
- If additional titration is required, administer a dose of 5 mcg at least 24 hours later.
- During titration, no more than 2 doses should be given within a 24-hour period.
- The optimal dose should produce an erection suitable for intercourse that does not exceed a duration of 1 hour.
- The patient must stay in the health care provider’s office until complete detumescence occurs.
Repeat the titration as necessary until the optimal dose is achieved. Doses greater than 60 mcg are not recommended.
Maintenance Dosage for Patient Home Use
- Once the dose of CAVERJECT has been determined in the health care provider’s office, additional dose adjustment may be required after consultation with the health care provider. Adjust the dose in accordance with the titration guidelines described above.
- The recommended frequency of injection is no more than 3 times weekly, with at least 24 hours between each dose.
Adjunct to the Diagnosis of Erectile Dysfunction
As an adjunct to the diagnosis of erectile dysfunction, inject CAVERJECT intracavernosally and monitor patients for the occurrence of an erection. Extensions of this testing are the use of CAVERJECT as an adjunct to laboratory investigations, such as duplex or Doppler ultrasound imaging. For any of these tests, use a single dose of CAVERJECT that induces a rigid erection. Use the dose regimen for ‘Erectile Dysfunction of Vasculogenic, Psychogenic, or Mixed Etiology’ above.
2.3 Preparation Instructions
Supplies Needed and Not Supplied With CAVERJECT
- 1 mL of the diluent (bacteriostatic water for injection)
- 1 mL to 3 mL syringe, dependent on the titrated dose
- 21 to 27 gauge needle for reconstitution
- 29 or 30 gauge one-half inch needle for injection
- alcohol swabs
Reconstitution Instructions
- CAVERJECT vial(s): Using the correct strength vial containing 20 mcg or 40 mcg of CAVERJECT, use a 1 mL to 3 mL syringe, a 21 to 27 gauge needle, and 1 mL of the diluent (bacteriostatic water for injection) for reconstitution. Reconstitution results in CAVERJECT 20 mcg/mL or 40 mcg/mL.
- Visually inspect the solution in the vial for particulate matter and discoloration. Do not use the solution if it is cloudy, colored or contains particles.
Table 1: Volume of CAVERJECT Solution to Inject using 1 mL syringe
| 20 mcg Vial | 40 mcg Vial | ||
|---|---|---|---|
| Dose | Volume to Inject | Dose | Volume to Inject |
| 1.25 mcg | 0.06 mL | 1.25 mcg | --- |
| 2.5 mcg | 0.125 mL | 2.5 mcg | --- |
| 5 mcg | 0.25 mL | 5 mcg | 0.125 mL |
| 10 mcg | 0.5 mL | 10 mcg | 0.25 mL |
| 15 mcg | 0.75 mL | 15 mcg | 0.375 mL |
| 20 mcg | 1 mL | 20 mcg | 0.5 mL |
| 25 mcg | --- | 25 mcg | 0.625 mL |
| 30 mcg | --- | 30 mcg | 0.75 mL |
| 40 mcg | --- | 40 mcg | 1 mL |
- Draw the dose of CAVERJECT into the syringe.
- Replace the needle used for reconstitution with a 29 or 30 gauge one-half inch needle prior to injection.
- The reconstituted solution should be used within 24 hours when stored at or below 25°C (77°F).
Refer to the Patient Information and Instructions for Use in the FDA-approved patient labeling for the complete detailed instructions on reconstitution and needle preparation steps.
2.4 Administration Instructions
- Use a 29 or 30 gauge one-half inch needle for injecting each dose.
- The patient should be in a sitting or slightly reclined position when injecting a dose.
- Retract the foreskin in uncircumcised patients.
- Grasp the head of the penis with the thumb and forefinger and stretch it lengthwise along the thigh.
- The site of injection is either the right or left lateral penis. See Figures A and B below.
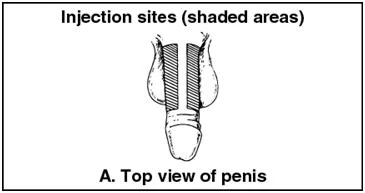 | 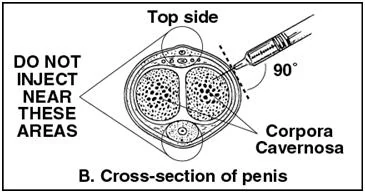 |
| Figure A | Figure B |
- Wipe the intended injection site with an alcohol swab prior to injection.
- Insert needle perpendicular to the long dorsolateral penile axis in the proximal third of penis. Avoid angulation of the syringe and do not bend the needle.
- Avoid visible veins during injection.
- With each use of CAVERJECT, alternate the side of the penis that is injected.
- Compress the site of injection with an alcohol swab or sterile gauze for 5 minutes.
- CAVERJECT is intended for single patient use only and should be discarded after use.
3 DOSAGE FORMS AND STRENGTHS
For injection: 20 mcg/vial and 40 mcg/vial lyophilized powder in single-dose vials for reconstitution.
4 CONTRAINDICATIONS
CAVERJECT is contraindicated:
- in men who have a known hypersensitivity to the drug [see Adverse Reactions (6.1)]
- in men who have conditions that predispose them to priapism, such as sickle cell anemia or sickle cell trait, multiple myeloma, or leukemia [see Warnings and Precautions (5.1)]
- for the treatment of erectile dysfunction in men with fibrotic conditions of the penis, such as anatomical deformation, angulation, cavernosal fibrosis, or Peyronie's disease [see Warnings and Precautions (5.2)]
- in men with penile implants.
5 WARNINGS AND PRECAUTIONS
5.1 Prolonged Erection and Priapism
Prolonged erection, defined as erection lasting between 4 to 6 hours in duration, occurred in 4% of 1,861 patients treated up to 18 months in studies of CAVERJECT. The incidence of priapism (erections lasting more than 6 hours in duration) was 0.4%. In the event of an erection that persists longer than 4 hours, the patient should seek immediate medical assistance. If priapism is not treated immediately, penile tissue damage and permanent loss of potency may result.
To minimize the chances of prolonged erection or priapism, titrate CAVERJECT to the lowest effective dose [see Dosage and Administration (2.1)]. In addition, do not use CAVERJECT in patients who have conditions that predispose them to priapism, such as sickle cell anemia or sickle cell trait, multiple myeloma, or leukemia [see Contraindications (4)].
5.2 Penile Fibrosis
The overall incidence of penile fibrosis reported in clinical studies with CAVERJECT was 3%. In one self-injection clinical study where duration of use was up to 18 months, the incidence of penile fibrosis was 7.8%.
Physical examination of the penis should be performed periodically, to detect signs of penile fibrosis. Treatment with CAVERJECT should be discontinued in patients who develop penile angulation or cavernosal fibrosis.
5.3 Hypotension
Intracavernous injections of CAVERJECT can increase peripheral blood levels of alprostadil which can result in hypotension. Avoid use of CAVERJECT in patients with known cavernosal venous leakage.
5.4 Injection Site Bleeding When Used with Anticoagulants
Patients on anticoagulants, such as warfarin or heparin, may have increased propensity for injection site bleeding after intracavernosal injection with CAVERJECT. Compress the site of injection with an alcohol swab or sterile gauze for 5 minutes.
5.5 Cardiovascular Risk Related to Underlying Medical Conditions
There is a potential for cardiac risk of sexual activity in patients with preexisting cardiovascular disease. Therefore, treatments for erectile dysfunction, including CAVERJECT, generally should not be used in men for whom sexual activity is inadvisable because of their underlying cardiovascular status. In addition, the evaluation of erectile dysfunction should include a determination of potential underlying causes and the identification of appropriate treatment following a complete medical assessment.
5.6 Risks of Use in Combination with Other Vasoactive Medications Injected Intracavernosally
The safety and efficacy of combinations of CAVERJECT and other vasoactive agents injected intracavernosally have not been established in clinical studies. The risks of prolonged erection, priapism, and hypotension may be increased.
5.7 Needle Breakage
Separate needles should be used for reconstitution and administration. A superfine needle is used for administration of CAVERJECT. As with all superfine needles, the possibility of needle breakage exists. Needle breakage, with a portion of the needle remaining in the penis, has been reported and, in some cases, has required hospitalization and surgical removal. Careful instruction in proper patient handling and injection techniques may minimize the potential for needle breakage [see Dosage and Administration (2.3) and Adverse Reactions (6.2)].
5.8 Risk of Serious Adverse Reactions in Infants due to Benzyl Alcohol Preservative
When reconstituted using the recommended diluent, the solution contains benzyl alcohol. Serious and fatal adverse reactions including "gasping syndrome" can occur in neonates and low birth weight infants treated with benzyl alcohol-preserved formulations in infusion solutions, including CAVERJECT. The "gasping syndrome" is characterized by central nervous system depression, metabolic acidosis, and gasping respirations. CAVERJECT is not indicated for use in pediatric patients.
5.9 Counsel Patients about Sexually Transmitted Diseases
The use of CAVERJECT offers no protection against sexually transmitted diseases. Counsel patients about the protective measures necessary to guard against sexually transmitted diseases, including the Human Immunodeficiency Virus (HIV).
6 ADVERSE REACTIONS
The following are described elsewhere in the labeling:
- Prolonged Erection and Priapism [see Warnings and Precautions (5.1)]
- Penile Fibrosis [see Warnings and Precautions (5.2)]
6.1 Clinical Trials Experience
Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice.
Local Adverse Reactions: Local adverse reactions derived from 1861 patients in clinical studies of CAVERJECT, including an 18-month, open-label study, are shown in Table 2.
Table 2. Local Adverse Reactions Reported by ≥ 1% of Patients Treated with CAVERJECT for up to 18 Months
| Penile pain | 37% |
| Prolonged erection | 4% |
| Penile fibrosis | 3% |
| Injection site hematoma | 3% |
| Penis disorderPenis disorder includes: numbness, irritation, sensitivity, pruritus, erythema, skin tear, discoloration, itching. | 3% |
| Injection site ecchymosis | 2% |
| Penile rash | 1% |
| Penile edema | 1% |
The following local adverse reactions were reported in < 1% of patients: injection site hemorrhage, injection site inflammation, injection site itching, injection site swelling, injection site edema, urethral bleeding, penile warmth, numbness, irritation, sensitivity, pruritus, erythema, painful erection, and abnormal ejaculation.
In these studies, no local adverse reactions were reported in the 294 patients who received placebo, except for penile pain (2%).
Penile Pain: In the majority of the cases, penile pain was rated mild or moderate in intensity. Three percent of patients discontinued treatment because of penile pain
Prolonged Erection/Priapism: Prolonged erection was defined as an erection that lasted for 4 to 6 hours; priapism was defined as an erection that lasted 6 hours or longer. In clinical studies the frequency of prolonged erection after CAVERJECT was 4%, while the frequency of priapism was 0.4% [see Warnings and Precautions (5.1)].
Penile Hematoma/Ecchymosis: In clinical studies, the frequency of penile hematoma and ecchymosis was 3% and 2%, respectively.
Systemic Adverse Reactions : Systemic adverse reactions reported by ≥ 1% of subjects in clinical studies of CAVERJECT included: dizziness (1%).
The following systemic adverse reactions were reported in < 1% of patients: testicular pain, scrotal edema, hematuria, pelvic pain, hypotension, vasodilation, vasovagal reaction, diaphoresis, rash, and non-application site pruritus. Three patients (0.2%) discontinued due to symptomatic hypotension.
No systemic adverse reactions were reported in the 294 patients who received placebo.
In addition to the adverse reactions observed for CAVERJECT, the following adverse reactions have been reported in clinical studies of CAVERJECT IMPULSE:
CAVERJECT IMPULSE was evaluated in 87 patients in an open-label crossover study of 6 weeks treatment duration that compared the formulation of alprostadil for injection contained in CAVERJECT IMPULSE with the formulation contained in CAVERJECT. Doses used in this study ranged from 2.5 mcg to 20 mcg. Adverse reactions reported for the CAVERJECT IMPULSE formulation included: penis disorder (4.6%), prolonged erection (1.1%), injection site erythema (1.1%), rash (1.1%), dizziness (1.1%), and hematospermia (1.1%). Penis disorder included penile pain, post-injection pain, and pain with erection.
CAVERJECT IMPULSE was also evaluated in 63 patients in a single-dose, double-blind, crossover study that compared CAVERJECT IMPULSE with CAVERJECT. Doses used in this study ranged from 2.5 mcg to 20 mcg. Adverse reactions reported for the CAVERJECT IMPULSE formulation included: penile pain (1.6%) and pruritis (1.6%).
6.2 Postmarketing Experience
The following adverse reaction has been identified during post-approval use of CAVERJECT.
Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
Injury and procedural complications: Needle breakage during administration of CAVERJECT. In some instances, surgical removal of the needle was required.
7 DRUG INTERACTIONS
The potential for pharmacokinetic drug-drug interactions between alprostadil and other agents administered orally or intracavernosally has not been formally studied [see Warnings and Precautions (5.6)].
8 USE IN SPECIFIC POPULATIONS
8.1 Pregnancy
CAVERJECT is not indicated for use in females.
8.2 Lactation
CAVERJECT is not indicated for use in females.
8.4 Pediatric Use
Safety and effectiveness have not been established in pediatric patients [see Warnings and Precautions (5.8)].
8.5 Geriatric Use
A total of 341 subjects included in clinical studies were 65 and older. No overall differences in safety and effectiveness were observed between these subjects and younger subjects, and the other reported clinical experience has not identified differences in responses between elderly and younger patients.
10 OVERDOSAGE
Overdosage was not observed in clinical trials with CAVERJECT. If intracavernous overdose of CAVERJECT occurs, the patient should be under medical supervision until any systemic effects have resolved and/or until penile detumescence has occurred. Treatment of any systemic symptoms (e.g., hypotension) would be appropriate.
11 DESCRIPTION
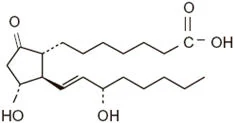
CAVERJECT contains alprostadil, a synthetic form of prostaglandin E1 (PGE1), and is designated chemically as (11α,13E,15S)-11,15-dihydroxy-9-oxoprost-13-en-1-oic acid. The molecular weight is 354.49.
Alprostadil is a white to off-white crystalline powder with a melting point between 115°C and 116° C. CAVERJECT is available as a sterile freeze-dried powder for intracavernosal use in sizes: 20 mcg and 40 mcg per vial. When reconstituted as directed with 1 mL of bacteriostatic water for injection, the volume of the reconstituted solution is 1.13 mL. Each mL of CAVERJECT contains 20.5 mcg or 41.1 mcg of alprostadil depending on vial strength, 172 mg of lactose, 47 mcg of sodium citrate and 8.4 mg of benzyl alcohol. The deliverable amount of alprostadil is 20 mcg or 40 mcg per mL because approximately 0.5 mcg for the 20 mcg strength and 1.1 mcg for the 40 mcg strength is lost due to adsorption to the vial and syringe. During manufacture, the pH of alprostadil for injection was adjusted with hydrochloric acid and/or sodium hydroxide before lyophilization.
The structural formula of alprostadil is represented below:
12 CLINICAL PHARMACOLOGY
12.1 Mechanism of Action
Alprostadil (PGE1) is a prostaglandin with a wide variety of pharmacological actions including vasodilation and inhibition of platelet aggregation. Alprostadil induces erection by relaxation of trabecular smooth muscle and by dilation of cavernosal arteries by binding to its receptors and increasing intracellular cyclic adenosine monophosphate (cAMP) levels via modulation of adenylate cyclase. This leads to expansion of lacunar spaces and entrapment of blood by compressing the venules against the tunica albuginea, a process referred to as the corporal veno-occlusive mechanism. Alprostadil also attenuates presynaptic noradrenaline release in the corpus cavernosum.
Studies in vitro have shown that alprostadil relaxed isolated preparations of human corpus cavernosum and spongiosum, as well as cavernous arterial segments contracted by either noradrenaline or PGF2α. In pigtail monkeys (Macaca nemestrina), alprostadil increased cavernous arterial blood flow in a dose-dependent manner in vivo.
12.3 Pharmacokinetics
Absorption: For the treatment of erectile dysfunction, alprostadil is administered by injection into the corpora cavernosa. The absolute bioavailability of alprostadil has not been determined.
Distribution: Following intracavernosal injection of 20 mcg alprostadil, mean peripheral plasma concentrations of alprostadil at 30 and 60 minutes after injection (89 picograms/mL and 102 picograms/mL, respectively) were not significantly greater than baseline levels of endogenous alprostadil (96 picograms/mL). Plasma levels of alprostadil were measured using a radioimmunoassay method. Alprostadil is bound in plasma primarily to albumin (81% bound) and to a lesser extent α-globulin IV-4 fraction (55% bound). No significant binding to erythrocytes or white blood cells was observed.
Metabolism: Alprostadil is converted to compounds which are further metabolized prior to excretion. Following intravenous administration, approximately 80% of circulating alprostadil is metabolized in one pass through the lungs, primarily by beta- and omega-oxidation. Following intracavernosal injection of 20 mcg alprostadil, peripheral levels of the major circulating metabolite, 13, 14-dihydro-15-oxo-PGE1, increased to reach a peak 30 minutes after injection and returned to pre-dose levels by 60 minutes after injection.
Excretion: The metabolites of alprostadil are excreted primarily by the kidney, with almost 90% of an administered intravenous dose excreted in urine within 24 hours post-dose. The remainder of the dose is excreted in the feces. There is no evidence of tissue retention of alprostadil or its metabolites following intravenous administration.
Pharmacokinetics in Specific Populations
Geriatric: The potential effect of age on the pharmacokinetics of alprostadil has not been formally evaluated.
Race: The potential effect of race on the pharmacokinetics of alprostadil has not been formally evaluated.
Renal and Hepatic Insufficiency: The pharmacokinetics of alprostadil have not been formally studied in patients with renal or hepatic insufficiency.
13 NONCLINICAL TOXICOLOGY
13.1 Carcinogenesis, Mutagenesis, Impairment of Fertility
Carcinogenesis
Long-term carcinogenicity studies have not been conducted.
Mutagenesis
Alprostadil was negative in bacterial mutation (Ames), alkaline elution, rat micronucleus, sister chromatid exchange, CHO/HGPRT mammalian cell forward gene mutation, and unscheduled DNA synthesis (UDS) assays.
Impairment of Fertility
Rat reproductive studies indicate that alprostadil at doses of up to 0.2 mg/kg/day does not adversely affect or alter male rat fertility. These doses are approximately 32-fold higher than the maximum recommended human dose of 60 mcg based on body surface area.
14 CLINICAL STUDIES
The efficacy of CAVERJECT was investigated in men with a diagnosis of erectile dysfunction due to psychogenic, vasculogenic, neurogenic, and/or mixed etiology in two double-blind, placebo-controlled studies (Study 1 and Study 2) and in one 6-month open-label study (Study 3). In clinical studies (Study 1 and Study 3), over 80% of patients experienced an erection sufficient for sexual intercourse after intracavernosal injection of CAVERJECT.
Study 1: A total of 153 men with ED with a mean age of 53 years (range 23–69 years) were enrolled. The study had three phases: a 2.5 week, randomized, double-blind, placebo-controlled crossover phase in which each man received in-office injections of placebo or 2.5 mcg, 5 mcg, 7.5 mcg, or 10 mcg of CAVERJECT; a 2 week, open-label, in-office dose-titration phase to identify the optimum home-use dose (the latter dose was defined as a dose inducing an erection sufficient for intercourse and lasting ≤ 60 minutes); and a 4-week open-label, at-home phase. In the double-blind placebo-controlled, crossover phase, each dose of CAVERJECT was significantly more effective than placebo by clinical evaluation ("full penile rigidity") and by RigiScan criteria (≥ 70% rigidity for at least 10 minutes); there was no response to placebo. The percentage of responders increased with increasing doses of CAVERJECT. The overall response rates in the crossover and dose-titration phases were 76% (117/153) by clinical evaluation and 51% (78/152) by RigiScan criteria. Seventy-three percent of the injections in 102 men who used CAVERJECT in the at-home phase resulted in satisfactory intercourse. Seventy-five percent of the men who used CAVERJECT in the at-home phase remained on the dose identified as optimum for them during the dose-titration phase; 17% and 8% of the men decreased or increased their dose, respectively. The mean duration of erection per injection was 70.8 minutes.
Study 2: A total of 296 men with ED with a mean age of 54 years (range 21–74 years) were enrolled in this double-blind, placebo-controlled, parallel-arm design study. The men were randomly assigned to one of five groups and received either a single dose of placebo, 2.5 mcg, 5 mcg, 10 mcg, or 20 mcg of CAVERJECT. No patient responded to placebo. The differences in the response rates in both the clinical and the RigiScan evaluations between each of the doses of CAVERJECT and placebo were statistically significant. There was also a statistically significant dose-response relationship with higher clinical response rates and higher RigiScan response rates with increasing doses of CAVERJECT (with exception of the 10-mcg dose). The mean duration of erection after injection ranged from 12 minutes after the 2.5-mcg dose to 44 minutes after the 20-mcg dose and the relationship was linear (p = .025, linear regression analysis).
Study 3: The efficacy of CAVERJECT was further evaluated in a 6-month, open-label, at-home study in 683 men with ED with a mean age of 58 years (range 20–79 years). The optimum dose of CAVERJECT was established by titration in 89% of men (606/683). A total of 471/683 men (69%) completed the 6-month study. Eighty-seven percent of the 13,762 injections of CAVERJECT administered resulted in satisfactory sexual activity. The mean duration of erection was 67.5 minutes.
The formulation of alprostadil contained in CAVERJECT IMPULSE was compared to CAVERJECT in 87 men with ED in a single-blind, crossover study. The doses used by the patients in the study ranged from 2.5 mcg to 20 mcg and were the same for both formulations. The efficacy of the two formulations was shown to be comparable, as assessed by the 30-point erectile function (EF) domain score from the International Index of Erectile Function (IIEF) and by a physician-assessment score for erectile response. The mean EF domain scores for CAVERJECT and the formulation contained in CAVERJECT were 26.6 (SD=5.3) and 27.6 (SD=3.8), respectively. The mean physician's assessment scores for CAVERJECT and the formulation contained in CAVERJECT IMPULSE were 2.6 (SD=0.6) and 2.7 (SD=0.5), respectively, based on a scale of 0 (no tumescence) to 3 (full rigidity).
16 HOW SUPPLIED/STORAGE AND HANDLING
CAVERJECT is a lyophilized powder supplied in vials containing 23.2 or 46.4 mcg of alprostadil for intracavernosal administration. When reconstituted as directed with 1 milliliter of bacteriostatic water for injection, the delivered amount of alprostadil is 20 mcg or 40 mcg.
Store CAVERJECT 20 mcg vials between 20°C to 25°C (68°F to 77°F). The reconstituted solution should be used within 24 hours when stored at or below 25°C (77°F) and not refrigerated or frozen.
Store CAVERJECT 40 mcg vials between 2°C to 8°C (36° to 46°F) until dispensed. Once dispensed, vials should be stored at or below 25°C (77°F) for up to 3 months or until the expiration date, whichever occurs first. The reconstituted solution should be used within 24 hours when stored at or below 25°C (77°F) and not refrigerated or frozen.
When reconstituted and used as directed, the deliverable amount of alprostadil is 20 micrograms or 40 micrograms, respectively. Only bacteriostatic water for injection, should be used when reconstituting CAVERJECT.
CAVERJECT is available in the following packages:
| Package of six 20 mcg vials | NDC 0009-3701-05 |
| Package of six 40 mcg vials | NDC 0009-7686-04 |
The following supplies are needed for injection and are not supplied with CAVERJECT:
- 1 mL of the diluent (bacteriostatic water for injection)
- 1 mL to 3 mL syringe, dependent on the titrated dose
- 21 to 27 gauge needle for reconstitution
- 29 or 30 gauge one-half inch needle for injection
- alcohol swabs
17 PATIENT COUNSELING INFORMATION
Advise the patient to read the FDA-approved patient labeling (Patient Information and Instructions for Use).
Dosing and Self-Administration
To ensure safe and effective use of CAVERJECT, instruct and train the patient in the self-injection technique before he begins treatment with CAVERJECT, at home. Inform the patient the initial dose administration and dose titration will take place in the health care provider’s office [see Dosage and Administration (2.1)].
Once the home dose of CAVERJECT has been established, instruct the patient not to change the dose without consulting their health care provider.
The patient may expect an erection to occur within 5 minutes to 20 minutes and it should last no longer than 1 hour. CAVERJECT should be used no more than 3 times per week, with at least 24 hours between each use [see Dosage and Administration (2.2)].
Inform the patient that they must visit the health care provider’s office for regular check-ups for assessment of the therapeutic benefit and safety of treatment with CAVERJECT.
When self-administering the patient should be instructed to [see Dosage and Administration (2.2, 2.3)]:
- Discard any reconstituted solution with precipitates or discoloration
- Administer the injection along the dorso-lateral aspect of the proximal third of the penis
- Wipe the intended injection site with an alcohol swab prior to injection
- Avoid visible veins during injection
- Alternate the side of the penis that is injected and the site of injection
- Compress the site of injection with an alcohol swab or sterile gauze for 5 minutes
- Use each CAVERJECT vial only once and discard after use. Use a new vial of CAVERJECT for each dose.
- Not use a bent needle for reconstitution or injection. Do not attempt to straighten a bent needle. Remove the needle from the syringe, discard it, and attach a new, unused sterile needle to the syringe
- Not re-use or share needles and to properly discard after use.
Needle Breakage
Advise patients that needle breakage has occurred during self-injection of CAVERJECT. Advise patients to insert the needle perpendicular to the long axis of the penis to avoid bending or breakage of the needle [see Dosage and Administration (2.4), Warnings and Precautions (5.7) and Adverse Reactions (6.2)].
Penile Pain
Advise patients that the most frequently occurring side-effect is penile pain after injection and is usually mild to moderate in severity [see Adverse Reactions (6.1)].
Priapism
A potentially serious adverse reaction with CAVERJECT is priapism. Instruct the patient to seek immediate medical assistance if an erection persists for longer than 4 hours [see Warnings and Precautions (5.1)].
Penile Fibrosis
Penile fibrosis has been reported in clinical studies with CAVERJECT. Advise the patient to report any penile pain that was not present before or that increased in intensity, as well as the occurrence of nodules or hard tissue in the penis or curvature of the erect penis to his physician as soon as possible. [see Warnings and Precautions (5.2)].
Injection Site Reactions
Inform the patient that injection of CAVERJECT can induce a small amount of bleeding at the site of injection and that hematoma and ecchymosis may occur. Advise the patient to report any persistent redness, tenderness or swelling [see Warnings and Precautions (5.4)].
Sexually Transmitted Disease
Use of CAVERJECT offers no protection from the transmission of sexually transmitted diseases. Advise the patient about the protective measures that are necessary to guard against the spread of sexually transmitted diseases, including the human immunodeficiency virus (HIV) [see Warnings and Precautions (5.9)].
This product's labeling may have been updated. For the most recent prescribing information, please visit www.pfizer.com

LAB-0764-5.0