


Prescribing information (package insert) - Bosutinib
1 INDICATIONS AND USAGE
Bosutinib tablets are indicated for the treatment of:
- Adult patients with chronic phase (CP) Philadelphia chromosome-positive chronic myelogenous leukemia (Ph+ CML), resistant or intolerant to prior therapy [see Clinical Studies (14.2)].
- Adult patients with accelerated phase (AP), or blast phase (BP) Ph+ CML with resistance or intolerance to prior therapy [see Clinical Studies (14.2)].
Pediatric use information is approved for PF PRISM CV’s BOSULIF® (bosutinib) tablets. However, due to PF PRISM CV’s marketing exclusivity rights, this drug product is not labeled with that information.
2 DOSAGE AND ADMINISTRATION
2.1 Recommended Dosage
The recommended dosage is taken orally once daily with food. Swallow tablets whole. Do not cut, crush, break or chew tablets. Continue treatment with bosutinib tablets until disease progression or intolerance to therapy.
If a dose is missed beyond 12 hours, the patient should skip the dose and take the usual prescribed dose on the following day.
Dosage in Adult Patients with CP, AP, or BP Ph+ CML with Resistance or Intolerance to Prior Therapy
The recommended dosage of bosutinib tablet is 500 mg orally once daily with food.
Pediatric use information is approved for PF PRISM CV’s BOSULIF® (bosutinib) tablets. However, due to PF PRISM CV’s marketing exclusivity rights, this drug product is not labeled with that information.
2.2 Dose Escalation
In clinical studies of adult patients with Ph+ CML, dose escalation by increments of 100 mg once daily to a maximum of 600 mg once daily was allowed in patients who did not achieve or maintain a hematologic, cytogenetic, or molecular response and who did not have Grade 3 or higher adverse reactions at the recommended starting dosage.
The maximum dose in adult patients is 600 mg once daily.
Pediatric use information is approved for PF PRISM CV’s BOSULIF® (bosutinib) tablets. However, due to PF PRISM CV’s marketing exclusivity rights, this drug product is not labeled with that information.
2.3 Dosage Adjustments for Non-Hematologic Adverse Reactions
Elevated liver transaminases: If elevations in liver transaminases greater than 5×institutional upper limit of normal (ULN) occur, withhold bosutinib tablets until recovery to less than or equal to 2.5×ULN and resume at 400 mg once daily thereafter. If recovery takes longer than 4 weeks, discontinue bosutinib tablets. If transaminase elevations greater than or equal to 3×ULN occur concurrently with bilirubin elevations greater than 2×ULN and alkaline phosphatase less than 2×ULN (Hy’s law case definition), discontinue bosutinib tablets [see Warnings and Precautions (5.3)].
Diarrhea: For National Cancer Institute Common Terminology Criteria for Adverse Events (NCI CTCAE) Grade 3 to 4 diarrhea (increase of greater than or equal to 7 stools/day over baseline/pretreatment), withhold bosutinib tablets until recovery to Grade less than or equal to 1. Bosutinib tablets may be resumed at 400 mg once daily [see Warnings and Precautions (5.1)].
For other clinically significant, moderate or severe non-hematological toxicity, withhold bosutinib tablets until the toxicity has resolved, then consider resuming bosutinib tablets at a dose reduced by 100 mg taken once daily. If clinically appropriate, consider re-escalating the dose of bosutinib tablets to the starting dose taken once daily.
Pediatric use information is approved for PF PRISM CV’s BOSULIF® (bosutinib) tablets. However, due to PF PRISM CV’s marketing exclusivity rights, this drug product is not labeled with that information.
2.4 Dosage Adjustments for Myelosuppression
Dose reductions for severe or persistent neutropenia and thrombocytopenia are described below (Table 3).
Table 3: Dose Adjustments for Neutropenia and Thrombocytopenia in Adult Patients
ANCa less than 1000 x106/L or Platelets less than 50,000 x106/L | Withhold bosutinib tablets until ANC greater than or equal to 1000x106/L and platelets greater than or equal to 50,000x106/L. Resume treatment with bosutinib tablets at the same dose if recovery occurs within 2 weeks. If blood counts remain low for greater than 2 weeks, upon recovery, reduce dose by 100 mg and resume treatment. If cytopenia recurs, reduce dose by an additional 100 mg upon recovery and resume treatment. |
a Absolute Neutrophil Count
Pediatric use information is approved for PF PRISM CV’s BOSULIF® (bosutinib) tablets. However, due to PF PRISM CV’s marketing exclusivity rights, this drug product is not labeled with that information.
2.5 Dosage Adjustments for Renal Impairment or Hepatic Impairment
The recommended starting doses for patients with renal and hepatic impairment are described in Table 4 below.
Table 4: Dose Adjustments for Renal and Hepatic Impairment in Adult Patients
| Recommended Starting Dosage | |
| Chronic, accelerated, or blast phase Ph+ CML with resistance or intolerance to prior therapy | |
| Normal | 500 mg daily |
| Renal impairment | |
| Creatinine clearance 30 to 50 mL/min | 400 mg daily |
| Creatinine clearance less than 30 mL/min | 300 mg daily |
| Hepatic impairment | |
| Mild (Child-Pugh A), Moderate (Child-Pugh B) or severe (Child-Pugh C) | 200 mg daily |
[see Use in Specific Populations (8.6, 8.7) and Clinical Pharmacology (12.3)].
Pediatric use information is approved for PF PRISM CV’s BOSULIF® (bosutinib) tablets. However, due to PF PRISM CV’s marketing exclusivity rights, this drug product is not labeled with that information.
3 DOSAGE FORMS AND STRENGTHS
- 100 mg are yellow colored, oval shaped, biconvex, film coated tablet, debossed with L603 on one side and plain on other side.
- 500 mg are red colored, oval shaped, biconvex, film coated tablet debossed with L604 on one side and plain on the other.
4 CONTRAINDICATIONS
Bosutinib tablet is contraindicated in patients with a history of hypersensitivity to bosutinib. Reactions have included anaphylaxis [see Adverse Reactions (6.1)].
5 WARNINGS AND PRECAUTIONS
5.1 Gastrointestinal Toxicity
Diarrhea, nausea, vomiting, and abdominal pain occur with bosutinib tablets treatment. Monitor and manage patients using standards of care, including antidiarrheals, antiemetics, and fluid replacement.
Among 546 adult patients in a single-arm study in patients with CML who were resistant or intolerant to prior therapy, the median time to onset for diarrhea (all grades) was 2 days and the median duration per event was 2 days. Among the patients who experienced diarrhea, the median number of episodes of diarrhea per patient during treatment with bosutinib tablets was 3 (range 1 to 268).
To manage gastrointestinal toxicity, withhold, dose reduce, or discontinue bosutinib tablets as necessary [see Dosage and Administration (2.3) and Adverse Reactions (6)].
Pediatric use information is approved for PF PRISM CV’s BOSULIF® (bosutinib) tablets. However, due to PF PRISM CV’s marketing exclusivity rights, this drug product is not labeled with that information.
5.2 Myelosuppression
Thrombocytopenia, anemia and neutropenia occur with bosutinib tablets treatment. Perform complete blood counts weekly for the first month of therapy and then monthly thereafter, or as clinically indicated. To manage myelosuppression, withhold, dose reduce, or discontinue bosutinib tablets as necessary [see Dosage and Administration (2.4) and Adverse Reactions (6)].
5.3 Hepatic Toxicity
Bosutinib may cause elevations in serum transaminases (alanine aminotransferase [ALT], aspartate aminotransferase [AST]).
Two cases consistent with drug induced liver injury (defined as concurrent elevations in ALT or AST greater than or equal to 3×ULN with total bilirubin greater than 2×ULN and alkaline phosphatase less than 2×ULN) have occurred without alternative causes. This represented 2 out of 1711 patients in bosutinib tablets clinical trials.
Among the 546 adult patients in a single-arm study in patients with CML who were resistant or intolerant to prior therapy, the incidence of increased ALT was 53.3% and AST elevation was 46.7%. Sixty percent of the patients experienced an increase in either ALT or AST. Most cases of transaminase elevations in this study occurred early in treatment; of patients who experienced increased transaminase of any grade, more than 81% experienced their first increase within the first 3 months. The median time to onset of increased ALT and AST was 22 and 29 days, respectively, and the median duration for each was 21 days.
Perform hepatic enzyme tests monthly for the first 3 months of bosutinib tablets treatment and as clinically indicated. In patients with transaminase elevations, monitor liver enzymes more frequently. Withhold, dose reduce, or discontinue bosutinib tablets as necessary [see Dosage and Administration (2.3) and Adverse Reactions (6)].
Pediatric use information is approved for PF PRISM CV’s BOSULIF® (bosutinib) tablets. However, due to PF PRISM CV’s marketing exclusivity rights, this drug product is not labeled with that information.
5.4 Cardiovascular Toxicity
Bosutinib can cause cardiovascular toxicity including cardiac failure, left ventricular dysfunction, and cardiac ischemic events. Cardiac failure events occurred more frequently in previously treated patients and were more frequent in patients with advanced age or risk factors, including previous medical history of cardiac failure. Cardiac ischemic events occurred in previously treated patients and were more common in patients with coronary artery disease risk factors, including history of diabetes, body mass index greater than 30, hypertension, and vascular disorders.
In a single-arm study in adult patients with CML who were resistant or intolerant to prior therapy, cardiac failure was observed in 5.3% of patients and cardiac ischemic events were observed in 5.1% of patients treated with bosutinib.
Monitor patients for signs and symptoms consistent with cardiac failure and cardiac ischemia and treat as clinically indicated. Interrupt, dose reduce, or discontinue bosutinib as necessary [see Dosage and Administration (2.3) and Adverse Reactions (6)].
Pediatric use information is approved for PF PRISM CV’s BOSULIF® (bosutinib) tablets. However, due to PF PRISM CV’s marketing exclusivity rights, this drug product is not labeled with that information.
5.5 Fluid Retention
Fluid retention occurs with bosutinib tablets and may manifest as pericardial effusion, pleural effusion, pulmonary edema, and/or peripheral edema.
Among 546 adult patients in a single-arm study in patients with Ph+ CML who were resistant or intolerant to prior therapy, Grade 3 or 4 fluid retention was reported in 30 patients (6%). Some patients experienced more than one fluid retention event. Specifically, 24 patients experienced Grade 3 or 4 pleural effusions, 9 patients experienced Grade 3 or Grade 4 pericardial effusions, and 6 patients experienced Grade 3 edema.
Monitor and manage patients using standards of care. Interrupt, dose reduce or discontinue bosutinib tablets as necessary [see Dosage and Administration (2.3) and Adverse Reactions (6)].
Pediatric use information is approved for PF PRISM CV’s BOSULIF® (bosutinib) tablets. However, due to PF PRISM CV’s marketing exclusivity rights, this drug product is not labeled with that information.
5.6 Renal Toxicity
An on-treatment decline in estimated glomerular filtration rate (eGFR) has occurred in patients treated with bosutinib tablets. Table 6 identifies the shift from baseline to lowest observed eGFR during bosutinib tablets therapy for patients in the pooled leukemia studies regardless of line of therapy. The median duration of therapy with bosutinib tablets was approximately 24 months (range, 0.03 to 155) for patients in these studies.
Table 6: Shift From Baseline to Lowest Observed eGFR Group During Treatment Safety Population in Clinical Studies (N=1372)*
| Baseline | Follow-Up | ||||||
| Renal Function Status | N | Normal n (%) | Mild n (%) | Mild to Moderate n (%) | Moderate to Severe n (%) | Severe n (%) | Kidney Failure n (%) |
| Normal | 527 | 115 (21.8) | 330 (62.6) | 50 (9.5) | 23 (4.4) | 3 (0.6) | 5 (0.9) |
| Mild | 672 | 10 (1.5) | 259 (38.5) | 271 (40.3) | 96 (14.3) | 26 (3.9) | 6 (0.9) |
| Mild to Moderate | 137 | 0 | 6 (4.4) | 40 (29.2) | 66 (48.2) | 24 (17.5) | 1 (0.7) |
| Moderate to Severe | 33 | 0 | 1 (3) | 1 (3) | 8 (24.2) | 19 (57.6) | 4 (12.1) |
| Severe | 1 | 0 | 0 | 0 | 0 | 0 | 1 (100) |
| Total | 1370 | 125 (9.1) | 596 (43.5) | 362 (26.4) | 193 (14.1) | 72 (5.2) | 17 (1.2) |
Abbreviations: eGFR=estimated glomerular filtration rate; N/n=number of patients. Notes: eGFR was calculated using Modification in Diet in Renal Disease method (MDRD). Notes: Grading is based on Kidney Disease Improving Global Outcomes (KDIGO) Classification by eGFR: Normal: greater than or equal to 90, Mild: 60 to less than 90, Mild to Moderate: 45 to less than 60, Moderate to Severe: 30 to less than 45, Severe: 15 to less than 30, Kidney Failure: less than 15 ml/min/1.73 m2. *Among the 1372 patients, eGFR was missing in 7 patients at baseline or on-therapy. There were no patients with kidney failure at baseline. | |||||||
Monitor renal function at baseline and during therapy with bosutinib tablets, with particular attention to those patients who have preexisting renal impairment or risk factors for renal dysfunction. Consider dose adjustment in patients with baseline and treatment emergent renal impairment [see Dosage and Administration (2.5)].
Pediatric use information is approved for PF PRISM CV’s BOSULIF® (bosutinib) tablets. However, due to PF PRISM CV’s marketing exclusivity rights, this drug product is not labeled with that information.
5.7 Embryofetal Toxicity
Based on findings from animal studies and its mechanism of action, bosutinib tablets can cause fetal harm when administered to a pregnant woman. There are no available data in pregnant women to inform the drug-associated risk. In animal reproduction studies conducted in rats and rabbits, oral administration of bosutinib during organogenesis caused adverse developmental outcomes, including structural abnormalities, embryo-fetal mortality, and alterations to growth at maternal exposures (AUC) as low as 1.2 times the human exposure at the dose of 500 mg/day. Advise pregnant women of the potential risk to a fetus. Advise females of reproductive potential to use effective contraception during treatment and for 2 weeks after the last dose [see Use in Specific Populations (8.1, 8.3) and Clinical Pharmacology (12.1)].
6 ADVERSE REACTIONS
The following clinically significant adverse reactions are discussed in greater detail in other sections of the labeling:
- Gastrointestinal toxicity [see Warnings and Precautions (5.1)].
- Myelosuppression [see Warnings and Precautions (5.2)].
- Hepatic toxicity [see Warnings and Precautions (5.3)].
- Cardiovascular toxicity [see Warnings and Precautions (5.4)].
- Fluid retention [see Warnings and Precautions (5.5)].
- Renal toxicity [see Warnings and Precautions ( 5.6)].
6.1 Clinical Trials Experience
Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice.
The most common adverse reactions, in ≥20% of adults with resistance or intolerance to prior therapy (N=814) were diarrhea (80%), rash (44%), nausea (44%), abdominal pain (43%), vomiting (33%), fatigue (33%), hepatic dysfunction (33%), respiratory tract infection (25%), pyrexia (24%), and headache (21%).
The most common laboratory abnormalities that worsened from baseline in ≥20% of adults were creatinine increased (93%), hemoglobin decreased (90%), lymphocyte count decreased (72%), platelets decreased (69%), ALT increased (58%), calcium decreased (53%), white blood cell count decreased (52%), absolute neutrophils count decreased (50%), AST increased (50%), glucose increased (46%), phosphorus decreased (44%), urate increased (41%), alkaline phosphatase increased (40%), lipase increased (36%), creatine kinase increased (29%), and amylase increased (24%).
Adverse Reactions in Adult Patients With Imatinib-Resistant or-Intolerant Ph+ CP, AP, and BP CML
The single-arm clinical trial enrolled patients with Ph+ CP, AP and BP CML and with resistance or intolerance to prior therapy [see Clinical Studies (14.2)]. The safety population (received at least 1 dose of bosutinib tablets) included 546 CML patients:
- two hundred eighty-four (284) patients with CP CML previously treated with imatinib only who had a median duration of bosutinib tablets treatment of 26 months (range: 0.2 to 155 months), and a median dose intensity of 437 mg/day.
- one hundred and nineteen (119) patients with CP CML previously treated with both imatinib and at least 1 additional tyrosine kinase inhibitor (TKI) who had a median duration of bosutinib tablets treatment of 9 months (range: 0.2 to 148 months), and a median dose intensity of 427 mg/day.
- one hundred forty three (143) patients with advanced phase (AdvP) CML including 79 patients with AP CML and 64 patients with BP CML. In the patients with AP CML and BP CML, the median duration of bosutinib tablets treatment was 10 months (range: 0.1 to 140 months) and 3 months (range: 0.03 to 71 months), respectively. The median dose intensity was 406 mg/day, and 456 mg/day, in the AP CML and BP CML cohorts, respectively.
Serious adverse reactions occurred in 30% of patients in the safety population of the single-arm trial in patients with CML (N=546) who were resistant or intolerant to prior therapy. Serious adverse reactions reported in >2% of patients included pneumonia (7%), pleural effusion (6%), pyrexia (3.7%), coronary artery disease (3.5%), dyspnea (2.6%), rash (2.2%), thrombocytopenia (2%), abdominal pain (2%), and diarrhea (2%).
Fatal adverse reactions occurred in 12 patients (2.2%) due to coronary artery disease (0.9%), pneumonia (0.4%), respiratory failure (0.4%), gastrointestinal hemorrhage (0.2%), acute kidney injury (0.2%), and acute pulmonary edema (0.2%).
Permanent discontinuation of bosutinib due to an adverse reaction occurred in 22% of patients with CML who were resistant or intolerant to prior therapy. Adverse reactions which resulted in permanent discontinuation in >2% of patients included thrombocytopenia (6%), hepatic dysfunction (3.3%), and neutropenia (2%).
Dose modifications (dose interruption or reductions) of bosutinib due to an adverse reaction occurred in 66% of patients with CML who were resistant or intolerant to prior therapy. Adverse reactions which required dose interruptions or reductions in >5% of patients included thrombocytopenia (24%), diarrhea (14%), rash (13%), hepatic dysfunction (10%), neutropenia (9%), pleural effusion (8%), vomiting (7%), anemia (6%), and abdominal pain (6%).
The most common adverse reactions, in ≥20% of patients in the safety population of the single-arm trial in patients with CML (N=546) who were resistant or intolerant to prior therapy were diarrhea (83%), nausea (47%), rash (46%), abdominal pain (45%), vomiting (39%), fatigue (33%), pyrexia (28%), hepatic dysfunction (27%), respiratory tract infection (24%), cough (23%), and headache (21%).
The most common laboratory abnormalities that worsened from baseline in ≥20% were creatinine increased (93%), hemoglobin decreased (91%), lymphocyte decreased (80%), platelets decreased (69%), absolute neutrophil count (54%), ALT increased (53%), calcium decreased (53%), white blood cell count decreased (52%), urate increased (48%), AST increased (47%), phosphorus decreased (39%), alkaline phosphatase increased (39%), lipase increased (28%), magnesium increased (25%), potassium decreased (24%), potassium increased (23%). See Table 10 for Grade 3/4 laboratory abnormalities.
Table 9 identifies adverse reactions greater than or equal to 10% for All Grades and Grades 3 or 4 for the Phase 1/2 CML safety population based on long-term follow-up.
Table 9: Adverse Reactions (10% or Greater) in Patients With CML Who Were Resistant or Intolerant to Prior Therapy in Single-Arm Trial*
| System Organ Class | Preferred Term | CP CML N=403 | AdvP CML N=143 | ||
|---|---|---|---|---|---|
All Grades (%) | Grade 3/4 (%) | All Grades (%) | Grade 3/4 (%) | ||
| Gastrointestinal disorders | Diarrhea | 85 | 10 | 76 | 4 |
| Abdominal paina | 49 | 2 | 36 | 7 | |
| Nausea | 47 | 1 | 48 | 2 | |
| Vomiting | 38 | 3 | 43 | 3 | |
| Constipation | 15 | <1 | 17 | 1 | |
| Skin and subcutaneous tissue disorders | Rashe | 48 | 9 | 42 | 5 |
| Pruritus | 12 | 1 | 7 | 0 | |
| General disorders and administration-site conditions | Fatigue | 35 | 3 | 27 | 6 |
| Pyrexia | 25 | 1 | 37 | 3 | |
| Edemac | 19 | <1 | 17 | 1 | |
| Chest paing | 8 | 1 | 12 | 1 | |
| Hepatobiliary disorders | Hepatic dysfunctionh | 29 | 11 | 21 | 10 |
| Infections and infestations | Respiratory tract infectionf | 27 | <1 | 17 | 0 |
| Influenzai | 11 | 1 | 3 | 0 | |
| Pneumoniad | 10 | 4 | 18 | 12 | |
| Respiratory, thoracic, and mediastinal disorders | Cough | 24 | 0 | 22 | 0 |
| Pleural effusion | 14 | 4 | 9 | 4 | |
| Dyspnea | 12 | 2 | 20 | 6 | |
| Nervous system disorders | Headache | 21 | 1 | 18 | 4 |
| Dizziness | 11 | 0 | 14 | 1 | |
| Musculoskeletal and connective tissue disorders | Arthralgia | 19 | 1 | 15 | 0 |
| Back pain | 14 | 1 | 8 | 1 | |
| Metabolism and nutrition disorders | Decreased appetite | 14 | 1 | 14 | 0 |
| Vascular disorders | Hypertensionb | 11 | 3 | 8 | 3 |
ADR Definition
* Based on Minimum of 105 Months of Follow-up.
Adverse drug reactions are based on all-causality treatment-emergent adverse events.
The commonality stratification is based on 'All Grades' under Total column.
‘Grade 3’, ‘Grade 4’ columns indicate maximum toxicity
a Abdominal pain includes the following preferred terms: Abdominal discomfort, Abdominal pain, Abdominal pain lower, Abdominal pain upper, Abdominal tenderness, Dyspepsia, Epigastric discomfort, Gastrointestinal pain, Hepatic pain.
g Chest pain includes the following preferred terms: Chest discomfort, Chest pain.
h Hepatic dysfunction includes the following preferred terms: Alanine aminotransferase increased, Aspartate aminotransferase increased, Bilirubin conjugated increased, Blood alkaline phosphatase increased, Blood bilirubin increased, Blood bilirubin unconjugated increased, Gamma-glutamyltransferase increased, Hepatic enzyme increased, Hepatic function abnormal, Hepatic steatosis, Hepatitis toxic, Hepatomegaly, Hepatotoxicity, Hyperbilirubinemia, Liver disorder, Liver function test abnormal, Liver function test increased, Transaminases increased.
b Hypertension* includes the following preferred terms: Blood pressure increased, Blood pressure systolic increased, Essential hypertension, Hypertension, Hypertensive crisis, Retinopathy hypertensive.
i Influenza includes the following preferred terms: H1N1 influenza, Influenza.
c Edema includes the following preferred terms: Eye edema, Eyelid edema, Face edema, Generalized edema, Localized edema, Edema, Edema peripheral, Penile edema, Periorbital edema, Periorbital swelling, Peripheral swelling, Scrotal edema, Scrotal swelling, Swelling, Swelling face, Swelling of eyelid, Testicular edema, Tongue edema.
d Pneumonia includes the following preferred terms: Atypical pneumonia, Lower respiratory tract congestion, Lower respiratory tract infection, Pneumonia, Pneumonia aspiration, Pneumonia bacterial, Pneumonia fungal, Pneumonia necrotising, Pneumonia streptococcal.
e Rash includes the following preferred terms: Acarodermatitis, Acne, Angular cheilitis, Blister, Dermatitis, Dermatitis acneiform, Dermatitis psoriasiform, Drug eruption,
Eczema, Eczema asteatotic, Erythema, Erythema annulare, Exfoliative rash, Lichenoid keratosis, Palmar erythema, Photosensitivity reaction, Pigmentation disorder, Psoriasis, Pyoderma gangrenosum, Pyogenic granuloma, Rash, Rash erythematous, Rash generalised, Rash macular, Rash maculo-papular, Rash pruritic, Rash pustular, Seborrhoeic dermatitis, Seborrhoeic keratosis, Skin depigmentation, Skin discoloration, Skin disorder, Skin exfoliation, Skin hyperpigmentation, Skin hypopigmentation, Skin irritation, Skin lesion, Skin plaque, Skin toxicity, Stasis dermatitis.
f Respiratory tract infection includes the following preferred terms: Nasopharyngitis, Respiratory tract congestion, Respiratory tract infection, Respiratory tract infection viral, Upper respiratory tract infection, Viral upper respiratory tract infection.
* ADR identified post-marketing
In the single-arm study in patients with CML who were resistant or intolerant to prior therapy, 2 patients (0.4%) experienced QTcF interval of greater than 500 milliseconds. Patients with uncontrolled or significant cardiovascular disease including QT interval prolongation were excluded by protocol.
Table 10 identifies the clinically relevant or severe Grade 3/4 laboratory test abnormalities for the safety population of the study in patients with CML who were resistant or intolerant to prior therapy based on long-term follow-up.
Table 10: Number (%) of Patients With Clinically Relevant All Grade or Grade 3/4 Laboratory Test Abnormalities in the Safety Population of the Study of Patients With CML Who Were Resistant or Intolerant to Prior Therapy*
CP CML N=403 % | AdvP CML N=143 % | |||
| All grade | Grade 3/4 | All grade | Grade 3/4 | |
| Hematology Parameters | ||||
| Platelet Count decreased | 66 | 26 | 80 | 57 |
| Absolute Neutrophil Count decreased | 50 | 16 | 66 | 39 |
| Hemoglobin decreased | 89 | 13 | 97 | 38 |
| Lymphocyte decreased | 79 | 14 | 82 | 21 |
| White Blood Cell Count decreased | 51 | 7 | 57 | 27 |
| Biochemistry Parameters | ||||
| SGPT/ALT increased | 58 | 11 | 39 | 6 |
| SGOT/AST increased | 50 | 5 | 37 | 3.5 |
| Lipase increased | 32 | 12 | 19 | 6 |
| Phosphorus decreased | 41 | 8 | 33 | 7 |
| Total Bilirubin increased | 16 | 0.7 | 22 | 2.8 |
| Creatinine increased | 95 | 3 | 87 | 1.4 |
| Alkaline Phosphatase increased | 39 | 0 | 39 | 1.4 |
| Glucose increased | 42 | 2.7 | 39 | 6 |
| Sodium increased | 23 | 0.5 | 11 | 0 |
| Sodium decreased | 18 | 2.2 | 27 | 6 |
| Calcium decreased | 55 | 4.7 | 45 | 3.5 |
| Urate increased | 49 | 6 | 43 | 6 |
| Magnesium increased | 27 | 7 | 18 | 4.9 |
| Potassium decreased | 22 | 1.7 | 29 | 4.9 |
| Potassium increased | 25 | 2.7 | 19 | 2.1 |
* Based on Minimum of 105 Months of Follow-up.
Abbreviations: AdvP=advanced phase; ALT=alanine aminotransferase; AST=aspartate aminotransferase; CML=chronic myelogenous leukemia; CP=chronic phase; N/n=number of patients; SGPT=serum glutamate-pyruvate transaminase; SGOT=serum glutamate-oxaloacetate aminotransferase; ULN=upper limit of normal.
Additional Adverse Reactions From Multiple Clinical Trials
The following adverse reactions were reported in patients in clinical trials with bosutinib tablets (less than 10% of bosutinib tablets-treated patients). They represent an evaluation of the adverse reaction data from all 1372 patients with leukemia who received at least 1 dose of single-agent bosutinib tablets. These adverse reactions are presented by system organ class and are ranked by frequency. These adverse reactions are included based on clinical relevance and ranked in order of decreasing seriousness within each category.
Blood and Lymphatic System Disorders: 0.1% and less than 1% - Febrile neutropenia
Cardiac Disorders: 1% and less than 10% - Cardiac ischemia (includes Acute coronary syndrome, Acute myocardial infarction, Angina pectoris, Angina unstable, Arteriosclerosis coronary artery, Coronary artery disease, Coronary artery occlusion, Coronary artery stenosis, Myocardial infarction, Myocardial ischemia, Troponin increased), Pericardial effusion, Cardiac failure (includes Cardiac failure, Cardiac failure acute, Cardiac failure chronic, Cardiac failure congestive, Cardiogenic shock, Cardiorenal syndrome, Ejection fraction decreased, Left ventricular failure); 0.1% and less than 1% - Pericarditis
Ear and Labyrinth Disorders: 1% and less than 10% - Tinnitus
Endocrine Disorders: 1% and less than 10% - Hypothyroidism; 0.1% and less than 1% -Hyperthyroidism
Gastrointestinal Disorders: 1% and less than 10% - Gastritis, Pancreatitis (includes Edematous pancreatitis, Pancreatic enzymes increased, Pancreatitis, Pancreatitis acute, Pancreatitis chronic), Gastrointestinal hemorrhage (includes Anal hemorrhage, Gastric hemorrhage, Gastrointestinal hemorrhage, Intestinal hemorrhage, Lower gastrointestinal hemorrhage, Rectal hemorrhage, Upper gastrointestinal hemorrhage)
General Disorders and Administrative Site Conditions: 1% and less than 10% - Pain
Immune System Disorders: 1% and less than 10% - Drug hypersensitivity; 0.1% and less than 1% - Anaphylactic shock
Infections and Infestations: 1% and less than 10% - Bronchitis
Investigations: 1% and less than 10% - Electrocardiogram QT prolonged (includes Electrocardiogram QT prolonged, Long QT syndrome)
Metabolism and Nutrition Disorders: 1% and less than 10% - Dehydration
Musculoskeletal and Connective Tissue Disorders: 1% and less than 10% - Myalgia
Nervous System Disorders: 1% and less than 10% - Dysgeusia
Renal and Urinary Disorders: 1% and less than 10% - Acute kidney injury, Renal impairment, Renal failure
Respiratory, Thoracic and Mediastinal Disorders: 1% and less than 10% - Pulmonary hypertension (includes Pulmonary hypertension, Pulmonary arterial hypertension, Pulmonary arterial pressure increased); 0.1% and less than 1% - Acute pulmonary edema (includes Acute pulmonary edema, Pulmonary edema), Interstitial lung disease, Respiratory failure
Skin and Subcutaneous Disorders: 0.1% and less than 1% - Erythema multiforme, Cutaneous vasculitis
Pediatric use information is approved for PF PRISM CV’s BOSULIF® (bosutinib) tablets. However, due to PF PRISM CV’s marketing exclusivity rights, this drug product is not labeled with that information.
6.2 Postmarketing Experience
The following additional adverse reactions have been identified during post-approval use of bosutinib tablets. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
Blood and Lymphatic System Disorders: Thrombotic microangiopathy
Skin and Subcutaneous Tissue Disorders: Stevens-Johnson syndrome
7 DRUG INTERACTIONS
7.1 Effect of Other Drugs on Bosutinib Tablets
Strong or Moderate CYP3A Inhibitors
Avoid the concomitant use of strong or moderate CYP3A inhibitors with bosutinib tablets. Bosutinib is a CYP3A substrate. Concomitant use with a strong or moderate CYP3A inhibitor increases bosutinib Cmax and AUC [see Clinical Pharmacology (12.3)] which may increase the risk of toxicities.
Strong CYP3A Inducers
Avoid the concomitant use of strong CYP3A inducers with bosutinib tablets. Bosutinib is a CYP3A substrate. Concomitant use with a strong CYP3A inducer decreases bosutinib Cmax and AUC [see Clinical Pharmacology (12.3)] which may reduce bosutinib tablets efficacy.
Proton Pump Inhibitors (PPI)
As an alternative to PPIs, use short-acting antacids or H2 blockers and separate dosing by more than 2 hours from bosutinib tablets dosing. Bosutinib displays pH dependent aqueous solubility, Concomitant use with a PPI decreases bosutinib Cmax and AUC [see Clinical Pharmacology (12.3)] which may reduce bosutinib tablets efficacy.
8 USE IN SPECIFIC POPULATIONS
8.1 Pregnancy
Risk Summary
Based on findings from animal studies and its mechanism of action, bosutinib tablets can cause fetal harm when administered to a pregnant woman [see Clinical Pharmacology (12.1)].
There are no available data in pregnant women to inform the drug-associated risk. In animal reproduction studies conducted in rats and rabbits, oral administration of bosutinib during organogenesis caused adverse developmental outcomes, including structural abnormalities, embryo-fetal mortality, and alterations to growth at maternal exposures (AUC) as low as 1.2 times the human exposure at the dose of 500 mg/day (see Data ). Advise pregnant women of the potential risk to a fetus.
The background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies are 2 to 4% and 15 to 20%, respectively.
Data
Animal Data
In a rat fertility and early embryonic development study, bosutinib was administered orally to female rats for approximately 3 to 6 weeks, depending on day of mating (2 weeks prior to cohabitation with untreated breeder males until gestation day [GD] 7). Increased embryonic resorptions occurred at greater than or equal to 10 mg/kg/day of bosutinib (1.6 and 1.2 times the human exposure at the recommended doses of 400 or 500 mg/day, respectively), and decreased implantations and reduced number of viable embryos at 30 mg/kg/day of bosutinib (3.4 and 2.5 times the human exposure at the recommended doses of 400 or 500 mg/day, respectively).
In an embryo-fetal development study conducted in rabbits, bosutinib was administered orally to pregnant animals during the period of organogenesis at doses of 3, 10 and 30 mg/kg/day. At the maternally-toxic dose of 30 mg/kg/day of bosutinib, there were fetal anomalies (fused sternebrae, and 2 fetuses had various visceral observations), and an approximate 6% decrease in fetal body weight. The dose of 30 mg/kg/day resulted in exposures (AUC) approximately 5.1 and 3.8 times the human exposures at the recommended doses of 400 and 500 mg/day, respectively.
Fetal exposure to bosutinib-derived radioactivity during pregnancy was demonstrated in a placental-transfer study in pregnant rats. In a rat pre-and postnatal development study, bosutinib was administered orally to pregnant animals during the period of organogenesis through lactation day 20 at doses of 10, 30, and 70 mg/kg/day. Reduced number of pups born occurred at greater than or equal to 30 mg/kg/day bosutinib (3.4 and 2.5 times the human exposure at the recommended doses of 400 or 500 mg/day, respectively), and increased incidence of total litter loss and decreased growth of offspring after birth occurred at 70 mg/kg/day bosutinib (6.9 and 5.1 times the human exposure at the recommended doses of 400 or 500 mg/day, respectively).
8.2 Lactation
Risk Summary
No data are available regarding the presence of bosutinib or its metabolites in human milk or its effects on a breastfed child or on milk production. However, bosutinib is present in the milk of lactating rats. Because of the potential for serious adverse reactions in a nursing child, breastfeeding is not recommended during treatment with bosutinib tablets and for 2 weeks after the last dose.
Animal Data
After a single radiolabeled bosutinib dose to lactating rats, radioactivity was present in the plasma of suckling offspring for 24 to 48 hours.
8.3 Females and Males of Reproductive Potential
Based on findings from animal studies, bosutinib tablets can cause fetal harm when administered to a pregnant woman [see Use in Specific Populations (8.1)].
Pregnancy
Females of reproductive potential should have a pregnancy test prior to starting treatment with bosutinib tablets.
Contraception
Females
Advise females of reproductive potential to use effective contraception (methods that result in less than 1% pregnancy rates) during treatment with bosutinib tablets and for 2 weeks after the last dose.
Infertility
The risk of infertility in females or males of reproductive potential has not been studied in humans. Based on findings from animal studies, bosutinib tablets may cause reduced fertility in females and males of reproductive potential [see Nonclinical Toxicology (13.1)].
8.4 Pediatric Use
The safety and effectiveness of bosutinib tablets in pediatric patients younger than 1 year of age with newly diagnosed CP Ph+ CML, pediatric patients younger than 1 year of age with CP Ph+ CML that is resistant or intolerant to prior therapy, and pediatric patients with AP Ph+ CML or BP Ph+ CML have not been established.
Pediatric use information is approved for PF PRISM CV’s BOSULIF® (bosutinib) tablets. However, due to PF PRISM CV’s marketing exclusivity rights, this drug product is not labeled with that information.
8.5 Geriatric Use
In the single-arm study in patients with CML who were resistant or intolerant to prior therapy of bosutinib tablets in patients with Ph+ CML, 20% were age 65 and over, 4% were 75 and over. No overall differences in safety or effectiveness were observed between these patients and younger patients, and other reported clinical experience has not identified differences in responses between the elderly and younger patients, but greater sensitivity of some older individuals cannot be ruled out.
8.6 Renal Impairment
Reduce the bosutinib tablets starting dose in patients with moderate (creatinine clearance [CLcr] 30 to 50 mL/min, estimated by Cockcroft-Gault (C-G)) and severe (CLcr less than 30 mL/min, C-G) renal impairment at baseline. For patients who have declining renal function while on bosutinib tablets who cannot tolerate the starting dose, follow dose adjustment recommendations for toxicity [see Dosage and Administration (2.3, 2.5) and Clinical Pharmacology (12.3)]. Bosutinib tablet has not been studied in patients undergoing hemodialysis.
8.7 Hepatic Impairment
Reduce the bosutinib tablets dosage in patients with hepatic impairment (Child-Pugh A, B, or C) [see Dosage and Administration (2.3, 2.5) and Clinical Pharmacology (12.3)].
10 OVERDOSAGE
Experience with bosutinib tablets overdose in clinical studies was limited to isolated cases. There were no reports of any serious adverse events associated with the overdoses. Patients who take an overdose of bosutinib tablets should be observed and given appropriate supportive treatment.
11 DESCRIPTION
Bosutinib tablet contains bosutinib, a kinase inhibitor. The chemical name for bosutinib is 3-Quinolinecarbonitrile, 4-[(2,4-dichloro-5-methoxyphenyl)amino]-6-methoxy-7-[3-(4-methyl-1-piperazinyl) propoxy]. Its chemical formula is C26H29Cl2N5O3; its molecular weight is 530.45. Bosutinib has the following chemical structure:
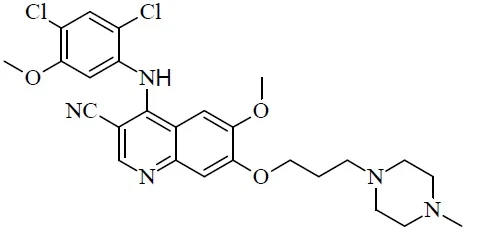
Bosutinib is a white to yellowish-tan powder. Bosutinib is freely soluble in dimethyl sulfoxide, very slightly soluble in ethyl acetate and practically insoluble in water.
Bosutinib tablets are supplied for oral administration in two strengths: 100 mg and 500 mg. Each strength reflects the equivalent amount of bosutinib content (on anhydrous basis). The tablets contain the following inactive ingredients: croscarmellose sodium, hypromellose, iron oxide red (for 500 mg tablet), iron oxide yellow (for 100 mg tablet), magnesium stearate, microcrystalline cellulose, poloxamer 188, polyethylene glycol 6000, povidone K-25, talc (for 500 mg tablet) and titanium dioxide.
12 CLINICAL PHARMACOLOGY
12.1 Mechanism of Action
Bosutinib is a TKI. Bosutinib inhibits the BCR-ABLkinase that promotes CML; it is also an inhibitor of Src-family kinases including Src, Lyn, and Hck. Bosutinib inhibited 16 of 18 imatinib-resistant forms of BCR-ABL kinase expressed in murine myeloid cell lines. Bosutinib did not inhibit the T315I and V299L mutant cells.
12.2 Pharmacodynamics
A greater likelihood of response and a greater likelihood of safety events were observed with higher bosutinib exposure in clinical studies. The time course of bosutinib pharmacodynamic response has not been fully characterized.
Cardiac Electrophysiology
At a single oral dose of 500 mg bosutinib tablet with ketoconazole (a strong CYP3A inhibitor), bosutinib tablets does not prolong the QT interval to any clinically relevant extent.
12.3 Pharmacokinetics
Bosutinib pharmacokinetics were assessed following oral dosing with food in adult patients with CML and were presented as geometric mean (CV%), unless otherwise specified.
Bosutinib exhibits dose proportional increases in Cmax and AUC over the oral dose range of 200 to 800 mg (0.33 to 1.3 times the maximum approved recommended dosage of 600 mg). Bosutinib steady state Cmax was 127 ng/mL (31%), Ctrough was 68 ng/mL (39%) and AUC was 2370 ng•h/mL (34%) following multiple oral doses of bosutinib tablets 400 mg; Bosutinib steady state Cmax was 171 ng/mL (38%),Ctrough was 91 ng/mL (42%) and AUC was 3150 ng•h/mL (38%) following multiple oral doses of bosutinib tablets 500 mg. No clinically significant differences in the pharmacokinetics of bosutinib were observed following administration of either the tablet or capsule dosage forms of bosutinib at the same dose, under fed conditions.
Absorption
The median bosutinib (minimum, maximum) time-to-Cmax (tmax) was 6 (6, 6) hours following oral administration of a single oral dose of bosutinib tablets 500 mg with food. The absolute bioavailability was 34% in healthy subjects.
Effect of Food
Bosutinib Cmax increased 1.8-fold and AUC increased 1.7-fold when bosutinib tablets were given with a high fat meal to healthy subjects compared to administration under fasted condition. The high-fat meal (800 to 1000 total calories) consisted of approximately 150 protein calories, 250 carbohydrate calories, and 500 to 600 fat calories.
Distribution
The mean (SD) apparent bosutinib volume of distribution is 6080 (1230) L after an oral dose of 500 mg of bosutinib. Bosutinib protein binding is 94% in vitro and 96% ex vivo, and is independent of concentration.
Elimination
The mean (SD) bosutinib terminal phase elimination half-life (t½) was 22.5 (1.7) hours, and the mean (SD) apparent clearance was 189 (48) L/h following a single oral dose of bosutinib tablets.
Metabolism
Bosutinib is primarily metabolized by CYP3A4.
Excretion
Following a single oral dose of [14C] radiolabeled bosutinib without food, 91.3% of the dose was recovered in feces and 3.3% of the dose recovered in urine.
Specific Populations
Patients with Renal Impairment
Bosutinib AUC increased 1.4-fold in subjects with moderate renal impairment (CLcr: 30 to 50 mL/min, estimated by Cockcroft-Gault (C-G)) and increased 1.6-fold in subjects with severe renal impairment (CLcr less than 30 mL/min) following a single oral dose of bosutinib tablets 200 mg (0.33 times the maximum approved recommended dosage of 600 mg). No clinically significant difference in the pharmacokinetics of bosutinib was observed in subjects with mild renal impairment (CLcr: 51 to 80 mL/min, C-G). Bosutinib tablets has not been studied in patients undergoing hemodialysis.
Patients with Hepatic Impairment
Bosutinib Cmax increased 2.4-fold, 2-fold, and 1.5-fold, and AUC increased 2.3-fold, 2-fold, and 1.9-fold in hepatic impairment Child-Pugh A, B, and C, respectively, following a single oral dose of bosutinib tablet 200 mg (0.33 times the maximum approved recommended dosage of 600 mg).
Drug Interaction Studies
Clinical Studies
Strong CYP3A Inhibitors: Bosutinib Cmax increased 5.2-fold and AUC increased 8.6-fold following a single dose of bosutinib tablets 100 mg (0.17 times the maximum approved recommended dosage) without food when used concomitantly with 400 mg ketoconazole (a strong CYP3A inhibitor) administered over multiple daily doses.
Moderate CYP3A Inhibitors: Bosutinib Cmax increased 1.5-fold and AUC increased 2.0-fold following a single dose of bosutinib tablet 500 mg with food when administered concomitantly with 125 mg aprepitant (a moderate CYP3A inhibitor).
Strong CYP3A Inducers: Bosutinib Cmax decreased by 86% and AUC decreased by 94% following a single dose of bosutinib tablet 500 mg with food administered concomitantly with multiple daily doses of 600 mg of rifampin (a strong CYP3A inducer).
Proton Pump Inhibitors: Lansoprazole decreased bosutinib Cmax by 46% and AUC by 26% following a single oral dose of bosutinib tablet 400 mg without food when used concomitantly with lansoprazole 60 mg (proton pump inhibitor) administered over multiple daily doses. Bosutinib displays pH-dependent aqueous solubility, in vitro [see Description (11)].
P-gp Substrates: No clinically significant differences in bosutinib pharmacokinetics were observed when used concomitantly with dabigatran etexilate mesylate (a P-glycoprotein (P-gp) substrate).
In Vitro Studies
Transporters Systems:
Bosutinib inhibits breast cancer resistance protein (BCRP) but, does not inhibit organic anion transporting polypeptide (OATP)1B1, OATP1B3, organic anion transporter (OAT)1, OAT3, organic cation transporter (OCT)1, and OCT2.
Pediatric use information is approved for PF PRISM CV’s BOSULIF® (bosutinib) tablets. However, due to PF PRISM CV’s marketing exclusivity rights, this drug product is not labeled with that information.
13 NONCLINICAL TOXICOLOGY
13.1 Carcinogenesis, Mutagenesis, Impairment of Fertility
Bosutinib was not carcinogenic in rats or transgenic mice. The rat 2-year carcinogenicity study was conducted at bosutinib oral doses up to 25 mg/kg in males and 15 mg/kg in females. Exposures at these doses were approximately 1.5 times (males) and 3.1 times (females) the human exposure at the 400 mg dose and 1.2 times (males) and 2.4 times (females) exposure in humans at the 500 mg dose. The 6-month RasH2 transgenic mouse carcinogenicity study was conducted at bosutinib oral doses up to 60 mg/kg.
Bosutinib was not mutagenic or clastogenic in a battery of tests, including the bacteria reverse mutation assay (Ames Test), the in vitro assay using human peripheral blood lymphocytes and the micronucleus test in orally treated male mice.
In a rat fertility study, drug-treated males were mated with untreated females, or untreated males were mated with drug-treated females. Females were administered the drug from pre-mating through early embryonic development. The dose of 70 mg/kg/day of bosutinib resulted in reduced fertility in males as demonstrated by 16% reduction in the number of pregnancies. There were no lesions in the male reproductive organs at this dose. This dose of 70 mg/kg/day resulted in exposure (AUC) in male rats approximately 1.5 times and equal to the human exposure at the recommended doses of 400 and 500 mg/day, respectively. Fertility (number of pregnancies) was not affected when female rats were treated with bosutinib. However, there were increased embryonic resorptions at greater than or equal to 10 mg/kg/day of bosutinib (1.6 and 1.2 times the human exposure at the recommended doses of 400 and 500 mg/day, respectively), and decreased implantations and reduced number of viable embryos at 30 mg/kg/day of bosutinib (3.4 and 2.5 times the human exposure at the recommended doses of 400 or 500 mg/day, respectively).
14 CLINICAL STUDIES
14.2 Adult Patients with Imatinib-Resistant or -Intolerant Ph+ CP, AP, and BP CML
Study 200 (NCT00261846), a single-arm open-label, multicenter study in patients with CML who were resistant or intolerant to prior therapy was conducted to evaluate the efficacy and safety of bosutinib tablets 500 mg once daily in patients with imatinib-resistant or -intolerant CML with separate cohorts for CP, AP, and BP disease previously treated with 1 prior TKI (imatinib) or more than 1 TKI (imatinib followed by dasatinib and/or nilotinib). The definition of imatinib resistance included (1) failure to achieve or maintain any hematologic improvement within 4 weeks; (2) failure to achieve a CHR by 3 months, cytogenetic response by 6 months or major cytogenetic response (MCyR) by 12 months; (3) progression of disease after a previous cytogenetic or hematologic response; or (4) presence of a genetic mutation in the BCR-ABL gene associated with imatinib resistance. Imatinib intolerance was defined as inability to tolerate imatinib due to toxicity, or progression on imatinib and inability to receive a higher dose due to toxicity. The definitions of resistance and intolerance to both dasatinib and nilotinib were similar to those for imatinib. The protocol was amended to exclude patients with a known history of the T315I mutation after 396 patients were enrolled in the trial.
The efficacy endpoints for patients with CP CML previously treated with 1 prior TKI (imatinib) were the rate of attaining MCyR by Week 24 and the duration of MCyR. The efficacy endpoints for patients with CP CML previously treated with both imatinib and at least 1 additional TKI were the cumulative rate of attaining MCyR by Week 24 and the duration of MCyR. The efficacy endpoints for patients with previously treated AP and BP CML were confirmed CHR and overall hematologic response (OHR).
The study enrolled 546 patients with CP, AP or BP CML. Of the total patient population 73% were imatinib resistant and 27% were imatinib intolerant. In this trial, 53% of patients were males, 65% were Caucasian, and 20% were 65 years old or older. Of the 546 treated patients, 506 were considered evaluable for cytogenetic or hematologic efficacy assessment. Patients were evaluable for efficacy if they had received at least 1 dose of bosutinib tablets and had a valid baseline efficacy assessment. Among evaluable patients, there were 262 patients with CP CML previously treated with 1 prior TKI (imatinib), 112 patients with CP CML previously treated with both imatinib and at least 1 additional TKI, and 132 patients with advanced phase CML previously treated with at least 1 TKI.
Median duration of bosutinib tablets treatment was 26 months in patients with CP CML previously treated with 1 TKI (imatinib), 9 months in patients with CP CML previously treated with imatinib and at least 1 additional TKI, 10 months in patients with AP CML previously treated with at least imatinib, and 3 months in patients with BP CML previously treated with at least imatinib.
The 24 week efficacy and MCyR at any time results are summarized in Table 14.
Table 14: Efficacy Results in Patients with Ph+ CP CML With Resistance to or Intolerance to Imatinib
Prior Treatment With Imatinib Only (N=262 evaluable) n (%) | Prior Treatment With Imatinib and Dasatinib or Nilotinib (N=112 evaluable) n (%) | |
By Week 24 MCyR (95% CI) | 105 (40.1) (34.1, 46.3) | 29 (25.9) (18.1, 35) |
| MCyR any time | 156 (59.5) (53.3, 65.5) | 45 (40.2) (31, 49.9) |
Abbreviations: CI=confidence interval; CML=chronic myelogenous leukemia; CP=chronic phase; MCyR=major cytogenetic response; N/n=number of patients; Ph+=Philadelphia chromosome positive.
The long-term follow-up data analysis was based on a minimum of 60 months for patients with CP CML treated with 1 prior TKI (imatinib) and a minimum of 48 months for patients with CP CML treated with imatinib and at least 1 additional TKI. For the 59.5% of patients with CP CML treated with 1 prior TKI (imatinib) who achieved a MCyR at any time, the median duration of MCyR was not reached. Among these patients, 65.4% and 42.9% had a MCyR lasting at least 18 and 54 months, respectively. For the 40.2% of patients with CP CML treated with imatinib and at least 1 additional TKI who achieved a MCyR at any time, the median duration of MCyR was not reached. Among these patients, 64.4% and 35.6% had a MCyR lasting at least 9 and 42 months, respectively. Of the 403 treated patients with CP CML, 20 patients had confirmed disease transformation to AP or BP while on treatment with bosutinib tablets.
The 48-week efficacy results in patients with accelerated and blast phases CML previously treated with at least imatinib are summarized in Table 15.
Table 15: Efficacy Results in Patients With Accelerated Phase and Blast Phase CML Previously Treated With at Least Imatinib
AP CML (N=72 evaluable) (n%) | BP CML (N=60 evaluable) n (%) | |
CHRa by Week 48 (95% CI) | 22 (30.6) (20.2, 42.5) | 10 (16.7) (8.3, 28.5) |
OHRa by Week 48 (95% CI) | 41 (56.9) (44.7, 68.6) | 17 (28.3) (17.5, 41.4) |
Abbreviations: AP=accelerated phase; BP=blast phase; CHR=complete hematologic response; CI=confidence interval; CML=chronic myelogenous leukemia; CI=confidence interval, OHR=overall hematologic response, CHR=complete hematologic response, N/n=number of patients
a. Overall hematologic response (OHR) = major hematologic response (complete hematologic response + no evidence of leukemia) or return to chronic phase (RCP). All responses were confirmed after 4 weeks. Complete hematologic response (CHR) for AP and BP CML: WBC less than or equal to institutional ULN, platelets greater than or equal to 100,000/mm3 and less than 450,000/mm3, absolute neutrophil count (ANC) greater than or equal to 1×10⁹ /L, no blasts or promyelocytes in peripheral blood, less than 5% myelocytes + metamyelocytes in bone marrow, less than 20% basophils in peripheral blood, and no extramedullary involvement. No evidence of leukemia (NEL): Meets all other criteria for CHR except may have thrombocytopenia (platelets greater than or equal to 20,000/mm3 and less than 100,000/mm3) and/or neutropenia (ANC greater than or equal to 0.5×10⁹ /L and less than 1×10⁹ /L). Return to chronic phase (RCP) = disappearance of features defining accelerated or blast phases but still in chronic phase.
The long-term follow-up data analysis was based on a minimum of 48 months for patients with AP CML and BP CML. Of the 79 treated patients with AP CML, 3 patients had confirmed disease transformation to BP while on bosutinib tablets treatment.
Pediatric use information is approved for PF PRISM CV’s BOSULIF® (bosutinib) tablets. However, due to PF PRISM CV’s marketing exclusivity rights, this drug product is not labeled with that information.
16 HOW SUPPLIED/STORAGE AND HANDLING
How Supplied
Bosutinib tablets are available in the following packaging configurations with a child-resistant (CR) closure. Bottle contains desiccants.
Bosutinib tablets 100 mg are yellow colored, oval shaped, biconvex, film coated tablet, debossed with L603 on one side and plain on other side.
NDC 46708-311-35 bottle of 120 tablets
Bosutinib tablets 500 mg are red colored, oval shaped, biconvex, film coated tablet debossed with L604 on one side and plain on the other.
NDC 46708-312-30 bottle of 30 tablets
Storage
Store at 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature].
Handling and Disposal
Procedures for proper disposal of anticancer drugs should be considered. Touching or handling crushed or broken tablets is to be avoided. Any unused product or waste material should be disposed of in accordance with local requirements, or drug take back programs.
17 PATIENT COUNSELING INFORMATION
Advise the patient to read the FDA-approved patient labeling (Patient Information).
- Dosage and Administration
Instruct patients to take bosutinib tablets exactly as prescribed, not to change their dose or to stop taking bosutinib tablets unless they are told to do so by their doctor. If patients miss a dose beyond 12 hours, they should be advised to take the next scheduled dose at its regular time. A double dose should not be taken to make up for any missed dose. Advise patients to take bosutinib tablets with food. Patients should be advised: “Swallow tablets whole. Do not crush, break, or cut tablet. Do not touch or handle crushed or broken tablets.”
- Gastrointestinal Toxicity
Advise patients that they may experience diarrhea, nausea, vomiting, abdominal pain, or blood in their stools with bosutinib tablets and to seek medical attention promptly for these symptoms [see Warnings and Precautions (5.1)].
- Myelosuppression
Advise patients of the possibility of developing low blood cell counts and to immediately report fever, any suggestion of infection, or signs or symptoms suggestive of bleeding or easy bruising [see Warnings and Precautions (5.2)].
- Hepatic Toxicity
Advise patients of the possibility of developing liver function abnormalities and to immediately report jaundice [see Warnings and Precautions (5.3)].
- Cardiovascular Toxicity
Advise patients that cardiac failure, left ventricular dysfunction, and cardiac ischemic events have been reported. Advise patients to seek immediate medical attention if any symptoms suggestive of cardiac failure and cardiac ischemia occur, such as shortness of breath, weight gain, or fluid retention [see Warnings and Precautions (5.4)].
- Fluid Retention
Advise patients of the possibility of developing fluid retention (swelling, weight gain, or shortness of breath) and to seek medical attention promptly if these symptoms arise [see Warnings and Precautions (5.5)].
- Renal Toxicity
Advise patients of the possibility of developing renal problems and to immediately report frequent urination, polyuria or oliguria [see Warnings and Precautions (5.6)].
- Adverse Reactions
Advise patients that they may experience other adverse reactions such as respiratory tract infections, rash, fatigue, headache, dizziness, back pain, arthralgia, or pruritus with bosutinib tablets and to seek medical attention if symptoms are significant. There is a possibility of anaphylactic shock [see Contraindications (4) and Adverse Reactions (6)].
- Embryo-Fetal Toxicity
Advise females to inform their healthcare provider if they are pregnant or become pregnant. Advise female patients of the risk to a fetus and potential loss of the pregnancy [see Use in Specific Populations (8.1)].
Advise females of reproductive potential, to use effective contraception during treatment and for 2 weeks after receiving the last dose of bosutinib tablets [see Warnings and Precautions (5.7) and Use in Specific Populations (8.1, 8.3)].
Advise lactating women not to breastfeed during treatment with bosutinib tablets and for 2 weeks after the last dose [see Use in Specific Populations (8.2)].
- Drug Interactions
Advise patients that bosutinib tablets and certain other medicines, including over the counter medications or herbal supplements (such as St. John’s wort) can interact with each other and may alter the effects of bosutinib tablets [see Drug Interactions (7)].
Manufactured by:
Alembic Pharmaceuticals Limited
Formulations Division II,
Panelav 389350, Gujarat, India
Revised: 05/2026