


Prescribing information (package insert) - Beqalzi
1 INDICATIONS AND USAGE
BEQALZI is indicated for the treatment of adult patients with relapsed or refractory mantle cell lymphoma (MCL) after at least two lines of systemic therapy, including a Bruton's tyrosine kinase (BTK) inhibitor.
This indication is approved under accelerated approval based on response rate and durability of response. Continued approval for this indication may be contingent upon verification and description of clinical benefit in a confirmatory trial(s) [see Clinical Studies (14.1)].
2 DOSAGE AND ADMINISTRATION
2.1 Important Safety Information
- BEQALZI can cause tumor lysis syndrome (TLS), especially during the ramp-up phase or during restart after a dosage interruption [see Warnings and Precautions (5.1)].
- Initiate BEQALZI with a dose ramp-up. For dose interruption lasting greater than 7 days, adjust the restart BEQALZI dose as instructed [see Dosage and Administration (2.3) and (2.4)].
- Assess patient risk for TLS and whether hospitalization for monitoring is warranted.
- Initiate prophylactic hydration and anti-hyperuricemics before the first dose of BEQALZI and continue as appropriate.
- Correct pre-existing electrolyte abnormalities before the first dose.
- Monitor blood chemistries closely [see Warnings and Precautions (5.1)].
2.2 Recommended Dosage for Mantle Cell Lymphoma
BEQALZI dosing begins with a 4-week ramp-up. The ramp-up dosing schedule is designed to gradually reduce tumor burden (debulk) and decrease the risk of TLS.
4-Week Dose Ramp-Up Schedule
Administer BEQALZI orally once daily, according to the ramp-up dosing schedule shown in Table 1.
Table 1: Dosing Schedule for 4-Week Ramp-Up Phase
| Week Number | Days | Daily Dose | Number of Tablets per Dose |
|---|---|---|---|
| Week 1 | Days 1 to 3 | 1 mg | One 1 mg tablet |
| Days 4 to 7 | 2 mg | Two 1 mg tablets | |
| Week 2 | Days 1 to 3 | 5 mg | One 5 mg tablet |
| Days 4 to 7 | 10 mg | Two 5 mg tablets | |
| Week 3 | Days 1 to 3 | 20 mg | One 20 mg tablet |
| Days 4 to 7 | 40 mg | Two 20 mg tablets | |
| Week 4 | Days 1 to 3 | 80 mg | One 80 mg tablet |
| Days 4 to 7 | 160 mg | Two 80 mg tablets |
The Starter Pack provides the first 4 weeks of BEQALZI according to the ramp-up schedule [see How Supplied/Storage and Handling (16)].
Target Dose Week 5 and Beyond
After completion of the 4-week ramp-up phase, the recommended dosage of BEQALZI is 320 mg (four 80 mg tablets) taken orally once daily until disease progression or unacceptable toxicity.
Dosing after treatment interruption greater than 7 days is described in Table 3 [see Dosage Modifications for Adverse Reactions (2.3)].
2.3 Dosage Modifications for Adverse Reactions
Table 2 provides recommended BEQALZI dosage modifications for adverse reactions.
Table 3 provides temporary dose modifications upon restart after dose interruptions lasting more than 7 days.
Table 4 provides recommended modifications to the target dose after adverse reactions are resolved.
Table 2: Recommended BEQALZI Dosage Modifications for Adverse Reactions
| Adverse ReactionAdverse reactions were graded using NCI CTCAE version 5.0. | Occurrence | Dosage Modification |
|---|---|---|
| Tumor Lysis Syndrome | ||
| Any blood chemistry changes or symptoms suggestive of TLS [see Warnings and Precautions (5.1)] | Any | Interrupt BEQALZI. Upon resolution of lab abnormalities, resume BEQALZI.
|
| Hematologic Toxicity | ||
| Grade ≥3 febrile neutropenia | First | Interrupt BEQALZI. Resume BEQALZI at the same dose upon recovery. |
| Second and subsequent | Interrupt BEQALZI.A maximum of 2 dose reductions is recommended. Upon recovery to Grade 1 or baseline level, resume BEQALZI and follow dose reduction guidelines in Table 3 and Table 4. | |
Platelet count <50,000/mm3 with significant bleeding Platelet count <25,000/mm3 Neutrophil count <500/mm3 lasting greater than 7 consecutive days | First | Interrupt BEQALZI. Resume BEQALZI at the same dose upon recovery to Grade 1 or baseline level. |
| Second and subsequent | Interrupt BEQALZI. Upon recovery to Grade 1 or baseline level, resume BEQALZI and follow dose reduction guidelines in Table 3 and Table 4. | |
| Nonhematologic Toxicity | ||
Grade 3 nonhematologic toxicityPatients may continue taking BEQALZI for the following:
| First | Interrupt BEQALZI. Upon recovery to Grade 1 or baseline level, resume BEQALZI at the same dose. |
| Second and subsequent | Interrupt BEQALZI. Upon recovery to Grade 1 or baseline level, resume BEQALZI and follow dose reduction guidelines in Table 3 and Table 4. | |
| Grade 4 nonhematologic toxicity | First | Interrupt BEQALZI. Upon recovery to Grade 1 or baseline level, resume BEQALZI and follow dose reduction guidelines in Table 3 and Table 4. |
| Second and subsequent | Interrupt BEQALZI. Upon recovery to Grade 1 or baseline level, resume BEQALZI and follow dose reduction guidelines in Table 3 and Table 4. | |
For patients with a dose interruption lasting 7 days or less:
- During ramp-up phase (Weeks 1 to 4): Resume BEQALZI and continue the remaining ramp-up schedule.
- During the target dose (Week 5 and beyond): Resume BEQALZI once the adverse reaction has resolved. Refer to Table 2 and Table 4 if a modified target dose is needed.
For patients with a dose interruption lasting more than 7 days:
- During ramp-up phase (Weeks 1 to 4): Restart BEQALZI at the dose shown in Table 3 based on the dose at the time of interruption, then re-escalate following the ramp-up schedule.
- During the target dose (Week 5 and beyond): Restart BEQALZI at the dose shown in Table 3 based on the dose at the time of interruption. Then, re-escalate to target dose determined per Table 4 when clinically appropriate.
Table 3: Dose to Restart BEQALZI After a Dose Interruption Greater than 7 Days
| Dose at Time of Interruption (mg) | Highest Restart Dose (mg)The physician may restart at a lower dose than noted. |
|---|---|
| 1 mg | 1 mgResume on Day 1 of the individual restart pack. Instruct patients to follow the dosing schedule printed on the blister card starting on Day 1 (1 tablet daily on Days 1 through 3, then 2 tablets daily on Days 4 through 7). |
| 2 mg | 1 mg |
| 5 mg | 2 mgResume on Day 4 of the individual restart pack. Instruct patients to remove and dispose of single tablets labeled Days 1 through 3 and restart taking tablets labeled Day 4 (2 tablets daily) of the individual restart pack. |
| 10 mg | 5 mg |
| 20 mg | 10 mg |
| 40 mg | 20 mg |
| 80 mg | 40 mg |
| 160 mg | 80 mg |
| 320 mg | 160 mg |
Table 4: Recommended Modification of Target Dose Level for Adverse Reactions
| Target Dose Level at Interruption | Modified Target Dose Level |
|---|---|
| 320 mg | 160 mg |
| 160 mg | 80 mg |
| 80 mg | Discontinue |
2.4 Dosage Modifications for Drug Interactions
Strong or Moderate CYP3A Inhibitors
Concomitant strong CYP3A inhibitors are contraindicated at initiation and during ramp-up of BEQALZI. For dose adjustments after ramp-up, see Table 5. Avoid moderate CYP3A inhibitors during initiation and at the 1 mg and 2 mg dose of sonrotoclax.
Table 5: Management of Potential BEQALZI Interactions with CYP3A Inhibitors
| Concomitant Drug | During Initiation and Ramp-Up Phase | Target Daily Dose (after ramp-up phase) |
|---|---|---|
| Strong CYP3A inhibitors | Contraindicated | Reduce BEQALZI dose to 20 mg. |
| Moderate CYP3A inhibitorsConsider alternative medicinal products or reduce the sonrotoclax dose as described in Table 6. | Avoid concomitant use of moderate CYP3A inhibitors at 1 mg and 2 mg dose of sonrotoclax. Reduce all other doses of sonrotoclax by at least 4-fold (see Table 6). | Reduce BEQALZI dose to 80 mg. |
Resume the BEQALZI dosage that was used prior to treatment with a strong or moderate CYP3A inhibitor at least 5 days after discontinuation of the inhibitor.
Table 6: BEQALZI Dose with Moderate CYP3A Inhibitor
| Original Sonrotoclax Dose (mg) | Sonrotoclax Dose When Administered with a Moderate CYP3A Inhibitor |
|---|---|
| 1 mg | Avoid moderate CYP3A inhibitor |
| 2 mg | Avoid moderate CYP3A inhibitor |
| 5 mg | 1 mg |
| 10 mg | 2 mg |
| 20 mg | 5 mg |
| 40 mg | 10 mg |
| 80 mg | 20 mg |
| 160 mg | 40 mg |
| 320 mg | 80 mg |
2.5 Administration
Take BEQALZI tablets with a meal once a day at the same approximate time. Swallow tablets whole with a glass of water. Do not break, chew, or crush the tablets.
Missed Dose
If a dose of BEQALZI is missed within 8 hours of when it is usually taken, instruct the patient to take the missed dose as soon as possible with a meal and resume the normal daily dosing schedule. If a dose is missed by more than 8 hours, instruct the patient to not take the missed dose, and resume the usual dosing schedule the next day.
If the patient vomits following a dose, instruct the patient to not take an additional dose that day, and resume the usual dosing schedule the next day.
3 DOSAGE FORMS AND STRENGTHS
| Tablet Strength | Description |
|---|---|
| 1 mg | Purple, oval, film-coated tablets with 1 debossed on one side. |
| 5 mg | Purple, oval, film-coated tablets with 5 debossed on one side. |
| 20 mg | Purple, oblong, film-coated tablets with 20 debossed on one side. |
| 80 mg | Purple, oval, film-coated tablets with 80 debossed on one side. |
4 CONTRAINDICATIONS
Concomitant use of sonrotoclax with strong CYP3A inhibitors at initiation and during the ramp-up phase is contraindicated in patients due to the potential for increased risk of tumor lysis syndrome [see Drug Interactions (7.1)].
5 WARNINGS AND PRECAUTIONS
5.1 Tumor Lysis Syndrome
BEQALZI can cause serious or life-threatening tumor lysis syndrome (TLS). BEQALZI can cause rapid reduction in tumor and changes in blood chemistries consistent with TLS that require prompt management. This can occur as early as 4 hours after the first dose, at any dose increases, and upon restart following dosage interruption. Laboratory or clinical TLS occurred in 7% of the 115 patients with MCL who followed the recommended dose ramp-up.
Risk factors for TLS include higher tumor burden such as bulky lymphadenopathy or lymphocytosis and reduced renal function.
Assess all patients for TLS risk and provide appropriate prophylaxis, including hydration and anti-hyperuricemics begun prior to the first dose of BEQALZI. Correct relevant chemistry abnormalities prior to starting BEQALZI. Consider hospitalization with intravenous hydration and monitoring and employ more frequent monitoring for patients with high TLS risk. Monitor blood chemistries and manage abnormalities promptly. Interrupt dosing if needed; when restarting BEQALZI, follow the dose modification guidance [see Dosage and Administration (2.3)].
Concomitant use of sonrotoclax with strong or moderate CYP3A inhibitors increases sonrotoclax exposure, which may increase the risk of TLS at initiation and during the ramp-up phase [see Dosage and Administration (2.4) and Drug Interactions (7.1)].
5.2 Serious Infections
BEQALZI can cause fatal or serious infections [see Adverse Reactions (6.1)]. Among patients who received BEQALZI at the recommended dosage in the clinical trial, serious infections occurred in 14% of patients and Grade 3 or higher infections in 17%, with fatal infections in 2.6% of patients. The most common Grade 3 or greater infection was pneumonia (10%). Monitor for signs and symptoms of infection and treat appropriately. Consider prophylactic antimicrobials and immunoglobulins according to guidelines. Withhold or dose reduce BEQALZI based on severity [see Dosage and Administration (2.3)].
5.3 Neutropenia
BEQALZI can cause serious or severe cytopenias, including neutropenia.
Among 115 patients with MCL who received BEQALZI, new or worsening Grade 3 or 4 decrease in neutrophils developed in 18% (Grade 4, 6%). Febrile neutropenia occurred in 1.7% of patients. Monitor complete blood counts throughout treatment. Based on severity, reduce dose, interrupt, or permanently discontinue BEQALZI [see Dosage and Administration (2.3)].
5.4 Embryo-Fetal Toxicity
Based on findings in animals and its mechanism of action, BEQALZI can cause fetal harm when administered to a pregnant woman. In embryo-fetal development toxicity studies conducted in pregnant mice and rabbits, oral administration of sonrotoclax during the period of organogenesis caused adverse developmental outcomes, including structural abnormalities and altered fetal growth at approximately ≥2 times the clinical exposure based on the area under the concentration-time curve (AUC) at the recommended dose in humans (320 mg/day).
Advise patients of the potential risk to a fetus. Advise females of reproductive potential to use effective contraception during treatment with BEQALZI and for 1 week after the last dose. Advise males with female partners of reproductive potential to use effective contraception during treatment and for 1 week after the last dose [see Use in Specific Populations (8.1, 8.3)].
6 ADVERSE REACTIONS
The following clinically significant adverse reactions are described elsewhere in the labeling:
- Tumor Lysis Syndrome [see Warnings and Precautions (5.1)]
- Serious Infections [see Warnings and Precautions (5.2)]
- Neutropenia [see Warnings and Precautions (5.3)]
6.1 Clinical Trials Experience
Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice.
Mantle Cell Lymphoma
The safety of BEQALZI was evaluated in 115 adult patients with previously treated MCL in a single-arm, multicenter clinical trial, BGB-11417-201 (NCT05471843) [see Clinical Studies (14.1)]. The trial required prior receipt of anti-CD20–based therapy and a BTK inhibitor. The trial excluded patients on moderate or strong CYP3A inhibitors or strong CYP3A inducers and required an absolute neutrophil count (ANC) ≥1000/mm3; platelets ≥75,000/mm3; creatinine clearance ≥50 mL/min; AST and ALT ≤3 × upper limit of normal (ULN); and serum total bilirubin ≤2 × ULN.
Patients received BEQALZI 320 mg orally once daily following completion of a 4-week ramp-up dosing schedule. Of the 115 patients who received BEQALZI, 52% were exposed for at least 6 months and 34% were exposed for at least 1 year.
Serious adverse reactions were reported in 37% of patients who received BEQALZI, most frequently (≥2%) from pneumonia (10%). Fatal adverse reactions occurred in 4.3% of patients, including from pneumonia (2.6%) and sudden death (1.7%).
Adverse reactions led to dose interruption of BEQALZI in 27% of patients, dose reduction in 0.9%, and permanent discontinuation in 8%. The most common reasons for dose interruption were infections (10%) and neutropenia (5%). The most common adverse reaction leading to treatment discontinuation was infection (1.7%).
Table 7 summarizes select adverse reactions in Study BGB-11417-201, excluding laboratory terms.
Table 7: Adverse Reactions (≥10%) in Patients with MCL Who Received BEQALZI in BGB-11417-201
| Adverse Reaction | BEQALZI (N=115) | |
|---|---|---|
| All Grades (%) | Grade 3 or 4 (%) | |
| Infections | ||
| PneumoniaIncludes pneumonia, COVID-19 pneumonia, pneumonia bacterial, and other related terms. | 16Additionally includes three fatal cases (2.6%) of pneumonia. | 10 |
| Upper respiratory tract infectionIncludes upper respiratory tract infection, pharyngitis, sinusitis, and other related terms. | 12 | 1.7 |
| General Disorders | ||
| FatigueIncludes fatigue and asthenia. | 16 | 0.9 |
| EdemaIncludes edema peripheral, generalized edema, and other related terms. | 14 | 0 |
| Pyrexia | 10 | 0.9 |
| Gastrointestinal Disorders | ||
| Diarrhea | 14 | 1.7 |
| Constipation | 10 | 0 |
| Skin and Subcutaneous Tissue Disorders | ||
| RashIncludes rash, dermatitis, drug eruption, and other related terms. | 10 | 0 |
| Musculoskeletal and Connective Tissue Disorders | ||
| Musculoskeletal painIncludes musculoskeletal pain, back pain, bone pain, and other related terms. | 10 | 0 |
Clinically relevant adverse reactions in <10% of patients who received BEQALZI included: TLS, headache, nausea, vomiting, mucositis, peripheral sensory neuropathy, febrile neutropenia, pneumonitis, herpes zoster infection, and sepsis.
Table 8 summarizes new or worsening laboratory abnormalities throughout treatment. Grade 4 laboratory abnormalities in ≥2% of patients included decreases in neutrophils (6%) and platelet count (3.5%).
Table 8: Select Laboratory Abnormalities (≥20%) That Worsened from Baseline in Patients with Previously Treated MCL Who Received BEQALZI
| Laboratory AbnormalityThe denominator used to calculate the rate varied from 103 to 115 based on the number of patients with a baseline value and at least one post-treatment value. | BEQALZI | |
|---|---|---|
| All Grades, % | Grade 3 or 4 (%) | |
| Hematology | ||
| Lymphocytes decreased | 66 | 29 |
| Hemoglobin decreased | 52 | 9 |
| Neutrophils decreased | 50 | 18 |
| Platelets decreased | 36 | 9 |
| Chemistry | ||
| Calcium decreased | 42 | 1.7 |
| Uric acid increased | 42 | 0 |
| Glucose increased | 35 | 0 |
| Creatinine increased | 32 | 1.7 |
| Potassium decreased | 30 | 4.3 |
| Sodium decreased | 29 | 9 |
| Aspartate aminotransferase increased | 27 | 2.8 |
| Alkaline phosphatase increased | 25 | 0 |
| Alanine aminotransferase increased | 22 | 0.9 |
| Calcium increased | 21 | 0 |
7 DRUG INTERACTIONS
7.1 Effects of Other Drugs on BEQALZI
Strong or Moderate CYP3A Inhibitors
Concomitant use of strong CYP3A inhibitors during the initiation and ramp-up phase with BEQALZI is contraindicated. After the ramp-up phase, reduce the target dose of BEQALZI as in Table 5 [see Dosage and Administration (2.4)].
For dose modifications of sonrotoclax with moderate CYP3A inhibitors, see Dosage and Administration (2.4).
Sonrotoclax is a CYP3A substrate [see Clinical Pharmacology (12.3)]. Concomitant use with strong and moderate CYP3A inhibitors increase sonrotoclax exposure [see Clinical Pharmacology (12.3)], which may increase the risk of BEQALZI adverse reactions.
Strong or Moderate CYP3A Inducers
Avoid concomitant use of strong or moderate CYP3A inducers with BEQALZI.
Sonrotoclax is a CYP3A substrate [see Clinical Pharmacology (12.3)]. Concomitant use with strong CYP3A inducers decreases sonrotoclax exposure [see Clinical Pharmacology (12.3)], which may reduce effectiveness of sonrotoclax.
8 USE IN SPECIFIC POPULATIONS
8.1 Pregnancy
Risk Summary
Based on findings in animals and its mechanism of action [see Clinical Pharmacology (12.1)], BEQALZI can cause embryo-fetal harm when administered to pregnant women. There are no available data on BEQALZI use in pregnant women to evaluate for a drug-associated risk.
In animal reproduction studies, oral administration of sonrotoclax to pregnant mice and rabbits during the period of organogenesis resulted in adverse developmental outcomes, including structural abnormalities and altered fetal growth, at maternal exposures approximately ≥2 times the human exposure (AUC) at the recommended dose of 320 mg daily (see Data). Advise patients of the potential risk to a fetus.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Data
Animal Data
Sonrotoclax was administered orally to pregnant mice at doses of 100, 300, and 1000 mg/kg/day during organogenesis (gestation days 6-15). Decreased fetal body weight and crown-rump length were noted at all doses. At the dose of 100 mg/kg/day in mice, the maternal exposure was approximately 8 times the human exposure at the recommended dose of 320 mg once daily.
Sonrotoclax was administered orally to pregnant rabbits at doses of 15, 75, and 300 mg/kg/day during organogenesis (gestation days 6-19). Fetal external (absent or open eye, cleft lip, misshapen mouth, acephalostoma) malformations were noted at 300 mg/kg/day. At the dose of 300 mg/kg/day in rabbits, the maternal exposure was approximately 2 times the human exposure at the recommended dose of 320 mg once daily.
8.2 Lactation
Risk Summary
There are no data on the presence of sonrotoclax or its metabolites in human milk or the effects on the breastfed child or milk production. Because of the potential for serious adverse reactions in a breastfed child, advise women not to breastfeed during treatment with BEQALZI and for 1 week after the last dose.
8.3 Females and Males of Reproductive Potential
Based on findings in animals and its mechanism of action, BEQALZI can cause fetal harm when administered to pregnant women [see Use in Specific Populations (8.1)].
Pregnancy Testing
Verify pregnancy status in females of reproductive potential prior to initiating BEQALZI.
Contraception
Females
Advise females of reproductive potential to use effective contraception during treatment with BEQALZI and for 1 week after the last dose.
Males
Advise males with female partners of reproductive potential to use effective contraception during treatment with BEQALZI and for 1 week after the last dose.
Infertility
Based on findings in animals, BEQALZI may impair male and female fertility. Fertility findings were reversible in animals [see Nonclinical Toxicology (13.1)].
8.4 Pediatric Use
The safety and effectiveness of BEQALZI in pediatric patients have not been established.
8.5 Geriatric Use
Of the 115 patients with MCL who were treated with BEQALZI, 74 (64%) were 65 years old or older and 26 (23%) were 75 years old or older. Patients aged 65 years and older experienced higher rates of serious adverse reactions (42%) compared to younger patients (29%). Clinical studies of BEQALZI did not include sufficient numbers of patients to determine whether efficacy differs in patients 65 years of age or older compared to younger patients.
8.6 Renal Impairment
No dose adjustments are recommended for patients with mild or moderate renal impairment (estimated glomerular filtration rate (eGFR) ≥30 mL/min). BEQALZI has not been studied in patients with severe renal impairment (eGFR <30 mL/min) [see Clinical Pharmacology (12.3)].
8.7 Hepatic Impairment
No dose adjustments are recommended for patients with mild or moderate hepatic impairment (bilirubin ≤3 × upper limit of normal [ULN] and any aspartate aminotransferase [AST]). BEQALZI has not been studied in patients with severe hepatic impairment (bilirubin >3 × ULN and any AST) [see Clinical Pharmacology (12.3)].
11 DESCRIPTION
BEQALZI tablets contain sonrotoclax, a B-cell lymphoma 2 (BCL-2) inhibitor. The molecular formula of sonrotoclax is C49H59N7O7S and the chemical name is N-[4-({[(1r,4r)-4-hydroxy-4-methylcyclohexyl]methyl}amino)-3-nitrobenzene-1-sulfonyl]-4-(2-{(2S)-2-[2-(propan-2-yl)phenyl]pyrrolidin-1-yl}-7-azaspiro[3.5]nonan-7-yl)-2-[(1H-pyrrolo[2,3- b]pyridin-5-yl)oxy]benzamide.
The molecular weight of sonrotoclax is 890.11 Daltons.
Sonrotoclax has the following structure:
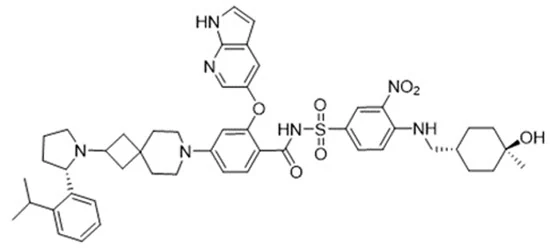
BEQALZI tablets for oral use contain 1, 5, 20, or 80 mg of sonrotoclax. Each tablet contains the following inactive ingredients: anhydrous dibasic calcium phosphate, colloidal silicon dioxide (20 and 80 mg only), croscarmellose sodium, hydroxypropyl methylcellulose acetate succinate, magnesium stearate, microcrystalline cellulose, talc (20 and 80 mg only). The tablet film coating contains FD&C Blue No. 1/brilliant blue FCF aluminum lake, FD&C Red No. 40/allura red ac aluminum lake, polyethylene glycol, polyvinyl alcohol, soy lecithin, talc, and titanium dioxide.
12 CLINICAL PHARMACOLOGY
12.1 Mechanism of Action
Sonrotoclax is an inhibitor of B-cell lymphoma 2 (BCL-2) protein. Overexpression of BCL-2 in various cancers mediates cell survival and has been associated with chemotherapeutic resistance. Sonrotoclax binds to the BCL-2 protein, displacing pro-apoptotic proteins, thereby inducing apoptosis of cells. In nonclinical studies, sonrotoclax demonstrated cytotoxicity in cancer cells overexpressing BCL-2, with a series of intrinsic apoptotic events, including caspase activation.
12.2 Pharmacodynamics
Sonrotoclax exposure-response relationships and the time course of pharmacodynamic response have not been fully characterized.
Cardiac Electrophysiology
Administration of sonrotoclax has the potential to increase the QTc interval. The largest mean increase in QTc interval was 7 ms (upper confidence interval = 14 ms) after administration of sonrotoclax (320 mg once daily) with a low-fat meal in patients with mature B-cell malignancies. There is insufficient information to characterize the QTc effects of sonrotoclax at higher concentrations above recommended dose.
12.3 Pharmacokinetics
Sonrotoclax pharmacokinetics were determined following a single dose or at steady state at the approved recommended dosage of 320 mg once daily and are presented as mean (CV%), unless otherwise specified.
Sonrotoclax area under the plasma drug concentration-time curve (AUC0-24 h) is 3395 (55%) ng∙h/mL and maximum plasma concentration (Cmax) is 353 (49%) ng/mL, following 320 mg once daily with a low-fat meal. Sonrotoclax Cmax and AUC0-tau increase in a less than dose proportional manner over the dosage range of 320 mg to 640 mg (1 to 2 times the highest approved recommended dosage). Limited systemic accumulation of sonrotoclax was observed following repeated administration.
Absorption
The median Tmax of sonrotoclax is 4 hours (ranged from 1 to 8 hours) following 320 mg once daily dosing.
Effect of Food
Sonrotoclax AUC and Cmax increased by approximately 1.5-fold following administration with a low-fat meal (approximately 333-500 kilocalories, 25% fat calories). Sonrotoclax AUC increased by 2-fold and Cmax by 2.4-fold following administration with a high-fat meal (1000 kilocalories, 50% fat).
Distribution
The geometric mean apparent volume of distribution of sonrotoclax is 482 (38%) L. Sonrotoclax plasma protein binding is 99% across a concentration range of 1 to 10 µM. The blood-to-plasma ratio is 0.6 to 0.7.
Elimination
The mean terminal elimination half-life (t½) of sonrotoclax ranges from 4 to 6 hours. The geometric mean apparent oral clearance (CL/F) of sonrotoclax is 94 (62%) L/h.
Metabolism
Sonrotoclax is primarily metabolized by CYP3A and to a lesser extent by CYP2C8 in vitro.
Excretion
After a single radiolabeled sonrotoclax dose of 20 mg to healthy subjects, approximately 86% of the dose was recovered in feces (19.5% unchanged) and 0.28% in urine (0.04% unchanged).
Specific Populations
No clinically meaningful differences in the pharmacokinetics of sonrotoclax were observed based on race, age (27-91 years), sex, weight (37-165 kg), mild to moderate renal impairment (eGFR ≥30 mL/min) or mild to moderate hepatic impairment (bilirubin ≤3 × upper limit of normal (ULN) and any aspartate aminotransferase (AST)). The effect of severe renal impairment (eGFR <30 mL/min) or severe hepatic impairment (total bilirubin >3 × ULN with any AST) on sonrotoclax pharmacokinetics is unknown.
Drug Interactions Studies
Clinical Studies and Model-Informed Approaches
Strong CYP3A inhibitors:
Sonrotoclax AUC increased 11-fold and Cmax increased 4-fold following concomitant administration of itraconazole (strong CYP3A inhibitor and P-gp inhibitor).
Sonrotoclax AUC increased 13-fold and Cmax increased 7-fold following concomitant administration of posaconazole (strong CYP3A inhibitor).
Strong CYP3A inducers: Sonrotoclax AUC decreased to 35% and Cmax to 58% following concomitant use of phenytoin (strong CYP3A inducer).
Other drugs: No clinically significant differences in sonrotoclax pharmacokinetics were observed following concomitant administration with gastric acid reducing agents (proton pump inhibitors, H2-receptor antagonists).
In Vitro Studies
CYP450 Enzymes: Sonrotoclax is not an inhibitor of CYP1A2, CYP2B6, CYP2C8, CYP2C9, CYP2C19, and CYP2D6. Sonrotoclax inhibits CYP3A in vitro, but this is not anticipated to have a clinically meaningful impact. Sonrotoclax is not an inducer of CYP1A2, CYP2B6, or CYP3A4.
Transporters: Sonrotoclax is a substrate of P-gp and BCRP but not OATP1B1 or OATP1B3. Sonrotoclax does not inhibit P-gp, BCRP OATP1B1, OATP1B3, OAT1, OAT3, OCT1, OCT2, MATE1, or MATE2-K.
13 NONCLINICAL TOXICOLOGY
13.1 Carcinogenesis, Mutagenesis, Impairment of Fertility
Carcinogenesis
Carcinogenicity studies have not been conducted with sonrotoclax.
Mutagenesis
Sonrotoclax was not mutagenic in a bacterial mutagenicity (Ames) assay and not clastogenic in a chromosome aberration assay in mammalian cells or in an in vivo bone marrow micronucleus assay in mice.
Impairment of Fertility
Fertility studies in animals have not been conducted with sonrotoclax. In a repeat dose, 13-week toxicity study in mice treated with oral administration of sonrotoclax at 20, 100, or 300 mg/kg/day, changes were reported in female reproductive organs at all doses, including the development of ovarian cysts, vaginal mucification, and uterine atrophy. At the dose of 20 mg/kg/day in mice, exposures (AUC) were approximately the same as the human exposure at the recommended dose. In a repeat dose, 13-week toxicity study in dogs treated with oral administration of sonrotoclax at 10, 30, or 100 mg/kg/day, changes were reported in male reproductive organs at all doses, including atrophy, necrosis, and vacuolation of the epididymis with reduced sperm, and atrophy of the prostate and testis. At the dose of 10 mg/kg/day in dogs, exposures were approximately 2 times the human exposure at the recommended dose. Reversibility was noted in both species by the end of the recovery period.
14 CLINICAL STUDIES
14.1 Mantle Cell Lymphoma
The efficacy of BEQALZI was evaluated in a single-arm, multicenter clinical trial, BGB-11417-201 (NCT05471843). Efficacy was based on 103 adults with relapsed or refractory MCL who previously received anti-CD20–based therapy and a BTK inhibitor. The trial required an ANC ≥1000/mm3, platelets ≥75,000/mm3, and AST and ALT ≤3 × upper limit of normal (ULN). The trial excluded patients with central nervous system lymphoma, prior BCL-2 inhibitor, or an ECOG performance status >2.
Following completion of the ramp-up dosing schedule, patients received BEQALZI at 320 mg orally once daily.
The median age was 68 years (range: 39 to 85 years); 74% were male; 58% were White, 33% Asian, and 3% Black or African American. Most patients (93%) had an ECOG performance of 0 to 1.
Patients had a median of 3 prior lines of therapy (range: 1 to 8), with 89% having at least 2 and 60% having at least 3 prior lines of therapy. All patients were exposed to at least one covalent or noncovalent BTK inhibitor, most commonly ibrutinib (53%), zanubrutinib (27%), and pirtobrutinib (14%). Other prior therapies included lenalidomide in 19%, autologous HSCT in 17%, and CAR-T therapy in 2%. The simplified Mantle Cell Lymphoma International Prognostic Index (sMIPI) score was low in 35%, intermediate in 36%, and high in 29% of patients. High ≥30%) Ki-67 expression was detected in 35% of patients.
Efficacy was established based on overall response rate (ORR) and duration of response (DOR), as assessed by an independent review committee (IRC) using 2014 Lugano criteria. Efficacy results are shown in Table 9. The median time to response was 1.9 months (range: 1.6 to 6.2). The estimated median follow-up for DOR was 11.9 months.
Table 9: Efficacy Results per IRC in Patients with Previously Treated MCL
| Outcome | BEQALZI (N=103) |
|---|---|
| Abbreviations: CI: confidence interval; DOR: duration of response; NE: not estimable | |
| Overall Response Rate | |
| Overall response, n | 54 (52%) |
| (95% CI, %) | 42, 62 |
| Complete response, n | 16 (16%) |
| Partial response, n | 38 (37%) |
| Duration of Response | |
| Median DOR (95% CI), monthsKaplan-Meier estimate. | 15.8 (7.4, NE) |
16 HOW SUPPLIED/STORAGE AND HANDLING
How Supplied
| Package | Number of Tablets | NDC Number |
|---|---|---|
| Starter pack carton | Each starter pack carton contains 4 weekly blister pack wallets:
| 72579-015-04 |
| Individual restart packs | ||
| 1 mg wallet in carton (Week 1 wallet) | 11 × 1 mg tablets | 72579-020-01 |
| 5 mg wallet in carton (Week 2 wallet) | 11 × 5 mg tablets | 72579-017-01 |
| 20 mg wallet in carton (Week 3 wallet) | 11 × 20 mg tablets | 72579-025-01 |
| 80 mg wallet in carton (Week 4 wallet) | 11 × 80 mg tablets | 72579-022-01 |
| Additional packs | ||
| 20 mg wallet in carton | 14 × 20 mg tablets | 72579-025-02 |
| 80 mg bottle in carton | 120 × 80 mg tablets | 72579-022-08 |
BEQALZI 1 mg film-coated tablets are purple, oval, and debossed with 1 on one side.
BEQALZI 5 mg film-coated tablets are purple, oval, and debossed with 5 on one side.
BEQALZI 20 mg film-coated tablets are purple, oblong, and debossed with 20 on one side.
BEQALZI 80 mg film-coated tablets are purple, oval, and debossed with 80 on one side.
Storage
Store at 20°C to 25°C (68°F to 77°F); excursions permitted between 15°C and 30°C (59°F and 86°F) [See USP Controlled Room Temperature].
Storage of blister wallets: Store tablets in the original blister package; do not transfer the tablets to a different container.
17 PATIENT COUNSELING INFORMATION
Advise patients to read the FDA-approved patient labeling (Medication Guide).
Tumor Lysis Syndrome
Advise patients of the potential risk of TLS, particularly at treatment initiation, during the ramp-up phase, and with restarting the dose after an interruption, and to immediately report any signs and symptoms associated with this event (fever, chills, nausea, vomiting, confusion, shortness of breath, seizure, irregular heartbeat, decreased urination, unusual tiredness, muscle cramps or twitches) to their healthcare provider (HCP) for evaluation [see Warnings and Precautions (5.1)].
Advise patients to be adequately hydrated when taking BEQALZI to reduce the risk of TLS. The recommended volume is 6 to 8 glasses (approximately 1.5 to 2 liters) of water daily starting 1-2 days before taking BEQALZI, on the day of the first dose, on any day the dose is increased until target dose is reached, and at restart, if applicable [see Dosage and Administration (2.1)].
Advise patients of the importance of keeping scheduled appointments for blood work or other laboratory tests [see Dosage and Administration (2.1)].
Advise patients that it may be necessary to take BEQALZI in the hospital or medical office setting to allow monitoring for TLS.
Serious Infections
Advise patients to contact their healthcare provider immediately if they develop a fever or any signs of infection [see Warnings and Precautions (5.2)].
Neutropenia
Advise patients of the need for periodic monitoring of blood counts [see Warnings and Precautions (5.3)].
Drug Interactions
Advise patients to avoid consuming grapefruit products, Seville oranges, or star fruit during treatment with BEQALZI. BEQALZI may interact with some drugs; therefore, advise patients to inform their healthcare provider of the use of any prescription medication, over-the-counter drugs, vitamins, and herbal products [see Contraindications (4) and Drug Interactions (7.1)].
Embryo-Fetal Toxicity
Advise pregnant women and females of reproductive potential of the potential risk to a fetus. Advise females of reproductive potential to inform their healthcare provider of a known or suspected pregnancy [see Warnings and Precautions (5.4) and Use in Specific Populations (8.1)].
Advise females of reproductive potential to use effective contraception during treatment with BEQALZI and for 1 week after the last dose. Advise males with female partners of reproductive potential to use effective contraception during treatment with BEQALZI and for 1 week after the last dose [see Use in Specific Populations (8.3)].
Lactation
Advise women not to breastfeed during treatment with BEQALZI and for 1 week after the last dose [see Use in Specific Populations (8.2)].
Infertility
Advise males and females of reproductive potential that BEQALZI may impair fertility [see Use in Specific Populations (8.3)].
Administration Instructions
Advise patients to take BEQALZI exactly as prescribed and not to change their dose or to stop taking BEQALZI unless they are told to do so by their healthcare provider. Advise patients to take BEQALZI orally once daily, at approximately the same time each day, according to their healthcare provider's instructions and that the tablets should be swallowed whole with a meal and a glass of water without being broken, chewed, or crushed [see Dosage and Administration (2.5)].
Missed Dose
Advise patients if BEQALZI is missed within 8 hours, to take it as soon as possible with a meal on the same day with a return to the normal schedule the following day. If they miss a dose by more than 8 hours, advise patients to not take the missed dose and resume the usual dosing schedule the next day. Advise patients not to take any additional dose that day if they vomit after taking BEQALZI, and to take the next dose at the usual time the following day [see Dosage and Administration (2.5)].
Restarting After Treatment Interruption
Advise patients to contact their healthcare provider before restarting BEQALZI after stopping treatment. Advise patients that:
- Their healthcare provider will determine the correct dose based on their previous dose and how long they were off treatment.
- Depending on how long they were off treatment, they may resume at the same dose where they left off, or they may need to restart at a lower dose.
If needed, individual restart packs are available outside of the starter pack for restart dosing as prescribed by their healthcare provider.
- They may be instructed to resume dosing on Day 1 or Day 4 of the restart pack depending on their prescribed restart dose.
- If instructed to start on Day 4, they will not use all tablets in the blister pack and should remove and dispose of tablets from Days 1 through 3 in order to avoid confusion or accidental use.
- They should not use leftover packs from previous treatment without consulting their healthcare provider.
Manufactured for:
BeOne Medicines USA, Inc.
Pennington, NJ 08534
BEQALZI is a trademark owned by BeOne Medicines I GmbH or its affiliates.
©BeOne Medicines I GmbH 2026. All rights reserved.