


Prescribing information (package insert) - Apidra
1 INDICATIONS AND USAGE
APIDRA is indicated to improve glycemic control in adult and pediatric patients with diabetes mellitus.
2 DOSAGE AND ADMINISTRATION
2.1 Important Administration Instructions
- Always check insulin label before administration [see Warnings and Precautions (5.4)].
- Inspect visually for particulate matter and discoloration. Only use APIDRA if the solution appears clear and colorless.
- Use APIDRA SoloStar prefilled pen with caution in patients with visual impairment who may rely on audible clicks to dial their dose.
2.2 Route of Administration Instructions
Subcutaneous Injection
- Inject APIDRA subcutaneously within 15 minutes before a meal or within 20 minutes after starting a meal into the abdominal wall, thigh, or upper arm.
- Rotate injection sites within the same region from one injection to the next to reduce the risk of lipodystrophy and localized cutaneous amyloidosis. Do not inject into areas of lipodystrophy or localized cutaneous amyloidosis [see Warnings and Precautions (5.2), Adverse Reactions (6)].
- APIDRA given by subcutaneous injection should generally be used in regimens with an intermediate or long-acting insulin.
- The APIDRA SoloStar prefilled pen dials in 1-unit increments.
- Do not mix APIDRA for subcutaneous injection with insulins other than NPH insulin. If APIDRA is mixed with NPH insulin, draw APIDRA into the syringe first and inject immediately after mixing.
Continuous Subcutaneous Infusion (Insulin Pump)
- Refer to the continuous subcutaneous insulin infusion pump user manual to see if APIDRA can be used with the insulin pump. Use APIDRA in accordance with the insulin pump system's instructions for use.
- Administer APIDRA by continuous subcutaneous infusion in a region recommended in the instructions from the pump manufacturer. Rotate infusion sites within the same region to reduce the risk of lipodystrophy and localized cutaneous amyloidosis. [see Warnings and Precautions (5.2), Adverse Reactions (6)].
- Train patients using continuous subcutaneous insulin infusion pump therapy to administer insulin by injection and have alternate insulin therapy available in case of insulin pump failure [see Warnings and Precautions (5.8)].
- During changes to a patient's insulin regimen, increase the frequency of blood glucose monitoring [see Warnings and Precautions (5.2)].
- Change APIDRA in the reservoir at least every 48 hours or according to the pump user manual, whichever is shorter.
- Change the infusion sets and the infusion set insertion site according to the manufacturer's user manual.
- Do not dilute or mix APIDRA when administering by continuous subcutaneous infusion.
- Do not expose APIDRA in the pump reservoir to temperatures greater than 98.6°F (37°C).
Intravenous Administration
- Administer APIDRA intravenously only under medical supervision with close monitoring of blood glucose and potassium levels to avoid hypoglycemia and hypokalemia [see Warnings and Precautions (5.3, 5.5)].
- Dilute APIDRA to concentrations from 0.05 unit/mL to 1 unit/mL insulin glulisine in infusion systems using polyvinyl chloride (PVC) infusion bags.
- Diluted APIDRA is stable at room temperature for 48 hours only in normal saline solution (0.9% Sodium Chloride Injection, USP) [see How Supplied/Storage and Handling (16.2)].
- APIDRA is not compatible with Dextrose solution and Ringers solution.
2.3 Dosage Information
- Individualize and adjust the dosage of APIDRA based on the patient's metabolic needs, blood glucose monitoring results, and glycemic control goal.
- Dose adjustments may be needed when switching from another insulin, with changes in physical activity, changes in concomitant medications, changes in meal patterns (i.e., macronutrient content or timing of food intake), changes in renal or hepatic function, or during acute illness to minimize the risk of hypoglycemia or hyperglycemia [see Warnings and Precautions (5.2, 5.3), Drug Interactions (7), Use in Specific Populations (8.6, 8.7)].
3 DOSAGE FORMS AND STRENGTHS
Injection: 100 units per mL (U-100), a clear and colorless solution available as:
- 10 mL multiple-dose vial
- 3 mL single-patient-use APIDRA SoloStar prefilled pen
4 CONTRAINDICATIONS
APIDRA is contraindicated:
- during episodes of hypoglycemia
- in patients with known hypersensitivity to insulin glulisine or to any of the excipients in APIDRA; systemic allergic reactions have occurred with APIDRA [see Adverse Reactions (6.1)].
5 WARNINGS AND PRECAUTIONS
5.1 Never Share an APIDRA SoloStar Pen or Syringe or Needle between Patients
APIDRA SoloStar pens must never be shared between patients, even if the needle is changed. Patients using APIDRA vials must never reuse or share needles or syringes with another person. Sharing poses a risk for transmission of blood-borne pathogens.
5.2 Hyperglycemia or Hypoglycemia with Changes in Insulin Regimen
Changes in an insulin regimen (e.g., insulin, insulin strength, manufacturer, type, injection site or method of administration) may affect glycemic control and predispose to hypoglycemia [see Warnings and Precautions (5.3)] or hyperglycemia. Repeated insulin injections into areas of lipodystrophy or localized cutaneous amyloidosis have been reported to result in hyperglycemia; a sudden change in the injection site (to unaffected area) has been reported to result in hypoglycemia [see Adverse Reactions (6)].
Make any changes to a patient's insulin regimen under close medical supervision with increased frequency of blood glucose monitoring. Advise patients who have repeatedly injected into areas of lipodystrophy or localized cutaneous amyloidosis to change the injection site to unaffected areas and closely monitor for hypoglycemia. For patients with type 2 diabetes, dosage adjustments in concomitant oral antidiabetic treatment may be needed.
5.3 Hypoglycemia
Hypoglycemia is the most common adverse reaction of all insulins, including APIDRA [see Adverse Reactions (6.1)]. Severe hypoglycemia can cause seizures, may lead to unconsciousness, may be life-threatening, or cause death. Hypoglycemia can impair concentration ability and reaction time; this may place the patient and others at risk in situations where these abilities are important (e.g., driving or operating other machinery). APIDRA, or any insulin, should not be used during episodes of hypoglycemia [see Contraindications (4)].
Hypoglycemia can happen suddenly, and symptoms may differ in each patient and change over time in the same patient. Symptomatic awareness of hypoglycemia may be less pronounced in patients with longstanding diabetes, in patients with diabetic neuropathy, in patients using medications that block the sympathetic nervous system (e.g., beta-blockers) [see Drug Interactions (7)], or in patients who experience recurrent hypoglycemia.
Risk Factors for Hypoglycemia
The risk of hypoglycemia after an injection is related to the duration of action of the insulin and, in general, is highest when the glucose lowering effect of the insulin is maximal. The timing of hypoglycemia usually reflects the time-action profile of the administered insulin formulation. As with all insulins, the glucose lowering effect time course of APIDRA may vary in different individuals or at different times in the same individual and depends on many conditions, including the area of injection as well as the injection site blood supply and temperature [see Clinical Pharmacology (12.2)].
Other factors which may increase the risk of hypoglycemia include changes in meal pattern (e.g., macronutrient content or timing of meals), changes in level of physical activity, or changes to concomitant drugs [see Drug Interactions (7)]. Patients with renal or hepatic impairment may be at higher risk of hypoglycemia [see Use in Specific Populations (8.6, 8.7)].
Risk Mitigation Strategies for Hypoglycemia
Patients and caregivers must be educated to recognize and manage hypoglycemia. Self-monitoring of blood glucose plays an essential role in the prevention and management of hypoglycemia. In patients at higher risk for hypoglycemia and patients who have reduced symptomatic awareness of hypoglycemia, increased frequency of blood glucose monitoring is recommended.
5.4 Hypoglycemia Due to Medication Errors
Accidental mix-ups between insulin products have been reported. To avoid medication errors between APIDRA and other insulins, instruct patients to always check the insulin label before each injection [see Adverse Reactions (6.3)].
5.5 Hypokalemia
All insulins, including APIDRA, cause a shift in potassium from the extracellular to intracellular space, possibly leading to hypokalemia. Untreated hypokalemia may cause respiratory paralysis, ventricular arrhythmia, and death. Use caution in patients who may be at risk for hypokalemia (e.g., patients using potassium-lowering medications, patients taking medications sensitive to serum potassium concentrations).
5.6 Hypersensitivity Reactions
Severe, life-threatening, generalized allergy, including anaphylaxis, can occur with insulins, including APIDRA [see Adverse Reactions (6.1)]. If hypersensitivity reactions occur, discontinue APIDRA; treat per standard of care and monitor until symptoms and signs resolve. APIDRA is contraindicated in patients who have had a hypersensitivity reaction to insulin glulisine or any of its excipients.
5.7 Fluid Retention and Heart Failure with Concomitant Use of PPAR-Gamma Agonists
Thiazolidinediones (TZDs), which are peroxisome proliferator-activated receptor (PPAR) gamma agonists, can cause dose-related fluid retention, when used in combination with insulin. Fluid retention may lead to or exacerbate heart failure. Patients treated with insulin, including APIDRA and a PPAR-gamma agonist should be observed for signs and symptoms of heart failure. If heart failure develops, it should be managed according to current standards of care, and discontinuation or dose reduction of the PPAR-gamma agonist must be considered.
5.8 Hyperglycemia and Ketoacidosis Due to Insulin Pump Device Malfunction
Malfunction of the insulin pump or insulin infusion set or insulin degradation can rapidly lead to hyperglycemia and ketoacidosis. Prompt identification and correction of the cause of hyperglycemia or ketosis is necessary. Interim subcutaneous injections with APIDRA may be required. Patients using continuous subcutaneous insulin infusion pump therapy must be trained to administer insulin by injection and have alternate insulin therapy available in case of pump failure [see How Supplied/Storage and Handling (16.2)].
6 ADVERSE REACTIONS
The following adverse reactions are discussed elsewhere:
- Hypoglycemia [see Warnings and Precautions (5.3)]
- Hypoglycemia Due to Medication Errors [see Warnings and Precautions (5.4)]
- Hypokalemia [see Warnings and Precautions (5.5)]
- Hypersensitivity Reactions [see Warnings and Precautions (5.6)]
6.1 Clinical Trials Experience
Because clinical trials are conducted under widely varying designs, the adverse reaction rates reported in one clinical trial may not be easily compared to those rates reported in another clinical trial and may not reflect the rates actually observed in clinical practice.
The data in Table 1 reflect the exposure of 1591 patients with type 1 diabetes to APIDRA or comparators [see Clinical Studies (14.1)]. The type 1 diabetes population had the following characteristics: Mean age was 39.74 years. 54.5 % were male, 95.5% were Caucasian, 1.5% were Black or African American.
The data in Table 2 reflect the exposure of 1766 patients with type 2 diabetes to APIDRA or comparators [see Clinical Studies (14.2)]. The type 2 diabetes population had the following characteristics: Mean age was 59.08 years. 51.2% were male, 88.5% were Caucasian, 7.2% were Black or African American.
The frequencies of adverse drug reactions during APIDRA clinical trials in patients with type 1 diabetes mellitus and type 2 diabetes mellitus are listed in the tables below.
Table 1: Adverse Reactions Occurring ≥5% in Pooled Studies of Adults with Type 1 Diabetes
APIDRA, % (n=950) | All ComparatorsInsulin lispro, regular human insulin, insulin aspart, % (n=641) | |
|---|---|---|
| Nasopharyngitis | 10.6 | 12.9 |
| HypoglycemiaOnly severe symptomatic hypoglycemia | 6.8 | 6.7 |
| Upper respiratory tract infection | 6.6 | 5.6 |
| Influenza | 4.0 | 5.0 |
Table 2: Adverse Reactions Occurring ≥5% in Pooled Studies of Adults with Type 2 Diabetes
APIDRA, % (n=883) | Regular Human Insulin, % (n=883) | |
|---|---|---|
| Upper respiratory tract infection | 10.5 | 7.7 |
| Nasopharyngitis | 7.6 | 8.2 |
| Edema peripheral | 7.5 | 7.8 |
| Influenza | 6.2 | 4.2 |
| Arthralgia | 5.9 | 6.3 |
| Hypertension | 3.9 | 5.3 |
Pediatrics
Table 3 summarizes the adverse reactions occurring with frequency higher than 5% in a clinical study in pediatric patients with type 1 diabetes treated with APIDRA (n=277) or insulin lispro (n=295).
Table 3: Adverse Reactions Occurring ≥5% in Pediatric Patients with Type 1 Diabetes
APIDRA, % (n=277) | Insulin Lispro, % (n=295) | |
|---|---|---|
| Nasopharyngitis | 9.0 | 9.5 |
| Upper respiratory tract infection | 8.3 | 10.8 |
| Headache | 6.9 | 11.2 |
| Hypoglycemic seizure | 6.1 | 4.7 |
Severe Symptomatic Hypoglycemia
Hypoglycemia was the most commonly observed adverse reaction in patients treated with insulin, including APIDRA. The rates of reported hypoglycemia depend on the definition of hypoglycemia used, diabetes type, insulin dose, intensity of glucose control, background therapies, and other intrinsic and extrinsic patient factors. For these reasons, comparing rates of hypoglycemia in clinical trials for APIDRA with the incidence of hypoglycemia for other products may be misleading and also, may not be representative of hypoglycemia rates that occur in clinical practice. The rates and incidence of severe symptomatic hypoglycemia, defined as hypoglycemia requiring intervention from a third party are presented in Table 4. In the clinical trials, children and adolescents with type 1 diabetes had a higher incidence of severe symptomatic hypoglycemia in the two treatment groups compared to adults with type 1 diabetes (see Table 4) [see Clinical Studies (14)].
Table 4: Severe Symptomatic HypoglycemiaSevere symptomatic hypoglycemia defined as a hypoglycemic event requiring the assistance of another person that met one of the following criteria:
the event was associated with a whole blood referenced blood glucose <36 mg/dL or the event was associated with prompt recovery after oral carbohydrate, intravenous glucose, or glucagon administration.
Type 1 Diabetes Adults 12 weeks with insulin glargine | Type 1 Diabetes Adults 26 weeks with insulin glargine | Type 2 Diabetes Adults 26 weeks with NPH human insulin | Type 1 Diabetes Pediatrics 26 weeks | ||||||
|---|---|---|---|---|---|---|---|---|---|
APIDRA Pre meal | APIDRA Post meal | Regular Human Insulin | APIDRA | Insulin Lispro | APIDRA | Regular Human Insulin | APIDRA | Insulin Lispro | |
| Events per month per patient | 0.05 | 0.05 | 0.13 | 0.02 | 0.02 | 0.00 | 0.00 | 0.09 | 0.08 |
Percent of patients (n/total N) | 8.4% (24/286) | 8.4% (25/296) | 10.1% (28/278) | 4.8% (16/339) | 4.0% (13/333) | 1.4% (6/416) | 1.2% (5/420) | 16.2% (45/277) | 19.3% (57/295) |
Adverse Reactions with Continuous Subcutaneous Insulin Infusion (CSII)
In a 12-week randomized study in patients with type 1 diabetes (n=59), the rates of catheter occlusions and infusion site reactions were similar for APIDRA and insulin aspart–treated patients (see Table 5).
Table 5: Catheter Occlusions and Infusion Site Reactions
APIDRA (n=29) | Insulin Aspart (n=30) | |
|---|---|---|
| Catheter occlusions/month | 0.08 | 0.15 |
| Infusion site reactions | 10.3% (3/29) | 13.3% (4/30) |
Allergic Reactions
Severe, life-threatening, generalized allergy, including anaphylaxis, may occur with any insulin, including APIDRA. Generalized allergy to insulin may cause whole body rash (including pruritus), dyspnea, wheezing, hypotension, tachycardia, or diaphoresis.
In controlled clinical trials up to 12 months duration, potential systemic allergic reactions were reported in 79 of 1833 patients (4.3%) who received APIDRA and 58 of 1524 patients (3.8%) who received the comparator short-acting insulins. During these trials, treatment with APIDRA was permanently discontinued in 1 of 1833 patients due to a potential systemic allergic reaction.
Injection Site Reactions
As with any insulin, patients taking APIDRA may experience redness, swelling, or itching at the site of injection. These minor reactions usually resolve in a few days to a few weeks, but on some occasions may require discontinuation of APIDRA. In some instances, these reactions may be related to factors other than insulin, such as irritants in a skin cleansing agent or poor injection technique.
Insulin Initiation and Intensification of Glucose Control
Intensification or rapid improvement in glucose control has been associated with a transitory, reversible ophthalmologic refraction disorder, worsening of diabetic retinopathy, and acute painful peripheral neuropathy. However, long-term glycemic control decreases the risk of diabetic retinopathy and neuropathy.
Lipodystrophy
Long-term use of insulin, including APIDRA, can cause lipodystrophy at the site of repeated insulin injections or infusion. Lipodystrophy includes lipohypertrophy (thickening of adipose tissue) and lipoatrophy (thinning of adipose tissue) and may affect insulin absorption [see Dosage and Administration (2.2)].
Peripheral Edema
Insulins, including APIDRA, may cause sodium retention and edema, particularly if previously poor metabolic control is improved by intensified insulin therapy.
Weight Gain
Weight gain can occur with insulins, including APIDRA, and has been attributed to the anabolic effects of insulin and the decrease in glucosuria.
6.2 Immunogenicity
As with all therapeutic proteins, there is potential for immunogenicity. The detection of antibody formation is highly dependent on the sensitivity and specificity of the assay. Additionally, the observed incidence of antibody (including neutralizing antibody) positivity in an assay may be influenced by several factors including assay methodology, sample handling, timing of sample collection, concomitant medication, and underlying disease. For these reasons, comparison of the incidence of antibodies to APIDRA in the studies described below with the incidence of antibodies in other studies or to other insulin products may be misleading.
In a study in patients with type 1 diabetes (n=333), the concentrations of insulin antibodies that react with both human insulin and insulin glulisine (cross-reactive insulin antibodies) remained near baseline during the first 6 months of the study in the patients treated with APIDRA. A decrease in antibody concentration was observed during the following 6 months of the study. In a study in patients with type 2 diabetes (n=411), a similar increase in cross-reactive insulin antibody concentration was observed in the patients treated with APIDRA and in the patients treated with human insulin during the first 9 months of the study. Thereafter the concentration of antibodies decreased in the APIDRA patients and remained stable in the human insulin patients. There was no correlation between cross-reactive insulin antibody concentration and changes in HbA1c, insulin doses, or incidence of hypoglycemia. APIDRA did not elicit a significant antibody response in a study of pediatric patients with type 1 diabetes.
6.3 Postmarketing Experience
The following adverse reactions have been identified during postapproval use of APIDRA. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to estimate reliably their frequency or establish a causal relationship to drug exposure.
Medication errors have been reported in which other insulins, particularly long-acting insulins, have been accidentally administered instead of APIDRA.
Localized cutaneous amyloidosis at the injection site has occurred. Hyperglycemia has been reported with repeated insulin injections into areas of localized cutaneous amyloidosis; hypoglycemia has been reported with a sudden change to an unaffected injection site.
7 DRUG INTERACTIONS
Table 6: Clinically Significant Drug Interactions with APIDRA
| Drugs that May Increase the Risk of Hypoglycemia | |
| Drugs: | Antidiabetic agents, ACE inhibitors, angiotensin II receptor blocking agents, disopyramide, fibrates, fluoxetine, monoamine oxidase inhibitors, pentoxifylline, pramlintide, salicylates, somatostatin analog (e.g., octreotide), and sulfonamide antibiotics. |
| Intervention: | Dose adjustment and increased frequency of glucose monitoring may be required when APIDRA is coadministered with these drugs. |
| Drugs that May Decrease the Blood Glucose Lowering Effect of APIDRA | |
| Drugs: | Atypical antipsychotics, corticosteroids, danazol, diuretics, estrogens, glucagon, isoniazid, niacin, phenothiazine derivatives, progestogens (e.g., in oral contraceptives), protease inhibitors, somatropin, sympathomimetic agents (e.g., albuterol, epinephrine, terbutaline), and thyroid hormones. |
| Intervention: | Dose adjustment and increased frequency of glucose monitoring may be required when APIDRA is coadministered with these drugs. |
| Drugs that May Increase or Decrease the Blood Glucose Lowering Effect of APIDRA | |
| Drugs: | Alcohol, beta-blockers, clonidine, and lithium salts. Pentamidine may cause hypoglycemia, which may sometimes be followed by hyperglycemia. |
| Intervention: | Dose adjustment and increased frequency of glucose monitoring may be required when APIDRA is coadministered with these drugs. |
| Drugs that May Blunt Signs and Symptoms of Hypoglycemia | |
| Drugs: | Beta-blockers, clonidine, guanethidine, and reserpine. |
| Intervention: | Increased frequency of glucose monitoring may be required when APIDRA is coadministered with these drugs. |
8 USE IN SPECIFIC POPULATIONS
8.1 Pregnancy
Risk Summary
Available pharmacovigilance data have not established an association with insulin glulisine use during pregnancy and major birth defects, miscarriage or adverse maternal or fetal outcomes. There are risks to the mother and fetus associated with poorly controlled diabetes in pregnancy (see Clinical Considerations). Animal reproduction studies have been conducted with insulin glulisine in rats and rabbits using regular human insulin as a comparator. Insulin glulisine was given to female rats throughout pregnancy at subcutaneous doses up to 10 units/kg/day (2 times the average human dose, based on body surface area comparison) and to rabbits during organogenesis at subcutaneous doses up to 1.5 units/kg/day (0.5 times the average human dose, based on body surface area comparison). The effects did not differ from those observed with subcutaneous regular human insulin (see Data).
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. The estimated background risk of major birth defects is 6% to 10% in women with pre-gestational diabetes with a peri-conceptional HbA1c >7 and has been reported to be as high as 20% to 25% in women with a peri-conceptional HbA1c >10. The estimated background risk of miscarriage for the indicated population is unknown.
Clinical Considerations
Disease-associated maternal and/or embryo-fetal risk
Hypoglycemia and hyperglycemia occur more frequently during pregnancy in patients with pre-gestational diabetes. Poorly controlled diabetes in pregnancy increases the maternal risk for diabetic ketoacidosis, pre-eclampsia, spontaneous abortions, preterm delivery, and delivery complications. Poorly controlled diabetes increases the fetal risk for major birth defects, still birth, and macrosomia-related morbidity.
Data
Animal data
Insulin glulisine was given to pregnant female rabbits during gestation at doses up to 1.5 units/kg/day, resulting in an exposure 0.5 times the average human dose, based on body surface area. Adverse effects on embryo-fetal development, including postimplantation loss and skeletal defects, were observed at dose levels that caused maternal hypoglycemia and mortality.
Insulin glulisine given to pregnant female rats during gestation at doses up to 10 units/kg/day, resulting in an exposure 2 times the average human dose based on body surface area, resulted in maternal toxicity indicative of hypoglycemia but did not adversely affect embryo-fetal development. Postnatal development was not adversely affected following administration of insulin glulisine to pregnant female rats during gestation and throughout lactation at doses up to 8 units/kg/day.
The effects of insulin glulisine did not differ from those observed with regular human insulin used as a comparator in the same studies and administered at the same doses.
8.2 Lactation
Risk Summary
Available data from published literature suggest that human insulin products, including APIDRA, are transferred into human milk. There are no adverse reactions reported in the breastfed infants in the literature. There are no data on the effects of exogenous human insulin products, including APIDRA, on milk production. The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for APIDRA and any potential adverse effects on the breastfed infant from APIDRA or from the underlying maternal condition.
8.4 Pediatric Use
The safety and effectiveness of APIDRA to improve glycemic control have been established in pediatric patients. Use of APIDRA for this indication is supported by evidence from an active-controlled non-inferiority study in pediatric patients 4 years of age and older with type 1 diabetes mellitus treated with APIDRA (n=271) and from studies in adults with diabetes mellitus [see Clinical Pharmacology (12.3), and Clinical Studies (14)].
In the clinical trials, pediatric patients with type 1 diabetes mellitus had a higher incidence of severe symptomatic hypoglycemia in the two treatment groups compared to adults with type 1 diabetes mellitus [see Adverse Reactions (6.1)].
8.5 Geriatric Use
In clinical trials, APIDRA was administered to 147 patients ≥65 years of age and 27 patients ≥75 years of age. The majority of this small subset of geriatric patients had type 2 diabetes. The change in HbA1c values and hypoglycemia frequencies did not differ by age.
Nevertheless, caution should be exercised when APIDRA is administered to geriatric patients. In geriatric patients with diabetes, the initial dosing, dose increments, and maintenance dosage should be conservative to reduce the risk of hypoglycemia [see Warnings and Precautions (5.3)].
8.6 Renal Impairment
Patients with renal impairment may be at increased risk of hypoglycemia and may require more frequent APIDRA dose adjustment and more frequent blood glucose monitoring [see Warnings and Precautions (5.3) and Clinical Pharmacology (12.3)].
8.7 Hepatic Impairment
Patients with hepatic impairment may be at increased risk of hypoglycemia and may require more frequent APIDRA dose adjustment and more frequent blood glucose monitoring [see Warnings and Precautions (5.3) and Clinical Pharmacology (12.3)].
10 OVERDOSAGE
Excess insulin may cause hypoglycemia and, particularly when given intravenously, hypokalemia. Mild episodes of hypoglycemia usually can be treated with oral glucose. Adjustments in drug dosage, meal patterns, or exercise may be needed. More severe episodes of hypoglycemia with coma, seizure, or neurologic impairment may be treated with a glucagon product for emergency use or concentrated intravenous glucose. Sustained carbohydrate intake and observation may be necessary because hypoglycemia may recur after apparent clinical recovery. Hypokalemia must be corrected appropriately.
11 DESCRIPTION
Insulin glulisine is a rapid-acting human insulin analog used to lower blood glucose. Insulin glulisine is produced by recombinant DNA technology utilizing a non-pathogenic laboratory strain of Escherichia coli (K12). Insulin glulisine differs from human insulin in that the amino acid asparagine at position B3 is replaced by lysine and the lysine in position B29 is replaced by glutamic acid. Insulin glulisine has a molecular weight of 5.823 kDa.
APIDRA (insulin glulisine) injection is a sterile, aqueous, clear, and colorless solution for subcutaneous or intravenous use. Each milliliter of APIDRA contains 100 units insulin glulisine, metacresol (3.15 mg), polysorbate 20 (0.01 mg), sodium chloride (5 mg), tromethamine (6 mg), and water for injection. APIDRA has a pH of approximately 7.3. The pH is adjusted by addition of aqueous solutions of hydrochloric acid and/or sodium hydroxide.
12 CLINICAL PHARMACOLOGY
12.1 Mechanism of Action
Regulation of glucose metabolism is the primary activity of insulins and insulin analogs, including insulin glulisine. Insulins lower blood glucose by stimulating peripheral glucose uptake by skeletal muscle and fat, and by inhibiting hepatic glucose production. Insulins inhibit lipolysis and proteolysis and enhance protein synthesis.
12.2 Pharmacodynamics
Studies in healthy volunteers and patients with diabetes demonstrated that APIDRA has a more rapid onset of action and a shorter duration of activity than regular human insulin when given subcutaneously.
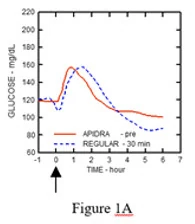
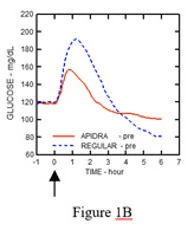
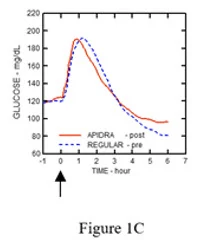
In a study in patients with type 1 diabetes (n=20), the glucose-lowering profiles of APIDRA and regular human insulin were assessed at various times in relation to a standard meal at a dose of 0.15 units/kg (see Figure 1).
The maximum blood glucose excursion (ΔGLUmax; baseline subtracted glucose concentration) for APIDRA injected 2 minutes before a meal was 65 mg/dL compared to 64 mg/dL for regular human insulin injected 30 minutes before a meal (see Figure 1A), and 84 mg/dL for regular human insulin injected 2 minutes before a meal (see Figure 1B). The maximum blood glucose excursion for APIDRA injected 15 minutes after the start of a meal was 85 mg/dL compared to 84 mg/dL for regular human insulin injected 2 minutes before a meal (see Figure 1C).
Figure 1: Serial mean blood glucose collected up to 6 hours following a single dose of APIDRA and regular human insulin. APIDRA given 2 minutes (APIDRA - pre) before the start of a meal compared to regular human insulin given 30 minutes (Regular - 30 min) before start of the meal (see Figure 1A) and compared to regular human insulin (Regular - pre) given 2 minutes before a meal (see Figure 1B). APIDRA given 15 minutes (APIDRA - post) after start of a meal compared to regular human insulin (Regular - pre) given 2 minutes before a meal (see Figure 1C). On the x-axis, zero (0) is the start of a 15-minute meal.
 |  |
 |  |
In a randomized, open-label, two-way crossover study, 16 healthy male subjects received an intravenous infusion of APIDRA or regular human insulin with saline diluent at a rate of 0.8 milliunits/kg/min for two hours. Infusion of the same dose of APIDRA or regular human insulin produced equivalent glucose disposal at steady state.
12.3 Pharmacokinetics
Absorption and Bioavailability
Pharmacokinetic profiles in healthy volunteers and patients with diabetes (type 1 or type 2) demonstrated that absorption of insulin glulisine was faster than that of regular human insulin.
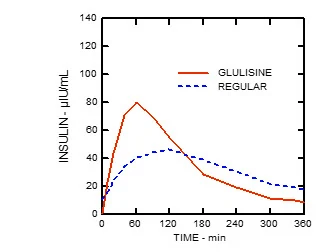
In a study in patients with type 1 diabetes (n=20) after subcutaneous administration of 0.15 units/kg, the median time to maximum concentration (Tmax) was 60 minutes (range 40 to 120 minutes) and the peak concentration (Cmax) was 83 microunits/mL (range 40 to 131 microunits/mL) for insulin glulisine compared to a median Tmax of 120 minutes (range 60 to 239 minutes) and a Cmax of 50 microunits/mL (range 35 to 71 microunits/mL) for regular human insulin (see Figure 2).
Figure 2: Pharmacokinetic Profiles of Insulin Glulisine and Regular Human Insulin in Patients with Type 1 Diabetes after a Dose of 0.15 units/kg.
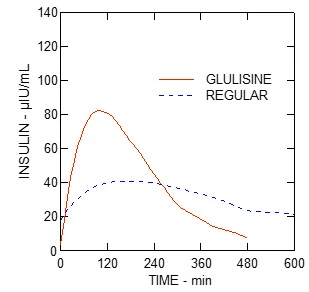
Insulin glulisine and regular human insulin were administered subcutaneously at a dose of 0.2 units/kg in a euglycemic clamp study in patients with type 2 diabetes (n=24) and a body mass index (BMI) between 20 and 36 kg/m2. The median time to maximum concentration (Tmax) was 100 minutes (range 40 to 120 minutes) and the median peak concentration (Cmax) was 84 microunits/mL (range 53 to 165 microunits/mL) for insulin glulisine compared to a median Tmax of 240 minutes (range 80 to 360 minutes) and a median Cmax of 41 microunits/mL (range 33 to 61 microunits/mL) for regular human insulin (see Figure 3).
Figure 3: Pharmacokinetic Profiles of Insulin Glulisine and Regular Human Insulin in Patients with Type 2 Diabetes after a Subcutaneous Dose of 0.2 units/kg.
When APIDRA was injected subcutaneously into different areas of the body, the time-concentration profiles were similar. The absolute bioavailability of insulin glulisine after subcutaneous administration is approximately 70%, regardless of injection area (abdomen 73%, deltoid 71%, thigh 68%).
In a clinical study in healthy volunteers (n=32) the total insulin glulisine bioavailability was similar after subcutaneous injection of insulin glulisine and NPH insulin (premixed in the syringe) and following separate simultaneous subcutaneous injections. There was 27% attenuation of the maximum concentration (Cmax) of APIDRA after premixing; however, the time to maximum concentration (Tmax) was not affected.
Distribution and Elimination
The distribution and elimination of insulin glulisine and regular human insulin after intravenous administration are similar with volumes of distribution of 13 and 21 L and half-lives of 13 and 17 minutes, respectively. After subcutaneous administration, insulin glulisine is eliminated more rapidly than regular human insulin with an apparent half-life of 42 minutes compared to 86 minutes.
Specific Populations
Pediatric patients
The pharmacokinetic and pharmacodynamic properties of APIDRA and regular human insulin were assessed in a study conducted in pediatric patients 7 to 11 years old (n=10) and 12 to 16 years old (n=10) with type 1 diabetes. The relative differences in pharmacokinetics and pharmacodynamics between APIDRA and regular human insulin in these patients with type 1 diabetes were similar to those in healthy adult subjects and adults with type 1 diabetes.
Race
A study in 24 healthy Caucasians and Japanese subjects compared the pharmacokinetics and pharmacodynamics after subcutaneous injection of insulin glulisine, insulin lispro, and regular human insulin. With subcutaneous injection of insulin glulisine, Japanese subjects had a greater initial exposure (33%) for the ratio of AUC(0–1h) to AUC(0–clamp end) than Caucasians (21%) although the total exposures were similar. There were similar findings with insulin lispro and regular human insulin.
Obesity
Insulin glulisine and regular human insulin were administered subcutaneously at a dose of 0.3 units/kg in a euglycemic clamp study in obese, non-diabetic subjects (n=18) with a body mass index (BMI) between 30 and 40 kg/m2. The median time to maximum concentration (Tmax) was 85 minutes (range 49 to 150 minutes) and the median peak concentration (Cmax) was 192 microunits/mL (range 98 to 380 microunits/mL) for insulin glulisine compared to a median Tmax of 150 minutes (range 90 to 240 minutes) and a median Cmax of 86 microunits/mL (range 43 to 175 microunits/mL) for regular human insulin.
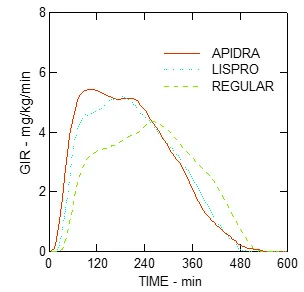
The more rapid onset of action and shorter duration of activity of APIDRA and insulin lispro compared to regular human insulin were maintained in an obese non-diabetic population (n=18) (see Figure 4).
Figure 4: Glucose Infusion Rates (GIR) in a Euglycemic Clamp Study after Subcutaneous Injection of 0.3 units/kg of APIDRA, Insulin Lispro or Regular Human Insulin in an Obese Population.
Renal impairment
Studies with human insulin have shown increased circulating levels of insulin in patients with renal failure. In a study performed in 24 non-diabetic subjects with normal renal function (ClCr >80 mL/min), moderate renal impairment (30–50 mL/min), and severe renal impairment (<30 mL/min), the subjects with moderate and severe renal impairment had increased exposure to insulin glulisine by 29% to 40% and reduced clearance of insulin glulisine by 20% to 25% compared to subjects with normal renal function [see Use in Specific Populations (8.6)].
Hepatic impairment
The effect of hepatic impairment on the pharmacokinetics and pharmacodynamics of APIDRA has not been studied. Some studies with human insulin have shown increased circulating levels of insulin in patients with liver failure [see Use in Specific Populations (8.7)].
Gender
The effect of gender on the pharmacokinetics and pharmacodynamics of APIDRA has not been studied.
Smoking
The effect of smoking on the pharmacokinetics and pharmacodynamics of APIDRA has not been studied.
13 NONCLINICAL TOXICOLOGY
13.1 Carcinogenesis, Mutagenesis, Impairment of Fertility
Long-term carcinogenicity studies in animals have not been performed. In Sprague Dawley rats, a 12-month study was conducted with insulin glulisine at subcutaneous doses of 2.5, 5, 20 or 50 units/kg administered twice daily, resulting in an exposure 1, 2, 8, and 20 times the average human dose, based on body surface area.
There was a non-dose dependent higher incidence of mammary gland tumors in female rats administered insulin glulisine compared to untreated controls. The incidence of mammary tumors for insulin glulisine and regular human insulin was similar. Insulin glulisine was not mutagenic in the following tests: Ames test, in vitro mammalian chromosome aberration test in V79 Chinese hamster cells, and in vivo mammalian erythrocyte micronucleus test in rats.
In fertility studies in male and female rats at subcutaneous doses up to 10 units/kg/day (2 times the average human dose, based on body surface area comparison), no clear adverse effects on male and female fertility, or general reproductive performance of animals were observed.
14 CLINICAL STUDIES
The safety and efficacy of APIDRA were studied in adult patients with type 1 and type 2 diabetes (n=1833) and in pediatric patients (4 to 17 years) with type 1 diabetes (n=572). The primary efficacy parameter in these trials was glycemic control, assessed using glycated hemoglobin (GHb reported as HbA1c equivalent).
14.1 Type 1 Diabetes-Adults
A 26-week, randomized, open-label, active-controlled, non-inferiority study was conducted in patients with type 1 diabetes to assess the safety and efficacy of APIDRA (n=339) compared to insulin lispro (n=333) when administered subcutaneously within 15 minutes before a meal. Insulin glargine was administered once daily in the evening as the basal insulin. There was a 4-week run-in period with insulin lispro and insulin glargine prior to randomization. Most patients were Caucasian (97%). Fifty-eight percent of the patients were men. The mean age was 39 years (range 18 to 74 years). Glycemic control, the number of daily short-acting insulin injections and the total daily doses of APIDRA and insulin lispro were similar in the two treatment groups (see Table 7).
Table 7: Type 1 Diabetes Mellitus–Adult
Treatment duration Treatment in combination with: | 26 weeks Insulin glargine | |
|---|---|---|
| APIDRA | Insulin Lispro | |
Glycated hemoglobin (GHb)GHb reported as HbA1c equivalent (%) Number of patients | 331 | 322 |
| Baseline mean | 7.6 | 7.6 |
| Adjusted mean change from baseline | -0.1 | -0.1 |
| Treatment difference: APIDRA – Insulin Lispro | 0.0 | |
| 95% CI for treatment difference | (-0.1; 0.1) | |
| Basal insulin dose (Units/day) | ||
| Baseline mean | 24 | 24 |
| Adjusted mean change from baseline | 0 | 2 |
| Short-acting insulin dose (Units/day) | ||
| Baseline mean | 30 | 31 |
| Adjusted mean change from baseline | -1 | -1 |
| Mean number of short-acting insulin injections per day | 3 | 3 |
| Body weight (kg) | ||
| Baseline mean | 73.9 | 74.1 |
| Mean change from baseline | 0.6 | 0.3 |
14.2 Type 2 Diabetes-Adults
A 26-week, randomized, open-label, active-controlled, non-inferiority study was conducted in insulin-treated patients with type 2 diabetes to assess the safety and efficacy of APIDRA (n=435) given within 15 minutes before a meal compared to regular human insulin (n=441) administered 30 to 45 minutes prior to a meal. NPH human insulin was given twice a day as the basal insulin. All patients participated in a 4-week run-in period with regular human insulin and NPH human insulin. Eighty-five percent of patients were Caucasian and 11% were Black. The mean age was 58 years (range 26 to 84 years). The average body mass index (BMI) was 34.6 kg/m2. At randomization, 58% of the patients were taking an oral antidiabetic agent. These patients were instructed to continue use of their oral antidiabetic agent at the same dose throughout the trial. The majority of patients (79%) mixed their short-acting insulin with NPH human insulin immediately prior to injection. The reductions from baseline in GHb were similar between the 2 treatment groups (see Table 8). No differences between APIDRA and regular human insulin groups were seen in the number of daily short-acting insulin injections or basal or short-acting insulin doses (see Table 8).
Table 8: Type 2 Diabetes Mellitus–Adult
Treatment duration Treatment in combination with: | 26 weeks NPH human insulin | |
|---|---|---|
| APIDRA | Regular Human Insulin | |
Glycated hemoglobin (GHb)GHb reported as HbA1c equivalent (%) Number of patients | 404 | 403 |
| Baseline mean | 7.6 | 7.5 |
| Adjusted mean change from baseline | -0.5 | -0.3 |
| Treatment difference: APIDRA – Regular Human Insulin | -0.2 | |
| 95% CI for treatment difference | (-0.3; -0.1) | |
| Basal insulin dose (Units/day) | ||
| Baseline mean | 59 | 57 |
| Adjusted mean change from baseline | 6 | 6 |
| Short-acting insulin dose (Units/day) | ||
| Baseline mean | 32 | 31 |
| Adjusted mean change from baseline | 4 | 5 |
| Mean number of short-acting insulin injections per day | 2 | 2 |
| Body weight (kg) | ||
| Baseline mean | 100.5 | 99.2 |
| Mean change from baseline | 1.8 | 2.0 |
14.3 Type 1 Diabetes-Adults: Pre and Postmeal Administration
A 12-week, randomized, open-label, active-controlled, non-inferiority study was conducted in patients with type 1 diabetes to assess the safety and efficacy of APIDRA administered at different times with respect to a meal. APIDRA was administered subcutaneously either within 15 minutes before a meal (n=286) or immediately after a meal (n=296) and regular human insulin (n=278) was administered subcutaneously 30 to 45 minutes prior to a meal. Insulin glargine was administered once daily at bedtime as the basal insulin. There was a 4-week run-in period with regular human insulin and insulin glargine followed by randomization. Most patients were Caucasian (94%). The mean age was 40 years (range 18 to 73 years). Glycemic control (see Table 9) was comparable for the 3 treatment regimens. No changes from baseline between the treatments were seen in the total daily number of short-acting insulin injections (see Table 9).
Table 9: Pre and Postmeal Administration in Type 1 Diabetes Mellitus–Adult
Treatment duration Treatment in combination with: | 12 weeks insulin glargine | 12 weeks insulin glargine | 12 weeks insulin glargine |
|---|---|---|---|
APIDRA pre meal | APIDRA post meal | Regular Human Insulin | |
Glycated hemoglobin (GHb)GHb reported as HbA1c equivalent (%) Number of patients | 268 | 276 | 257 |
| Baseline mean | 7.7 | 7.7 | 7.6 |
Adjusted mean change from baselineAdjusted mean change from baseline treatment difference (98.33% CI for treatment difference): APIDRA pre meal vs Regular Human Insulin -0.1 (-0.3; 0.0) APIDRA post meal vs Regular Human Insulin 0.0 (-0.1; 0.2) APIDRA post meal vs pre meal 0.2 (0.0; 0.3) | -0.3 | -0.1 | -0.1 |
| Basal insulin dose (Units/day) | |||
| Baseline mean | 29 | 29 | 28 |
| Adjusted mean change from baseline | 1 | 0 | 1 |
| Short-acting insulin dose (Units/day) | |||
| Baseline mean | 29 | 29 | 27 |
| Adjusted mean change from baseline | -1 | -1 | 2 |
| Mean number of short-acting insulin injections per day | 3 | 3 | 3 |
| Body weight (kg) | |||
| Baseline mean | 79.2 | 80.3 | 78.9 |
| Mean change from baseline | 0.3 | -0.3 | 0.3 |
14.4 Type 1 Diabetes-Pediatric Patients
A 26-week, randomized, open-label, active-controlled, non-inferiority study was conducted in children and adolescents older than 4 years of age with type 1 diabetes mellitus to assess the safety and efficacy of APIDRA (n=277) compared to insulin lispro (n=295) when administered subcutaneously within 15 minutes before a meal. Patients also received insulin glargine (administered once daily in the evening) or NPH insulin (administered once in the morning and once in the evening). There was a 4-week run-in period with insulin lispro and insulin glargine or NPH prior to randomization. Most patients were Caucasian (91%). Fifty percent of the patients were male. The mean age was 12.5 years (range 4 to 17 years). Mean BMI was 20.6 kg/m2. Glycemic control (see Table 10) was comparable for the two treatment regimens.
Table 10: Results from a 26-Week Study in Pediatric Patients with Type 1 Diabetes Mellitus
| APIDRA | Insulin Lispro | |
|---|---|---|
| Number of patients | 271 | 291 |
| Basal Insulin | NPH or insulin glargine | NPH or insulin glargine |
| Glycated hemoglobin (GHb)GHb reported as HbA1c equivalent (%) | ||
| Baseline mean | 8.2 | 8.2 |
| Adjusted mean change from baseline | 0.1 | 0.2 |
| Treatment Difference: Mean (95% confidence interval) | -0.1 (-0.2, 0.1) | |
| Basal insulin dose (Units/kg/day) | ||
| Baseline mean | 0.5 | 0.5 |
| Mean change from baseline | 0.0 | 0.0 |
| Short-acting insulin dose (Units/kg/day) | ||
| Baseline mean | 0.5 | 0.5 |
| Mean change from baseline | 0.0 | 0.0 |
| Mean number of short-acting insulin injections per day | 3 | 3 |
Baseline mean body weight (kg) Mean weight change from baseline (kg) | 51.5 2.2 | 50.8 2.2 |
14.5 Type 1 Diabetes-Adults: Continuous Subcutaneous Insulin Infusion
A 12-week randomized, active control study (APIDRA versus insulin aspart) conducted in adults with type 1 diabetes (APIDRA n=29, insulin aspart n=30) evaluated the use of APIDRA in an external continuous subcutaneous insulin pump. All patients were Caucasian. The mean age was 46 years (range 21 to 73 years). The mean GHb increased from baseline to endpoint in both treatment groups (from 6.8% to 7.0% for APIDRA; from 7.1% to 7.2% for insulin aspart).
16 HOW SUPPLIED/STORAGE AND HANDLING
16.1 How Supplied
APIDRA injection, 100 units/mL (U-100), is a clear and colorless solution available as:
| APIDRA | NDC number | Package size |
|---|---|---|
| 10 mL multiple-dose vial | 0088-2500-33 | 1 vial per carton |
| 3 mL single-patient-use APIDRA SoloStar prefilled pen | 0088-2502-05 | 5 pens per carton |
Pen needles are not included in the packs.
SoloStar is compatible with all pen needles from Becton Dickinson and Company, Ypsomed, and Owen Mumford.
The APIDRA SoloStar prefilled pen dials in 1-unit increments.
16.2 Storage
Dispense in the original sealed carton with the enclosed Instructions for Use. Do not freeze.
Do not use after the expiration date (see carton and container).
Storage conditions are summarized in the following table:
Not in-use (unopened) Refrigerated (36°F-46°F [2°C-8°C]). Protect from light | Not in-use (unopened) Room Temperature (up to 77°F [25°C]) | In-use (opened) (See temperature below) | |
|---|---|---|---|
| 10 mL multiple-dose vial | Until expiration date | 28 days | 28 daysThe in-use time for multiple-dose vial is either 28 days at room temperature up to 77°F (25°C) or 48 hours in insulin pump up to 98.6°F (37°C)., Refrigerated or room temperature |
| 3 mL single-patient-use APIDRA SoloStar prefilled pen | Until expiration date | 28 days | 28 days, Room temperature (Do not refrigerate) |
Use in an External Insulin Pump
Change the APIDRA in the pump reservoir at least every 48 hours, or according to the pump user manual, whichever is shorter, or after exposure to temperatures that exceed 98.6°F (37°C).
Intravenous Use
Diluted APIDRA in infusion bags in normal saline solution (0.9% Sodium Chloride Injection, USP) are stable at room temperature for 48 hours [see Dosage and Administration (2.2)].
17 PATIENT COUNSELING INFORMATION
Advise the patient to read the FDA-approved patient labeling (Patient Information and Instructions for Use).
Never Share an APIDRA SoloStar Pen or Syringe or Needle between Patients
Advise patients that they must never share an APIDRA SoloStar pen with another person, even if the needle is changed. Advise patients using APIDRA vials not to reuse or share needles or syringes with another person. Sharing carries a risk for transmission of blood-borne pathogens [see Warnings and Precautions (5.1)].
Hyperglycemia or Hypoglycemia
Inform patients that hypoglycemia is the most common adverse reaction with insulin. Instruct patients on self-management procedures including glucose monitoring, proper injection technique, and management of hypoglycemia and hyperglycemia, especially at initiation of APIDRA therapy. Instruct patients on handling of special situations such as intercurrent conditions (illness, stress, or emotional disturbances), an inadequate or skipped insulin dose, inadvertent administration of an increased insulin dose, inadequate food intake, and skipped meals. Instruct patients on the management of hypoglycemia [see Warnings and Precautions (5.3)].
Inform patients that their ability to concentrate and react may be impaired as a result of hypoglycemia. Advise patients who have frequent hypoglycemia or reduced or absent warning signs of hypoglycemia to use caution when driving or operating machinery.
Advise patients that changes in insulin regimen can predispose to hyperglycemia or hypoglycemia and that changes in insulin regimen should be made under close medical supervision [see Warnings and Precautions (5.2)].
Hypoglycemia due to Medication Errors
Instruct patients to always check the insulin label before each injection to avoid mix-ups between insulin products [see Warnings and Precautions (5.4)].
Hypersensitivity Reactions
Advise patients that hypersensitivity reactions have occurred with APIDRA. Inform patients on the symptoms of hypersensitivity reactions and to seek medical attention if they occur [see Warnings and Precautions (5.6)].
Instructions For Patients Using Continuous Subcutaneous Insulin Pumps
- Train patients in intensive insulin therapy with multiple injections and in the function of their pump and pump accessories.
- Instruct patients to follow healthcare provider recommendations when setting pump basal rates and bolus settings.
- Refer to the continuous subcutaneous infusion pump user manual to see if APIDRA can be used with the pump. See recommended reservoir and infusion sets in the insulin pump user manual.
- Instruct patients to replace APIDRA in the reservoir at least every 48 hours, or according to the pump user manual, whichever is shorter. By following this schedule, patients avoid insulin degradation, infusion set occlusion, and loss of the insulin preservative.
- Instruct patients that infusion sets and infusion set insertion sites should be changed according to the manufacturer's user manual.
- Instruct patients to discard insulin exposed to temperatures higher than 98.6°F (37°C). The temperature of the insulin may exceed ambient temperature when the pump housing, cover, tubing, or sport case is exposed to sunlight or radiant heat.
- Instruct patients to inform healthcare provider and select a new site for infusion if infusion site becomes erythematous, pruritic, or thickened.
- Instruct patients on the risk of rapid hyperglycemia and ketosis due to pump malfunction; infusion set occlusion, leakage, disconnection, or kinking; and degraded insulin. Instruct patients on the risk of hypoglycemia from pump malfunction. If these problems cannot be promptly corrected, instruct patients to resume therapy with subcutaneous insulin injection and contact their healthcare provider [see Warnings and Precautions (5) and How Supplied/Storage and Handling (16.2)].
Manufactured by:
sanofi-aventis U.S. LLC
Morristown, NJ 07960
A SANOFI COMPANY
U.S. License No. 1752
©2025 sanofi-aventis U.S. LLC
Other brands listed are the registered trademarks of their respective owners and are not trademarks of sanofi-aventis U.S. LLC